Tag Archive for: Prostate cancer screening

Movember and the digital rectal examination: does it still matter?

The digital rectal examination (DRE) has been part of prostate assessment for generations. It is also one of the tests men are most likely to dread, joke about, or avoid. As Movember prompts conversations about prostate health, it is worth asking what a DRE can actually tell us today and when it is useful.

The short answer: a DRE still has a place in clinical assessment, but it is not recommended as a routine add-on to PSA testing for every asymptomatic man. PSA blood testing is the main early-detection test. A DRE can add physical information in selected situations, and it remains one part of monitoring some men with known prostate cancer.

What is a DRE?

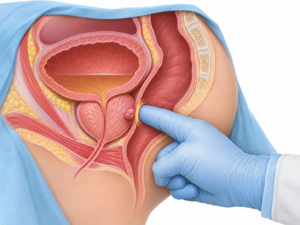
A DRE is a brief examination in which a clinician gently inserts a gloved, lubricated finger into the rectum to feel the back surface of the prostate. The clinician assesses features such as the prostate’s size, shape, firmness, symmetry and any distinct lump or irregular area. It may also give information about tenderness or other rectal findings.

The prostate sits in front of the rectum, so the examination can only feel part of the gland. It cannot reliably assess the whole prostate, and some cancers, particularly those in areas that cannot be reached by touch, may not be felt. A normal DRE therefore does not rule out prostate cancer.
What extra information can it provide?

PSA is a blood marker produced by prostate tissue. It helps estimate risk, but PSA alone does not show where a possible cancer is or how the prostate feels. A DRE gives the clinician a physical finding to interpret alongside the PSA result, symptoms, family history and, when indicated, MRI and biopsy.

A firm nodule, marked asymmetry, or an unusually hard or fixed-feeling area can increase concern and prompt further assessment, even if the PSA is not markedly raised. An abnormal DRE may also help estimate the clinical extent of a cancer and its likelihood of being more significant. But it is not a cancer diagnosis: benign enlargement, inflammation and examiner variation can affect what is felt. A suspicious finding usually needs further assessment, often including MRI and possibly biopsy.

DRE is not a substitute for PSA, MRI or biopsy. Nor does a normal examination provide a guarantee that cancer is absent.

Can it find cancers that produce little PSA?

Occasionally, prostate cancer is found after a suspicious DRE even when PSA is low. Some uncommon or poorly differentiated cancers can produce less PSA than expected. In the 2026 European Association of Urology guideline, a suspicious DRE with PSA at or below 4 ng/mL was associated with a positive predictive value ranging widely from 5% to 30% in the cited evidence. This shows why a distinctly abnormal examination should not automatically be dismissed because of a reassuring PSA.

That does not mean DRE is a dependable way to screen for low-PSA cancers. Many cancers cannot be felt, and DRE’s performance as a stand-alone screening test is limited. If symptoms, imaging or other clinical features raise concern, the clinician should consider the full picture rather than rely on either a normal PSA or a normal DRE alone.

Should every man having a PSA test also have a DRE?

No. The NHMRC-approved 2026 Guidelines for the Early Detection of Prostate Cancer in Australia suggest that DRE not be offered in primary care as a routine addition to PSA testing and risk assessment for asymptomatic men. The RACGP Red Book also advises against routine DRE as an addition to PSA testing in asymptomatic men seeking early detection.

This reflects evidence that routine DRE adds little to population early-detection pathways compared with PSA-based assessment, while it can create discomfort and deter some men from discussing testing. PSA testing itself is a choice to make after discussing potential benefits and harms with a GP; it is not an automatic test for everyone.

A DRE may still be appropriate when a person has symptoms, a concerning PSA result, an abnormality on imaging, or another clinical reason for a physical examination. A clinician should explain why it may help in that specific situation and discuss alternatives where appropriate.

What about men already on active surveillance?

Active surveillance is a monitoring approach for selected men with lower-risk prostate cancer, intended to identify evidence of meaningful change while avoiding or delaying treatment side effects when it is safe to do so.

The 2026 Australian guideline proposes periodic DRE alongside PSA measurements, MRI where appropriate and repeat biopsy when clinically indicated. A change in the examination may be one reason to bring forward MRI or biopsy. It is not, by itself, usually enough to decide that treatment should start. The European Association of Urology also includes DRE in surveillance protocols, while recognising that its frequency may be reduced in selected men with stable MRI and other reassuring findings. Monitoring plans vary with the cancer’s features, prior tests and the person’s circumstances.

Why is the DRE so famous, and why are some men apprehensive?

For many years, before PSA testing and prostate MRI were available, clinicians had fewer ways to assess the prostate. The DRE was a quick bedside examination that could identify a large or locally advanced abnormality. It became closely associated with “getting your prostate checked,” and popular culture has kept it in the spotlight.

When I discuss it with patients, I sometimes call DRE the “dreaded rectal examination” a little wordplay that can break the ice. It acknowledges the test’s reputation, but it is not a request to grin and bear it: I explain what I’m doing, ask permission, and stop if you ask.

The examination can feel intimate or embarrassing. Some men worry it will hurt, feel exposed, or be judged. Others have heard jokes that link the test to masculinity or sexuality. These concerns are understandable, but a DRE is a clinical examination; it says nothing about a person’s identity or sexuality. Many people find it awkward or uncomfortable rather than painful, although experiences differ.

You can ask the clinician to explain each step before starting, request a chaperone, discuss positioning, and ask them to stop at any time. Consent matters. You do not need to agree to an examination simply because you have come to talk about PSA testing.

What should I do this Movember?

If you are thinking about prostate testing, speak with your GP about your age, family history, health and preferences. Ask whether PSA testing is suitable for you and whether an examination would add useful information in your circumstances. If you have urinary symptoms, blood in your urine or semen, persistent unexplained pain, or another concern, arrange an assessment rather than waiting for a routine screening test.

Movember is a chance to make the conversation easier. The aim is not to insist that every man must have a DRE. It is to help each person understand the available tests, feel able to ask questions, and make an informed decision with their clinician.

This article provides general information and is not a substitute for personal medical advice.

References and further information

  1. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia. NHMRC-approved recommendations, 18 May 2026. See Recommendations 4.1 and 8.2.1.
  2. The Royal Australian College of General Practitioners. Guidelines for preventive activities in general practice, 10th edition — prostate cancer. Recommendations updated 28 June 2024.
  3. European Association of Urology. EAU Guidelines on Prostate Cancer: Diagnostic Evaluation, 2026 edition.
  4. European Association of Urology. EAU Guidelines on Prostate Cancer: Treatment and active-surveillance follow-up, 2026 edition.
  5. Sajjad W, et al. Comparing the Performance of Digital Rectal Examination and Prostate-specific Antigen as a Screening Test for Prostate Cancer: A Systematic Review and Meta-analysis. European Urology Oncology. 2024. PubMed.


Movember: PSA testing: what it can tell you, and what it can’t

An informed conversation with your GP can help you decide whether a PSA test is right for you. Your age, family history, general health and preferences all matter.

Movember is a good time to talk about men’s health, including prostate cancer. One of the most useful steps is often a simple conversation with your GP about prostate-specific antigen (PSA) testing. A PSA blood test can help identify men who may need further assessment, but it is not a yes-or-no cancer test. Understanding what it can and cannot show helps you make an informed choice.

What is PSA?

PSA is a protein made by cells in the prostate. A small amount normally enters the bloodstream, where it can be measured with a blood test. PSA is prostate-specific, but not cancer-specific: a higher result can occur with prostate cancer, but also with benign prostate enlargement, inflammation or infection, urinary retention, or after some urinary procedures. PSA levels also tend to rise with age.

A PSA test is different from a digital rectal examination (DRE). The blood test measures PSA. A DRE is an examination in which a clinician feels the prostate through the rectum. A DRE is not routinely required as an addition to PSA testing for an asymptomatic man under RACGP guidance, although examination may be useful when symptoms or other findings make it appropriate.

Why do we use PSA?

Prostate cancer may cause no symptoms in its early stages. PSA testing can identify a result that deserves a closer look before symptoms develop. Used thoughtfully, early detection may help find clinically significant cancer while treatment or monitoring options remain available.

There are limits and possible harms. PSA can be raised when cancer is not present, leading to anxiety, repeat tests, scans and sometimes biopsy. It can also find a slow-growing cancer that would never have caused a problem during a person’s lifetime. Diagnosis and treatment can have side effects, including changes to urinary continence and sexual function. The chance of benefit depends on a person’s risk, health and life expectancy. That is why Australian guidance recommends an informed discussion before testing rather than testing everyone automatically.

Is PSA a good marker for prostate disease or prostate cancer?

PSA is a useful risk marker, not a diagnosis. It can help estimate the chance of prostate cancer and guide whether further assessment is sensible. It is not a reliable general test for every prostate problem, and it cannot by itself distinguish cancer from benign enlargement or inflammation.

A low PSA lowers the chance of prostate cancer but does not make it zero. A raised PSA does not mean that cancer is present. If the result is higher than expected for a person’s age and risk, the GP will usually consider the whole picture and repeat the test before acting on a single result. Infection, inflammation, retention and recent instrumentation can affect the result, so timing and clinical context matter.

If PSA remains elevated, further assessment may include a clinical review, examination when appropriate, and prostate MRI. Current Australian guidance recommends multiparametric MRI before biopsy. A biopsy, when indicated, is what confirms whether cancer is present and provides information about its grade. Not everyone with a raised PSA needs a biopsy.

How often should PSA be tested?

Australia’s guidance has evolved. The RACGP’s Guidelines for preventive activities in general practice (Red Book, 10th edition, 2024) recommends offering informed men at average risk aged 50–69 PSA testing every two years if they choose regular testing. It recommends testing every two years from age 45 for men at moderately increased risk because of family history, and from age 40 for those at high risk due to family history, through age 69.

USANZ’s published PSA position statement is described as an interim document pending updates to the PCFA and RACGP guidelines. It supports an individualised, risk-based discussion for well-informed men over 50 with an adequate life expectancy, earlier testing from over 45 for men with a family history or higher-risk ethnicity, and from over 40 for men with a BRCA2 mutation.

Since those documents, the NHMRC approved the 2026 Guidelines for the Early Detection of Prostate Cancer in Australia. These are the latest national recommendations and give the following general pathway for people who decide to test after discussion with their GP:

Age and risk General testing approach
Average risk, age 50–69 Offer PSA testing every two years.
Higher risk, age 45 and over Offer testing every two years, using lower PSA levels to trigger a repeat test and possible referral.
Age 70 and over Individualise the decision. The guideline generally considers testing when estimated life expectancy is more than seven years.
Age 45–49, not at higher risk Routine testing is not recommended; an initial test may be discussed if the person is interested.

The 2026 guideline defines higher risk to include having a brother with prostate cancer; a father diagnosed before age 65; two or more second-degree relatives who died from prostate cancer; Black sub-Saharan ancestry; or a confirmed BRCA2 mutation. Family-history details and other health factors still need to be discussed with a GP. The guideline uses age- and risk-specific PSA action levels; a result at or above an action level is generally repeated within one to three months, rather than treated as a cancer diagnosis.

These recommendations guide discussion; they are not a substitute for individual advice. Screening recommendations apply to people without symptoms. If you have symptoms, your GP may recommend assessment regardless of your age or the usual testing interval.

How important is family history?

Family history can make a real difference. Prostate cancer in a close relative, especially a brother, or a father diagnosed at a younger age, can increase a person’s risk and may mean discussing PSA testing earlier than age 50. Multiple affected relatives can also point to an inherited risk. A known BRCA2 mutation is another important risk factor.

If you know that prostate cancer has affected your family, tell your GP which relative was affected and how old they were when diagnosed. Also mention any known breast, ovarian, pancreatic or other cancers in the family, as these may help the GP decide whether genetic counselling or testing should be discussed. Do not wait for symptoms before raising a strong family history.

When should I see a urologist?

Your GP is usually the right first contact. A referral to a urologist may be appropriate if a repeat PSA remains at or above the age- and risk-based action level, if the prostate examination is concerning, or if MRI or other findings suggest that specialist assessment is needed. A urologist can discuss the benefits and limits of further tests, including MRI and biopsy, and help decide on next steps.

Make an appointment with your GP if you notice persistent or new urinary problems, blood in your urine or semen, or ongoing unexplained pain. These symptoms can have many causes and do not automatically mean prostate cancer, but they deserve assessment. Do not wait for a routine PSA check if you have a concerning symptom. If you cannot pass urine, seek urgent medical care.

A useful Movember conversation

Ask your GP: “Given my age, health and family history, should I have a PSA test? If we test, how often should I repeat it, and what would we do if it is raised?” Knowing your family history and discussing the possible benefits and harms can make the decision more useful than simply ordering a blood test without a plan.

Movember is a reminder to look out for one another. Start the conversation, share what you know about your family history, and encourage the men in your life to seek advice when something does not feel right.

This article provides general information and is not a substitute for personal medical advice. PSA testing is a shared decision between you and your healthcare professional.

References and further information

  1. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia: summary and recommendations. NHMRC approved 18 May 2026.
  2. The Royal Australian College of General Practitioners. Guidelines for preventive activities in general practice, 10th edition — prostate cancer, recommendations updated 28 June 2024.
  3. Urological Society of Australia and New Zealand. PSA Testing position statement. Interim guidance pending updated guidelines.
  4. Huang S, Chen DC, Crowe J, et al. Navigating the shift: New RACGP Red Book guidelines for prostate-specific antigen testing in general practice. Australian Journal of General Practice. 2025;54(12). Article PDF.

Support Movember

Help stop men dying too young: support Movember

Every November, the moustache gives us a reason to start a conversation. But Movember is about much more than facial hair. It brings attention to the health issues that affect men and boys, and supports work in prostate cancer, testicular cancer, mental health and suicide prevention.

I’m raising funds for these causes because they touch the lives of our dads, brothers, sons, partners, friends and mates. A diagnosis, a difficult period with mental health, or the loss of someone to suicide can affect an entire family and community.

Why this matters

You may have seen the message that men die, on average, six years earlier than women. The figure depends on the population and source: Movember’s current Australian campaign reports around four years in Australia and 4.5 years globally. The difference is a reminder that men’s health deserves attention throughout the year, not only when a problem becomes hard to ignore.

Movember focuses on prostate cancer, testicular cancer, mental health and suicide prevention. Donations support programs and research across these areas. The charity also encourages men to look after their health, stay connected and reach out when they need support.

How you can help

If you’re able, please consider making a donation through my Mo Space. Every contribution helps support Movember’s work. Sharing the page or talking about men’s health with someone you care about also helps keep these issues in view.

Donate via my Mo Space:


QR Code


Thank you for supporting this cause: for all the dads, brothers, sons and mates in your life.

Together, we can help stop men dying too young.


Movember’s current information and cause areas: Movember Australia – Our cause and Movember Australia – FAQs.

Prostate cancer, Movember and the moustache: a conversation worth having

Each November, a moustache can do more than change a face. It can open a conversation that might encourage someone to learn their risk, ask about testing or support a person affected by prostate cancer.

Movember is a good time to talk about prostate cancer, but the message matters all year. The aim is not to alarm every man or suggest that everyone needs the same test. It is to make sure people know the facts and can make an informed decision with their doctor.

Prostate cancer in Australia

Prostate cancer is common. The Australian Institute of Health and Welfare (AIHW) estimated that around 29,000 men would be diagnosed in 2025, making it the most commonly diagnosed cancer in Australian men and accounting for about 30% of cancers diagnosed in men that year. These are projected figures, not a final count. Around 1 in 5 men are expected to be diagnosed with prostate cancer during their lifetime.

The outlook is often very good: the AIHW reports a 96% five-year relative survival rate for prostate cancer diagnosed in 2017–2021. That is a population statistic, not a prediction for any one person. Prostate cancers vary: some grow slowly and may never cause harm, while others can be aggressive and need timely treatment. Early assessment can help identify cancers that are more likely to matter, while careful risk assessment helps avoid unnecessary tests and treatment.

What does Movember mean?

Movember began with a simple idea: grow a moustache, raise funds and get people talking about men’s health. It has grown into a global movement supporting men’s health, including prostate cancer, testicular cancer, mental health and physical activity.

The moustache is a friendly, visible conversation starter. Someone may ask, “Why the Mo?” and that gives you a chance to mention prostate cancer, ask a friend whether he knows his family history, or check in with someone who is going through diagnosis or treatment. A moustache cannot detect cancer, and growing one does not replace medical advice. Its value is in helping make a sometimes awkward subject easier to raise.

How is prostate cancer found?

Prostate cancer often causes no symptoms in its early stages. Urinary symptoms such as a weaker stream, needing to urinate more often or difficulty starting are common with ageing and an enlarged prostate, and do not by themselves mean cancer. Blood in the urine or semen, persistent pain, or a new urinary problem should be discussed with a doctor.

The first step in early detection is usually a conversation about personal risk and the possible benefits and downsides of testing. A prostate-specific antigen (PSA) blood test measures a protein made by the prostate. PSA can rise for reasons other than cancer, including prostate enlargement, infection or inflammation. A raised result is not a diagnosis, and a low result does not rule out every cancer.

Australia’s updated national early-detection guidelines, approved by the National Health and Medical Research Council in May 2026, recommend discussing individual risks, preferences, benefits and possible harms before starting PSA testing. For men who choose testing, the guidelines recommend offering it every two years from age 50 to 69 for those not at higher risk, and from age 45 for those at higher risk. Higher risk includes a relevant family history, a confirmed BRCA2 gene mutation or Black sub-Saharan ancestry. Men aged 70 and over should discuss whether to continue testing in light of their health and preferences. These are discussion points, not a substitute for individual medical advice.

If a PSA result is higher than expected, a doctor may repeat the test and consider other information, such as age, symptoms, family history and examination findings. A urologist may recommend a prostate MRI to help decide whether a biopsy is appropriate and, if so, where to take samples. A biopsy is currently the test that confirms a diagnosis and provides information about the cancer’s grade. Not everyone with an elevated PSA needs a biopsy, and no test is perfect. If cancer is found, the next steps depend on its grade and stage, the person’s health and their preferences; some lower-risk cancers can be monitored with active surveillance.

Make November a reason to check in

This November, consider wearing blue when you walk, jog, run or volunteer at your local parkrun. Invite a friend or family member to join you. It is a simple way to show support, start a conversation and make space for men’s health alongside the usual weekend catch-up. This is a community invitation, not a claim that parkrun is running an official Movember campaign.

If you are unsure whether PSA testing is right for you, speak with your GP. Mention your age, family history and any symptoms, and ask what a result could mean and what the next steps might be. If someone close to you has prostate cancer, listening and offering to go with them to an appointment can be a practical form of support.

Grow a Mo, wear blue, or simply start the conversation. The moustache is the prompt; informed choices and looking out for one another are the point.

This article provides general information and is not a substitute for advice from your doctor. Testing decisions should be made with a health professional who can consider your personal circumstances.

References and further information

  1. Australian Institute of Health and Welfare. Cancer data in Australia: Overview of cancer in Australia, 2025.
  2. Australian Institute of Health and Welfare. Cancer outcomes improving overall.
  3. Prostate Cancer Foundation of Australia. PSA testing and the 2026 Australian early-detection guidelines.
  4. Prostate Cancer Foundation of Australia. Diagnosis of prostate cancer.
  5. Movember. About Movember.
  6. parkrun Australia. Find a parkrun event.

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

A moustache can start a conversation. A conversation can sometimes save a life.

Every November, moustaches begin appearing on faces around Australia and across the world. Some are magnificent. Some are questionable. Some probably deserve their own urological assessment.

But behind the facial hair lies an important message.

Movember is about getting men talking about their health.

What began in Melbourne in 2003 with 30 men growing moustaches has developed into an international men’s health movement focusing particularly on prostate cancer, testicular cancer, mental health and suicide prevention. Movember reports that it has funded more than 1,320 men’s health projects around the world.

And few recent stories demonstrate the importance of men paying attention to their health better than that of King Charles III.


First, an important clarification: King Charles does NOT have prostate cancer

This point has frequently been confused in media and social-media discussions.

In January 2024, Buckingham Palace announced that King Charles was receiving treatment for an enlarged prostate.

This was benign prostatic enlargement, commonly called benign prostatic hyperplasia or BPH. It is extremely common as men get older and is not prostate cancer.

The King underwent a planned hospital procedure for his enlarged prostate.

During this episode of care, however, doctors identified a separate abnormality. Further investigations subsequently diagnosed a form of cancer.

Buckingham Palace specifically confirmed that the King’s cancer was not prostate cancer. The precise type of cancer has remained private.

That distinction matters.

But so does what happened next.


A prostate problem led to something else being discovered

The King’s story provides an interesting lesson for men’s health.

He sought medical attention for a prostate problem.

He underwent investigation and treatment.

During that process, doctors discovered another potentially important medical condition.

In February 2024 Buckingham Palace announced that the King had begun a programme of regular cancer treatments and temporarily reduced his public-facing duties.

By April 2024, following treatment and recuperation, he was able to return to public-facing duties.

The exact cancer treatment has never been publicly disclosed, and it would therefore be inappropriate to speculate whether he has received surgery, radiotherapy, chemotherapy, immunotherapy or another form of treatment.

More recently, the King has continued to speak publicly about his cancer experience. In December 2025 he announced that, following early diagnosis, treatment and adherence to medical advice, his treatment schedule could be reduced in the following year.

In June 2026 he and Queen Camilla hosted a reception marking the 125th anniversary of Cancer Research UK, of which the King has been Patron since 2024.

His message has increasingly centered on a simple theme:

Early diagnosis matters.


The other royal problem: an enlarged prostate

For a urologist, the first part of the King’s story is equally important.

An enlarged prostate is extraordinarily common.

As the prostate enlarges, it can compress the urethra and interfere with the passage of urine.

Men may notice:

  • a slower urinary stream
  • difficulty starting urination
  • stopping and starting
  • straining
  • feeling that the bladder has not emptied completely
  • getting up several times during the night
  • urgency or frequency
  • occasionally an inability to pass urine at all.

These symptoms do not automatically mean prostate cancer.

Most commonly they are associated with benign prostate enlargement.

But that does not mean they should simply be accepted as part of getting older.


“It’s probably just my prostate”

Possibly.

But that is precisely why it is worth having it checked.

Assessment of urinary symptoms may include a discussion about symptoms and medications, examination, urine testing, kidney function, PSA testing where appropriate, urinary flow measurement, ultrasound assessment of bladder emptying and occasionally further investigations.

The objective is not simply to find prostate cancer.

It is to work out why the urinary system is behaving differently.


What about prostate cancer?

This is where Movember becomes particularly relevant.

Prostate cancer remains the most commonly diagnosed cancer in Australian men. Australian Institute of Health and Welfare data indicate that prostate cancer accounted for approximately 28% of cancers diagnosed in Australian males in 2024.

AIHW’s updated projections estimate approximately 26,397 prostate cancer diagnoses in Australia during 2026, although it is important to recognise that this is a projection rather than a final observed case count.

Movember estimates that approximately one in five Australian men will be diagnosed with prostate cancer during their lifetime.

And there is another important difference between prostate cancer and benign enlargement:

Early prostate cancer frequently causes no urinary symptoms at all.

Waiting until something hurts or the urine flow deteriorates is therefore not an effective prostate cancer detection strategy.


The PSA conversation

A PSA blood test can help identify men who may require further investigation for prostate cancer.

But PSA is not simply a “cancer test”.

PSA can be elevated for several reasons, including:

  • benign prostate enlargement
  • prostatitis or inflammation
  • urinary infection
  • recent instrumentation
  • urinary retention
  • and prostate cancer.

An abnormal PSA therefore does not automatically mean cancer.

Similarly, decisions about PSA testing should consider a man’s age, family history, previous PSA results, general health and individual risk factors.

The important step is having the conversation with your GP or urologist rather than avoiding the subject altogether.


And if prostate cancer is found?

Modern prostate cancer treatment is no longer a simple choice between “operate” and “do nothing”.

Depending upon the PSA, MRI findings, biopsy grade, tumour volume, stage, age and general health of the patient, options may include:

Active surveillance for suitable low-risk disease.

Robotic-assisted radical prostatectomy for appropriate localised cancers.

Radiation therapy, sometimes combined with hormonal treatment.

Focal therapies in carefully selected patients and specialised settings.

Androgen deprivation and newer androgen-receptor targeted treatments for more advanced disease.

Chemotherapy and radioligand therapies for selected advanced cancers.

The right treatment is increasingly personalised to both the biology of the cancer and the priorities of the man sitting in front of us.


Treatment is not only about surviving cancer

This is another area in which organisations such as Movember have made an important contribution.

Men understandably want their cancer controlled.

But they also care about what happens afterwards.

Will I leak urine?

Will I still have erections?

What happens to ejaculation and orgasm?

Can I continue working?

How will treatment affect my relationship?

Will I still feel like myself?

Movember has invested not only in prostate cancer research but also in projects examining quality of life, urinary function, sexual function and outcomes following treatment. The Prostate Cancer Outcomes Registry Australia and New Zealand, for example, collects patient-reported outcomes including urinary, bowel and sexual function after prostate cancer diagnosis and treatment.

These aren’t embarrassing side issues.

They are part of treating the whole man.


So what does King Charles have to do with Movember?

Quite a lot, despite the fact that he does not have prostate cancer.

His story began with something millions of older men experience:

an enlarged prostate.

Instead of ignoring it, he sought treatment.

That interaction with the healthcare system resulted in another cancer being discovered.

And by publicly announcing his prostate treatment and subsequent cancer diagnosis, the King did something particularly useful for men’s health:

he made it easier to talk about it.

That is essentially what Movember has been trying to achieve for more than two decades.

A moustache is simply the billboard.

The conversation is the important bit.


My Movember message to men

If your urinary stream isn’t what it used to be, get it checked.

If you’re getting up repeatedly during the night, ask why.

If you’re struggling with erections, don’t be embarrassed to mention it.

If you notice a testicular lump, don’t wait.

If prostate cancer runs in your family, discuss your individual risk.

And if you’ve been putting off that conversation about PSA testing, perhaps Movember is a good time to have it.

Men are remarkably good at servicing cars, replacing batteries, checking tyre pressures and investigating strange noises coming from engines.

We are sometimes considerably less enthusiastic when the strange noise is coming from ourselves.

This Movember, grow the moustache if you wish.

But more importantly:

Have the conversation.
Know your prostate.
Know your risk.
And don’t ignore a change in your body simply because it’s embarrassing to talk about.

Your prostate may be small.

Its ability to cause trouble is disproportionately ambitious.


References and further reading

  1. The Royal Family. A Statement from Buckingham Palace. 5 February 2024. Buckingham Palace confirmed that a separate cancer was discovered during treatment for benign prostate enlargement.
  2. The Royal Family. The King returns to public-facing duties. April 2024.
  3. The Royal Family. A message from The King in support of Stand Up To Cancer. December 2025.
  4. The Royal Family. The King and Queen host a reception for Cancer Research UK. June 2026.
  5. Australian Institute of Health and Welfare. The health of men in Australia. Prostate cancer statistics and Australian cancer burden.
  6. Australian Institute of Health and Welfare. Cancer data in Australia: Prostate cancer projection method changes and updated long-term projections. Updated July 2026.
  7. Movember. Prostate Cancer: Prostate Cancer Action, Innovation & Collaboration. Australian prostate cancer statistics and research programs.
  8. Movember. Our Story. History of the Movember movement from Melbourne in 2003.
  9. Movember. Prostate Cancer Outcomes Registry Australia and New Zealand. Patient outcomes and quality-of-life research.

Medical disclaimer

This article provides general information and should not replace individual medical assessment. Urinary symptoms, an abnormal PSA or concerns about prostate cancer should be discussed with your GP or urologist.

Active Surveillance for Prostate Cancer

Being diagnosed with prostate cancer does not always mean that treatment needs to start immediately.

Many prostate cancers grow very slowly and may never cause symptoms or threaten a man’s life. For carefully selected men, active surveillance allows the cancer to be closely monitored while avoiding, or at least delaying, treatments such as surgery or radiation therapy.

Importantly, active surveillance does not mean ignoring the cancer. It is a structured programme of PSA testing, clinical review, prostate MRI and, when appropriate, repeat prostate biopsy. If there are signs that the cancer is becoming more significant, treatment can be recommended while the disease is still potentially curable.

Current international guidelines consider active surveillance the preferred or standard management approach for most suitable men with low-risk localised prostate cancer, and it may also be considered in carefully selected men with favourable intermediate-risk disease.


What Is Active Surveillance?

Active surveillance is a management strategy for prostate cancer in which curative treatment is deliberately postponed while the cancer is carefully monitored.

The aim is simple:

Avoid unnecessary treatment and its potential side effects, without compromising the opportunity for cure if the cancer changes.

This is particularly relevant because prostate cancer behaves very differently from one man to another. Some cancers are aggressive and require treatment, while others may remain small and slow-growing for many years.

Australian patient guidance describes active surveillance as close monitoring of low-risk prostate cancer that is not causing symptoms, with treatment initiated if investigations indicate that the cancer is becoming more aggressive.


Who Qualifies for Active Surveillance?

Active surveillance is most commonly recommended for men with low-risk prostate cancer.

Typical features include:

  • Cancer confined to the prostate
  • Grade Group 1 / Gleason score 3+3=6
  • PSA generally less than 10 ng/mL
  • Clinical stage T1 to T2a
  • Relatively small volume of cancer on prostate biopsy
  • Favourable findings on multiparametric MRI
  • A PSA density that supports low-volume disease
  • No clinical or imaging evidence suggesting more aggressive cancer

The AUA/ASTRO risk classification defines low-risk disease as PSA below 10 ng/mL, Grade Group 1 and clinical stage T1–T2a. For these patients, active surveillance is recommended as the preferred management strategy.

However, no single number determines suitability. Age, general health, family history, MRI findings, PSA density, biopsy findings, life expectancy and personal preferences all contribute to the decision.


Can Men With Gleason 3+4 / Grade Group 2 Cancer Have Active Surveillance?

Sometimes.

Active surveillance is increasingly considered for carefully selected men with favourable intermediate-risk prostate cancer, particularly when there is only a small amount of Gleason pattern 4 disease.

The 2026 European Association of Urology guidelines support active surveillance for selected men with favourable Grade Group 2 cancer. Features favouring surveillance include a small amount of pattern 4 disease, PSA below 10 ng/mL, limited tumour volume on biopsy and favourable imaging.

Similarly, AUA/ASTRO guidance suggests that favourable intermediate-risk patients with low PSA density, low tumour volume and a low percentage of Gleason pattern 4 disease may be considered for active surveillance.

These men require careful counselling because their risk of progression is higher than for men with Grade Group 1 disease.

Active surveillance is generally not appropriate for Grade Group 3 or higher-risk prostate cancer in men otherwise suitable for curative treatment.


What Happens Before Starting Active Surveillance?

The first step is making sure that the cancer really is suitable for surveillance.

Assessment may include:

PSA and PSA Density

PSA is considered together with prostate volume to calculate the PSA density.

A relatively low PSA density, commonly around less than 0.15 ng/mL/cc, provides additional reassurance in men being considered for surveillance, although it should not be interpreted as an absolute cut-off in isolation.

Multiparametric MRI of the Prostate

A high-quality multiparametric MRI (mpMRI) provides important information about:

  • The location of the tumour
  • Tumour size
  • Suspicious areas within the prostate
  • Possible extension outside the prostate
  • Areas that should be targeted during biopsy

MRI has become an important part of modern active surveillance, but MRI alone does not completely replace prostate biopsy.

Review or Confirmation of the Biopsy

The initial biopsy determines the Grade Group, Gleason score and volume of cancer.

Depending on how the original diagnosis was made, a confirmatory biopsy may be recommended. MRI-targeted biopsies can specifically sample suspicious lesions, while systematic or regional biopsies assess other areas of the prostate.


How Is Active Surveillance Performed?

Active surveillance is an ongoing programme rather than a single test.

The exact protocol varies according to the patient’s age, cancer characteristics, previous investigations and the treating urologist or institution.

A typical programme may include:

PSA Testing

PSA is usually measured approximately every 3–6 months initially, although intervals may become longer in men with very stable disease.

Current EAU guidance recommends PSA testing at least every six months, while Australian Cancer Council information describes PSA testing every 3–6 months.

The trend in PSA is usually more informative than one isolated reading.

An unexpected rise does not automatically mean that the cancer has progressed. PSA can fluctuate because of benign prostate enlargement, inflammation, infection and other factors.

For this reason, an unexpected PSA rise will often be repeated before further decisions are made.

Clinical Review

Regular appointments allow your urologist to review:

  • PSA changes
  • Urinary symptoms
  • General health
  • Examination findings
  • MRI results
  • Whether further investigation is required

A digital rectal examination may form part of surveillance, although its frequency can be individualised.

Repeat Prostate MRI

Repeat mpMRI may be performed periodically or earlier if PSA or other findings become concerning.

MRI allows comparison with previous scans to determine whether a lesion is:

  • Stable
  • Increasing in size
  • Becoming more suspicious
  • Showing features suggesting progression

Importantly, a change on MRI will often lead to a repeat biopsy rather than automatically triggering treatment. The EAU recommends confirming suspected histological progression before changing treatment strategy where appropriate.

Repeat Prostate Biopsy

Repeat biopsy remains an important component of active surveillance.

The frequency varies according to individual risk, previous MRI and biopsy findings and the surveillance protocol being followed.

The biopsy may involve:

  • Targeted biopsy of an MRI abnormality
  • Systematic sampling
  • A combination of targeted and regional/systematic biopsies

Modern surveillance programmes increasingly tailor biopsy frequency according to the individual’s risk rather than applying exactly the same schedule to every patient.


What Are We Looking for During Surveillance?

The purpose of surveillance is to identify reclassification or progression before the cancer becomes difficult to cure.

Your urologist will be looking for several possible warning signs.

These include:

Increasing cancer grade

For example, a cancer initially classified as Grade Group 1 may subsequently demonstrate a significant amount of Gleason pattern 4 disease.

Increasing cancer volume

More biopsy samples may contain cancer, or individual samples may contain a greater amount of cancer.

Changes on MRI

An existing lesion may enlarge or become more suspicious, or a new lesion may appear.

Persistent PSA changes

A progressively increasing PSA, particularly when accompanied by increasing PSA density or concerning MRI findings, may trigger further investigation.

Clinical progression

Changes on examination or other investigations may suggest that the cancer is no longer behaving as expected.


When Should Active Surveillance Stop?

Active surveillance should generally continue for as long as the cancer remains suitable for surveillance and curative treatment remains relevant.

The decision to move to treatment should ideally be based on the overall picture rather than PSA alone.

Treatment may be recommended when there is:

  • Significant upgrading of the cancer on repeat biopsy
  • Increasing amounts of higher-grade cancer
  • Significant increase in tumour volume
  • Concerning progression on MRI confirmed by appropriate investigation
  • Evidence suggesting progression beyond the original low-risk category
  • A change in the patient’s preference after informed discussion

AUA/ASTRO guidance recommends that significantly higher-volume or higher-grade disease on surveillance biopsy should prompt discussion about definitive therapy.


What Happens If the Cancer Progresses?

The important concept behind active surveillance is that treatment has been postponed, not abandoned.

If investigations demonstrate clinically significant progression, curative treatment can be considered.

Depending on the man’s age, general health, cancer characteristics and preferences, options may include:

Radical Prostatectomy

Surgical removal of the prostate, increasingly performed using robotic-assisted radical prostatectomy.

Focal therapy

Nanoknife electroporation

ProFocal laser ablation

Radiation Therapy

Options may include:

  • External beam radiation therapy
  • Stereotactic radiation therapy in appropriate patients
  • Brachytherapy in selected cases
  • Radiation combined with hormonal therapy where clinically indicated

Other Selected Treatments

In carefully selected circumstances, other approaches may be discussed. The evidence for focal ablative therapies remains less mature than that for established treatments such as surgery and radiation therapy, and suitability needs individual assessment.


What Are the Benefits of Active Surveillance?

For appropriately selected men, the major advantage is avoiding treatment that may never have been necessary.

Avoiding or Delaying Treatment Side Effects

Radical treatment can potentially cause:

  • Urinary incontinence
  • Erectile dysfunction
  • Ejaculatory changes
  • Urinary symptoms
  • Bowel symptoms following some forms of radiation therapy

Active surveillance allows men to maintain their existing urinary, sexual and bowel function for longer.

Maintaining Quality of Life

Many men can continue normal work, exercise, travel and sexual activity without the recovery period or functional consequences associated with immediate treatment.

Avoiding Overtreatment

Some low-risk prostate cancers may never become clinically significant during a man’s lifetime.

Treating every prostate cancer immediately would therefore expose some men to treatment complications without providing a meaningful survival advantage.

Treatment Remains Available

Active surveillance preserves the opportunity for curative treatment if the cancer subsequently demonstrates significant progression.

Long-term outcomes from well-conducted active surveillance programmes are reassuring. The EAU reports 10-year prostate cancer-specific survival rates of approximately 98–100% in active surveillance cohorts, although outcomes depend on appropriate patient selection and follow-up.


What Are the Risks of Active Surveillance?

Active surveillance is not completely risk-free.

The Cancer May Progress

Some cancers initially thought to be low risk will subsequently demonstrate more aggressive features.

In fact, a significant proportion of men are eventually reclassified during long-term surveillance and may proceed to treatment.

The Initial Biopsy May Underestimate the Cancer

A prostate biopsy samples only part of the prostate.

Occasionally, higher-grade cancer may already be present but was not captured during the original biopsy. Modern MRI and targeted biopsy techniques help reduce this risk but cannot eliminate it completely.

Small Risk of Losing the Optimal Window for Treatment

This is one of the main reasons that regular follow-up is essential.

In appropriately selected men who comply with structured surveillance, the risk is low, but surveillance must be active rather than passive.

Repeat Investigations

Active surveillance may involve:

  • Repeated blood tests
  • MRI scans
  • Urology appointments
  • Repeat prostate biopsies

Biopsies can cause discomfort, bleeding and infection, although contemporary transperineal biopsy techniques can substantially reduce the risk of serious infection.

Psychological Impact

Some men find living with untreated cancer surprisingly easy. Others find it difficult.

Anxiety may occur around:

  • PSA tests
  • MRI scans
  • Repeat biopsies
  • Waiting for results
  • Concern that the cancer may be progressing

For some men, the psychological burden becomes an important factor when deciding whether to remain on surveillance.


Active Surveillance Is Not the Same as Watchful Waiting

These terms are sometimes confused, but they describe different approaches.

Active surveillance is generally used for men with potentially curable prostate cancer. The cancer is actively monitored, with the intention of offering curative treatment if clinically significant progression occurs.

Watchful waiting is more commonly used in older men or men with significant other medical conditions where prostate cancer is unlikely to affect life expectancy. Monitoring is less intensive, and treatment is generally introduced to control symptoms rather than with the intention of cure.


Does Active Surveillance Mean Doing Nothing?

No.

This is perhaps the most important misconception about active surveillance.

A better description might be:

“Treatment if and when it becomes necessary.”

The cancer is being monitored carefully so that unnecessary treatment can be avoided while retaining the opportunity to intervene if its behaviour changes.

For the right patient, this can provide an excellent balance between cancer control and preservation of quality of life.


The Bottom Line

Active surveillance has become an established standard of care for appropriately selected men with low-risk prostate cancer and can also be considered for some men with carefully selected favourable intermediate-risk disease.

The decision should take into account:

  • PSA and PSA density
  • Grade Group and Gleason score
  • Amount of cancer found on biopsy
  • MRI findings
  • Clinical stage
  • Age and life expectancy
  • General health
  • Family and genetic risk factors
  • Personal preferences

Most importantly, active surveillance requires a partnership between the patient and his urologist.

The goal is not simply to avoid treatment.

The goal is to avoid treatment that is unnecessary, while identifying the point at which treatment becomes worthwhile.


This information is intended for general education and does not replace individual medical advice. Recommendations for prostate cancer management should be based on a detailed assessment of the individual patient, pathology, PSA results, imaging, general health and personal preferences.

PSA Screening for Prostate Cancer in Australia: Should You Have a PSA Test?

Prostate cancer is one of the most commonly diagnosed cancers in Australian men. One of the difficulties with prostate cancer is that early prostate cancer usually causes no symptoms. By the time symptoms develop, some cancers may already have progressed beyond the prostate.

A simple blood test called the prostate-specific antigen (PSA) test can help identify men who may be at increased risk of prostate cancer. However, PSA testing is not a perfect cancer test and deciding whether to have regular PSA testing involves balancing the potential benefits of early diagnosis against the risks of unnecessary investigation and treatment.

In Australia, there is currently no national population-based prostate cancer screening program. Instead, PSA testing is based on an informed discussion between a man and his doctor, taking into account age, family history, overall health, life expectancy and personal preferences.


What is PSA?

PSA, or prostate-specific antigen, is a protein produced by prostate cells. A small amount normally enters the bloodstream and can be measured with a simple blood test.

An elevated PSA does not automatically mean that you have prostate cancer.

PSA can rise because of:

  • prostate cancer
  • benign enlargement of the prostate (BPH)
  • inflammation or infection of the prostate
  • urinary infection
  • recent ejaculation or sexual activity
  • recent instrumentation of the urinary tract
  • manipulation of the prostate.

Conversely, some men with prostate cancer can have a PSA within the expected range. PSA is therefore best considered a marker of prostate activity and prostate cancer risk rather than a test that diagnoses cancer.


Who Should Consider PSA Testing in Australia?

Current Australian guidance supports informed, individualized PSA testing rather than universal population screening.

For men at average risk who have been informed about the potential benefits and harms and decide to undergo regular testing, current RACGP guidance recommends offering PSA testing every two years between the ages of 50 and 69 years.

Men with a significant family history may be advised to start earlier. Depending on the strength of the family history, testing may begin from approximately 40–45 years of age and continue every two years to age 69.

A stronger family history includes having a father, brother or multiple close relatives diagnosed with prostate cancer, particularly when prostate cancer occurred at a younger age.

Other factors, including ancestry, genetic predisposition and an individual’s general health and life expectancy, may also influence the decision about when to begin testing.

Importantly, these recommendations apply to men without symptoms. Men with symptoms or clinical findings that raise concern about prostate cancer require individual assessment rather than simply entering a screening program.


What Does an Elevated PSA Mean?

An elevated PSA is not a diagnosis of prostate cancer.

For men aged 50–69 undergoing early detection testing, a PSA above 3.0 ng/mL generally prompts further assessment under current Australian guidance. An abnormal result will often be repeated because PSA levels can fluctuate and temporary elevations are common.

Depending on the PSA level, age, prostate size, family history and other risk factors, further assessment may include:

Repeat PSA → assessment of PSA trend and other risk factors → specialist review → prostate MRI → possible prostate biopsy

Modern prostate cancer assessment has changed substantially. An abnormal PSA no longer necessarily means proceeding directly to a prostate biopsy. Multiparametric MRI (mpMRI) can help identify suspicious areas within the prostate and assist the urologist in deciding whether biopsy is necessary.


The Potential Benefits of PSA Screening

The principal advantage of PSA testing is straightforward:

It may detect a significant prostate cancer while it is still curable.

Aggressive prostate cancer can spread to lymph nodes, bones and other organs. Once metastatic prostate cancer develops, treatment is generally aimed at controlling rather than curing the disease.

Regular PSA testing provides an opportunity to identify some clinically important cancers years before they would otherwise become apparent.

Large screening trials have produced differing results, which is one reason PSA screening remains controversial. European screening data have demonstrated a reduction in prostate cancer mortality associated with PSA-based screening, while other trials have shown less convincing mortality benefits.

For an individual man, therefore, the potential benefit is significant: early detection may identify an aggressive cancer at a stage when curative treatment remains possible.


What Are the Downsides of PSA Screening?

The difficulty is that prostate cancer is not one disease.

Some prostate cancers are aggressive and potentially life-threatening. Others grow extremely slowly and may never cause symptoms during a man’s lifetime.

PSA testing can detect both.

False-positive PSA results

An elevated PSA may lead to anxiety, repeat blood tests, MRI scans and sometimes biopsy even when no cancer is ultimately found.

Overdiagnosis

PSA testing can identify a prostate cancer that would never have caused illness or shortened the man’s life.

This is known as overdiagnosis.

Overtreatment

If an insignificant cancer is diagnosed and subsequently treated, the man can potentially experience treatment complications without gaining a meaningful survival benefit.

Potential consequences of prostate cancer treatment include:

  • erectile dysfunction
  • urinary incontinence
  • urinary symptoms
  • ejaculatory changes
  • bowel symptoms following some forms of radiotherapy.

This is one of the major reasons Australia does not currently have a universal PSA population-screening program.

Importantly, however, diagnosing prostate cancer does not automatically mean treating it.

Many men with low-risk prostate cancer are now managed with active surveillance, involving PSA monitoring, MRI and selective repeat biopsy. Treatment is reserved for evidence that the cancer is becoming more significant.


What Are the Implications of Not Having PSA Screening?

Choosing not to undergo PSA testing is also a legitimate decision, particularly after considering the benefits and disadvantages.

The advantage is avoiding the potential cascade of:

PSA testing → abnormal result → anxiety → MRI → biopsy → diagnosis of an insignificant cancer → possible unnecessary treatment.

However, there is another side to this decision.

Because early prostate cancer frequently produces no symptoms, a man who does not undergo PSA testing may remain unaware that he has prostate cancer.

For most men who never develop clinically significant disease, this causes no harm.

For a smaller group who develop aggressive prostate cancer, however, the first indication of the disease may occur after the cancer has grown substantially or spread beyond the prostate.

At that stage, the opportunity for curative treatment may have been reduced or lost.

The decision is therefore not simply:

“Do I want to know whether I have prostate cancer?”

A more useful question is:

“Given my age, health, family history and personal priorities, do the potential benefits of finding a significant prostate cancer early outweigh the potential harms of investigating and possibly diagnosing a cancer that may never affect me?”

This is why shared decision-making with your GP or urologist is important.


What About a Digital Rectal Examination?

The digital rectal examination, or DRE, involves a doctor gently inserting a gloved, lubricated finger into the rectum to examine the back surface of the prostate.

The doctor assesses the prostate for abnormalities such as:

  • unusual hardness
  • nodules
  • asymmetry
  • irregularity
  • loss of the normal contour of the gland.

Historically, DRE was routinely combined with PSA testing for prostate cancer screening.

This has changed.

DRE is no longer recommended as a routine screening test in asymptomatic men

Current Australian guidance states that DRE should not routinely be added to PSA testing for early detection in asymptomatic men in primary care.

There are several reasons.

A finger can examine only part of the prostate. Small cancers may not be palpable, and cancers in areas of the prostate that cannot be reached during examination can be missed. A normal DRE therefore does not exclude prostate cancer.

Conversely, benign prostate enlargement and other abnormalities can sometimes produce an abnormal examination.


Does DRE Still Have a Role?

Yes.

Not recommending DRE as a routine screening test does not mean that the examination has become obsolete.

A urologist may perform a DRE when assessing a man with:

  • an elevated or rising PSA
  • urinary symptoms
  • suspected prostate disease
  • an abnormal MRI
  • concern about locally advanced prostate cancer
  • other pelvic or rectal symptoms.

Occasionally, a prostate cancer may produce a distinctly hard or irregular prostate even when the PSA is not dramatically elevated. An abnormal DRE can therefore remain clinically important and may prompt further investigation. Cancer Council Australia notes that urologists will commonly perform DRE as part of prostate assessment even though GPs no longer routinely use it for screening asymptomatic men.

The key distinction is:

DRE has a role in clinical examination and investigation, but it is not recommended as a routine population-screening test in an otherwise well man undergoing PSA testing.


PSA Screening Is About Risk, Not Just a Number

One of the most important changes in modern prostate cancer detection is moving away from treating PSA as simply “normal” or “abnormal.”

A PSA result should be interpreted in context.

Your doctor or urologist may consider:

your age + PSA level + change in PSA over time + family history + prostate size + symptoms + examination findings + MRI findings + overall health

Together, these provide a much more meaningful assessment of prostate cancer risk than a single PSA result.


Should I Have a PSA Test?

There is no single answer that is appropriate for every man.

For a healthy man in the appropriate age group, particularly someone with a family history of prostate cancer, the potential benefit of identifying an aggressive cancer while it remains curable may be important.

For an older man with substantial medical problems or limited life expectancy, the likelihood that PSA screening will provide meaningful benefit becomes considerably smaller. Current Australian guidance advises against PSA testing in men whose life expectancy is likely to be less than approximately seven years because a mortality benefit from early detection is unlikely to occur within that period.

The decision should therefore be individual rather than automatic.


The Bottom Line

PSA testing can save lives by detecting clinically significant prostate cancer at an earlier and potentially curable stage, but it can also detect cancers that would never have caused harm.

Australia therefore does not currently operate a universal PSA screening program. Instead, men are encouraged to make an informed decision about PSA testing after discussing their individual risk and the potential benefits and harms with their doctor.

For men who choose screening, current Australian guidance generally supports PSA testing every two years from age 50–69 for men at average risk, with earlier testing considered for men with a significant family history.

A digital rectal examination is no longer recommended as a routine addition to PSA screening in asymptomatic men, but it remains an important component of specialist prostate assessment in selected circumstances.

Concerned about your prostate cancer risk?

If you are considering PSA testing, have a family history of prostate cancer, have noticed a change in your PSA, or have urinary symptoms, discuss your individual risk with your GP or urologist.

Early detection should not simply be about finding more prostate cancers. The goal is to identify the cancers that matter, at a time when something useful can still be done about them.

This information is intended for general education and does not replace individual medical advice. Recommendations may differ according to your age, family history, medical conditions and previous PSA results.

Further information

Australian patient information and guidance are available from Cancer Council Australia: Prostate cancer screening and early detection and the RACGP Guidelines for preventive activities in general practice.

How Diet & Lifestyle Can Support Prostate Health

Prostate health: food, movement and informed testing

The prostate is a small gland below the bladder that contributes fluid to semen. It surrounds the first part of the urethra, so changes in the prostate can affect urination. Prostate enlargement, inflammation and cancer are different conditions; urinary symptoms alone cannot tell us which, if any, is present.[1, 2]

A healthy diet and regular activity support overall wellbeing. They may help some people manage weight and cope with treatment, but no food or exercise programme has been shown to guarantee prevention of prostate enlargement or prostate cancer. Similarly, a “check-up” is not the same thing as screening everyone for cancer: the decision to have a PSA blood test should take account of age, individual risk, preferences and the possible harms of testing.[3, 4]

What can affect the prostate?

Benign prostate enlargement (BPH) becomes more common with age. It may cause a weak stream, hesitancy, more frequent urination or waking at night. Similar symptoms can come from bladder conditions, medicines or other causes. Treatment depends on the degree of bother and any complications, and can range from monitoring and practical changes to medicines or a procedure.[1]

Prostatitis describes inflammation of the prostate and has several forms. Pain, urinary symptoms or fever require assessment; diet alone will not diagnose or treat the cause.[1]

Prostate cancer often causes no symptoms in its early stages. Some cancers grow slowly and may never need treatment; others are more aggressive. An abnormal PSA result does not by itself establish a cancer diagnosis.[2, 4]

Is there a “prostate-friendly” diet?

It is reasonable to use this phrase for a varied, balanced eating pattern, but it should not imply that a particular menu protects the prostate. The Australian Dietary Guidelines recommend vegetables, fruit, mostly wholegrain cereals, appropriate protein foods and water as a usual drink, while limiting foods high in added salt and saturated fat.[5] Food choices should also fit a person’s other conditions and cultural preferences.

The foods often promoted for prostate health can fit into that pattern, with important limits to the evidence:

Food What it offers What remains unproven
Tomatoes A vegetable source of lycopene and other nutrients Eating tomatoes or taking lycopene supplements has not been established as a way to prevent or treat prostate cancer.[3, 6]
Broccoli and cauliflower Vegetables that add variety and fibre Laboratory theories about their compounds do not prove that they prevent prostate disease in people.[3]
Salmon and sardines Protein and, in oily fish, omega-3 fats Fish is not a proven prostate cancer treatment or prevention strategy.[3, 5]
Green tea A beverage some people enjoy Antioxidant content does not establish a clinical benefit for prostate cancer; caffeine may aggravate urinary urgency in some people.[3, 7]
Chia and flaxseeds Fibre and unsaturated fats Eating these seeds is not proven to prevent BPH or prostate cancer.[3, 5]

No supplement should be assumed to be beneficial because it is sold as “natural” or “prostate supporting.” The SELECT trial, for example, found increased prostate cancer risk among men assigned vitamin E alone. Discuss supplements with your clinician, particularly if you are receiving treatment or taking medicines.[6]

A practical meal might include vegetables, a wholegrain food and fish, beans, eggs, tofu or another suitable protein. Add fruit or unsalted nuts and seeds according to preference. The value is in the overall pattern, not a particular “superfood.” If cancer treatment is affecting appetite or weight, an accredited practising dietitian can tailor the plan.[5, 8]

Movement, weight and everyday habits

Physical activity helps cardiovascular health, strength, mood and weight management. Australia’s current adult movement recommendations encourage activity on most days, including moderate to vigorous movement for at least 30 minutes on most days, strength activities twice a week, and mobility or balance activities on several days.[9] A walk, cycling, swimming or a manageable strength routine can be a starting point; build gradually if you have been inactive.

Excess body weight is associated with some adverse health outcomes, and Cancer Council Australia reports evidence linking overweight and obesity with prostate cancer risk. That association does not mean that weight loss prevents every prostate cancer, or that a person’s weight explains an individual diagnosis.[3]

For urinary symptoms, it can help to note when and how much you drink, whether caffeine or alcohol worsens urgency, and whether constipation is present. Drinking enough is important, but forcing large volumes can make frequency worse. These measures may ease symptoms for some people; they should not delay assessment of persistent or concerning changes.[1, 7]

If you are undergoing prostate cancer treatment, exercise may support fitness and help with treatment-related effects. The safest type and intensity depend on treatment, fatigue, bone health and other conditions. Ask your treating team or an accredited exercise physiologist for an individual plan when needed.[8]

What about PSA testing and “regular check-ups”?

A PSA test measures a protein made by the prostate. PSA may rise for reasons other than cancer, and testing can find slow-growing cancers that would never have caused harm. Further investigation and treatment can carry physical and emotional burdens. Testing may also identify a cancer at a stage when treatment can help. These benefits and harms should be discussed before testing.[2, 4]

The 2026 Australian guidelines for early detection recommend, after an informed discussion, PSA testing every two years for people aged 50–69 who choose testing. Routine testing at 45–49 is generally not recommended for average-risk people, although an interested person may be offered an initial test. People at higher risk, including those with certain family histories, Black sub-Saharan ancestry or a BRCA2 mutation, may be advised to start two-yearly testing at 45. For people aged 70 or older, the decision is individualised according to health, life expectancy and preferences.[4]

These are recommendations for people without symptoms. New difficulty passing urine, blood in the urine, persistent pain or other concerning symptoms call for assessment regardless of age or a planned PSA testing schedule. A GP is a sensible first contact and can arrange testing or referral when indicated.[2, 4]

A sustainable approach

Eat a varied diet, move regularly in ways you can sustain, and talk with your GP about symptoms and whether PSA testing makes sense for your age and risk. Healthy living is valuable in its own right, while medical decisions remain individual. There is no guarantee that these steps will prevent prostate disease, and a diagnosis does not mean someone has failed to look after their health.

General information only. This article does not replace personal medical advice or a discussion of the benefits and harms of PSA testing.

References

  1. Healthdirect Australia. Prostate problems.
  2. Cancer Council Australia. Early detection of prostate cancer.
  3. Cancer Council Australia. Prostate cancer prevention: evidence on lifestyle and diet.
  4. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia.
  5. National Health and Medical Research Council. Australian Dietary Guidelines.
  6. US National Cancer Institute. Prostate cancer, nutrition and dietary supplements; SELECT trial results.
  7. Healthdirect Australia. Benign prostatic hypertrophy: lifestyle measures.
  8. Cancer Council Australia. Life during and after prostate cancer treatment.
  9. Australian Government Department of Health. 24-hour movement recommendations for adults.