
Movember and the digital rectal examination: does it still matter?

The digital rectal examination (DRE) has been part of prostate assessment for generations. It is also one of the tests men are most likely to dread, joke about, or avoid. As Movember prompts conversations about prostate health, it is worth asking what a DRE can actually tell us today and when it is useful.

The short answer: a DRE still has a place in clinical assessment, but it is not recommended as a routine add-on to PSA testing for every asymptomatic man. PSA blood testing is the main early-detection test. A DRE can add physical information in selected situations, and it remains one part of monitoring some men with known prostate cancer.

What is a DRE?

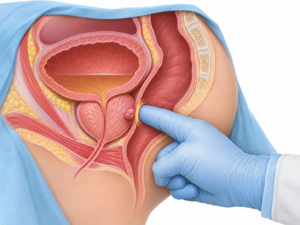
A DRE is a brief examination in which a clinician gently inserts a gloved, lubricated finger into the rectum to feel the back surface of the prostate. The clinician assesses features such as the prostate’s size, shape, firmness, symmetry and any distinct lump or irregular area. It may also give information about tenderness or other rectal findings.

The prostate sits in front of the rectum, so the examination can only feel part of the gland. It cannot reliably assess the whole prostate, and some cancers, particularly those in areas that cannot be reached by touch, may not be felt. A normal DRE therefore does not rule out prostate cancer.
What extra information can it provide?

PSA is a blood marker produced by prostate tissue. It helps estimate risk, but PSA alone does not show where a possible cancer is or how the prostate feels. A DRE gives the clinician a physical finding to interpret alongside the PSA result, symptoms, family history and, when indicated, MRI and biopsy.

A firm nodule, marked asymmetry, or an unusually hard or fixed-feeling area can increase concern and prompt further assessment, even if the PSA is not markedly raised. An abnormal DRE may also help estimate the clinical extent of a cancer and its likelihood of being more significant. But it is not a cancer diagnosis: benign enlargement, inflammation and examiner variation can affect what is felt. A suspicious finding usually needs further assessment, often including MRI and possibly biopsy.

DRE is not a substitute for PSA, MRI or biopsy. Nor does a normal examination provide a guarantee that cancer is absent.

Can it find cancers that produce little PSA?

Occasionally, prostate cancer is found after a suspicious DRE even when PSA is low. Some uncommon or poorly differentiated cancers can produce less PSA than expected. In the 2026 European Association of Urology guideline, a suspicious DRE with PSA at or below 4 ng/mL was associated with a positive predictive value ranging widely from 5% to 30% in the cited evidence. This shows why a distinctly abnormal examination should not automatically be dismissed because of a reassuring PSA.

That does not mean DRE is a dependable way to screen for low-PSA cancers. Many cancers cannot be felt, and DRE’s performance as a stand-alone screening test is limited. If symptoms, imaging or other clinical features raise concern, the clinician should consider the full picture rather than rely on either a normal PSA or a normal DRE alone.

Should every man having a PSA test also have a DRE?

No. The NHMRC-approved 2026 Guidelines for the Early Detection of Prostate Cancer in Australia suggest that DRE not be offered in primary care as a routine addition to PSA testing and risk assessment for asymptomatic men. The RACGP Red Book also advises against routine DRE as an addition to PSA testing in asymptomatic men seeking early detection.

This reflects evidence that routine DRE adds little to population early-detection pathways compared with PSA-based assessment, while it can create discomfort and deter some men from discussing testing. PSA testing itself is a choice to make after discussing potential benefits and harms with a GP; it is not an automatic test for everyone.

A DRE may still be appropriate when a person has symptoms, a concerning PSA result, an abnormality on imaging, or another clinical reason for a physical examination. A clinician should explain why it may help in that specific situation and discuss alternatives where appropriate.

What about men already on active surveillance?

Active surveillance is a monitoring approach for selected men with lower-risk prostate cancer, intended to identify evidence of meaningful change while avoiding or delaying treatment side effects when it is safe to do so.

The 2026 Australian guideline proposes periodic DRE alongside PSA measurements, MRI where appropriate and repeat biopsy when clinically indicated. A change in the examination may be one reason to bring forward MRI or biopsy. It is not, by itself, usually enough to decide that treatment should start. The European Association of Urology also includes DRE in surveillance protocols, while recognising that its frequency may be reduced in selected men with stable MRI and other reassuring findings. Monitoring plans vary with the cancer’s features, prior tests and the person’s circumstances.

Why is the DRE so famous, and why are some men apprehensive?

For many years, before PSA testing and prostate MRI were available, clinicians had fewer ways to assess the prostate. The DRE was a quick bedside examination that could identify a large or locally advanced abnormality. It became closely associated with “getting your prostate checked,” and popular culture has kept it in the spotlight.

When I discuss it with patients, I sometimes call DRE the “dreaded rectal examination” a little wordplay that can break the ice. It acknowledges the test’s reputation, but it is not a request to grin and bear it: I explain what I’m doing, ask permission, and stop if you ask.

The examination can feel intimate or embarrassing. Some men worry it will hurt, feel exposed, or be judged. Others have heard jokes that link the test to masculinity or sexuality. These concerns are understandable, but a DRE is a clinical examination; it says nothing about a person’s identity or sexuality. Many people find it awkward or uncomfortable rather than painful, although experiences differ.

You can ask the clinician to explain each step before starting, request a chaperone, discuss positioning, and ask them to stop at any time. Consent matters. You do not need to agree to an examination simply because you have come to talk about PSA testing.

What should I do this Movember?

If you are thinking about prostate testing, speak with your GP about your age, family history, health and preferences. Ask whether PSA testing is suitable for you and whether an examination would add useful information in your circumstances. If you have urinary symptoms, blood in your urine or semen, persistent unexplained pain, or another concern, arrange an assessment rather than waiting for a routine screening test.

Movember is a chance to make the conversation easier. The aim is not to insist that every man must have a DRE. It is to help each person understand the available tests, feel able to ask questions, and make an informed decision with their clinician.

This article provides general information and is not a substitute for personal medical advice.

References and further information

  1. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia. NHMRC-approved recommendations, 18 May 2026. See Recommendations 4.1 and 8.2.1.
  2. The Royal Australian College of General Practitioners. Guidelines for preventive activities in general practice, 10th edition — prostate cancer. Recommendations updated 28 June 2024.
  3. European Association of Urology. EAU Guidelines on Prostate Cancer: Diagnostic Evaluation, 2026 edition.
  4. European Association of Urology. EAU Guidelines on Prostate Cancer: Treatment and active-surveillance follow-up, 2026 edition.
  5. Sajjad W, et al. Comparing the Performance of Digital Rectal Examination and Prostate-specific Antigen as a Screening Test for Prostate Cancer: A Systematic Review and Meta-analysis. European Urology Oncology. 2024. PubMed.

Movember: PSA testing: what it can tell you, and what it can’t

An informed conversation with your GP can help you decide whether a PSA test is right for you. Your age, family history, general health and preferences all matter.

Movember is a good time to talk about men’s health, including prostate cancer. One of the most useful steps is often a simple conversation with your GP about prostate-specific antigen (PSA) testing. A PSA blood test can help identify men who may need further assessment, but it is not a yes-or-no cancer test. Understanding what it can and cannot show helps you make an informed choice.

What is PSA?

PSA is a protein made by cells in the prostate. A small amount normally enters the bloodstream, where it can be measured with a blood test. PSA is prostate-specific, but not cancer-specific: a higher result can occur with prostate cancer, but also with benign prostate enlargement, inflammation or infection, urinary retention, or after some urinary procedures. PSA levels also tend to rise with age.

A PSA test is different from a digital rectal examination (DRE). The blood test measures PSA. A DRE is an examination in which a clinician feels the prostate through the rectum. A DRE is not routinely required as an addition to PSA testing for an asymptomatic man under RACGP guidance, although examination may be useful when symptoms or other findings make it appropriate.

Why do we use PSA?

Prostate cancer may cause no symptoms in its early stages. PSA testing can identify a result that deserves a closer look before symptoms develop. Used thoughtfully, early detection may help find clinically significant cancer while treatment or monitoring options remain available.

There are limits and possible harms. PSA can be raised when cancer is not present, leading to anxiety, repeat tests, scans and sometimes biopsy. It can also find a slow-growing cancer that would never have caused a problem during a person’s lifetime. Diagnosis and treatment can have side effects, including changes to urinary continence and sexual function. The chance of benefit depends on a person’s risk, health and life expectancy. That is why Australian guidance recommends an informed discussion before testing rather than testing everyone automatically.

Is PSA a good marker for prostate disease or prostate cancer?

PSA is a useful risk marker, not a diagnosis. It can help estimate the chance of prostate cancer and guide whether further assessment is sensible. It is not a reliable general test for every prostate problem, and it cannot by itself distinguish cancer from benign enlargement or inflammation.

A low PSA lowers the chance of prostate cancer but does not make it zero. A raised PSA does not mean that cancer is present. If the result is higher than expected for a person’s age and risk, the GP will usually consider the whole picture and repeat the test before acting on a single result. Infection, inflammation, retention and recent instrumentation can affect the result, so timing and clinical context matter.

If PSA remains elevated, further assessment may include a clinical review, examination when appropriate, and prostate MRI. Current Australian guidance recommends multiparametric MRI before biopsy. A biopsy, when indicated, is what confirms whether cancer is present and provides information about its grade. Not everyone with a raised PSA needs a biopsy.

How often should PSA be tested?

Australia’s guidance has evolved. The RACGP’s Guidelines for preventive activities in general practice (Red Book, 10th edition, 2024) recommends offering informed men at average risk aged 50–69 PSA testing every two years if they choose regular testing. It recommends testing every two years from age 45 for men at moderately increased risk because of family history, and from age 40 for those at high risk due to family history, through age 69.

USANZ’s published PSA position statement is described as an interim document pending updates to the PCFA and RACGP guidelines. It supports an individualised, risk-based discussion for well-informed men over 50 with an adequate life expectancy, earlier testing from over 45 for men with a family history or higher-risk ethnicity, and from over 40 for men with a BRCA2 mutation.

Since those documents, the NHMRC approved the 2026 Guidelines for the Early Detection of Prostate Cancer in Australia. These are the latest national recommendations and give the following general pathway for people who decide to test after discussion with their GP:

Age and risk General testing approach
Average risk, age 50–69 Offer PSA testing every two years.
Higher risk, age 45 and over Offer testing every two years, using lower PSA levels to trigger a repeat test and possible referral.
Age 70 and over Individualise the decision. The guideline generally considers testing when estimated life expectancy is more than seven years.
Age 45–49, not at higher risk Routine testing is not recommended; an initial test may be discussed if the person is interested.

The 2026 guideline defines higher risk to include having a brother with prostate cancer; a father diagnosed before age 65; two or more second-degree relatives who died from prostate cancer; Black sub-Saharan ancestry; or a confirmed BRCA2 mutation. Family-history details and other health factors still need to be discussed with a GP. The guideline uses age- and risk-specific PSA action levels; a result at or above an action level is generally repeated within one to three months, rather than treated as a cancer diagnosis.

These recommendations guide discussion; they are not a substitute for individual advice. Screening recommendations apply to people without symptoms. If you have symptoms, your GP may recommend assessment regardless of your age or the usual testing interval.

How important is family history?

Family history can make a real difference. Prostate cancer in a close relative, especially a brother, or a father diagnosed at a younger age, can increase a person’s risk and may mean discussing PSA testing earlier than age 50. Multiple affected relatives can also point to an inherited risk. A known BRCA2 mutation is another important risk factor.

If you know that prostate cancer has affected your family, tell your GP which relative was affected and how old they were when diagnosed. Also mention any known breast, ovarian, pancreatic or other cancers in the family, as these may help the GP decide whether genetic counselling or testing should be discussed. Do not wait for symptoms before raising a strong family history.

When should I see a urologist?

Your GP is usually the right first contact. A referral to a urologist may be appropriate if a repeat PSA remains at or above the age- and risk-based action level, if the prostate examination is concerning, or if MRI or other findings suggest that specialist assessment is needed. A urologist can discuss the benefits and limits of further tests, including MRI and biopsy, and help decide on next steps.

Make an appointment with your GP if you notice persistent or new urinary problems, blood in your urine or semen, or ongoing unexplained pain. These symptoms can have many causes and do not automatically mean prostate cancer, but they deserve assessment. Do not wait for a routine PSA check if you have a concerning symptom. If you cannot pass urine, seek urgent medical care.

A useful Movember conversation

Ask your GP: “Given my age, health and family history, should I have a PSA test? If we test, how often should I repeat it, and what would we do if it is raised?” Knowing your family history and discussing the possible benefits and harms can make the decision more useful than simply ordering a blood test without a plan.

Movember is a reminder to look out for one another. Start the conversation, share what you know about your family history, and encourage the men in your life to seek advice when something does not feel right.

This article provides general information and is not a substitute for personal medical advice. PSA testing is a shared decision between you and your healthcare professional.

References and further information

  1. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia: summary and recommendations. NHMRC approved 18 May 2026.
  2. The Royal Australian College of General Practitioners. Guidelines for preventive activities in general practice, 10th edition — prostate cancer, recommendations updated 28 June 2024.
  3. Urological Society of Australia and New Zealand. PSA Testing position statement. Interim guidance pending updated guidelines.
  4. Huang S, Chen DC, Crowe J, et al. Navigating the shift: New RACGP Red Book guidelines for prostate-specific antigen testing in general practice. Australian Journal of General Practice. 2025;54(12). Article PDF.

Know your testes: testicular cancer, self-awareness and Movember

Movember is a good time to talk openly about men’s health. Testicular cancer is uncommon overall, but it matters because it often affects teenagers and younger adults, and a new lump can be easy to dismiss or feel awkward to discuss. Knowing what is usual for your body can help you notice a change and seek advice.

How common is testicular cancer in Australia?

Cancer Australia estimates that 1,040 people will be diagnosed with testicular cancer in Australia in 2025. The estimated lifetime risk for males is about 1 in 188 by age 85. The rate is highest in men aged 30–34, although it can occur at other ages. Testicular cancer is one of the more common cancers in younger men. [1,2]

The outlook is generally very good. For Australians diagnosed from 2017 to 2021, five-year relative survival was 98%. This is a population estimate: an individual’s outlook depends on the cancer type, stage, tumour markers, health and response to treatment. Many testicular cancers, including some that have spread, can be cured with modern treatment. [1,2]

What does “regular self-examination” mean?

There is no national screening program or recommended screening interval for testicular cancer. Research has not shown that scheduled self-examination of people without symptoms reduces deaths, and a Cochrane review found no randomised trials that tested whether screening by self-examination or a clinician prevents testicular-cancer deaths. Cancer Council Australia therefore does not recommend population screening. [3,4]

That is different from being familiar with your own body. Movember’s “Know Thy Nuts” campaign encourages men to learn what feels normal and to get changes checked. A practical approach is to check in with yourself from time to time, such as in the shower, without treating it as a test that can rule cancer in or out. If you have a higher-risk history, discuss an individual plan with your GP or urologist. [3,5]

A simple way to get familiar with what is normal

  1. Warm water can relax the scrotal skin, making it easier to feel the testicles.
  2. Examine one testicle at a time. Gently roll it between your thumb and fingers; do not squeeze hard.
  3. Notice its usual size, shape and feel. It is common for one testicle to hang lower or be slightly larger than the other.
  4. The epididymis, a soft, slightly ridged tube along the back of each testicle, is normal anatomy. It can be mistaken for a lump when you are not familiar with it.
  5. Pay attention to a new firm lump on the testicle, a change in size or shape, new swelling, a feeling of heaviness, or a persistent ache.

There is no need to follow a rigid monthly schedule. The useful point is to know what is usual for you and to arrange a medical review if something changes. Self-checking cannot diagnose cancer, and a normal-feeling testicle does not replace assessment of symptoms.

When should you see a doctor?

Arrange a prompt appointment with your GP if you find a new lump or notice persistent swelling, a change in size or shape, heaviness, or an ache in the testicle, scrotum or lower abdomen. Most scrotal changes are not cancer, but they deserve assessment rather than guesswork. A sudden, severe testicular pain needs urgent emergency assessment because conditions such as testicular torsion can threaten the testicle and require rapid treatment. [2,6]

Movember notes that a GP can ask about symptoms, examine the testicles and arrange an ultrasound or blood tests when needed. It is reasonable to ask when and how you will receive results, and to follow up if you have not heard back. [5]

What types of testicular cancer are there?

Most testicular cancers start in germ cells, the cells that develop into sperm. They are grouped into two main categories: [2,7]

  • Seminoma: Often grows and spreads more slowly than non-seminoma. It is most often diagnosed in adults roughly 25–45 years old, but can occur outside this range. A rare spermatocytic type tends to occur in older men.
  • Non-seminoma: More common in younger men, often from the late teens to early 30s. The main cell types are embryonal carcinoma, yolk-sac tumour, choriocarcinoma and teratoma. A tumour may contain more than one type; mixed tumours are generally managed as non-seminoma.
  • Stromal tumours: These arise from hormone-producing or supporting cells, such as Leydig or Sertoli cells. Many are benign, but specialist assessment is needed to determine what a mass is.
  • Germ-cell neoplasia in situ (GCNIS): Abnormal germ cells that have not invaded surrounding tissue. It is a precursor condition, rather than an invasive cancer, and is usually found on tissue examination.

The type matters because seminoma and non-seminoma can behave differently and may need different follow-up or treatment.

How is a testicular mass investigated?

A doctor will ask about the change and examine the scrotum and surrounding areas. Scrotal ultrasound is the key imaging test to distinguish a solid testicular mass from other causes of swelling. Blood tests may measure alpha-fetoprotein (AFP), beta-human chorionic gonadotrophin (β-hCG) and lactate dehydrogenase (LDH). These markers help with diagnosis, staging and monitoring, but normal results do not exclude testicular cancer. If cancer is suspected, further imaging—often CT scans—is used to assess whether it has spread. [6,8]

A needle biopsy through the scrotum is generally avoided when a germ-cell cancer is suspected. Diagnosis is usually confirmed by removing the affected testicle through an incision in the groin (radical inguinal orchidectomy) and examining it under a microscope. This operation is also the first treatment for most testicular cancers. [6]

Treatment options

Treatment depends on the tumour type, stage, blood-marker results, risk of recurrence, general health and the person’s priorities. Care is planned by a multidisciplinary team, usually including a urologist, medical oncologist, radiation oncologist and cancer-care nurses. Options can include: [6,9]

  • Orchidectomy: Removal of the affected testicle. For some cancers confined to the testicle, this may be the only treatment needed.
  • Active surveillance: Regular appointments, blood tests and imaging after surgery to detect any recurrence early. This is a structured treatment option, not being left without follow-up.
  • Chemotherapy: Often cisplatin-based combinations, such as BEP, for selected cancers with a higher recurrence risk or disease that has spread.
  • Radiotherapy: Used in selected seminoma cases; its role is more limited than in the past because surveillance and chemotherapy are alternatives, and long-term effects are considered.
  • Retroperitoneal lymph-node surgery: Removal of selected lymph nodes in the abdomen in particular non-seminoma situations, often when cancer remains after chemotherapy or when surgery is preferred in carefully selected cases.

The choice after orchidectomy is not the same for everyone. For early seminoma, surveillance is commonly offered; some people may consider a single dose of carboplatin. For early non-seminoma, surveillance, one cycle of chemotherapy, or (in selected cases) lymph-node surgery may be discussed. The aim is to cure the cancer while avoiding treatment that is not necessary. [6]

Fertility, hormones and life after treatment

If there is time before chemotherapy or radiotherapy, ask about sperm banking, even if you are unsure about future plans. Cancer and its treatment can affect fertility, and it is easier to discuss preservation before treatment begins. Many men retain adequate testosterone and fertility with one healthy testicle, but this is not guaranteed; hormone levels, semen quality and sexual wellbeing can be discussed with the treatment team. A testicular prosthesis can be considered before or after surgery. Follow-up also matters because recurrence and some late effects can occur after treatment. [6,9]

A Movember reminder

Movember’s message is straightforward: get to know what is normal for you, speak up if something changes, and make an appointment rather than carrying the worry alone. Testicular cancer is highly treatable, and getting a new lump assessed is a sensible step—not a reason to assume the worst. [1,5]

This article is for general education and does not replace an individual assessment by a doctor.

References

  1. Cancer Australia. Testicular cancer in Australia: statistics. Incidence estimates, age patterns, mortality and relative survival. Accessed 4 November 2026.
  2. Cancer Council Australia. Testicular cancer: causes, symptoms and treatments. Australian overview of incidence, symptoms, types, diagnosis, treatment and screening position. Accessed 4 November 2026.
  3. Ilic D, Misso ML. Screening for testicular cancer. Cochrane Database Syst Rev. 2011;(2). doi:10.1002/14651858.CD007853.pub2.
  4. Cancer Council Australia. Early detection policy: testicular cancer. Position statement on population screening and testicular self-awareness. Accessed 4 November 2026.
  5. Movember Australia. Seeing a doctor about testicles and testicular cancer; and Know Thy Nuts. Campaign information on noticing changes and seeking medical review. Accessed 4 November 2026.
  6. European Association of Urology. EAU Guidelines on Testicular Cancer (2026), including chapters on diagnostic evaluation and disease management. Accessed 4 November 2026.
  7. Cancer Australia. Types of testicular cancer. Accessed 4 November 2026.
  8. Cancer Australia. How is testicular cancer diagnosed?. Accessed 4 November 2026.
  9. Cancer Australia. Treatment options. Accessed 4 November 2026.
  10. Baade PD, Carrière P, Fritschi L. Trends in testicular germ cell cancer incidence in Australia. Cancer Causes Control. 2008;19(10):1043–1049. doi:10.1007/s10552-008-9168-z.

Masculine containment, relationships and men’s mental health

Content note: This article discusses suicidal thoughts and suicide. If you or someone else is in immediate danger, call 000. Support contacts are provided below.

The phrase “masculine containment” appears in Alex Charfen’s podcast and work with The Brotherhood Society. Charfen describes it as staying present, aware, grounded and curious when pressure rises, especially during a difficult conversation. He asks men to notice the urge to react, defend, push back or withdraw, and to choose a more considered response. [1, 2]

The word containment can sound as if men should keep their emotions inside. For this article, it is important to distinguish emotional regulation from suppression, stonewalling or control over another person. Healthy containment means recognising and regulating your own emotions well enough to express them honestly and safely. It does not mean carrying every problem alone or accepting mistreatment.

This is a relationship and personal-development framework, not a formal clinical diagnosis or a proven stand-alone treatment for depression or suicide risk. It may offer useful language for reflecting on conflict and connection, but it does not replace mental health care, couples counselling or practical support when these are needed.

Why relationships matter to men’s wellbeing

A close relationship can be a major source of belonging, affection, daily contact and emotional support. When a relationship is distressed or ends, a man may experience grief, loneliness, fear, shame, anger, changes in family life, financial pressure or reduced contact with children. Several of these pressures may arrive together.

Some men have a small support network outside their partner. This can make a separation or a period of conflict feel like the loss of both a relationship and a main source of connection. It may also be harder to speak about vulnerability when a man believes he should be self-reliant or should already have solved the problem. These patterns do not describe every man, and they do not mean that every relationship difficulty leads to a mental health crisis.

A relationship ending is not, by itself, a diagnosis or a prediction of suicide. Suicidal distress can arise through many interacting factors, including depression, anxiety, trauma, substance use, financial stress, disability, violence, isolation and previous self-harm. Every person’s situation is different.

What Australian data tell us

In the latest ABS data available for this article, for deaths registered in 2025, problems in spousal relationship circumstances, including separation, divorce, arguments and domestic violence situations, were recorded as a risk factor in 28.6% of male suicide deaths. They were the third most commonly recorded risk factor for males overall and the most common recorded risk factor among males aged 25–44, where they appeared in 36.6% of deaths. The ABS notes that several risk factors may be recorded for one death; this is not evidence that relationship problems alone caused a death. The 2025 death figures are preliminary and may be revised as coronial investigations are completed. [3]

Recent Australian survey findings also show why a relationship breakdown can be an important time to offer support. In the Ten to Men study’s 2024–2025 survey, 30.8% of men who had experienced a relationship breakdown in the previous 12 months reported recent thoughts of being better off dead or hurting themselves, compared with 14.4% of men without a recent breakdown. Past-year suicidal thoughts were reported by 18.3% and 5.2%, respectively; past-year suicide attempts by 6.8% and 0.9%. After adjustment for other factors, recent breakdown was still associated with a higher likelihood of recent suicidal thoughts. These are group-level survey findings, not predictions about an individual, and they show an association rather than proving that the breakup caused suicidal distress. [4]

A 2025 Australian cohort study of 14,610 men found that recent relationship breakdown was associated with 82% higher odds of recent suicidal ideation after adjustment for other factors. The association did not differ by age, social support, harmful alcohol use or endorsement of self-reliance or emotional control; relationship breakdown did not predict suicidal ideation at a later survey wave once the immediate experience of suicidal ideation was taken into account. This points to the value of timely support during a period of acute distress, without treating a breakup as a certain or lasting predictor. [5]

A 2025 systematic review and meta-analysis of 75 studies from 30 countries also found higher odds of suicidal thoughts, attempts and suicide deaths among separated or divorced men compared with married men. The authors noted differences in study methods and gaps in evidence, particularly for non-marital relationships. [6]

These figures should be read with care. A percentage of deaths where a factor was recorded is not the same as a suicide rate among separated men. Neither statistic says that a partner is responsible for a suicide, or that a person experiencing a breakup will become suicidal. The practical message is that relationship distress can mark a period when compassionate check-ins and accessible support are especially important.

Where containment may help in a relationship

Conflict can quickly become a loop. One person raises a concern; the other feels criticised and becomes defensive, argues, tries to fix the issue immediately or shuts down. The first person may then feel ignored or unsafe and push harder. Both can end up more isolated, even when each wants connection.

The containment idea asks a man to notice his own part in that moment. For example:

  1. Notice the pressure. What is happening in your body? Are you tightening, raising your voice, interrupting, feeling an urge to leave, or preparing a counterargument?
  2. Pause before responding. Take a breath or ask for a short break if you need one. Agree on when you will return to the conversation so the pause does not become indefinite withdrawal.
  3. Name what is happening for you. “I’m getting defensive because I feel criticised. I want to understand what you’re saying.”
  4. Listen to understand. Reflect back the concern before explaining your view. Ask what the other person needs you to understand.
  5. Speak honestly and set a boundary. Staying calm does not require agreeing with everything, taking responsibility for another adult’s emotions, or remaining in an unsafe conversation.
  6. Repair and follow through. If you have hurt someone, acknowledge the impact, apologise without qualification and make a practical change. If you need help with recurring conflict, consider a GP, psychologist or relationship counsellor.

This is not a demand that men should be endlessly calm while others express emotion. Relationships require mutual respect, responsibility and room for both people’s experience. Containment should never be used to silence a partner, excuse coercion or violence, or pressure someone to stay in a harmful relationship. If there is abuse or fear for safety, prioritise safety and seek specialist support.

Containment is not the same as bottling things up

Keeping distress hidden may sometimes look like composure from the outside. A man might instead become irritable, withdraw from friends, work excessively, take more risks, use more alcohol or drugs, or feel unable to sleep. These changes are not proof of depression, but a persistent change from someone’s usual behaviour is a reason to check in.

Research on masculinity and emotion regulation describes a complex relationship: expectations about toughness and self-reliance may affect how some men respond to emotions, but masculinity is not one fixed thing and does not affect every man in the same way. A recent scoping review found that stronger conformity to some masculine norms was associated with lower psychological help-seeking and treatment engagement, while also recommending strength-based approaches that build on men’s values and capacities. [7]

A small Australian qualitative study of 22 men aged 19–30 who had experienced a breakup described how grief, sadness, anger and other emotions could build into overwhelm for some. Participants also described recovery through different strategies, including expression, social support and giving attention to their own needs. This study offers insight into experiences; its small sample cannot represent every man or relationship. [8]

In practice, healthy containment can include saying: “I’m not coping as well as I’ve let on.” It can mean tolerating the discomfort of a vulnerable conversation, asking for help, and letting trusted people support you. Reaching out is not a failure of self-control; it is one way to take responsibility for your wellbeing.

How to check in with a man who may be struggling

A friend, brother, colleague or family member does not need perfect words. Notice a change and ask directly: “You haven’t seemed yourself lately. How are things really going?” Listen without rushing to judge or solve everything. If you are concerned about suicide, ask clearly whether he is thinking about suicide. Stay with him, help him connect with a health professional or crisis service, and involve someone he trusts. If there is immediate danger, call 000.

If you are the man going through relationship pain, try not to make one person your only source of support. Tell someone you trust what is happening. A GP can help assess mood, sleep, alcohol or drug use, safety and treatment options. A psychologist or counsellor can help with grief, emotional regulation, relationship patterns and recovery after separation.

Support in Australia

  • Immediate danger: call 000 or go to an emergency department.
  • Lifeline: 13 11 14, 24 hours a day (lifeline.org.au).
  • Suicide Call Back Service: 1300 659 467, 24/7 telephone and online counselling (suicidecallbackservice.org.au).
  • MensLine Australia: 1300 78 99 78, telephone and online counselling for men (mensline.org.au).
  • 1800RESPECT: 1800 737 732 for confidential support regarding domestic, family and sexual violence (1800respect.org.au).
  • Your GP: a practical first point of contact for mental health assessment and referrals.

A steadier kind of strength

Masculine containment, as Alex Charfen discusses it, is best understood as a prompt to take responsibility for one’s own reactions while staying emotionally present with others. Its value is not in asking men to suppress pain or manage a partner. It is in making room for honesty, listening, boundaries, repair and help-seeking.

That kind of presence can support healthier relationships. It can also help a man recognise when a relationship problem has become part of a larger mental health crisis and reach for support before he is alone with it.

This article provides general information and is not a substitute for individual medical, psychological or relationship advice.

References

  1. Alex Charfen. The Masculine Containment Podcast, episode 2, “Masculine Containment Defined: The Missing Discipline for Modern Men.”
  2. Alex Charfen. Masculine Containment: official overview and podcast; see also What Is Masculine Containment? with Alex Charfen.
  3. Australian Bureau of Statistics. Intentional self-harm (suicide) deaths, 2025. Preliminary registered-death data; see male risk factors by age.
  4. Gasser C, Scurrah K, Woldegiorgis M, et al. Intimate partner relationship breakdown and the risk of suicidal thoughts and behaviours in men. Ten to Men Snapshot Series no. 5. Australian Institute of Family Studies; 2026.
  5. Wilson MJ, Mansour K, Seidler ZE, et al. Intimate partner relationship breakdown and suicidal ideation in a large representative cohort of Australian men. Journal of Affective Disorders. 2025;372:618–626. doi:10.1016/j.jad.2024.12.071.
  6. Wilson MJ, Scott AJ, Pilkington V, et al. Suicidality in men following relationship breakdown: a systematic review and meta-analysis of global data. Psychological Bulletin. 2025;151(7):819–860. doi:10.1037/bul0000482.
  7. Burns L, Olive L, Turner A, et al. The role of gender norm conformity in men’s psychological help-seeking and treatment engagement: a scoping review. Journal of Mental Health. 2026;35(2):230–248. doi:10.1080/09638237.2025.2512304.
  8. Wilson MJ, Oliffe JL, Macdonald JA, et al. Young men and relationship breakdown: a grounded theory. Qualitative Health Research. 2025. doi:10.1177/10497323251398369.

Movember: Men’s mental health

Movember: Men’s mental health and suicide prevention in Australia

Content note: This article discusses suicide. If you are in immediate danger, call 000. Support contacts are listed below.

Movember gives us a visible reminder to talk about men’s health. The moustache can start a conversation, but the more important work is noticing when someone is struggling, listening without judgement and helping them connect with support.

Mental health difficulties are common, treatable and not a personal failure. Suicide is complex: it rarely has one cause, and a difficult period does not mean a person is destined to reach crisis. Timely support, connection and practical help can make a difference.

The Australian picture

The latest Australian Bureau of Statistics (ABS) release available for this article covers deaths registered in 2025. It recorded 3,283 deaths by suicide, including 2,425 males—73.9% of the total. The male age-standardised rate was 17.3 deaths per 100,000 males. The 2025 figures are preliminary and may be revised as coronial investigations are completed. [1]

Age-standardised rates allow comparisons between populations with different age structures. The age-specific rates below are deaths per 100,000 people in the same age group; they describe population patterns, not an individual’s likelihood of suicide.

Age group Male suicide rate in 2025 (per 100,000) What the ABS reported about recorded risk factors
15–24 9.5–18.1 (15–19: 9.5; 20–24: 18.1) Suicide ideation was the most commonly recorded risk factor for people under 25. For children aged 5–17, recorded factors also included education, family and peer relationships, social environment and prior self-harm.
25–44 19.7–26.0 (25–29: 19.7; 30–34: 23.1; 35–39: 26.0; 40–44: 23.3) Relationship circumstances were the most commonly recorded risk factor in this age range. Psychoactive substance use was also frequently recorded.
45–64 23.0–26.8 (45–49 was the peak at 26.8) Mood disorders, including depression, were the most commonly recorded risk factor for people aged 45–84.
65–84 16.2–22.8 Rates varied across these age bands; mood disorders were commonly recorded. Illness, pain and disability may also affect wellbeing and quality of life.
85 and over 24.9 Limitation of activities due to illness or disability was the most commonly recorded risk factor in this age group.

These age bands summarise the ABS’s five-year age data. In 2025, the highest male age-specific rate was among men aged 45–49 (26.8 per 100,000); the largest proportion of male deaths occurred among men aged 35–39 (10.7%). Both figures matter, but they measure different things. [1]

The ABS also records risk factors mentioned in preliminary death registrations. In 2025, the most frequently recorded factors across all people who died by suicide were mood disorders (35.8%), suicidal ideation (30.7%), problems in spousal relationship circumstances (26.7%), a personal history of self-harm (24.3%), and anxiety or stress-related disorders (21.9%). Several factors can be recorded for one person. These are not proof that any single factor caused a death, and the data may change as investigations are finalised. [1]

Mental health concerns can look different from one man to another

In the ABS National Study of Mental Health and Wellbeing, conducted in 2020–2022, 18.3% of males aged 16–85 reported a 12-month mental disorder. Anxiety disorders were reported by 13.3%, affective disorders (including depression) by 6.5%, and substance-use disorders by 4.4%. The equivalent substance-use figure for females was 2.1%. The survey found the highest prevalence of any 12-month mental disorder among males aged 16–24 (32.4%); prevalence declined across older age groups. These are survey estimates, not current-year suicide rates, and they do not mean that everyone with a mental disorder is suicidal. [2]

Depression and anxiety may involve persistent low mood, loss of interest, worry, panic, irritability, poor concentration, sleep changes or feeling overwhelmed. Some men describe distress mainly through anger, pulling away from family or friends, working excessively, taking more risks, or relying more heavily on alcohol or other drugs. These signs are not a diagnosis, but a lasting change from someone’s usual self is a good reason to check in. [3]

There is no single cause

Mental health and suicide risk develop through an interaction of individual, social and economic circumstances. A person may be affected by one issue or many at once. Factors that can contribute to distress include:

  • depression, anxiety, trauma, other mental health conditions or a previous episode of self-harm;
  • relationship conflict, separation, family stress, loneliness or bereavement;
  • financial pressure, unemployment, job insecurity, workplace stress or legal problems;
  • harmful alcohol or other drug use, which can worsen mood, judgement and coping;
  • chronic illness, pain, disability, sleep problems or loss of independence;
  • discrimination, bullying, violence, social exclusion or barriers to culturally safe care;
  • limited social support, or feeling unable to ask for help.

These are possible contributors, not a checklist that predicts what one person will do. A 2025 analysis of the Australian Ten to Men longitudinal study found that the onset of suicidal thoughts was associated with depressive symptoms, disability, financial stress, lower education, sexual orientation and a history of partner violence. The study also found that suicidal thoughts remitted for many men over time, an important reminder that suicidal thinking can change and support can help. Associations in a study do not establish that a factor causes an outcome. [4]

Ideas about having to cope alone or always appear strong can make it harder for some men to talk openly or seek help. This is not true of every man, and strength, responsibility and care for others can also support recovery. A 2025 Australian review found a broad range of formal and informal services for men, while noting that evidence about their effectiveness remains uneven. Services are more useful when they are accessible, respectful and responsive to the person in front of them. [5]

How to support a mate, partner or family member

Movember shares the ALEC approach, developed by R U OK?, as a simple guide for a supportive conversation: [6]

  • Ask how he is going and mention a change you have noticed: “You haven’t seemed yourself lately. How are things really going?”
  • Listen without judgement or rushing to solve everything. Give him time to speak.
  • Encourage action: offer to help contact a GP, counsellor or trusted person, or to go with him to an appointment.
  • Check in again. A message or planned catch-up can show that your support continues after the first conversation.

If you are worried he may be thinking about suicide, ask clearly and calmly whether he is thinking about suicide. Take the answer seriously. You do not need to manage the situation alone: involve a trusted person and contact a crisis service or health professional. If there is immediate danger, call 000 or go to an emergency department.

Getting help in Australia

  • Immediate danger: call 000 or attend an emergency department.
  • Lifeline: call 13 11 14 for 24/7 crisis support. [7]
  • Suicide Call Back Service: call 1300 659 467 for 24/7 telephone and online counselling. [8]
  • MensLine Australia: call 1300 78 99 78 for telephone and online counselling for men. [9]
  • Beyond Blue: call 1300 22 4636 for mental health support and information. [10]
  • Your GP: can discuss symptoms, safety, treatment options and referrals. If you are not sure where to start, a GP appointment is a practical first step.

If you are supporting someone, stay connected and help them access care. If you are struggling yourself, you deserve support too. You do not have to wait until things feel unbearable before reaching out.

A Movember conversation can matter

Movember’s focus on prevention, early intervention and social connection is a useful invitation to check in, not only during November, but throughout the year. The first conversation does not need to be perfect. Ask, listen, help with one next step and follow up.

This article is general information and is not a substitute for individual medical or mental health advice.

References

  1. Australian Bureau of Statistics. Intentional self-harm (suicide) deaths, 2025. Preliminary registered-death data; includes age-specific rates and risk factors.
  2. Australian Bureau of Statistics. National Study of Mental Health and Wellbeing, 2020–2022.
  3. Movember. Spot the signs of poor mental health.
  4. Haregu T, Armstrong G. Understanding the onset and remission of suicidal thoughts in Australian men: Findings from the Ten to Men study. Australian & New Zealand Journal of Psychiatry. 2025. doi:10.1177/00048674251333572.
  5. Slade A, Reily NM, Fujimoto H, et al. Men’s mental health and suicide prevention service landscape in Australia: a scoping review. BMC Public Health. 2025;25:1593. doi:10.1186/s12889-025-22676-6.
  6. Movember. ALEC conversation strategy. Movember credits R U OK? for developing the ALEC model.
  7. Lifeline Australia. Lifeline Crisis Support.
  8. Suicide Call Back Service. Get support.
  9. MensLine Australia. Contact MensLine.
  10. Beyond Blue. Men’s mental health.

Support Movember

Help stop men dying too young: support Movember

Every November, the moustache gives us a reason to start a conversation. But Movember is about much more than facial hair. It brings attention to the health issues that affect men and boys, and supports work in prostate cancer, testicular cancer, mental health and suicide prevention.

I’m raising funds for these causes because they touch the lives of our dads, brothers, sons, partners, friends and mates. A diagnosis, a difficult period with mental health, or the loss of someone to suicide can affect an entire family and community.

Why this matters

You may have seen the message that men die, on average, six years earlier than women. The figure depends on the population and source: Movember’s current Australian campaign reports around four years in Australia and 4.5 years globally. The difference is a reminder that men’s health deserves attention throughout the year, not only when a problem becomes hard to ignore.

Movember focuses on prostate cancer, testicular cancer, mental health and suicide prevention. Donations support programs and research across these areas. The charity also encourages men to look after their health, stay connected and reach out when they need support.

How you can help

If you’re able, please consider making a donation through my Mo Space. Every contribution helps support Movember’s work. Sharing the page or talking about men’s health with someone you care about also helps keep these issues in view.

Donate via my Mo Space:


QR Code


Thank you for supporting this cause: for all the dads, brothers, sons and mates in your life.

Together, we can help stop men dying too young.


Movember’s current information and cause areas: Movember Australia – Our cause and Movember Australia – FAQs.

Bladder neck contracture after TURP or laser prostate surgery

Why it happens, why it can recur, and how it may be treated

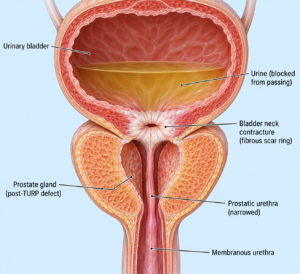
Transurethral resection of the prostate (TURP) and laser procedures such as photoselective vaporisation (PVP) or transurethral vaporisation (TUVP) are used to improve urine flow when an enlarged prostate obstructs the bladder outlet. In a small number of men, healing after surgery causes scar tissue to tighten at the bladder neck: the opening between the bladder and the prostate/urethra. This is called a bladder neck contracture (BNC) or bladder neck stenosis.

A BNC can cause a return of urinary symptoms after an initially successful operation. It is treatable, although some contractures return after treatment and a small group of men need several procedures or specialist reconstructive surgery.

This information is general and is not a substitute for assessment by your GP or urologist. The most suitable option depends on the exact site and length of narrowing, bladder function, previous procedures, continence, and general health.

How common is it?

The reported rate varies with the operation, the definition used, follow-up time, and the patients studied. A recent systematic review of randomised trials with at least two years of follow-up estimated BNC in about 3% after TURP and 9% after photo-selective laser vaporisation (PVP). The confidence intervals were wide, especially for PVP, so these figures should not be treated as a precise prediction for an individual patient. The European Association of Urology (EAU) guideline cites a broader range of approximately 0.3–9.7% for bladder neck stenosis after transurethral prostate surgery.[1,2]

“TUVP” is used for more than one vaporisation technique. Studies of older electrovaporisation, bipolar vaporisation and modern laser PVP are not interchangeable. For example, one small early study of transurethral vaporisation reported BNC in 3 of 30 patients; that result is too small and old to represent the risk from current laser surgery.[3] Your surgeon can explain which procedure was used and what the evidence for that specific technique shows.

Why can it develop?

The bladder neck can heal with excess scar tissue after surgical trauma, heat, or inflammation. The exact cause is not always clear. Factors associated with BNC in published studies include a smaller prostate or less tissue removed, infection around the time of surgery, smoking, diabetes or cardiovascular disease, longer operating time, and extensive treatment near the bladder neck. These are associations: they do not mean that a particular factor caused an individual person’s contracture.[2,4]

BNC often becomes apparent during the first months after surgery, but it can present later. Symptoms may include:

  • a weaker, slower or interrupted stream;
  • straining, hesitancy, or taking longer to pass urine;
  • a feeling that the bladder has not emptied;
  • frequent or urgent urination, or getting up at night;
  • recurrent urinary infections; or
  • inability to pass urine, which needs urgent medical attention.

These symptoms can also be caused by prostate regrowth, urethral narrowing, infection, an underactive bladder, or other bladder conditions. Testing is needed to identify the cause.

How is it assessed?

Assessment commonly includes a history, examination, urine testing, measurement of urine flow (uroflowmetry) and the amount left in the bladder after voiding (post-void residual). Cystoscopy, a small camera passed through the urethra, usually confirms whether the bladder neck is narrowed and whether a scope can pass. Depending on the situation, imaging such as a retrograde urethrogram or a bladder/urethral contrast study may help map the narrowing. Kidney and bladder imaging or kidney blood tests may be appropriate if there is significant retention, infection, or concern about the upper urinary tract.

Treatment options

Treatment is tailored to the narrowing and the person’s symptoms and priorities. A short, non-obliterated contracture is usually approached differently from a long, dense scar or a bladder neck that has closed completely.

Dilatation

A narrow area can sometimes be gently stretched with instruments or a balloon. This is relatively straightforward and can improve flow, but the scar may tighten again. In some cases a planned programme of intermittent self-catheterisation is discussed to help keep the opening stable. It is not suitable or acceptable for everyone.

Endoscopic incision or resection

A surgeon can use a small endoscope to cut (incise) the scar, or remove some of the scar tissue, using an electrical knife or laser. This is a common first treatment for a non-obliterated BNC. A catheter is often left temporarily while the area heals.

A first treatment may be enough, but recurrence is a recognised problem. EAU evidence summaries report patency after the first endoscopic treatment of about 58% following transurethral resection and 72% following incision in the cited studies. Those results come from varied, generally small observational series and should not be taken as a guaranteed personal outcome.[5] Repeated incision or dilation may be reasonable for some men with a passable narrowing; it can relieve symptoms or stabilise the opening, but each recurrence needs reassessment. A completely obliterated bladder neck is unlikely to be cured by routine endoscopic cutting and blind attempts can be unsafe.[5]

Scar-modulating injections

Steroid or mitomycin C injections have been used with endoscopic incision in selected recurrent cases. Evidence is mixed and largely based on retrospective series. Mitomycin C is not a routine, risk-free add-on: a multicentre study reported serious complications in 7% of treated patients, including tissue injury and fistula, with some requiring major further treatment.[6] If considered, the potential benefit and uncommon but significant risks should be discussed explicitly with a reconstructive urologist.

Bladder neck reconstruction

When a contracture repeatedly returns, is long or dense, or is completely closed, a reconstructive operation may be considered. The goal is to create a wider, durable outlet while protecting the bladder, ureters and continence mechanism as much as possible. The choice depends on the site and extent of scar, previous operations or radiotherapy, bladder function, continence, and surgeon expertise.

Options include a Y–V or T-plasty, in which healthy bladder tissue is rearranged to widen the outlet, with scar tissue released or removed as needed. The EAU guideline reports patency rates of 83–100% in published series, with follow-up of 14–45 months; new incontinence was reported in up to 14%. These results are from selected patients and small observational studies, not randomised comparisons.[5]

In selected complex cases, reconstruction can be performed with a robot-assisted approach. The magnified view and instruments that articulate inside the pelvis may help the surgeon work precisely around the bladder neck. Robotic reconstruction is specialised surgery, not a guarantee against recurrence or incontinence. In a systematic review of ten small case series (119 men with different causes and techniques), pooled patency was 80%; new incontinence was reported in 17% of the subset with suitable continence data. Follow-up was relatively short and the evidence was heterogeneous, so longer-term results remain important.[7]

Buccal mucosa graft reconstruction: an emerging option

Buccal mucosa is the moist lining inside the cheek. It can be taken as a graft and used to augment a narrowed or damaged urinary passage. For a severe bladder neck defect, a graft may be placed as an onlay/inlay to create a wider channel rather than simply cutting the scar again. The graft is harvested from the mouth, so temporary cheek soreness, altered mouth sensation, or tightness are possible in addition to the risks of the urinary reconstruction.

A/Prof Devang Desai and colleagues in Toowoomba have reported a robot-assisted reconstruction for complete bladder neck obliteration after TURP using two cheek grafts, one placed anteriorly and one posteriorly, to create a “double-faced” repair. In their reported case, the patient was voiding without incontinence at seven months, with a maximum flow of 23 mL/s. This is an innovative case report and conference abstract, not yet evidence that the technique is superior to established reconstruction or that results will be the same for other patients. The authors themselves note that longer follow-up is needed.[8,9]

This approach may be discussed by a reconstructive urologist for selected men with a complex or completely obliterated bladder neck, particularly after less invasive treatments have failed. It is not needed for most BNCs, and access to the technique depends on specialist experience and individual circumstances.

Catheter drainage and other options

If the bladder cannot empty, a urethral catheter or a suprapubic catheter (placed through the lower abdominal wall) may be needed, temporarily or longer term. A suprapubic catheter can be a practical choice while planning further treatment or when reconstruction is unsuitable or not wanted. In very complex cases, especially when the bladder itself is severely damaged, other forms of urinary diversion may be considered, but this is uncommon for BNC after routine TURP or vaporisation.

Continence and the possibility of further treatment

Opening a tight bladder neck can reveal leakage that was previously masked by the obstruction, or can worsen existing urinary incontinence. This may happen after endoscopic treatment as well as reconstruction. Some men remain dry; others may need continence treatment later. Before proceeding, ask your urologist how the contracture, any previous prostate surgery or radiotherapy, and your existing continence affect the plan.

A recurrence does not mean that you have done anything wrong. Scar healing is variable. If narrowing returns, the next step should be based on updated assessment rather than automatically repeating the same procedure. A reconstructive urologist can help weigh another endoscopic treatment against reconstruction, catheter drainage, or other options.

When to seek urgent help

Seek urgent medical care if you are unable to pass urine, develop fever or shaking chills with urinary symptoms, or have severe lower abdominal pain. Acute retention can require prompt bladder drainage.

References

  1. Mac Curtain BM, et al. Bladder neck contracture post-treatment for benign prostatic hyperplasia: a systematic review and meta-analysis of randomized clinical studies. International Urology and Nephrology. 2025. https://doi.org/10.1007/s11255-025-04648-2
  2. European Association of Urology. EAU Guidelines on Urethral Strictures: Definition, epidemiology, aetiology and prevention. https://uroweb.org/guidelines/urethral-strictures/chapter/definition-epidemiology-aetiology-and-prevention
  3. Chang PL, et al. Clinical outcome at 3 months after transurethral vaporization of prostate for benign prostatic hyperplasia. PubMed. https://pubmed.ncbi.nlm.nih.gov/9255294/
  4. Gül M, et al. Bladder neck contracture following transurethral surgery of prostate: a retrospective single-center study. PubMed. https://pubmed.ncbi.nlm.nih.gov/38189837/
  5. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease management in males—posterior urethral stenosis and bladder neck stenosis. https://uroweb.org/guidelines/urethral-strictures/chapter/disease-management-in-males
  6. Redshaw JD, et al. Intralesional injection of mitomycin C at transurethral incision of bladder neck contracture may offer limited benefit: TURNS Study Group. Journal of Urology. https://pubmed.ncbi.nlm.nih.gov/25200807/
  7. Zhang TR, et al. Summarizing the evidence for robotic-assisted bladder neck reconstruction: systematic review of patency and incontinence outcomes. Asian Journal of Urology. 2024;11(3):341–347. https://doi.org/10.1016/j.ajur.2023.08.007
  8. Desai D, Munien K, Namdarian B. Robotic bladder neck reconstruction using a double-faced buccal mucosal graft: a novel approach to complete bladder neck obliteration. Urology Video Journal. 2023. https://doi.org/10.1016/j.urolvj.2023.100247
  9. Desai D, Munien K, Namdarian B. Robotic bladder neck reconstruction using a double-faced buccal mucosal graft—a novel approach to complete bladder neck obliteration. BJU International. 2025;135(Suppl 2): abstract. https://doi.org/10.1111/bju.16629

This article is for general education and does not replace an individual consultation. Treatment choices, likely outcomes and risks should be discussed with the treating urologist.

Prostate cancer, Movember and the moustache: a conversation worth having

Each November, a moustache can do more than change a face. It can open a conversation that might encourage someone to learn their risk, ask about testing or support a person affected by prostate cancer.

Movember is a good time to talk about prostate cancer, but the message matters all year. The aim is not to alarm every man or suggest that everyone needs the same test. It is to make sure people know the facts and can make an informed decision with their doctor.

Prostate cancer in Australia

Prostate cancer is common. The Australian Institute of Health and Welfare (AIHW) estimated that around 29,000 men would be diagnosed in 2025, making it the most commonly diagnosed cancer in Australian men and accounting for about 30% of cancers diagnosed in men that year. These are projected figures, not a final count. Around 1 in 5 men are expected to be diagnosed with prostate cancer during their lifetime.

The outlook is often very good: the AIHW reports a 96% five-year relative survival rate for prostate cancer diagnosed in 2017–2021. That is a population statistic, not a prediction for any one person. Prostate cancers vary: some grow slowly and may never cause harm, while others can be aggressive and need timely treatment. Early assessment can help identify cancers that are more likely to matter, while careful risk assessment helps avoid unnecessary tests and treatment.

What does Movember mean?

Movember began with a simple idea: grow a moustache, raise funds and get people talking about men’s health. It has grown into a global movement supporting men’s health, including prostate cancer, testicular cancer, mental health and physical activity.

The moustache is a friendly, visible conversation starter. Someone may ask, “Why the Mo?” and that gives you a chance to mention prostate cancer, ask a friend whether he knows his family history, or check in with someone who is going through diagnosis or treatment. A moustache cannot detect cancer, and growing one does not replace medical advice. Its value is in helping make a sometimes awkward subject easier to raise.

How is prostate cancer found?

Prostate cancer often causes no symptoms in its early stages. Urinary symptoms such as a weaker stream, needing to urinate more often or difficulty starting are common with ageing and an enlarged prostate, and do not by themselves mean cancer. Blood in the urine or semen, persistent pain, or a new urinary problem should be discussed with a doctor.

The first step in early detection is usually a conversation about personal risk and the possible benefits and downsides of testing. A prostate-specific antigen (PSA) blood test measures a protein made by the prostate. PSA can rise for reasons other than cancer, including prostate enlargement, infection or inflammation. A raised result is not a diagnosis, and a low result does not rule out every cancer.

Australia’s updated national early-detection guidelines, approved by the National Health and Medical Research Council in May 2026, recommend discussing individual risks, preferences, benefits and possible harms before starting PSA testing. For men who choose testing, the guidelines recommend offering it every two years from age 50 to 69 for those not at higher risk, and from age 45 for those at higher risk. Higher risk includes a relevant family history, a confirmed BRCA2 gene mutation or Black sub-Saharan ancestry. Men aged 70 and over should discuss whether to continue testing in light of their health and preferences. These are discussion points, not a substitute for individual medical advice.

If a PSA result is higher than expected, a doctor may repeat the test and consider other information, such as age, symptoms, family history and examination findings. A urologist may recommend a prostate MRI to help decide whether a biopsy is appropriate and, if so, where to take samples. A biopsy is currently the test that confirms a diagnosis and provides information about the cancer’s grade. Not everyone with an elevated PSA needs a biopsy, and no test is perfect. If cancer is found, the next steps depend on its grade and stage, the person’s health and their preferences; some lower-risk cancers can be monitored with active surveillance.

Make November a reason to check in

This November, consider wearing blue when you walk, jog, run or volunteer at your local parkrun. Invite a friend or family member to join you. It is a simple way to show support, start a conversation and make space for men’s health alongside the usual weekend catch-up. This is a community invitation, not a claim that parkrun is running an official Movember campaign.

If you are unsure whether PSA testing is right for you, speak with your GP. Mention your age, family history and any symptoms, and ask what a result could mean and what the next steps might be. If someone close to you has prostate cancer, listening and offering to go with them to an appointment can be a practical form of support.

Grow a Mo, wear blue, or simply start the conversation. The moustache is the prompt; informed choices and looking out for one another are the point.

This article provides general information and is not a substitute for advice from your doctor. Testing decisions should be made with a health professional who can consider your personal circumstances.

References and further information

  1. Australian Institute of Health and Welfare. Cancer data in Australia: Overview of cancer in Australia, 2025.
  2. Australian Institute of Health and Welfare. Cancer outcomes improving overall.
  3. Prostate Cancer Foundation of Australia. PSA testing and the 2026 Australian early-detection guidelines.
  4. Prostate Cancer Foundation of Australia. Diagnosis of prostate cancer.
  5. Movember. About Movember.
  6. parkrun Australia. Find a parkrun event.

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

A moustache can start a conversation. A conversation can sometimes save a life.

Every November, moustaches begin appearing on faces around Australia and across the world. Some are magnificent. Some are questionable. Some probably deserve their own urological assessment.

But behind the facial hair lies an important message.

Movember is about getting men talking about their health.

What began in Melbourne in 2003 with 30 men growing moustaches has developed into an international men’s health movement focusing particularly on prostate cancer, testicular cancer, mental health and suicide prevention. Movember reports that it has funded more than 1,320 men’s health projects around the world.

And few recent stories demonstrate the importance of men paying attention to their health better than that of King Charles III.


First, an important clarification: King Charles does NOT have prostate cancer

This point has frequently been confused in media and social-media discussions.

In January 2024, Buckingham Palace announced that King Charles was receiving treatment for an enlarged prostate.

This was benign prostatic enlargement, commonly called benign prostatic hyperplasia or BPH. It is extremely common as men get older and is not prostate cancer.

The King underwent a planned hospital procedure for his enlarged prostate.

During this episode of care, however, doctors identified a separate abnormality. Further investigations subsequently diagnosed a form of cancer.

Buckingham Palace specifically confirmed that the King’s cancer was not prostate cancer. The precise type of cancer has remained private.

That distinction matters.

But so does what happened next.


A prostate problem led to something else being discovered

The King’s story provides an interesting lesson for men’s health.

He sought medical attention for a prostate problem.

He underwent investigation and treatment.

During that process, doctors discovered another potentially important medical condition.

In February 2024 Buckingham Palace announced that the King had begun a programme of regular cancer treatments and temporarily reduced his public-facing duties.

By April 2024, following treatment and recuperation, he was able to return to public-facing duties.

The exact cancer treatment has never been publicly disclosed, and it would therefore be inappropriate to speculate whether he has received surgery, radiotherapy, chemotherapy, immunotherapy or another form of treatment.

More recently, the King has continued to speak publicly about his cancer experience. In December 2025 he announced that, following early diagnosis, treatment and adherence to medical advice, his treatment schedule could be reduced in the following year.

In June 2026 he and Queen Camilla hosted a reception marking the 125th anniversary of Cancer Research UK, of which the King has been Patron since 2024.

His message has increasingly centered on a simple theme:

Early diagnosis matters.


The other royal problem: an enlarged prostate

For a urologist, the first part of the King’s story is equally important.

An enlarged prostate is extraordinarily common.

As the prostate enlarges, it can compress the urethra and interfere with the passage of urine.

Men may notice:

  • a slower urinary stream
  • difficulty starting urination
  • stopping and starting
  • straining
  • feeling that the bladder has not emptied completely
  • getting up several times during the night
  • urgency or frequency
  • occasionally an inability to pass urine at all.

These symptoms do not automatically mean prostate cancer.

Most commonly they are associated with benign prostate enlargement.

But that does not mean they should simply be accepted as part of getting older.


“It’s probably just my prostate”

Possibly.

But that is precisely why it is worth having it checked.

Assessment of urinary symptoms may include a discussion about symptoms and medications, examination, urine testing, kidney function, PSA testing where appropriate, urinary flow measurement, ultrasound assessment of bladder emptying and occasionally further investigations.

The objective is not simply to find prostate cancer.

It is to work out why the urinary system is behaving differently.


What about prostate cancer?

This is where Movember becomes particularly relevant.

Prostate cancer remains the most commonly diagnosed cancer in Australian men. Australian Institute of Health and Welfare data indicate that prostate cancer accounted for approximately 28% of cancers diagnosed in Australian males in 2024.

AIHW’s updated projections estimate approximately 26,397 prostate cancer diagnoses in Australia during 2026, although it is important to recognise that this is a projection rather than a final observed case count.

Movember estimates that approximately one in five Australian men will be diagnosed with prostate cancer during their lifetime.

And there is another important difference between prostate cancer and benign enlargement:

Early prostate cancer frequently causes no urinary symptoms at all.

Waiting until something hurts or the urine flow deteriorates is therefore not an effective prostate cancer detection strategy.


The PSA conversation

A PSA blood test can help identify men who may require further investigation for prostate cancer.

But PSA is not simply a “cancer test”.

PSA can be elevated for several reasons, including:

  • benign prostate enlargement
  • prostatitis or inflammation
  • urinary infection
  • recent instrumentation
  • urinary retention
  • and prostate cancer.

An abnormal PSA therefore does not automatically mean cancer.

Similarly, decisions about PSA testing should consider a man’s age, family history, previous PSA results, general health and individual risk factors.

The important step is having the conversation with your GP or urologist rather than avoiding the subject altogether.


And if prostate cancer is found?

Modern prostate cancer treatment is no longer a simple choice between “operate” and “do nothing”.

Depending upon the PSA, MRI findings, biopsy grade, tumour volume, stage, age and general health of the patient, options may include:

Active surveillance for suitable low-risk disease.

Robotic-assisted radical prostatectomy for appropriate localised cancers.

Radiation therapy, sometimes combined with hormonal treatment.

Focal therapies in carefully selected patients and specialised settings.

Androgen deprivation and newer androgen-receptor targeted treatments for more advanced disease.

Chemotherapy and radioligand therapies for selected advanced cancers.

The right treatment is increasingly personalised to both the biology of the cancer and the priorities of the man sitting in front of us.


Treatment is not only about surviving cancer

This is another area in which organisations such as Movember have made an important contribution.

Men understandably want their cancer controlled.

But they also care about what happens afterwards.

Will I leak urine?

Will I still have erections?

What happens to ejaculation and orgasm?

Can I continue working?

How will treatment affect my relationship?

Will I still feel like myself?

Movember has invested not only in prostate cancer research but also in projects examining quality of life, urinary function, sexual function and outcomes following treatment. The Prostate Cancer Outcomes Registry Australia and New Zealand, for example, collects patient-reported outcomes including urinary, bowel and sexual function after prostate cancer diagnosis and treatment.

These aren’t embarrassing side issues.

They are part of treating the whole man.


So what does King Charles have to do with Movember?

Quite a lot, despite the fact that he does not have prostate cancer.

His story began with something millions of older men experience:

an enlarged prostate.

Instead of ignoring it, he sought treatment.

That interaction with the healthcare system resulted in another cancer being discovered.

And by publicly announcing his prostate treatment and subsequent cancer diagnosis, the King did something particularly useful for men’s health:

he made it easier to talk about it.

That is essentially what Movember has been trying to achieve for more than two decades.

A moustache is simply the billboard.

The conversation is the important bit.


My Movember message to men

If your urinary stream isn’t what it used to be, get it checked.

If you’re getting up repeatedly during the night, ask why.

If you’re struggling with erections, don’t be embarrassed to mention it.

If you notice a testicular lump, don’t wait.

If prostate cancer runs in your family, discuss your individual risk.

And if you’ve been putting off that conversation about PSA testing, perhaps Movember is a good time to have it.

Men are remarkably good at servicing cars, replacing batteries, checking tyre pressures and investigating strange noises coming from engines.

We are sometimes considerably less enthusiastic when the strange noise is coming from ourselves.

This Movember, grow the moustache if you wish.

But more importantly:

Have the conversation.
Know your prostate.
Know your risk.
And don’t ignore a change in your body simply because it’s embarrassing to talk about.

Your prostate may be small.

Its ability to cause trouble is disproportionately ambitious.


References and further reading

  1. The Royal Family. A Statement from Buckingham Palace. 5 February 2024. Buckingham Palace confirmed that a separate cancer was discovered during treatment for benign prostate enlargement.
  2. The Royal Family. The King returns to public-facing duties. April 2024.
  3. The Royal Family. A message from The King in support of Stand Up To Cancer. December 2025.
  4. The Royal Family. The King and Queen host a reception for Cancer Research UK. June 2026.
  5. Australian Institute of Health and Welfare. The health of men in Australia. Prostate cancer statistics and Australian cancer burden.
  6. Australian Institute of Health and Welfare. Cancer data in Australia: Prostate cancer projection method changes and updated long-term projections. Updated July 2026.
  7. Movember. Prostate Cancer: Prostate Cancer Action, Innovation & Collaboration. Australian prostate cancer statistics and research programs.
  8. Movember. Our Story. History of the Movember movement from Melbourne in 2003.
  9. Movember. Prostate Cancer Outcomes Registry Australia and New Zealand. Patient outcomes and quality-of-life research.

Medical disclaimer

This article provides general information and should not replace individual medical assessment. Urinary symptoms, an abnormal PSA or concerns about prostate cancer should be discussed with your GP or urologist.

Can You Train Your Bladder Into Bad Habits?

Bladder training and pelvic floor rehabilitation

Bladder training and pelvic floor muscle training are often recommended for urinary urgency and leakage. They address different parts of bladder control, though, and the right approach depends on the symptoms and on whether the pelvic floor muscles are weak, overactive, or both.

A pelvic floor that works well needs to be able to contract when support is needed and relax when it is time to pass urine or stool. More squeezing is not always better.

What is bladder training?

Bladder training is a structured way of gradually changing toileting habits and responding to urgency. It aims to reduce “just in case” trips, increase the time between voids when appropriate, and help a person regain confidence that an urge can settle without immediately rushing to the toilet.

It is a supported behavioural treatment. It does not mean ignoring pain, forcing yourself to hold on for a long time, or following a rigid schedule regardless of what your body is telling you.

A bladder diary for a few days can help record fluid intake, urination times and volumes, urgency, leakage and night-time waking. Together with a clinician, a person can use this information to choose a realistic starting interval. The interval can then be extended gradually, often by small steps, while using calm breathing and urge-control strategies. Adequate fluid intake, avoiding excessive caffeine, and addressing constipation may also help. Fluid restriction should not be used without advice, as too little fluid can cause dehydration and concentrated urine.

When may bladder training help?

Bladder training is commonly offered as an initial treatment for people with:

  • Overactive bladder (OAB) symptoms: urgency, with or without urgency leakage, usually accompanied by increased daytime frequency and/or waking at night to urinate, when infection or another obvious cause has not been found.
  • Urinary frequency or urgency: including frequent “just in case” voiding or difficulty delaying a trip to the toilet.
  • Mixed urinary incontinence: a combination of leakage with urgency and leakage with activities such as coughing or exercise. Bladder training can be combined with pelvic floor muscle training.
  • Urgency without leakage: urgency can still be bothersome and may respond to behavioural strategies.

The International Continence Society defines OAB as a symptom syndrome. It is not the same thing as a urodynamic finding called detrusor overactivity. Some people with OAB symptoms show involuntary bladder contractions during urodynamics; others do not. Urodynamics is not needed for every person with typical OAB symptoms. Overactive Bladder

What does “sensory overactive bladder” mean?

“Sensory urgency” or “sensory OAB” is sometimes used when a person feels an early or unusually strong need to pass urine, often at relatively small bladder volumes, but testing does not show involuntary detrusor contractions. The term is used inconsistently and is not a separate diagnosis in the current ICS symptom definition.

When infection, pain-related bladder conditions, obstruction, significant residual urine and other relevant causes have been considered, a person with urgency or increased bladder sensation may still be offered bladder training according to their symptoms and goals. A normal urodynamic study does not mean that the symptoms are imagined, and a finding of detrusor overactivity does not by itself determine which treatment is best.

Practical urge-control strategies

When an urge arrives before the planned time:

  1. Pause and stop moving if it is safe to do so. Sit or stand comfortably.
  2. Breathe slowly and allow the abdomen and pelvic floor to soften.
  3. Avoid rushing, which can increase the sense of urgency.
  4. If you can contract and fully release the pelvic floor comfortably, a few brief, gentle contractions may help suppress the urge. Then let the muscles go completely.
  5. When the urgency has eased, walk calmly to the toilet if you still need to go.

The approach should be adjusted if contractions cause pain, increase urgency, or make it harder to empty. Repeatedly delaying urination despite pain, a very full bladder, or difficulty passing urine is not the aim.

Pelvic floor muscle training for stress urinary incontinence

Stress urinary incontinence (SUI) is leakage with coughing, sneezing, laughing, lifting or exercise. It commonly occurs when the urethral closure mechanism and its support do not respond adequately to a rise in abdominal pressure.

For SUI, pelvic floor muscle training (PFMT) aims to improve the muscles’ strength, endurance, timing and coordination. Guidelines recommend a supervised programme for at least three months as an initial treatment for women with SUI or mixed incontinence. Training is also commonly used in men recovering from prostate surgery, with advice tailored to their operation and recovery. NICE

A correct contraction should feel like a gentle closing and lifting around the openings of the pelvic floor. It should not feel like pushing down, holding your breath, or tightening the buttocks and thighs instead. Each contraction needs a complete release afterwards. A pelvic health physiotherapist or clinician can check that the muscles are being used correctly and can tailor the programme to the person.

For leakage with a cough or lift, a physiotherapist may teach a brief pelvic floor contraction just before and during the effort. This is sometimes called “the knack.” It is a coordination strategy, not a substitute for a progressive strengthening programme.

PFMT can also support urgency control when a person can contract and relax the muscles correctly. It may be combined with bladder training for OAB or mixed symptoms. However, a high number of forceful contractions is not suitable for everyone.

When pelvic floor relaxation may be the priority

Some people have pelvic floor muscles that are persistently tense, tender, difficult to coordinate, or unable to relax fully during urination or bowel movements. This may be described as a high-tone, overactive or non-relaxing pelvic floor. Symptoms can include pelvic pain or pressure, difficulty starting the stream, straining, a stop-start stream, a feeling of incomplete emptying, constipation, pain with sexual activity, or urinary urgency and frequency. These symptoms have other possible causes as well, so assessment matters.

When examination suggests that the pelvic floor is overactive or does not relax appropriately, treatment may focus first on down-training and coordination, often with a pelvic health physiotherapist. This can include relaxed diaphragmatic breathing, awareness of pelvic floor release, comfortable toileting posture, avoiding straining, and addressing constipation or pain. Biofeedback may be used in selected cases. The aim is not to push or bear down forcefully, but to learn a comfortable release.

In this situation, repeatedly doing “Kegels” without assessment may aggravate pain, urgency or difficulty emptying for some people. The evidence for relaxation-based treatment is less extensive than the evidence supporting supervised strengthening for SUI, but guidelines support relaxation-focused pelvic floor therapy for selected functional emptying problems. Uroweb

Relaxation is not the opposite treatment for ordinary stress incontinence. If the main problem is leakage with exertion and the pelvic floor is weak or poorly coordinated, strengthening and timing are usually the relevant goals. If a person has both stress leakage and a tight, painful or poorly relaxing pelvic floor, a clinician or physiotherapist can sequence the treatment: first restore comfortable release and coordination where needed, then progress to strengthening without reinforcing excessive tension.

When to seek assessment

A clinician may review the symptom pattern, medications, fluid and caffeine intake, bowel habits, urine test, bladder diary, pelvic floor function and how well the bladder empties. Further tests are considered when the diagnosis is uncertain or when results could change management.

Seek medical advice rather than relying on bladder training alone if you have visible blood in the urine, painful urination or fever, new difficulty passing urine, a persistent weak stream, recurrent infections, significant pelvic pain, new neurological symptoms, or a sudden change in bladder control. These symptoms can have causes that need specific assessment.

Key points

  • Bladder training is a first-line behavioural option for urgency, frequency, OAB symptoms and many cases of mixed incontinence.
  • “Sensory OAB” is an imprecise term; urgency can be real and treatable even when urodynamics does not show detrusor overactivity.
  • Supervised pelvic floor muscle training is a first-line treatment for SUI, but correct contraction and full relaxation matter.
  • A tight or non-relaxing pelvic floor may need relaxation and coordination work before strengthening.
  • The best programme is based on an assessment, not on the assumption that every pelvic floor needs more squeezing.

This article provides general information and is not a substitute for an individual assessment or treatment advice.

References

  1. National Institute for Health and Care Excellence (NICE). Urinary incontinence and pelvic organ prolapse in women: management (NG123).
  2. NICE. Pelvic floor dysfunction: prevention and non-surgical management (NG210).
  3. European Association of Urology (EAU). Guidelines on Non-neurogenic Female LUTS: Disease Management.
  4. International Continence Society (ICS). Overactive bladder: terminology and public factsheet.
  5. American Urological Association/Society of Urodynamics, Female Pelvic Medicine & Urogenital Reconstruction. The AUA/SUFU Guideline on the Diagnosis and Treatment of Idiopathic Overactive Bladder (2024).
  6. McAuley JA, Mahoney AT, Austin MM. Clinical Practice Guidelines: Rehabilitation Interventions for Urgency Urinary Incontinence, Urinary Urgency, and/or Urinary Frequency in Adult Women. Journal of Women’s & Pelvic Health Physical Therapy. 2023;47(4):214–216. doi:10.1097/JWH.0000000000000287.