
Overactive Bladder and Intravesical Botulinum Toxin Injections: A Patient Guide
Overactive bladder can have a significant impact on everyday life. The sudden need to find a toilet, frequent trips to the bathroom, waking repeatedly at night and episodes of urinary leakage can interfere with work, travel, exercise, sleep and social activities.
When bladder training, pelvic floor therapy or prescription medicines have not provided adequate relief—or are unsuitable—a clinician may discuss minimally invasive treatments. One option is injection of botulinum toxin type A into the bladder wall. This article provides general disease and treatment information and does not recommend a particular product or brand.
What is overactive bladder?
Overactive bladder (OAB) is a condition characterised by urinary urgency, usually accompanied by increased urinary frequency and waking at night to pass urine (nocturia), with or without urgency urinary incontinence.
Typical symptoms include:
- A sudden, difficult-to-defer urge to urinate
- Passing urine more frequently than expected
- Waking several times during the night to urinate
- Leakage of urine before reaching the toilet
- Planning activities around access to toilets
Importantly, similar symptoms can sometimes be caused by urinary infection, bladder stones, bladder obstruction or other urinary tract conditions. Appropriate assessment is therefore important before treatment.
What are intravesical botulinum toxin injections?
Botulinum toxin type A is a prescription-only medicine with several medical uses. When injected into the bladder muscle, it reduces nerve signalling and involuntary bladder contractions. In appropriately selected patients, this may reduce urgency, urgency incontinence and urinary frequency. Individual responses vary, and benefit is not guaranteed.
Who might be considered for this treatment?
Intravesical botulinum toxin injections may be considered for patients with troublesome overactive bladder symptoms, particularly when conservative or medicine-based treatments have not provided sufficient benefit, have caused unacceptable adverse effects or are unsuitable.
Clinical guidelines include intradetrusor botulinum toxin among the minimally invasive options that may be discussed with appropriately selected patients. Selection requires consideration of potential benefits, alternatives and the risks of infection, incomplete bladder emptying and temporary catheterisation.
It may be particularly useful for patients experiencing:
- Severe urinary urgency
- Urgency urinary incontinence
- Frequent urination
- Significant nocturia
- Persistent symptoms despite bladder training
- Persistent symptoms despite pelvic floor rehabilitation
- An inadequate response to medications
- Unacceptable medication side effects
Some patients choose procedural treatment because they would prefer not to take long-term medication.
Other minimally invasive options for refractory OAB include sacral neuromodulation and tibial nerve stimulation.
Assessment before treatment
Before proceeding, your urologist will usually assess the nature and severity of your bladder symptoms.
Depending upon the circumstances, this may include:
- Medical and urinary history
- Urinalysis and/or urine culture
- Bladder or voiding diary
- Measurement of urinary flow
- Ultrasound assessment of the bladder
- Measurement of the post-void residual (PVR) to determine how well the bladder empties
- Urodynamic testing in selected patients
A post-void residual is generally measured before intradetrusor treatment. Particular caution may be appropriate when residual urine is already elevated because treatment can temporarily reduce bladder-emptying strength.
How is the treatment performed?
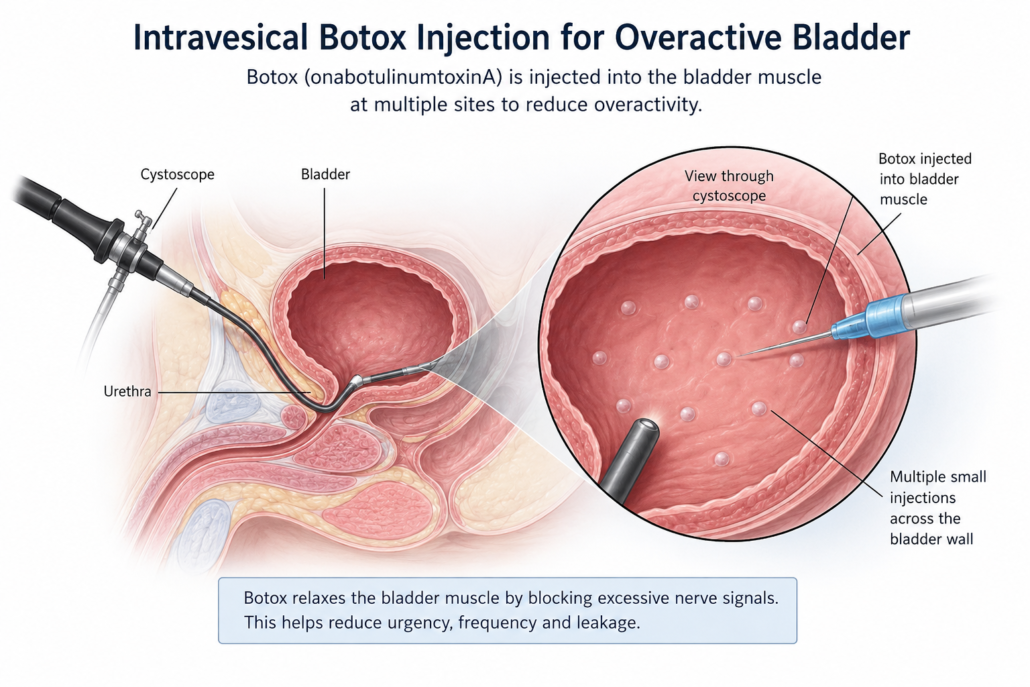
The medicine is administered using a procedure called cystoscopy.
A fine telescope is passed through the urethra into the bladder. A specialised injection needle is then passed through the cystoscope.
Small quantities of the prescribed medicine are injected at multiple sites across the bladder wall. The medicine, dose and injection technique are clinical decisions governed by the approved Australian Product Information and the individual patient’s circumstances. Botulinum toxin products and units are not necessarily interchangeable.
The procedure may be performed using:
- Local anaesthetic placed into the bladder
- Sedation, or
- General anaesthesia
The most appropriate option depends on the patient, the clinical setting and individual preference.
The procedure itself is generally relatively short, and most patients can go home on the same day.
What happens after the procedure?
Some patients notice an improvement within several days, although the full effect may take a little longer to become apparent.
If treatment is beneficial, a patient may experience:
- Less urgency
- Fewer visits to the toilet
- Fewer episodes of urgency incontinence
- Less nocturia
- Improved bladder capacity
- Improved confidence when away from a toilet
Some patients report a meaningful improvement in quality of life, while others obtain limited or no benefit.
How long might the effect last?
The effect is not permanent.
The nerve endings gradually recover and bladder symptoms may eventually return. The duration of benefit varies considerably between individuals, but treatment commonly provides symptom control for a number of months.
When symptoms return, repeat treatment may be considered after reassessment. It is not appropriate for every patient.
Repeat treatment may continue to provide benefit for some patients, while others may obtain less benefit or choose an alternative treatment.
What are the possible adverse effects?
The procedure is not without risk. The current Consumer Medicine Information and Product Information for the prescribed medicine contain the complete approved safety information.
Urinary tract infection
Urinary tract infection (UTI) is an important and relatively common complication following intravesical treatment.
Symptoms can include:
- Burning when passing urine
- Increased frequency
- Cloudy or offensive-smelling urine
- Lower abdominal discomfort
- Fever or feeling unwell
Intravesical botulinum toxin treatment is associated with an increased risk of UTI.
Difficulty emptying the bladder
The treatment reduces bladder muscle activity and can impair bladder emptying.
Some patients consequently develop an increased amount of urine remaining in the bladder after urination, known as an increased post-void residual.
This may cause:
- Difficulty starting urination
- A weak urinary stream
- A feeling of incomplete emptying
- Abdominal discomfort
- Recurrent urinary infection
For this reason, bladder emptying may be reassessed following treatment, particularly if symptoms suggest incomplete emptying.
Temporary need for self-catheterisation
Some patients may be unable to empty their bladder adequately after treatment.
If this occurs, clean intermittent self-catheterisation (CISC) may temporarily be required until the effect decreases and normal bladder emptying returns.
Patients should therefore understand this possibility and be willing and physically able to perform catheterisation if necessary before proceeding with treatment. Both EAU and AUA/SUFU guidance emphasise counselling patients about this risk.
Blood in the urine
A small amount of blood in the urine can occur following cystoscopy and the injections themselves. This is usually temporary.
Discomfort passing urine
Mild burning, urgency or bladder discomfort can occur for a short period following the procedure.
Rare systemic effects
Botulinum toxin can very rarely produce effects away from the injection site, potentially causing muscle weakness or other neurological symptoms.
Patients should seek medical attention if they develop significant weakness, difficulty swallowing or breathing difficulties following treatment.
Who may be unsuitable for treatment?
Intravesical botulinum toxin treatment is not suitable for everybody.
Important contraindications include:
- An active urinary tract infection
- Acute urinary retention in a patient who is not routinely catheterising
- Inability or unwillingness to perform intermittent catheterisation if it becomes necessary
- Known hypersensitivity to the proposed medicine or its components
- Certain neuromuscular disorders, including myasthenia gravis and Eaton-Lambert syndrome
Contraindications and precautions differ according to the medicine and individual circumstances. The prescriber should consult the current Australian Product Information.
Additional caution may be required in patients with:
- Significant pre-existing incomplete bladder emptying
- Recurrent urinary tract infections
- Bladder outlet obstruction
- Previous urinary retention
- Certain neurological conditions
- Frailty or significant medical comorbidity
Patients with recurrent UTIs require particularly careful consideration because treatment may further increase the risk of urinary infection.
Overactive bladder treatment in men
Men can also experience overactive bladder, but it is important to establish whether urinary symptoms are being caused or aggravated by bladder outlet obstruction from an enlarged prostate.
A man with urgency, frequency and nocturia may therefore require assessment of his prostate, urinary flow and residual urine before an invasive bladder treatment is considered.
In some men, treatment of prostate obstruction may need to be considered before or alongside treatment directed at the bladder.
Comparing treatment approaches for overactive bladder
Intravesical botulinum toxin injections form part of a broader range of OAB treatments and are not the right choice for every patient.
Management may include:
Conservative treatment
Bladder training, modification of fluid intake, reducing caffeine, weight management where appropriate and pelvic floor rehabilitation.
Medication
Antimuscarinic medications and beta-3 adrenergic agonists can reduce urgency, frequency and urgency incontinence.
Intravesical botulinum toxin injections
A minimally invasive prescription treatment that does not require a permanent implant. Benefit varies and repeat procedures may be needed when the effect wears off.
Tibial nerve stimulation
Electrical stimulation of the tibial nerve can modify the nerve pathways involved in bladder control.
Sacral neuromodulation
A small implanted device stimulates the sacral nerves controlling bladder function and can provide longer-term treatment for selected patients.
Current OAB guidelines discuss intravesical botulinum toxin injections, tibial nerve stimulation and sacral neuromodulation as minimally invasive options after an individual assessment. The options differ in procedure burden, adverse effects, reversibility, need for repeat treatment and availability.
When should I seek further assessment?
Further assessment may be helpful if overactive bladder is having a significant effect on quality of life and:
- Bladder training and conservative measures have not provided adequate control
- Medications have not worked sufficiently
- Medication side effects are unacceptable
- You do not wish to continue long-term medication
- You would like to consider a minimally invasive treatment
Any treatment decision should take into account expected benefit, uncertainty, alternatives and the possibility of urinary infection, incomplete bladder emptying and temporary catheterisation. Choosing no immediate procedure is also a reasonable option for some patients.
The bottom line
Intravesical botulinum toxin injections are one prescription treatment that may be considered for selected patients with overactive bladder or urgency urinary incontinence.
Some appropriately selected patients experience reduced urgency, frequency or leakage, but results vary. The effect is temporary, repeat procedures may be needed, and some patients obtain inadequate benefit.
The two most important complications to understand are urinary tract infection and incomplete bladder emptying, with a small proportion of patients requiring temporary intermittent catheterisation.
An appropriately qualified health professional can assess the cause of the symptoms and discuss conservative care, prescription medicines, tibial nerve stimulation, sacral neuromodulation, intravesical treatment and other relevant options.
This article provides general educational information and does not replace individual medical advice. It does not promote or recommend a particular prescription medicine, product or brand. Treatment decisions should follow assessment by an appropriately qualified health professional. Do not start, stop or seek a prescription medicine on the basis of this article alone.
References and further reading
- Therapeutic Goods Administration — Advertising health products
- Healthdirect Australia — Overactive bladder
- European Association of Urology — Non-neurogenic Female Lower Urinary Tract Symptoms
- American Urological Association — Idiopathic Overactive Bladder guideline
- The current Australian Product Information and Consumer Medicine Information for the medicine prescribed to the individual patient
Publication note
This draft is structured as general disease education for an Australian public-facing website. It should not be accompanied by branded product imagery, medicine pricing or supply information, testimonials, inducements, claims of superiority, or wording that invites patients to request a named prescription medicine. The title, metadata, social-media caption, images, links and nearby booking prompts should be reviewed together because the overall presentation determines whether material may be regarded as advertising.


Leave a Reply
Want to join the discussion?Feel free to contribute!