
Stress Urinary Incontinence in Women: Symptoms, Investigations and Treatment Options in Australia

Stress urinary incontinence (SUI) is one of the most common forms of urinary incontinence in women. It occurs when urine leaks because pressure inside the abdomen rises faster than the urethra and pelvic floor can close.

Coughing, sneezing, laughing, lifting, running, jumping and exercise can all trigger leakage. For some women the leakage is only a few drops; for others it can be substantial enough to interfere with exercise, work, intimacy and everyday life.
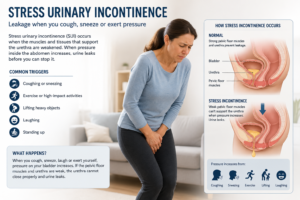
The good news is that SUI is treatable, and treatment can be tailored to the severity of symptoms, the woman’s lifestyle and preferences, previous surgery, pelvic floor function and other bladder symptoms.

What are the symptoms and signs of stress urinary incontinence?

The classic symptom is involunta

ry urine leakage with physical exertion.

Common triggers include:

  • Coughing or sneezing
  • Laughing
  • Getting up from a chair
  • Lifting children or heavy objects
  • Running or jumping
  • Exercise, particularly high-impact exercise
  • Sexual intercourse
  • Changes in position
  • Sports such as tennis, running or aerobics

Some women notice only occasional leakage, while others need pads every day.

Stress incontinence versus urgency incontinence

It is important to distinguish SUI from urgency urinary incontinence, where urine leakage follows a sudden, difficult-to-defer urge to urinate.

Many women have mixed urinary incontinence, with both stress and urgency leakage.

This distinction matters because the treatment strategy can be quite different. Treating the wrong component first can produce disappointing results.


How is stress urinary incontinence diagnosed?

For many women, the diagnosis can be made from the history and examination without an extensive battery of tests.

A specialist assessment usually includes:

1. Medical history

Your doctor will ask about:

  • The nature and severity of leakage
  • What activities trigger leakage
  • Urinary urgency and frequency
  • Night-time urination
  • Recurrent urinary tract infections
  • Previous pregnancies and childbirth
  • Menopause and hormonal symptoms
  • Previous pelvic or continence surgery
  • Pelvic-organ prolapse
  • Neurological conditions
  • Medications
  • Impact on exercise, work, social activities and sexual function

2. Bladder or voiding diary

A bladder diary records fluid intake, urinary frequency, urine volumes, urgency episodes and leakage over several days.

It can be surprisingly revealing. It helps determine whether the problem is predominantly stress leakage, urgency, excessive fluid intake, frequent small-volume voiding or a combination of these.

3. Physical examination

A pelvic examination can assess:

  • Pelvic organ prolapse
  • Pelvic floor muscle strength
  • Urethral mobility
  • Vaginal and vulval health
  • Atrophic changes associated with menopause
  • Evidence of previous surgery

A cough stress test may be performed with a comfortably full bladder. Leakage of urine through the urethra during coughing supports the diagnosis of stress urinary incontinence.

4. Urine testing

A urine test is often appropriate, particularly when there are symptoms suggesting infection, blood in the urine or other urinary abnormalities.

5. Measurement of residual urine

A bladder ultrasound can measure the amount of urine left after voiding. This is particularly useful if there are symptoms suggesting incomplete bladder emptying or voiding dysfunction.


Do I need urodynamic studies?

This is one of the most common questions asked by women considering treatment.

Not every woman with straightforward stress urinary incontinence requires urodynamics.

Urodynamic testing measures how the bladder, urethra and pelvic floor behave while the bladder fills and empties. It can determine whether leakage is associated with increased abdominal pressure, whether involuntary bladder contractions occur and whether there is evidence of obstruction or impaired bladder emptying.

Contemporary guidelines generally do not recommend routine urodynamics before surgery in women with uncomplicated, clinically demonstrable SUI because it has not been shown to improve surgical outcomes.

Urodynamics becomes particularly useful when:

  • The diagnosis is uncertain
  • There are significant urgency or other storage symptoms
  • Mixed urinary incontinence is present
  • Voiding dysfunction is suspected
  • There is significant pelvic organ prolapse
  • Previous continence surgery has failed
  • The symptoms and examination findings do not match
  • There is suspected intrinsic sphincter deficiency
  • The results may change the choice of treatment

In these situations, urodynamics can turn a clinical puzzle into a much clearer picture.


Treatment of stress urinary incontinence

Treatment is usually progressive, beginning with conservative measures and moving towards minimally invasive or surgical treatment when necessary.

The appropriate treatment depends on the severity of the leakage and, importantly, how much it bothers you.

1. Pelvic floor muscle training

Pelvic floor muscle training (PFMT) is generally the first-line treatment for SUI.

The pelvic floor muscles provide support to the bladder neck and urethra. Strengthening and correctly coordinating these muscles can significantly reduce leakage.

A structured program with a pelvic floor physiotherapist is preferable to simply being told to “do your Kegels”.

A good program may include:

  • Identification of the correct muscles
  • Strength training
  • Endurance training
  • Rapid contractions for coughs and sneezes
  • Coordination of the pelvic floor with movement
  • Techniques for managing leakage during exercise

Guidelines recommend supervised pelvic floor muscle training for at least three months as initial therapy for SUI.

The advantage is obvious: there is no incision, no anaesthetic and essentially no procedural risk.

The disadvantage is that it requires commitment, correct technique and time.


2. Lifestyle measures

Lifestyle modifications can make a meaningful difference, particularly when combined with pelvic floor rehabilitation.

These may include:

  • Weight reduction where appropriate
  • Optimizing fluid intake
  • Reducing excessive caffeine intake
  • Treating constipation
  • Addressing chronic coughing
  • Smoking cessation
  • Modifying high-impact exercise temporarily while rehabilitation is undertaken

These measures rarely “cure” significant anatomical SUI on their own, but they can reduce symptoms and improve the results of other treatments.


3. Continence pessary

A vaginal continence pessary can provide mechanical support to the urethra and bladder neck.

It may be particularly useful for women who:

  • Want to avoid surgery
  • Have leakage predominantly during exercise
  • Are awaiting surgery
  • Have coexisting pelvic organ prolapse
  • Want an additional treatment alongside pelvic floor rehabilitation

A pessary is fitted inside the vagina and can sometimes be removed and inserted by the patient.

Possible problems include vaginal irritation, discharge, discomfort and difficulty with insertion or removal. Regular review is important.


4. Vaginal oestrogen

For postmenopausal women with vaginal or genitourinary symptoms, local vaginal oestrogen may improve vaginal tissue health and urinary symptoms.

It is not a replacement for continence surgery when significant anatomical SUI is present, but it can be a useful component of treatment in appropriately selected women.


5. Urethral bulking injections

Urethral bulking involves injecting a material around the urethra to improve its ability to remain closed.

One example used clinically is polyacrylamide hydrogel.

The procedure is minimally invasive and can be attractive to women who:

  • Prefer to avoid sling surgery
  • Are poor surgical candidates
  • Have recurrent SUI after previous surgery
  • Want a relatively quick procedure

The trade-off is durability.

Bulking agents are generally less effective than sling procedures and repeat injections may be necessary. Their effectiveness can diminish with time.

Potential side effects include:

  • Temporary urinary urgency
  • Urinary tract infection
  • Difficulty emptying the bladder
  • Blood in the urine
  • Discomfort
  • Recurrent leakage
  • Need for repeat treatment

6. Mid-urethral sling

For women with bothersome SUI who have not obtained sufficient improvement from conservative treatment, a mid-urethral sling (MUS) is one of the most established surgical treatments.

The sling sits beneath the middle portion of the urethra and provides support when abdominal pressure rises.

Two principal approaches have been used:

Retropubic mid-urethral sling

The tape passes behind the pubic bone.

Mid-urethral slings have substantially reduced the morbidity and complexity of traditional continence surgery, with high rates of improvement and continence. Contemporary evidence suggests broadly similar effectiveness between retropubic and transobturator approaches, although their complication profiles differ.

Importantly, mid-urethral sling surgery is not the same as the transvaginal mesh products that were used for pelvic organ prolapse. The Australian regulatory position is different. Mid-urethral slings for SUI remain approved products in Australia, with approved devices subject to Class III medical-device requirements.


What are the risks of a mid-urethral sling?

Although most women do well, sling surgery is not risk-free.

Potential complications include:

  • Bleeding or haematoma
  • Infection
  • Bladder or urethral injury during insertion
  • Temporary or persistent difficulty passing urine
  • Urinary retention
  • New or worsening urgency
  • Recurrent stress incontinence
  • Pelvic, groin or suprapubic pain
  • Pain during sexual intercourse
  • Mesh exposure or erosion
  • Rarely, chronic pain or other mesh-related complications
  • Need for further surgery

The TGA specifically identifies complications including bladder or urethral injury, mesh exposure or erosion, voiding dysfunction, urinary retention, urgency and acute or chronic pain among the potential adverse outcomes associated with urogynaecological mesh.

The decision to use a sling should therefore involve an individual discussion about benefits, alternatives and risks rather than treating the operation as a one-size-fits-all solution.


7. Autologous fascial sling

For women who wish to avoid synthetic mesh, another established surgical option is an autologous fascial sling.

A strip of the woman’s own tissue, usually rectus fascia from the lower abdominal wall, is fashioned into a sling and placed beneath the bladder neck/urethra.

This avoids a synthetic implant.

It can be particularly useful in selected women with:

  • Severe stress incontinence
  • Intrinsic sphincter deficiency
  • Previous failed sling surgery
  • Previous mesh complications
  • A strong preference to avoid synthetic mesh

The disadvantages are that it is generally a more extensive operation, requires harvesting tissue and can have a higher risk of postoperative voiding dysfunction. Fascial harvest can also cause abdominal wound pain, infection, seroma or, rarely, hernia.


What about an allograft mid-urethral sling?

This is an important distinction.

An allograft is tissue obtained from another human donor, rather than tissue harvested from the woman herself. Historically, cadaveric fascia lata has been used to construct pubovaginal slings.

The attraction is obvious: it avoids harvesting the woman’s own rectus fascia and therefore avoids the additional abdominal wound associated with an autologous sling.

However, there is an important catch.

The evidence for allograft slings is considerably weaker than for modern mid-urethral synthetic slings or autologous fascial slings. This based on older studies and different mechanisms to prepare the graft.

Older studies of cadaveric fascia lata reported encouraging short-term outcomes, including reduced postoperative pain compared with harvesting autologous fascia. However, other studies reported substantial recurrence of stress incontinence, raising concerns about long-term durability.

Systematic evidence reviews have also concluded that the evidence supporting biological/allograft slings is limited and of low or very low certainty. In comparisons with synthetic slings, there has not been convincing evidence that cadaveric fascia lata provides a superior outcome.

For this reason, an allograft sling should not simply be regarded as a “mesh sling without mesh.”

Its role is much more selective.

Where available, it may be considered in carefully selected women who want to avoid synthetic mesh and would otherwise be candidates for a fascial sling, but the surgeon should explain the limitations of the evidence and uncertainty around long-term durability.

In Australia, the availability and regulatory status of any particular allograft product or technique should be confirmed with the treating surgeon and relevant institution. The TGA’s current approved urogynaecological mesh list specifically identifies approved devices for SUI, while not all historical mesh or biological products remain available.


8. Burch colposuspension

Burch colposuspension is a traditional operation in which sutures are placed to support the tissues around the bladder neck and urethra.

It can be performed through an abdominal approach, including laparoscopically or robotically in appropriately experienced centres.

It remains an important non-mesh surgical option, although it is more invasive than a mid-urethral sling.

Potential complications include:

  • Bleeding
  • Infection
  • Bladder injury
  • Postoperative urinary retention or voiding dysfunction
  • New urgency
  • Recurrent SUI
  • Pelvic or abdominal pain
  • Development or worsening of pelvic organ prolapse

Choosing the right operation

There is no single “best” operation for every woman.

The decision should take into account:

Consideration Why it matters
Severity of SUI Determines how much treatment is justified
Previous surgery May alter the choice of procedure
Intrinsic sphincter deficiency May favour a different surgical approach
Pelvic organ prolapse May require combined treatment
Urgency/mixed incontinence May affect expected outcome
Desire to avoid synthetic mesh Makes fascial procedures more relevant
Previous mesh complications May favour non-mesh options
General health Influences operative risk
Future pregnancies May influence timing and choice of surgery
Patient preference An essential part of shared decision-making

The aim is not simply to make the pad dry. The aim is to find the treatment that gives the woman the best balance between continence, bladder function, quality of life and procedural risk.


What happens after treatment?

Following continence surgery, women are generally reviewed to assess:

  • Continence
  • Urgency and frequency
  • Bladder emptying
  • Residual urine
  • Pelvic pain
  • Sexual function
  • Vaginal healing
  • Mesh exposure where a mesh sling has been used

If symptoms persist or recur, further investigation may be necessary. In women with failed previous SUI surgery, repeat urodynamics and specialist assessment can be particularly valuable.

Australia also has the Australasian Pelvic Floor Procedures Registry, which collects information about stress incontinence and pelvic floor procedures with the goal of improving quality and long-term safety.


The bottom line

Stress urinary incontinence is common, but it is not something women simply have to put up with.

Treatment ranges from pelvic floor physiotherapy and lifestyle modification through to pessaries, urethral bulking injections and surgery.

For women requiring surgery, options in Australia include mid-urethral sling procedures, autologous fascial sling surgery and colposuspension, with the appropriate choice depending on individual circumstances.

An allograft fascial sling is a more specialised option. Although it avoids harvesting the patient’s own fascia, the evidence base is considerably less robust than that for established mid-urethral sling and autologous fascial sling procedures. It should therefore be discussed as a selective option rather than assumed to be a routine alternative to synthetic mesh.

Most importantly, treatment should be individualised. A woman should understand not only the likelihood of becoming dry, but also the possibility of urgency, voiding problems, pain, recurrent incontinence and other procedure-specific complications before making a decision.

If urinary leakage is interfering with exercise, work, relationships or everyday life, an assessment by a GP, urogynaecologist, urologist or pelvic-floor physiotherapist is a good place to start.

This information is intended for education and does not replace an individual medical assessment. Treatment availability, device approvals and clinical recommendations can change, so patients should discuss the current options with their treating clinician.

Don’t suffer in silence. Come see what your Brisbane Urologist Uro-Jo can do for you.

Post-Prostatectomy Urinary Incontinence

Men’s Guide to Lower Urinary Tract Symptoms: What’s Causing Them and What Can Be Done?

Medical note: This is patient education rather than individual medical advice. The investigation and treatment approach should be tailored to the individual, particularly where there is haematuria, urinary retention, recurrent infection, neurological disease or concern about prostate cancer. The treatment information above reflects contemporary EAU guidance, including the 2026 guideline update.

Blood in the Urine (Haematuria): When Should You See a Urologist Brisbane?

Discovering blood in your urine can be alarming. While there are many possible causes, blood in the urine should never be ignored. Known medically as haematuria, this symptom can sometimes indicate an underlying condition requiring specialist assessment. Consulting an experienced Urologist Brisbane patients rely on can help identify the cause and provide appropriate treatment.

What Is Haematuria?

Haematuria refers to the presence of blood in the urine. It can occur in two forms:

Visible Haematuria

The urine appears pink, red or brown due to the presence of blood.

Microscopic Haematuria

Blood cells are detected only during laboratory testing and may not be visible to the naked eye.

Both forms should be assessed by a healthcare professional.

Common Causes of Blood in the Urine

There are numerous possible causes of haematuria, including:

Urinary Tract Infections

Infections affecting the bladder, kidneys or urinary tract can cause irritation and bleeding.

Kidney Stones

Kidney stones can damage the lining of the urinary tract, resulting in blood appearing in the urine.

Enlarged Prostate

An enlarged prostate can place pressure on the urinary system and may contribute to urinary symptoms and bleeding.

Vigorous Exercise

In some cases, intense physical activity can lead to temporary blood in the urine.

Kidney Disease

Various kidney conditions may result in haematuria and require specialist management.

Urinary Tract Cancers

Although less common, blood in the urine can sometimes be associated with cancers affecting the bladder, kidney or urinary tract. This is one reason why prompt evaluation by a Urologist Brisbane specialist is important.

Symptoms That May Accompany Haematuria

Depending on the underlying cause, patients may also experience:

  • Pain during urination
  • Frequent urination
  • Lower abdominal discomfort
  • Back or flank pain
  • Difficulty passing urine
  • Fever or chills

These symptoms can provide valuable clues during diagnosis.

How Does a Urologist Brisbane Diagnose Haematuria?

A comprehensive evaluation may include:

Medical History and Physical Examination

Your specialist will discuss symptoms, medical history and risk factors.

Urine Testing

Urinalysis helps identify infection, blood cells and other abnormalities.

Blood Tests

Blood tests may assess kidney function and identify underlying conditions.

Imaging Studies

Ultrasound or CT imaging can help detect stones, tumours or structural abnormalities.

Cystoscopy

A cystoscopy allows a Urologist Brisbane specialist to examine the inside of the bladder using a small camera.

Why Early Investigation Matters

While haematuria can sometimes result from minor conditions, it may also be an early warning sign of a more serious problem. Early diagnosis often leads to more effective treatment and improved outcomes.

Delaying assessment can allow certain conditions to progress and become more difficult to treat.

When Should You Seek Medical Advice?

You should arrange an appointment if:

  • You notice visible blood in your urine
  • Blood is detected during routine testing
  • Haematuria occurs repeatedly
  • You experience pain or urinary symptoms
  • You have a history of smoking or urinary tract conditions

Speak with a Urologist Brisbane Today

If you have noticed blood in your urine or have concerns about your urinary health, our experienced team is here to help. We provide thorough assessments, advanced diagnostic services and personalised treatment plans to identify the cause and protect your long-term health. Contact our clinic today to book a consultation with a trusted Urologist Brisbane specialist.

Kidney Stones: Symptoms, Causes and Treatment Options Explained

Kidney stones: symptoms, treatment and prevention

Kidney stones can cause sudden, intense pain, but some are discovered by chance and cause no symptoms. The right treatment depends on where a stone sits, its size, whether urine can drain, whether infection is present and how well the kidneys are working. If you have suspected stone pain, an assessment can establish which approach is safest for you.

What is a kidney stone?

A kidney stone forms when substances in urine crystallise and grow. Calcium-based stones are common; other types include uric acid, infection-related (struvite) and cystine stones. A stone may remain in the kidney or move into the ureter, the tube carrying urine to the bladder. A ureteric stone can obstruct urine flow and cause renal colic.

Symptoms to recognise

  • Severe pain in the side or back that may travel towards the lower abdomen or groin, often in waves
  • Blood in the urine, which may be visible or detected on a test
  • Nausea or vomiting
  • Urgency, frequent urination or discomfort passing urine, particularly when a stone is near the bladder

Cloudy urine, fever or chills may indicate infection. These symptoms also have other possible causes, so imaging and tests are important.

Seek urgent care at an emergency department if you have fever or chills with suspected stone pain, cannot pass urine, cannot keep fluids down, have pain that cannot be controlled, or have a single functioning kidney or known kidney disease with possible obstruction. An infected, obstructed kidney is a urological emergency: antibiotics and urgent drainage with a ureteric stent or nephrostomy may be needed before definitive stone treatment.

Why do stones form?

Low fluid intake, heavy sweating, a high-salt diet, previous stones and family history can increase risk. Other contributors include certain medicines and conditions such as gout, bowel disease or recurrent infection. The causes differ by stone type. Finding the type matters when planning prevention.

How are kidney stones diagnosed?

Assessment usually includes your symptoms and medical history, urine testing for blood and infection, and blood tests to check kidney function when appropriate. A low-dose CT scan without contrast is often used for adults with suspected renal colic because it shows the size and position of a stone and signs of obstruction. Ultrasound may be preferred first in pregnancy and some other circumstances. If you pass or have a stone removed, laboratory analysis can guide future prevention.

What are the treatment options?

Observation and pain relief. Many small ureteric stones pass without a procedure. This is reasonable when pain is controlled, there is no infection or concerning obstruction, and kidney function is safe. Your clinician will arrange follow-up to confirm that the stone has passed or the obstruction has resolved. Pain relief is tailored to your health; anti-inflammatory medicines may be useful but are unsuitable for some people, including those with impaired kidney function. Drink normally and avoid dehydration; forcing large amounts of water during acute colic does not push a blocked stone through.

Medication to help passage. An alpha blocker may improve passage for selected stones in the lower ureter, especially those around 5–10 mm. This use is off-label and should be discussed alongside possible adverse effects, such as dizziness. It is not suitable as a substitute for urgent treatment if infection, uncontrolled pain or worsening kidney function develops.

Shock wave lithotripsy (SWL or ESWL). Shock waves delivered from outside the body break a suitable stone into fragments. Its success depends on factors including stone size, position and density; further treatment can sometimes be needed.

Ureteroscopy and laser treatment. A fine telescope passes through the urethra and bladder into the ureter or kidney. The stone can be removed or fragmented with a laser. A temporary ureteric stent is sometimes placed and can cause urinary discomfort until removal.

Percutaneous nephrolithotomy (PCNL). For some large or complex kidney stones, instruments are passed through a small opening in the back to remove the stone. This is more invasive than ureteroscopy or shock wave treatment and has its own bleeding and infection risks.

Your urologist will discuss the expected chance of clearing the stone, anaesthetic needs, recovery, possible stenting and risks of each appropriate option.

Reducing the chance of another stone

For most people, drinking enough fluid to keep urine dilute is a useful starting point, particularly in Queensland heat. If you have heart failure or kidney disease, follow your treating team’s fluid advice instead of increasing intake on your own. Reduce excess salt, maintain a balanced diet and avoid unnecessarily restricting normal dietary calcium. Further dietary advice or preventive medication should be based on the stone’s composition and, for recurrent or higher-risk stones, blood and 24-hour urine testing. Follow-up imaging may be recommended to check for residual or new stones.

When should you see a urologist in Brisbane?

Arrange an assessment if you have a diagnosed stone that has not passed, recurrent stones, persistent pain, blood in the urine, or concerns about kidney function. If you are acutely unwell or have fever with stone symptoms, go to an emergency department rather than waiting for a routine appointment.

This article is general information and does not replace individual medical advice.

References

  1. European Association of Urology. EAU Guidelines on Urolithiasis (2026).
  2. National Institute for Health and Care Excellence. Renal and ureteric stones: assessment and management (NG118).
  3. Healthdirect Australia. Kidney stones: symptoms, diagnosis and treatment.
  4. Kidney Health Australia. Kidney stones.

Management Options for Benign Prostate Hyperplasia

What is BPH?

Benign Prostate Hyperplasia

(BPH) is a non-cancerous enlargement of the prostate gland that commonly affects men as they age.

As the prostate grows, it can press on the urethra and cause urinary symptoms such as:

  • Frequent or urgent need to urinate
  • Difficulty starting urination
  • Weak urine stream or dribbling
  • Getting up multiple times at night
  • Feeling the bladder hasn’t fully emptied

Watchful Waiting & Lifestyle Changes

Active Monitoring

  • Annual check-ups with your doctor
  • Symptom tracking using validated scores
  • Prostate size monitoring
  • ~79% of patients remain stable over 5 years

Lifestyle Adjustments

  • Reduce fluids before bedtime
  • Limit caffeine and alcohol
  • Avoid decongestants & antihistamines
  • Practice timed voiding
  • Stay active and maintain healthy weight

Medications

Alpha-Blockers

             Fast-acting relief
  • Relax prostate & bladder neck muscles
  • Improve urine flow within days
  • Examples: tamsulosin, alfuzosin
  • May cause dizziness or low blood pressure

5-Alpha Reductase Inhibitors

            Long-term shrinkage
  • Shrink prostate over 6-12 months
  • Best for larger prostates (>40 cc)
  • Examples: finasteride, dutasteride
  • Can be combined with alpha-blockers

PDE5 Inhibitors (Tadalafil)

          Dual benefit
  • Daily low-dose relaxes smooth muscle
  • Also treats erectile dysfunction
  • Newer AUA guidelines support combos
  • Preserves ejaculatory function

Minimally Invasive Procedures

  1. Rezum – Steam Therapy
  2. UroLift – Prostatic Lift
  3. iTIND – Temporary Implant

Surgical Options

  1. TURP
  2. HoLep
  3. Greenlight Vaporization (PVP)
  4. Robotic Simple Prostatectomy

TURP remains the traditional gold standard. HoLEP and RSP offers the best long-term durability, especially for larger prostates.

HoLEP: Lowest retreatment rate (2% at 10 years), works for all prostate sizes. GreenLight: Same-day discharge, safe on blood thinners.

Choosing the Right Treatment

Treatment depends on several individual factors. Discuss these with your doctor:

  1. Symptom severity and how much they bother you
  2. Prostate size (small, medium, or large)
  3. Whether medications have been tried already
  4. Recovery time and return-to-activity goals
  5. Sexual function priorities (ejaculation, erections)

Key Takeaways

  1. BPH is very common and not cancerous — effective treatments are available at every stage
  2. Mild symptoms often improve with simple lifestyle changes and regular monitoring
  3. Medications can significantly reduce symptoms; newer combinations offer added benefits.
  4. Minimally invasive procedures preserve sexual function with quick recovery times.
  5. Surgery provides the most durable results for larger prostates or severe symptoms.

Talk to your  urologist about which option is right for you


How Diet & Lifestyle Can Support Prostate Health

Prostate health: food, movement and informed testing

The prostate is a small gland below the bladder that contributes fluid to semen. It surrounds the first part of the urethra, so changes in the prostate can affect urination. Prostate enlargement, inflammation and cancer are different conditions; urinary symptoms alone cannot tell us which, if any, is present.[1, 2]

A healthy diet and regular activity support overall wellbeing. They may help some people manage weight and cope with treatment, but no food or exercise programme has been shown to guarantee prevention of prostate enlargement or prostate cancer. Similarly, a “check-up” is not the same thing as screening everyone for cancer: the decision to have a PSA blood test should take account of age, individual risk, preferences and the possible harms of testing.[3, 4]

What can affect the prostate?

Benign prostate enlargement (BPH) becomes more common with age. It may cause a weak stream, hesitancy, more frequent urination or waking at night. Similar symptoms can come from bladder conditions, medicines or other causes. Treatment depends on the degree of bother and any complications, and can range from monitoring and practical changes to medicines or a procedure.[1]

Prostatitis describes inflammation of the prostate and has several forms. Pain, urinary symptoms or fever require assessment; diet alone will not diagnose or treat the cause.[1]

Prostate cancer often causes no symptoms in its early stages. Some cancers grow slowly and may never need treatment; others are more aggressive. An abnormal PSA result does not by itself establish a cancer diagnosis.[2, 4]

Is there a “prostate-friendly” diet?

It is reasonable to use this phrase for a varied, balanced eating pattern, but it should not imply that a particular menu protects the prostate. The Australian Dietary Guidelines recommend vegetables, fruit, mostly wholegrain cereals, appropriate protein foods and water as a usual drink, while limiting foods high in added salt and saturated fat.[5] Food choices should also fit a person’s other conditions and cultural preferences.

The foods often promoted for prostate health can fit into that pattern, with important limits to the evidence:

Food What it offers What remains unproven
Tomatoes A vegetable source of lycopene and other nutrients Eating tomatoes or taking lycopene supplements has not been established as a way to prevent or treat prostate cancer.[3, 6]
Broccoli and cauliflower Vegetables that add variety and fibre Laboratory theories about their compounds do not prove that they prevent prostate disease in people.[3]
Salmon and sardines Protein and, in oily fish, omega-3 fats Fish is not a proven prostate cancer treatment or prevention strategy.[3, 5]
Green tea A beverage some people enjoy Antioxidant content does not establish a clinical benefit for prostate cancer; caffeine may aggravate urinary urgency in some people.[3, 7]
Chia and flaxseeds Fibre and unsaturated fats Eating these seeds is not proven to prevent BPH or prostate cancer.[3, 5]

No supplement should be assumed to be beneficial because it is sold as “natural” or “prostate supporting.” The SELECT trial, for example, found increased prostate cancer risk among men assigned vitamin E alone. Discuss supplements with your clinician, particularly if you are receiving treatment or taking medicines.[6]

A practical meal might include vegetables, a wholegrain food and fish, beans, eggs, tofu or another suitable protein. Add fruit or unsalted nuts and seeds according to preference. The value is in the overall pattern, not a particular “superfood.” If cancer treatment is affecting appetite or weight, an accredited practising dietitian can tailor the plan.[5, 8]

Movement, weight and everyday habits

Physical activity helps cardiovascular health, strength, mood and weight management. Australia’s current adult movement recommendations encourage activity on most days, including moderate to vigorous movement for at least 30 minutes on most days, strength activities twice a week, and mobility or balance activities on several days.[9] A walk, cycling, swimming or a manageable strength routine can be a starting point; build gradually if you have been inactive.

Excess body weight is associated with some adverse health outcomes, and Cancer Council Australia reports evidence linking overweight and obesity with prostate cancer risk. That association does not mean that weight loss prevents every prostate cancer, or that a person’s weight explains an individual diagnosis.[3]

For urinary symptoms, it can help to note when and how much you drink, whether caffeine or alcohol worsens urgency, and whether constipation is present. Drinking enough is important, but forcing large volumes can make frequency worse. These measures may ease symptoms for some people; they should not delay assessment of persistent or concerning changes.[1, 7]

If you are undergoing prostate cancer treatment, exercise may support fitness and help with treatment-related effects. The safest type and intensity depend on treatment, fatigue, bone health and other conditions. Ask your treating team or an accredited exercise physiologist for an individual plan when needed.[8]

What about PSA testing and “regular check-ups”?

A PSA test measures a protein made by the prostate. PSA may rise for reasons other than cancer, and testing can find slow-growing cancers that would never have caused harm. Further investigation and treatment can carry physical and emotional burdens. Testing may also identify a cancer at a stage when treatment can help. These benefits and harms should be discussed before testing.[2, 4]

The 2026 Australian guidelines for early detection recommend, after an informed discussion, PSA testing every two years for people aged 50–69 who choose testing. Routine testing at 45–49 is generally not recommended for average-risk people, although an interested person may be offered an initial test. People at higher risk, including those with certain family histories, Black sub-Saharan ancestry or a BRCA2 mutation, may be advised to start two-yearly testing at 45. For people aged 70 or older, the decision is individualised according to health, life expectancy and preferences.[4]

These are recommendations for people without symptoms. New difficulty passing urine, blood in the urine, persistent pain or other concerning symptoms call for assessment regardless of age or a planned PSA testing schedule. A GP is a sensible first contact and can arrange testing or referral when indicated.[2, 4]

A sustainable approach

Eat a varied diet, move regularly in ways you can sustain, and talk with your GP about symptoms and whether PSA testing makes sense for your age and risk. Healthy living is valuable in its own right, while medical decisions remain individual. There is no guarantee that these steps will prevent prostate disease, and a diagnosis does not mean someone has failed to look after their health.

General information only. This article does not replace personal medical advice or a discussion of the benefits and harms of PSA testing.

References

  1. Healthdirect Australia. Prostate problems.
  2. Cancer Council Australia. Early detection of prostate cancer.
  3. Cancer Council Australia. Prostate cancer prevention: evidence on lifestyle and diet.
  4. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia.
  5. National Health and Medical Research Council. Australian Dietary Guidelines.
  6. US National Cancer Institute. Prostate cancer, nutrition and dietary supplements; SELECT trial results.
  7. Healthdirect Australia. Benign prostatic hypertrophy: lifestyle measures.
  8. Cancer Council Australia. Life during and after prostate cancer treatment.
  9. Australian Government Department of Health. 24-hour movement recommendations for adults.

Nurse-led Urology Clinic in Bundaberg – Sandra Ilett and Carla Kerr

  • A nurse-led urology clinic is now operating at The Friendlies Medical Suites to provide an improved service for patients.Sandra Ilett and Carla Kerr from Community Nurse Service are available to see patients with bowel and bladder issues.

    – It was a “wraparound service” under the supervision of doctors.

    – Run by highly qualified, specialized nurses who can also provide education, support and help

    – Seeing people who might need to have a catheter removed or they might have a permanent catheter, and they need education on how to manage it, or if they have an incontinence problem of any sort.

    – Being seen in an outpatient setting saves people being admitted to the ward and reduces stress and anxiety for the patient.

Sandra has worked as a continence nurse for 25 years in a variety of settings and has worked independently in the community for five years.

Provides a service for people who have problems with their bowel and bladder across the whole lifespan, from small children right through to the elderly


Sandra’s connection with The Friendlies is a win-win for both organisations and patients. Her words:

“I previously only provided a domiciliary service where I visited consumers at home,” she said.

“Occasionally I come across people who don’t want a home visit or it’s totally inappropriate to do a home visit, so I started searching for a clinical space that I could use.

“At the same time, The Friendlies were looking to try and get a trial, where people who have a catheter after an operation, who need to come back to the hospital to have the catheter removed and make sure they’re okay … they were trying to get those people out of the wards into an outpatient setting.

“The two opportunities came together and we’re now offering the trial in an outpatient clinic.

“It’s mostly referral-based clients from the urologists and I can also arrange to meet people at The Friendlies if a home visit is not a suitable option.”

For more information, contact Community Nurse Service on 4126 2002

Sandra Ilett Continence Nurse | healthdirect

Microbiome of the Male Reproductive System: The Hidden Factor in Men’s Health

When most people think about the microbiome, they imagine gut bacteria affecting digestion and immunity. But did you know that the male reproductive system also has its own unique microbiome? This hidden ecosystem of microorganisms plays a surprising role in fertility, hormone balance, and overall sexual health.

What Is the Male Reproductive Microbiome?

The male reproductive microbiome refers to the community of bacteria and other microorganisms living in the penis, testes, prostate, and semen. While it’s less studied than the gut microbiome, research shows that these microbes are crucial for maintaining reproductive health.

A balanced microbiome supports sperm quality, prevents infections, and even influences the immune environment of the reproductive tract. On the other hand, imbalances sometimes caused by antibiotics, poor hygiene, infections, or lifestyle factors can lead to fertility issues and other complications.

How the Microbiome Affects Fertility

Studies suggest that an unhealthy male reproductive microbiome may contribute to:

  • Reduced sperm motility: making it harder for sperm to reach the egg.

  • Decreased sperm count: fewer sperm can lower the chance of conception.

  • DNA fragmentation: damaged sperm DNA can affect embryo quality.

  • Inflammation: chronic inflammation in the reproductive tract can impair fertility and sexual health.

Even small changes in microbial balance can have a measurable impact on reproductive outcomes, highlighting why men’s microbiomes deserve attention.

Factors That Influence the Male Microbiome

Several lifestyle and environmental factors can disrupt the delicate balance of microbes:

  • Antibiotic use: kills both harmful and beneficial bacteria.

  • Diet: processed foods, sugar, and alcohol can negatively impact microbial health.

  • Hygiene: poor genital hygiene can allow harmful bacteria to thrive.

  • Sexual activity: sexually transmitted infections can alter microbial balance.

  • Chronic stress: stress hormones can influence bacterial populations and immunity.

Maintaining healthy habits is essential for keeping the microbiome in check.

Supporting a Healthy Male Microbiome

Here are practical ways men can support their reproductive microbial health:

  1. Balanced diet: Include fiber-rich fruits, vegetables, fermented foods, and lean protein.

  2. Probiotics: Supplements or natural sources (like yogurt or kefir) can help maintain beneficial bacteria.

  3. Safe sexual practices: Use protection and get regular STI screenings.

  4. Gentle hygiene: Avoid harsh soaps; washing with mild cleansers is best.

  5. Lifestyle management: Reduce alcohol, quit smoking, manage stress, and exercise regularly.

Why It Matters

The male reproductive microbiome is more than just a scientific curiosity, it’s a critical component of sexual and reproductive health. By understanding and supporting this hidden ecosystem, men can improve fertility, reduce infection risk, and even support hormone balance and overall wellness.


Conclusion:
Men’s health isn’t just about testosterone, erections, or sperm count, it’s also about the microscopic world living inside the reproductive system. Paying attention to the male reproductive microbiome is a small step with potentially big benefits for fertility, sexual function, and overall health.

Subclinical Hypogonadism: Low Testosterone Without Obvious Symptoms

Low testosterone and “subclinical hypogonadism”: what do the results mean?

Testosterone contributes to sexual function, muscle and bone health, and other body processes. A man may wonder about testosterone when he notices a change in libido, energy or strength. Those symptoms deserve attention, but they have many possible causes. A blood result below a laboratory range does not, by itself, establish testosterone deficiency or mean that testosterone treatment will help.[1–3]

Is “subclinical hypogonadism” a hidden disease?

The term can be confusing. In specialist literature, compensated or subclinical hypogonadism may describe normal testosterone with an elevated luteinising hormone (LH). LH is the signal from the pituitary gland that stimulates the testes to make testosterone. The clinical significance of this laboratory pattern is uncertain; it should not be described as a predictable early stage that inevitably leads to complications.[2]

Established male hypogonadism is a clinical syndrome involving compatible symptoms or signs together with consistently low testosterone on appropriately collected tests. Some men have subtle symptoms, but fatigue, irritability and poor concentration are not specific to testosterone deficiency. Recent Endocrine Society guidance cautions against routine testosterone screening in men without symptoms and against applying vague “age-related” labels without a careful diagnosis.[1–3]

When might testosterone deficiency be considered?

A persistent reduction in sexual desire, fewer spontaneous morning erections, erectile difficulties, reduced body hair, small testes, loss of strength, infertility, unexplained anaemia or low-trauma fractures can prompt a clinician to consider testosterone deficiency. No one symptom proves it, and erectile dysfunction often has vascular, psychological, medication-related or other causes.[2, 3]

Potential causes include a disorder of the testes (primary hypogonadism) or of the hypothalamus or pituitary gland (secondary hypogonadism). Obesity, type 2 diabetes, chronic illness, sleep problems and medicines such as opioids or glucocorticoids may also be associated with lower measured testosterone. Acute illness can temporarily affect a test result. The aim is to find and address the cause rather than assume that a symptom is due to normal ageing or that testosterone is the answer.[1–3]

How is it investigated?

Assessment starts with the person’s symptoms, medical history, medicines, sleep, fertility plans and an examination when indicated. A clinician generally orders two separate early-morning testosterone tests, preferably fasting and when the person is otherwise well. Testosterone changes across the day, and assays and reference ranges vary. A single borderline result should be interpreted cautiously.[1–3]

LH and follicle-stimulating hormone (FSH) help distinguish testicular from pituitary or hypothalamic causes. Depending on the circumstances, a clinician may assess prolactin, other pituitary hormones, thyroid function, blood count or iron studies. Free testosterone may be helpful in selected cases when total testosterone is borderline or the protein that binds testosterone is altered; it is not an automatic replacement for a reliable total testosterone test. Further investigations, such as pituitary imaging or bone density assessment, are guided by the clinical findings.[2, 3]

A normal testosterone result with raised LH is not the same as confirmed low testosterone. It may warrant review in context, but there is no established reason to prescribe testosterone solely to “treat the number.”[2]

Does a borderline result predict future disease?

Confirmed, longstanding testosterone deficiency can affect bone density, body composition and sexual function. However, it is misleading to state that everyone with a borderline measurement or a compensated laboratory pattern will develop osteoporosis, diabetes or heart disease.[2]

Low testosterone is often found alongside obesity or poor health, but an association does not show that low testosterone caused a cardiovascular or metabolic condition. Likewise, testosterone treatment should not be offered as a way to prevent heart disease or treat diabetes. Benefits and risks depend on the person’s diagnosis and circumstances.[1, 3]

What can be done first?

If obesity, poor sleep, a medicine or another health condition may be contributing, addressing that issue is often a useful first step. A manageable programme of physical activity, including resistance exercise, a balanced diet and treatment of sleep problems can support overall health. These steps are valuable whether or not testosterone increases; they are not guaranteed to correct an underlying testicular or pituitary disorder. In men with obesity-related hypogonadism and no other identified cause, the Endocrine Society describes weight loss as the usual first-line approach.[1]

If low libido, fatigue or mood symptoms persist, assessment should also consider depression, sleep apnoea, relationship factors, diabetes, anaemia and other possible causes. The plan should follow the findings rather than a generic “testosterone boost” programme.[1–3]

When is testosterone treatment considered?

Testosterone replacement may be appropriate for a man with confirmed hypogonadism, clinically important symptoms and a discussion of likely benefits, uncertainties, alternatives and monitoring. An Australian registered product’s indication requires deficiency to be confirmed by clinical features and biochemical tests. Treatment is not routinely recommended for an otherwise well man because of age, a single borderline test or vague symptoms alone.[1, 3, 4]

Testosterone can suppress sperm production and may compromise fertility. Men planning children should discuss this before starting therapy; fertility-preserving management may require specialist input. Assessment before treatment also considers the blood count, prostate concerns, sleep apnoea, cardiovascular history and other conditions. Follow-up includes symptoms, testosterone level, haematocrit and prostate assessment as appropriate.[2, 3, 5]

The safety picture is nuanced. A large trial did not find a meaningful increase in heart attack or stroke over roughly one to four years in the men studied, but reported more pulmonary embolism and fractures in the testosterone group; long-term safety remains uncertain. Those findings do not justify declaring therapy either universally safe or universally harmful.[1]

The main message

If symptoms concern you, discuss them with your GP. A thoughtful assessment can identify testosterone deficiency when it is present and uncover other causes when it is not. “Subclinical hypogonadism” is not a reliable label for every man with tiredness or a borderline blood test. Treatment decisions should be based on a clear diagnosis and personal goals, especially future fertility.[1–3]

This article is general information, not an individual diagnosis or treatment recommendation. Do not start, stop or change prescribed hormones without advice from your treating clinician.

References

  1. Endocrine Society. Statement on Testosterone Replacement Therapy, 2026.
  2. European Association of Urology. Sexual and Reproductive Health Guidelines: Male Hypogonadism.
  3. Endocrine Society. Testosterone Therapy in Men With Hypogonadism: Clinical Practice Guideline.
  4. Therapeutic Goods Administration. ANDROFORTE 5 registration and approved indication.
  5. Healthy Male. Androgen deficiency clinical summary guide.