
Vaginal vault prolapse: understanding the options

Patient information | Reviewed 28 September 2026

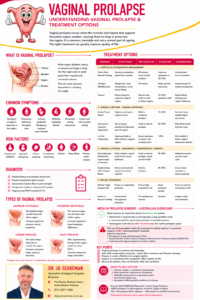
Vaginal vault prolapse occurs when the top of the vagina descends after a hysterectomy. It can occur alone or alongside a bulge of the front vaginal wall (anterior prolapse, often called a cystocele). Some women feel a bulge, dragging or pressure; others have difficulty emptying their bladder, recurrent urinary infections, bowel symptoms or discomfort during sex. The size of a prolapse on examination does not always match how troublesome it feels. Treatment should be guided by symptoms and personal priorities, rather than the examination alone. [1,2]

Why the front wall matters

The vaginal apex helps support the front and back walls. An anterior bulge may partly reflect loss of support at the apex. Repairing only the front wall while leaving significant vault prolapse untreated may leave the underlying problem unresolved. Conversely, restoring apical support may improve some anterior prolapse, although a separate anterior repair is sometimes needed. The surgeon should assess each compartment before deciding which parts require treatment. [1,3]

Assessment and treatment without surgery

Assessment includes a history of bulge, urinary and bowel symptoms, sexual function, prior hysterectomy and prolapse operations; examination while straining; and discussion of what the woman wants treatment to achieve. A bladder scan for residual urine is useful when emptying is difficult. Urine tests, urodynamics or imaging are considered for specific questions rather than required for every woman. Stress leakage can be hidden by a large prolapse and may appear after it is reduced or repaired; this possibility deserves discussion before surgery. [1,2]

If symptoms are mild, observation is reasonable. Pelvic floor muscle training can improve symptoms, particularly with less advanced prolapse, but cannot reliably lift a substantial vault prolapse back into place. A vaginal pessary can relieve a bulge without surgery and can also help someone decide whether restoring support improves bladder or bowel symptoms. Pessaries require fitting and ongoing review. Vaginal oestrogen may help postmenopausal vaginal dryness or irritation when appropriate; it is not a cure for the prolapse. [1,2]

Surgical options

Approach How the apex is supported Main considerations
Vaginal sacrospinous fixation Stitches attach the vaginal top to a pelvic ligament, usually on one side. Avoids an abdominal incision and implanted mesh; possible temporary buttock pain and recurrent anterior bulge.
Vaginal uterosacral ligament suspension Stitches attach the vaginal top to the uterosacral ligaments. Uses the woman’s own tissues; attention to the ureters is essential, often with cystoscopy during surgery.
Sacrocolpopexy (laparoscopic, robotic or open) Mesh attached to the vagina is fixed to the ligament over the sacrum through the abdomen. Often durable apical support; abdominal operative risks and mesh-specific risks must be weighed.
Colpocleisis The vaginal canal is closed or substantially shortened. Effective option for selected women who do not wish to retain vaginal intercourse; the loss of vaginal intercourse is permanent.

An anterior repair may be added if the front wall remains significantly prolapsed after apical support is restored. These operations can also be combined with treatment of stress incontinence when the benefits and added risks justify it. The decision is individual. [1–3]

Where does robotic sacrocolpopexy fit?

Robotic sacrocolpopexy is one way to perform abdominal sacrocolpopexy through small incisions. The robot helps the surgeon control instruments; it does not perform the surgery independently. It may be considered for symptomatic, substantial or recurrent vault prolapse, especially when preserving vaginal length and durable apical support are priorities, or when multiple compartments need reconstruction. It is not necessary for every prolapse and is not suitable for every patient. Previous abdominal operations, anaesthetic risk, ability to tolerate the operating position, mesh preferences, surgeon experience and costs all matter. [1–4]

Compared with vaginal operations using the patient’s own tissue, sacrocolpopexy generally has lower rates of recurrent prolapse and repeat prolapse surgery in studies of post-hysterectomy vault prolapse. In the 2023 Cochrane review, illustrative estimates were 6 in 100 requiring repeat surgery after sacrocolpopexy versus 14 in 100 after vaginal procedures, and 8 in 100 noticing recurrent prolapse versus 18 in 100 after vaginal procedures. These are pooled comparisons, not predictions for an individual. The certainty and length of follow-up vary. [3]

A multicentre randomised trial reported a 36-month composite treatment-failure estimate of 28% with sacrocolpopexy and 43% with vaginal native-tissue repair. Its definition combined symptoms, examination findings and retreatment: it does not mean 28% underwent another operation. Women in all groups reported sustained improvement, with similar satisfaction and decision regret. [4]

The benefit shown for sacrocolpopexy should not be attributed specifically to the robot. Comparative studies have not established better long-term anatomical or patient-reported results for robotic versus conventional laparoscopic sacrocolpopexy. Operating time and cost can be higher with robotic surgery, depending on the centre and surgeon. The quality of the repair and the experience of the team may matter more than the instrument platform. [5,6]

Risks and complications

Every prolapse operation can involve bleeding, infection, clots, anaesthetic complications, injury to the bladder, bowel or ureters, temporary difficulty emptying the bladder, new or persistent urinary leakage or urgency, constipation, pain with intercourse, and recurrence. A bulge can return in a different compartment even when the apex remains well supported. Some women need further treatment. Individual risk varies with previous operations and health. [1–4]

Sacrocolpopexy adds risks associated with abdominal access and permanent mesh, including mesh exposure through the vagina, infection, pain, and rarely erosion into an organ or complications near the sacrum. Mesh complications can arise years later and sometimes require further surgery. The 2024 randomised trial reported mesh exposure in about 3% after sacrocolpopexy during its follow-up; this is a study figure, not a lifetime risk. Vaginal native-tissue surgery avoids implanted mesh but has its own risks, including buttock pain with sacrospinous fixation and ureteric obstruction or injury with uterosacral suspension. [1,3,4]

An Australian distinction: Mesh inserted through the vagina to repair prolapse is not available for routine supply in Australia. That is different from mesh inserted through the abdomen for sacrocolpopexy, which remains an available category of device. An operation should never be described simply as “mesh-free” or “mesh surgery” without explaining the route, material and specific risks. [7]

Making a decision

There is no single best operation for every woman. A useful consultation covers how bothersome the bulge is; whether a pessary has been tried; the degree of vault and anterior prolapse; bladder, bowel and sexual symptoms; previous repairs; the wish to avoid mesh; the wish to maintain vaginal intercourse; likely recovery; and the surgeon’s experience with each approach. It should distinguish improvement in symptoms from an examination-based definition of anatomical success. For women seeking a durable reconstruction, sacrocolpopexy is an important option; vaginal native-tissue surgery remains a valid choice, particularly when avoiding abdominal surgery or mesh matters more. [1–4]

This article provides general information and cannot replace an individual examination and discussion of personal risks and goals.

References

  1. NICE. Urinary incontinence and pelvic organ prolapse in women: management (NG123). 2019, subsequent updates.
  2. RCOG. Pelvic organ prolapse: patient information.
  3. Maher C, et al. Surgery for women with apical vaginal prolapse. Cochrane Database Syst Rev. 2023;7:CD012376. doi:10.1002/14651858.CD012376.pub2.
  4. Menefee SA, et al. Apical suspension repair for vaginal vault prolapse: a randomized clinical trial. JAMA Surg. 2024.
  5. Robotic compared with laparoscopic sacrocolpopexy: a randomized controlled trial. Obstet Gynecol. 2014.
  6. Ferrari A, et al. Laparoscopic versus robot-assisted sacrocolpopexy: systematic review and meta-analysis. 2026.
  7. Therapeutic Goods Administration. About transvaginal surgical mesh devices.
Mid-Urethral Slings for Stress Urinary Incontinence: What Is the Current Australian Position?

Patient information for Australian women | Reviewed 22 September 2026

The word “mesh” can understandably cause concern. Public discussion has often grouped together several very different products and operations. A mid-urethral sling used to treat female stress urinary incontinence is not the same operation as transvaginal mesh used to repair pelvic organ prolapse, and it is also different from a single-incision mini-sling.

The Urological Society of Australia and New Zealand (USANZ) supports the continued availability of mid-urethral slings in Australia as one treatment option for appropriately selected women. That support is not unconditional: USANZ emphasises appropriate clinical governance, surgeon credentialing, informed consent, multidisciplinary review where appropriate, and monitoring of patient outcomes.

What is stress urinary incontinence?

Stress urinary incontinence, or SUI, is leakage caused by an increase in abdominal pressure, for example when coughing, sneezing, laughing, exercising or lifting. It is different from urge incontinence, in which leakage is associated with a sudden compelling need to pass urine.

An accurate diagnosis matters. Some women have both stress and urgency symptoms, difficulty emptying the bladder, prolapse, recurrent infections or previous pelvic surgery. A consultation may therefore include a history, examination, bladder diary, urine testing, measurement of residual urine and, in selected or complex cases, urodynamic studies or cystoscopy.

What is a mid-urethral sling?

A mid-urethral sling is a narrow strip of permanent synthetic polypropylene mesh placed beneath the middle part of the urethra. It provides support during coughing, exercise and other activities that raise abdominal pressure.

The two established approaches are:

  • Retropubic sling: the tape passes behind the pubic bone.
  • Transobturator sling: the tape passes through the obturator region towards the groin.

These approaches have different risk profiles. The retropubic route has a greater risk of bladder perforation and short-term voiding difficulty, while the transobturator route has a greater association with groin or thigh pain. The most appropriate approach depends on the woman’s anatomy, previous operations, clinical circumstances and preferences.

What does USANZ say?

USANZ states that mid-urethral slings have an established evidence base for relative safety and effectiveness and should remain available in Australia for the treatment of female SUI. In its 2023 statement, USANZ specifically linked continued use to the clinical-governance improvements introduced in Australia since 2018, including:

  • appropriate surgeon credentialing
  • careful patient selection
  • discussion through multidisciplinary processes where indicated
  • genuine informed consent
  • monitoring of outcomes through the Australasian Pelvic Floor Procedure Registry.

This position supports patient choice, not routine surgery for every woman. Conservative care should usually be considered first, and non-mesh alternatives must be discussed when surgery is being considered.

What is the TGA position?

The Therapeutic Goods Administration (TGA) regulates medical devices in Australia. Surgical mesh is classified as a Class III medical device, the highest-risk classification, requiring more stringent evidence and regulatory assessment.

Following its safety reviews, the TGA removed certain transvaginal prolapse mesh products and single-incision mini-slings from routine supply. This did not amount to a ban on established retropubic and transobturator mid-urethral slings for SUI. The TGA’s current register includes eligible Class III urogynaecological mesh devices intended for SUI; the precise indication must always be checked in the device’s approved Instructions for Use.

The TGA requires manufacturers to provide patient information leaflets and implant cards for these devices. A woman receiving a sling should know the product used and should retain her implant card.

How effective is a mid-urethral sling?

Mid-urethral sling surgery is one of the most extensively studied operations for female SUI. Australian safety and quality guidance describes it as highly effective in the short and medium term, with long-term studies showing sustained patient satisfaction for many women.

No operation can guarantee a cure. Outcomes depend on the definition of success, length of follow-up, type of sling, surgeon experience and the individual patient. Stress leakage may persist or recur, and urgency symptoms may remain, improve or occasionally develop after surgery.

What are the risks?

Most women do not develop a serious complication, but complications can be significant and may occur early or years later. Potential risks include:

  • bleeding, infection and anaesthetic complications
  • temporary or persistent difficulty emptying the bladder, sometimes requiring catheterisation or further surgery
  • bladder or urethral injury
  • urinary tract infection
  • new or worsened urinary urgency or urge incontinence
  • persistent or recurrent stress incontinence
  • vaginal mesh exposure
  • mesh erosion into the urethra or bladder
  • pelvic, vaginal, groin or thigh pain
  • pain during intercourse
  • rarely, injury to major blood vessels, bowel or other pelvic structures.

Mesh is intended to remain permanently. If a mesh complication develops, partial or complete removal may be considered, but complete removal can be technically difficult or impossible and may require more than one operation. Removal may not fully resolve pain and can cause stress incontinence to recur.

Seek medical assessment if you develop persistent pelvic or groin pain, pain during intercourse, vaginal bleeding or discharge, recurrent urinary infections, difficulty passing urine, blood in the urine, or recurrent leakage after sling surgery.

What are the alternatives?

Treatment should be individualised. Options include:

  • no active treatment or the use of continence products
  • lifestyle measures, including weight management, treatment of constipation and chronic cough, and smoking cessation
  • supervised pelvic-floor muscle training, usually for at least three months
  • a continence pessary in suitable women
  • urethral bulking injections, which are less invasive but generally less durable and may need repeating
  • an autologous fascial sling using the patient’s own tissue
  • Burch colposuspension using sutures and native tissue.

Autologous fascial sling and colposuspension avoid permanent synthetic mesh but usually involve a longer operation and recovery and have their own risks, including voiding difficulty. There is no single best operation for every woman.

Shared decision-making and informed consent

Before proceeding, a woman should have enough time and balanced information to consider:

  • whether her symptoms are predominantly stress, urgency or mixed incontinence
  • conservative, mesh and non-mesh options
  • the expected benefits and limitations of each option
  • short- and long-term risks, including mesh-specific complications
  • the surgeon’s training and experience with the proposed procedure and alternatives
  • what follow-up will occur and how complications would be managed
  • the name and TGA registration status of the proposed device.

A second opinion is reasonable, particularly if symptoms are complex, previous continence surgery has failed, chronic pelvic pain is present, or the available options remain unclear.

The balanced Australian position

Mid-urethral slings are not appropriate for every woman, but neither are they prohibited in Australia. USANZ supports their continued availability for carefully selected patients within strong clinical-governance systems. The TGA continues to regulate eligible SUI sling devices as Class III medical devices and requires enhanced patient information and traceability.

The most important principles are an accurate diagnosis, consideration of conservative care, a balanced discussion of mesh and non-mesh alternatives, surgeon credentialing, informed consent and structured follow-up.

Important: This article provides general educational information and does not replace individual medical advice. It does not claim endorsement or approval by AHPRA, USANZ or the TGA. These organisations do not pre-approve individual practitioner website articles. Treatment recommendations must be based on personal assessment and shared decision-making.

References and further reading

  1. Urological Society of Australia and New Zealand. Vaginal mesh complications: USANZ submission, position statement and patient resources.
  2. Urological Society of Australia and New Zealand. USANZ supports pause on mesh stress urinary incontinence surgery in New Zealand. 23 August 2023.
  3. Therapeutic Goods Administration. Urogynaecological (transvaginal) surgical mesh hub. Updated 28 April 2025.
  4. Therapeutic Goods Administration. Australian transvaginal surgical mesh regulatory actions.
  5. Therapeutic Goods Administration. Current status of mesh products in Australia. Updated 9 June 2026.
  6. Australian Commission on Safety and Quality in Health Care. Treatment options for stress urinary incontinence: information for consumers. 2018.
  7. Australian Commission on Safety and Quality in Health Care. Care pathway for the management of stress urinary incontinence. 2018.
  8. Australian Health Practitioner Regulation Agency. Guidelines for advertising a regulated health service.
  9. Australian Health Practitioner Regulation Agency. Summary of the advertising requirements.