PUJ obstruction: when urine cannot drain freely from the kidney

Understanding pelvi-ureteric junction obstruction, its symptoms, investigations and treatment, including robotic-assisted pyeloplasty.

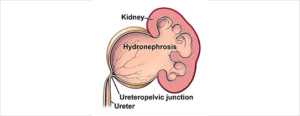
The kidneys produce urine, which collects in a funnel-shaped area called the renal pelvis before travelling down the ureter to the bladder. The pelvi-ureteric junction (PUJ) is where this funnel joins the ureter.

PUJ obstruction means urine does not pass freely through this junction. It is also called ureteropelvic junction obstruction, or UPJ obstruction. The collecting system can enlarge, a finding called hydronephrosis, and significant obstruction may eventually damage the affected kidney. However, a dilated collecting system does not automatically mean surgery is needed. Assessment must establish whether drainage is impaired and whether kidney function is at risk. [1,2]

What causes PUJ obstruction?

Some people are born with a short segment that is narrow or does not propel urine normally. Other anatomical causes include kinking or a ureter that joins the renal pelvis unusually high up. A blood vessel supplying the lower part of the kidney may cross the junction and contribute to compression. Seeing a crossing vessel on a scan does not, by itself, prove that it is causing obstruction.

A congenital problem may first become apparent in adulthood. Acquired narrowing can follow scarring, inflammation or previous surgery. Stones and other causes of upper urinary tract blockage must also be considered during investigation. [2,12]

How does it present?

Symptoms range from none at all to episodes of significant pain. Possible presentations include:

  • Aching or intermittent pain in the flank, the side of the back below the ribs.
  • Episodes of more severe pain, sometimes with nausea or vomiting.
  • Pain after a large fluid intake, when urine production increases.
  • Recurrent urinary infections, including infection of the kidney.
  • Blood in the urine or kidney stones.
  • An incidental finding of hydronephrosis on a scan.

Intermittent painful distension is sometimes called a Dietl’s crisis. These symptoms can also have other causes, so pain or blood in the urine should not simply be attributed to a known PUJ problem. [3,12]

Children may be diagnosed following an antenatal ultrasound. Childhood assessment and treatment decisions differ from those in adults and should involve a paediatric urology team. [3]

Which investigations are useful?

The investigation plan answers three questions: What does the anatomy look like? How well does each kidney function? Is urine drainage genuinely obstructed?

Urine and blood tests

Urine testing looks for blood and evidence of infection; a urine culture is useful when infection is suspected. Blood tests include creatinine and estimated glomerular filtration rate (eGFR). These assess overall kidney function, but can remain normal when the other kidney compensates for an affected kidney. [2,10]

Ultrasound

Ultrasound shows collecting-system dilatation and assesses the thickness of the kidney tissue. It is useful for follow-up because it does not involve radiation. Ultrasound alone cannot reliably establish the functional significance of a PUJ narrowing. [2,3]

CT or MR urography

CT urography can define the junction, identify stones and assess surrounding structures, including crossing vessels. The use of intravenous contrast depends on kidney function and other clinical factors.

MR urography is an alternative in selected patients, particularly when avoiding radiation is desirable. The choice of scan is individualised. [1,2]

MAG3 diuretic renogram

This nuclear medicine scan follows a small injected tracer through the kidneys. A diuretic, usually furosemide, helps assess drainage.

It measures:

  • Differential or split renal function: the proportion contributed by each kidney.
  • Drainage: how effectively tracer leaves the collecting system.

Interpretation considers the images, drainage curves, kidney function, hydration and bladder emptying. A slow drainage number alone is insufficient to diagnose clinically significant obstruction: a large collecting system or poorly functioning kidney can make interpretation difficult. [4]

Further tests in selected cases

A retrograde pyelogram introduces contrast into the ureter during a telescopic bladder examination. It can clarify anatomy when other imaging is incomplete. It is not routinely needed in every patient. [2]

Does every PUJ obstruction need treatment?

No. Observation can be appropriate when symptoms are absent or minor, kidney function is stable, and assessment does not suggest harmful obstruction. Monitoring may include symptoms, ultrasound and repeat functional imaging when indicated. The interval depends on the findings. [5]

Intervention is more likely to be recommended for persistent or troublesome symptoms, recurrent kidney infections, associated stones, or deteriorating function. Decisions use the overall clinical picture rather than the ultrasound appearance alone. [2]

What are the treatment options?

Option When it may be considered Main limitation
Observation Stable function with few symptoms Requires planned follow-up
Ureteric stent or nephrostomy Urgent drainage or temporary management Usually does not permanently correct the narrowing
Endopyelotomy or balloon dilatation Selected narrowings or recurrent obstruction Generally less durable than reconstructive repair
Pyeloplasty A significant obstruction requiring reconstruction Requires an operation and recovery

Temporary or emergency drainage

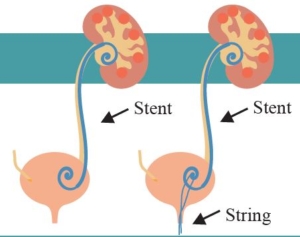
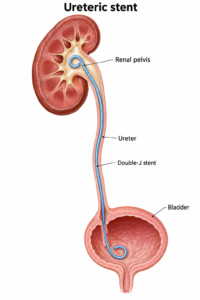
A ureteric stent passes internally from the kidney to the bladder. A nephrostomy drains the kidney through a tube placed through the skin of the back. These can relieve obstruction while infection is treated or definitive surgery is planned. [5,9]

An infected obstructed kidney is an emergency. Antibiotics may be needed together with urgent drainage. Definitive reconstruction is usually considered after the acute problem has been controlled. [9,10]
Endoscopic treatment

Endopyelotomy opens the narrowed segment from inside the urinary tract; balloon dilatation stretches it. Suitability depends on the anatomy, kidney function and previous treatment.

A large observational study found more repeat procedures after endopyelotomy than after pyeloplasty. Because patients were not randomly assigned to treatment, these results inform discussion but cannot predict an individual outcome. [1,6]

Robotic-assisted pyeloplasty: how is the repair performed?

Pyeloplasty reconstructs the junction to improve drainage. It can be performed through an open incision, conventional laparoscopic keyhole surgery, or robotic-assisted keyhole surgery.

The commonly used Anderson–Hynes dismembered pyeloplasty removes the narrowed segment. The surgeon opens the ureter more widely and stitches it back to the renal pelvis, creating a broader connection. Where a crossing vessel contributes to obstruction, the reconstruction can be positioned in front of it while preserving the vessel. [3]

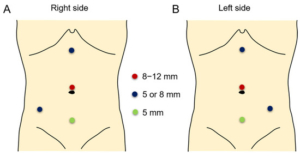
During robotic-assisted surgery, the surgeon controls the instruments from a console. Magnified three-dimensional vision and articulated instruments assist dissection and suturing. The robot does not operate independently. [7]

A temporary internal stent is commonly placed to support healing. A bladder catheter and, sometimes, a drain may also be used initially. [5,7]

How successful is pyeloplasty, and is robotic surgery better?

Published literature commonly reports success above 90% for primary pyeloplasty, including open, laparoscopic and robotic approaches. Success may mean symptom relief, improved drainage or freedom from further surgery; definitions and follow-up differ between studies. These figures are not a guarantee. [1]

Robotic surgery is an established option, but it should not be presented as necessary or universally superior. Comparative research supports good outcomes with both conventional laparoscopic and robotic repair. Much of the evidence is observational, with differences in patient selection, surgical experience and follow-up. The choice should consider anatomy, surgeon expertise, availability and cost. [8]

The goals are to improve drainage, relieve attributable symptoms and preserve function. Previously lost kidney function may not fully recover, even after a technically successful operation. [11]

What are the risks and recovery expectations?

Risks include bleeding, infection, urine leakage, injury to nearby structures, recurrent narrowing, persistent pain and the need for another procedure. Anaesthetic complications and blood clots are also possible. Occasionally, conversion to open surgery is required. [5,7]

Stents can cause urinary frequency, urgency, blood in the urine and discomfort. Their removal must be arranged. Many patients leave hospital after approximately one to three days following uncomplicated keyhole repair, but recovery varies. Stents are often removed after four to six weeks. [5,7]

Follow-up may include ultrasound and a repeat drainage scan. Residual dilatation does not automatically mean the repair has failed; symptoms, drainage and function are assessed together. [4]

What if the kidney already functions poorly?

A low split-function result does not automatically mean the kidney must be removed. Selected patients may benefit from reconstruction or temporary drainage followed by reassessment. A systematic review found that pyeloplasty may relieve symptoms and stabilise function in poorly functioning kidneys, but the evidence was limited and recovery was unpredictable. [11]

Nephrectomy may be considered if the kidney has negligible useful function and causes ongoing pain or infection. This requires an individual discussion, including the health of the other kidney.

When should I seek urgent help?

Seek urgent medical assessment for fever or shaking chills with flank pain, severe uncontrolled pain, persistent vomiting, markedly reduced urine output, or feeling seriously unwell. The threshold for urgent assessment is particularly low if you have a single functioning kidney. [9,10]

This page provides general education and does not replace an individual assessment. The most suitable investigation and treatment depend on symptoms, anatomy, kidney function and overall health.

References

  1. Khan F, Ahmed K, Lee N, et al. Management of ureteropelvic junction obstruction in adults. Nature Reviews Urology. 2014;11:629–638. doi:10.1038/nrurol.2014.240.
  2. Borin JF. Ureteropelvic Junction Obstruction in Adults. Reviews in Urology. 2017;19(4):261–264. Full text.
  3. Oxford University Hospitals NHS Foundation Trust. PUJ Obstruction and Pyeloplasty: information for parents and carers. 2025. Patient leaflet. Used for congenital presentation and reconstruction principles; adult management differs.
  4. SNMMI/EANM. Procedure Standard/Practice Guideline for Diuretic Renal Scintigraphy in Adults With Suspected Upper Urinary Tract Obstruction 1.0. 2018. Guideline.
  5. British Association of Urological Surgeons. Keyhole reconstruction of the kidney pelvis: laparoscopic pyeloplasty. 2023. Patient leaflet.
  6. Jacobs BL, Lai JC, Seelam R, et al. The comparative effectiveness of treatments for ureteropelvic junction obstruction. Urology. 2018;111:72–77. doi:10.1016/j.urology.2017.09.002.
  7. Kingston and Richmond NHS Foundation Trust. Kidney obstruction removal with robot. Patient information.
  8. Uhlig A, Uhlig J, Trojan L, et al. Surgical approaches for treatment of ureteropelvic junction obstruction—a systematic review and network meta-analysis. BMC Urology. 2019;19:112. doi:10.1186/s12894-019-0544-7.
  9. Guy’s and St Thomas’ NHS Foundation Trust. Nephrostomy catheter to drain urine from the kidney. Patient information.
  10. NHS. Hydronephrosis. Patient information.
  11. Pyeloplasty in Adults With Ureteropelvic Junction Obstruction in Poorly Functioning Kidneys: A Systematic Review. 2021. PubMed.
  12. Cleveland Clinic. Ureteropelvic Junction Obstruction. Reviewed 2024. Patient information.

Prepared October 2026.
Ureteroceles: symptoms, investigations and treatment

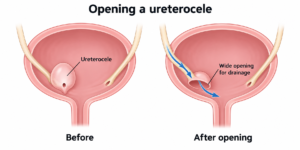
A ureterocoele (also spelt ureterocele) is a balloon-like swelling at the lower end of a ureter: the tube carrying urine from the kidney to the bladder. The swelling usually projects into the bladder. Its opening may be narrow, slowing urine drainage and sometimes causing infection, stones or pressure on the kidney.

Some ureterocoeles cause no problems and are found incidentally. Others need treatment to improve drainage and protect kidney function. [1,2]

Congenital or acquired?

Most true ureteroceles are congenital, meaning they develop before birth. They may be detected on pregnancy ultrasound, during childhood or much later in adult life. A diagnosis in adulthood does not necessarily mean the ureterocele developed recently.

A ureterocoele can occur with a single ureter or a duplex collecting system, in which a kidney has two drainage systems. In a duplex kidney, the ureterocoele commonly involves the ureter draining the upper part of the kidney.

An intravesical or orthotopic ureterocoele lies within the bladder. An ectopic ureterocoele extends into the bladder neck or urethra and may interfere with bladder emptying. Adults more often have an intravesical ureterocoele associated with a single drainage system. [1,3]

The term “acquired ureterocoele” needs care. An acquired swelling of the lower ureter that resembles a ureterocoele is often called a pseudoureterocoele. A stone or a lesion involving the bladder near the ureteric opening can cause this appearance. An irregular or unusual swelling should therefore be investigated rather than assumed to be a harmless congenital abnormality. [4]

Presentation and symptoms

A ureterocoele may be discovered during investigations for an unrelated problem. When symptoms occur, they can include:

  • Recurrent urinary tract infections.
  • Pain in the side, back or lower abdomen.
  • Burning, urgency or frequent urination, particularly with infection.
  • Blood in the urine.
  • Stones trapped within the ureterocoele.
  • Difficulty emptying the bladder or, occasionally, urinary retention.

Children may present with unexplained fever, feeding difficulties or poor growth associated with infection. Rarely, a large ureterocoele can prolapse through the urethra.

Symptoms depend on whether the swelling obstructs drainage, contains a stone or affects the bladder outlet. Prolonged obstruction and repeated kidney infections can damage kidney function. [2,5]

What investigations are needed?

Investigations establish the anatomy, assess drainage and kidney function, and look for infection or reflux. Not everyone needs every test.

Investigation What it helps assess
Urine testing and culture Infection and the appropriate antibiotic
Blood tests Kidney function; inflammatory markers when infection is suspected
Kidney and bladder ultrasound The ureterocoele, stones and swelling of the kidney or ureter
CT, sometimes CT urography Stones and detailed urinary tract anatomy, particularly in adults
MR urography Complex anatomy, including duplicated drainage systems
MAG3 or DMSA kidney scan Drainage and relative function, or functioning kidney tissue and scarring
Micturating cystourethrogram (MCUG/VCUG) Urine flowing backwards from the bladder into a ureter
Cystoscopy Direct inspection of the bladder and ureteric openings

CT involves radiation; contrast use depends on kidney function and the clinical question. Reflux testing is particularly relevant in children or when infection, complex anatomy or postoperative concerns warrant it. Cystoscopy can clarify an uncertain diagnosis and allow treatment during the same procedure. [1,3,5]

Does every ureterocoele need surgery?

No. Observation with planned follow-up may be appropriate when there are no troublesome symptoms, significant obstruction or recurrent infections, and kidney function is satisfactory.

Monitoring may include ultrasound and review of symptoms. Antibiotics treat infection but do not correct the swelling. Preventive antibiotics are considered selectively, particularly in children at increased infection risk. [6]

An infected, obstructed kidney requires urgent assessment and drainage, alongside antibiotics. Drainage may involve endoscopic opening of the ureterocoele or a nephrostomy, a tube placed through the skin into the kidney. Antibiotics alone may be insufficient when infected urine cannot drain. [1]

Endoscopic incision or deroofing

Treatment can often be performed through a telescope passed along the urethra into the bladder, usually under general anaesthesia.

Incision or puncture creates an opening in the wall of the ureterocoele. Deroofing removes part of its wall to create a broader opening. Both aim to let urine drain freely and reduce the balloon-like swelling.

The choice depends on anatomy, obstruction and associated stones. Instruments using electrical energy or a laser may be used. A stone within the sac can sometimes be fragmented and removed at the same operation.

A bladder catheter may be needed temporarily. Endoscopic treatment can be sufficient for a straightforward adult intravesical ureterocoele, while complex duplex or ectopic cases may need further surgery. [5,7,8]

Where does a ureteric stent fit in?

A double-J stent is a soft internal tube extending from the kidney to the bladder. It may be used selectively to support drainage after treatment, during associated stone surgery or while swelling settles. It is not required in every case and does not necessarily provide a permanent solution to the ureterocoele. [8]

Stents can cause frequency, urgency, bladder discomfort, blood in the urine and flank pain, sometimes after urination. Infection, displacement and mineral encrustation are other possible problems.

Every temporary stent needs a clear removal or exchange plan. The duration depends on the procedure and clinical circumstances. Contact the treating team if the removal date is unclear or overdue. [9]

Possible complications, including vesicoureteric reflux

Possible complications of endoscopic treatment include bleeding, infection, discomfort, injury to nearby urinary tract structures, persistent obstruction or narrowing as the opening heals. Repeat treatment or reconstructive surgery may be needed. [3,5,7]

Vesicoureteric reflux (VUR) means urine travels backwards from the bladder towards the kidney. It may already be present before treatment, particularly in a duplex system, or develop after opening the ureterocoele alters the natural anti-reflux mechanism.

Reflux does not automatically mean kidney damage or another operation. Its significance depends on its severity, infections, kidney function and bladder function. Monitoring may be appropriate; persistent significant reflux with recurrent infections can require further treatment, including ureteric reimplantation.

Risk varies with anatomy and technique. Ectopic ureterocoeles and duplex systems have higher rates of postoperative reflux and additional surgery than simpler intravesical cases. [1,7]

In one small adult study, reflux was detected in two of 23 patients followed after endoscopic incision, persisting in one at six months. These results illustrate the possibility of reflux; they do not predict an individual patient’s risk. Adult evidence largely comes from small studies. [7]

Further surgery and follow-up

Reconstructive options include reimplanting the ureter into the bladder or joining it to another healthy ureter in a duplex system. Occasionally, a severely damaged, poorly functioning kidney segment causing problems may require removal. Specialist assessment determines whether reconstruction, observation or removal is appropriate. [1]

Follow-up checks that drainage has improved and looks for recurrent infection, obstruction or reflux. Ultrasound is commonly used; further imaging is selected according to the findings. Symptom improvement alone does not confirm that drainage is normal. [5,7]

Seek urgent medical care for fever or shaking chills with flank pain, inability to pass urine, severe worsening pain, persistent vomiting or feeling seriously unwell. These symptoms may indicate infection or obstruction, including after treatment or with a stent in place. [1,9]

This article provides general education. Treatment should be tailored to the patient’s anatomy, symptoms and kidney function in consultation with their urologist.

References

  1. European Association of Urology. EAU Guidelines on Paediatric Urology: Ureterocele and ectopic ureter. Current online guideline, accessed 5 October 2026. https://uroweb.org/guidelines/paediatric-urology/chapter/ureterocele-and-ectopic-ureter
  2. European Association of Urology. Patient information: Ureterocele. https://patients.uroweb.org/condition/duplex-congenital-malformations-of-the-urinary-tract/ureterocele
  3. The Outcome of Transurethral Electro-Endoscopic Resection of Orthotopic Single System Ureterocoeles in Adults Nigerians. https://pmc.ncbi.nlm.nih.gov/articles/PMC11073836/
  4. Thornbury JR, Silver TM, Vinson RK. Ureteroceles vs. pseudoureteroceles in adults. Urographic diagnosis. Radiology. 1977;122(1):81–84. doi:10.1148/122.1.81. https://pubmed.ncbi.nlm.nih.gov/830358/
  5. An adult ureterocele complicated by a large stone: A case report. International Journal of Surgery Case Reports. 2018. https://pmc.ncbi.nlm.nih.gov/articles/PMC5927814/
  6. European Association of Urology. Watchful waiting for ureterocele. https://patients.uroweb.org/condition/duplex-congenital-malformations-of-the-urinary-tract/ureterocele/wait-and-see-ureterocele
  7. Vijay MK, et al. The safety and efficacy of endoscopic incision of orthotopic ureterocele in adult. Saudi Journal of Kidney Diseases and Transplantation. 2011;22(6):1169–1174. https://pubmed.ncbi.nlm.nih.gov/22089776/
  8. A Large Stone Within a Ureteroceles: A Diagnostic Pitfall and the Utility of Holmium Laser Deroofing as a Viable Surgical Option. https://pubmed.ncbi.nlm.nih.gov/29468199/
  9. British Association of Urological Surgeons. Information about your ureteric stent. https://www.baus.org.uk/_userfiles/pages/files/Patients/Leaflets/Stent%20advice.pdf

Upper Tract Urothelial Carcinoma

Cancer of the Renal Pelvis and Ureter

Urothelial carcinoma is most commonly associated with the bladder, but the same specialised lining extends all the way from the bladder up the ureters and into the collecting system of each kidney.

When a urothelial cancer develops in the renal pelvis or ureter, it is called upper tract urothelial carcinoma (UTUC).

UTUC is considerably less common than bladder cancer. Importantly, its behaviour varies enormously. Some tumours are small, superficial and relatively slow growing, while others are aggressive cancers capable of invading the kidney, surrounding tissues, lymph nodes and distant organs.

The key to successful management is therefore not simply finding the tumour, but determining how aggressive it is and how likely it is to spread.


What Is the Upper Urinary Tract?

Urine produced by the kidney drains through:

Kidney → renal calyces → renal pelvis → ureter → bladder → urethra

The inner surface of the renal pelvis, ureter and bladder is covered by urothelium, previously called transitional epithelium.

Cancer arising from these cells is called urothelial carcinoma.

UTUC can therefore occur in:

  • the renal pelvis;
  • one or more renal calyces;
  • the upper, middle or lower ureter;
  • multiple areas of the same urinary tract; or
  • occasionally both upper urinary tracts.

Patients with UTUC may also develop urothelial tumours within the bladder, either at the same time or later.


What Causes Upper Tract Urothelial Cancer?

Cancer develops when genetic damage accumulates within urothelial cells, allowing them to grow and divide abnormally.

Frequently there is no single identifiable cause, but several important risk factors are recognised.

Smoking

Cigarette smoking is one of the most important preventable risk factors for urothelial carcinoma.

Carcinogenic chemicals absorbed through the lungs enter the bloodstream, are filtered by the kidneys and become concentrated in the urine. The urothelium may therefore be exposed to these substances for many years.

Stopping smoking remains important even after diagnosis because of its wider health benefits and potential relevance to future urothelial cancer risk.

Previous bladder cancer

Patients who have previously had urothelial carcinoma of the bladder have an increased risk of developing urothelial carcinoma elsewhere within the urinary tract.

Similarly, patients treated for UTUC remain at risk of subsequently developing bladder cancer.

Occupational chemical exposure

Long-term exposure to certain industrial chemicals, particularly some aromatic amines historically associated with dye, rubber, textile, leather and chemical industries, has been associated with urothelial cancer.

Lynch syndrome

A small but important proportion of UTUC occurs in people with Lynch syndrome, an inherited disorder caused by abnormalities in DNA mismatch-repair genes.

UTUC, particularly in a younger patient or someone with a strong family history of bowel, endometrial or other Lynch-associated cancers, may prompt consideration of genetic assessment.

Chronic inflammation

Long-standing urinary tract inflammation and some chronic infections may contribute to malignant change. Chronic stone disease has particularly been associated with squamous carcinoma of the renal pelvis, which is a different and much less common tumour type.

Previous analgesic exposure

Heavy historical exposure to certain analgesics, particularly phenacetin-containing preparations that are no longer routinely used in many countries, has been associated with upper tract urothelial malignancy.


What Are the Symptoms?

Blood in the urine

The most common warning sign is:

Haematuria: blood in the urine

This may be obvious, turning the urine pink, red or occasionally dark brown.

Importantly, haematuria may:

  • occur only once;
  • disappear for weeks or months;
  • be completely painless; or
  • only be detected microscopically on a urine test.

Visible blood in the urine should always be appropriately investigated, particularly in adults.

Do not assume that painless bleeding is simply due to infection, prostate enlargement or a blood-thinning medication without appropriate assessment.


Flank or loin pain

A tumour can obstruct drainage of urine from the kidney.

This may produce:

  • persistent flank discomfort;
  • loin pain;
  • renal colic;
  • hydronephrosis, where the kidney becomes dilated because urine cannot drain normally.

Blood clots passing down the ureter can occasionally produce severe colicky pain resembling a kidney stone.


Recurrent urinary symptoms

Some patients experience:

  • urinary frequency;
  • urgency;
  • burning when passing urine;
  • recurrent apparent urinary tract infections.

These symptoms are much more commonly caused by benign conditions, but persistent or unexplained symptoms may warrant further investigation.


General symptoms

More advanced disease can occasionally cause:

  • unexplained weight loss;
  • loss of appetite;
  • fatigue;
  • persistent pain;
  • anaemia.

Fortunately, many tumours are detected before these symptoms develop.


How Is UTUC Diagnosed?

Investigation usually involves several complementary tests.

1. Urine testing

Urine is assessed for:

  • microscopic blood;
  • infection;
  • renal abnormalities; and
  • sometimes malignant cells.

Urine cytology

Urine cytology examines shed urinary cells under a microscope.

It is particularly useful for detecting high-grade urothelial carcinoma, although a negative cytology result does not completely exclude cancer.

Selective urine samples may sometimes be collected directly from the affected upper urinary tract.


2. CT Urography

CT urography is one of the most important imaging investigations for suspected UTUC.

Contrast-enhanced CT imaging allows assessment of:

  • the kidneys;
  • renal collecting systems;
  • ureters;
  • bladder;
  • lymph nodes; and
  • surrounding organs.

A tumour may appear as a filling defect, thickening of the ureter or renal pelvis, or an infiltrating mass.

CT can also identify obstruction and hydronephrosis.


3. Cystoscopy

Because urothelial cancer can occur at more than one location, the bladder should generally also be examined.

A flexible cystoscope is passed through the urethra into the bladder to look for associated bladder tumours.


Ureteroscopy and Biopsy

Sometimes imaging alone cannot provide enough information about the tumour.

A ureteroscope is a very fine telescope passed through the urethra and bladder and then into the ureter and renal collecting system.

This allows the urologist to directly inspect the tumour.

During ureteroscopy it may be possible to:

  • identify the location of the tumour;
  • assess whether there is one tumour or several;
  • estimate its size;
  • obtain selective urine cytology;
  • take a biopsy; and
  • in selected low-risk tumours, treat the lesion with a laser.

Biopsy is particularly helpful in determining whether the tumour is low-grade or high-grade.

An important limitation is that ureteroscopic biopsy samples are small, so determining the exact depth of invasion before definitive surgery can sometimes be difficult.


Low-Risk Versus High-Risk Disease

Modern management increasingly divides UTUC according to its risk of invasion and progression.

Factors considered include:

  • tumour grade;
  • appearance on CT;
  • tumour size;
  • number of tumours;
  • presence of hydronephrosis;
  • urine cytology;
  • ureteroscopic appearance;
  • biopsy findings;
  • evidence of invasion; and
  • previous urothelial cancer.

This distinction is extremely important because treatment can range from relatively conservative endoscopic therapy to removal of the entire kidney and ureter.


Treatment of Low-Risk UTUC

Selected patients with low-risk disease may be suitable for kidney-sparing treatment.

The objective is to control the cancer while preserving as much functioning kidney tissue as possible.

Ureteroscopic Laser Treatment

A ureteroscope is passed to the tumour and the lesion is treated using laser energy.

Laser treatment can:

  • vaporise;
  • coagulate; or
  • fragment the tumour.

Modern flexible ureteroscopes allow access to much of the renal collecting system.

Advantages

Kidney-sparing treatment may:

  • preserve kidney function;
  • avoid major abdominal surgery;
  • reduce recovery time;
  • be particularly valuable in patients with impaired kidney function or a solitary kidney.

Disadvantages

The trade-off is the need for very careful surveillance.

UTUC has a tendency to recur, so patients may require repeated:

  • ureteroscopy;
  • urine cytology;
  • CT imaging; and
  • occasionally further laser treatments or biopsies.

Kidney preservation therefore does not mean that the tumour can simply be treated once and forgotten.


Segmental Ureterectomy

Some tumours confined to a relatively short section of ureter can be treated by removing only the affected portion.

This is known as segmental ureterectomy.

It is particularly useful for appropriately selected tumours of the distal ureter.

The affected segment is removed and the remaining ureter is either reconnected or reimplanted into the bladder.

This can preserve the kidney while providing a complete surgical specimen for pathological examination.


Treatment of High-Risk UTUC

For patients with high-risk localised disease, the standard definitive operation is generally:

Radical Nephroureterectomy

This involves removal of:

the kidney + entire ureter + a cuff of bladder surrounding the ureteric opening

Removing the complete ureter is important because leaving part of the affected ureter behind may allow cancer to recur within the remaining urothelium.

The procedure can often be performed using:

  • robotic surgery;
  • laparoscopic surgery; or
  • occasionally open surgery.

The choice depends upon tumour characteristics, anatomy, previous surgery and individual circumstances.


What About the Lymph Nodes?

For selected high-risk tumours, lymph nodes draining the affected area may also be removed.

A lymph-node dissection can provide important staging information and may be incorporated into the surgical management of appropriately selected high-risk disease.


Chemotherapy

Systemic chemotherapy plays an important role in selected patients with higher-risk UTUC.

Platinum-based chemotherapy, particularly cisplatin-containing treatment, has traditionally formed an important part of systemic treatment.

Chemotherapy may be given:

Before surgery: neoadjuvant chemotherapy

One potential advantage is that both kidneys are still present, and renal function may therefore be better able to tolerate cisplatin.

After surgery: adjuvant chemotherapy

Chemotherapy may be recommended after nephroureterectomy when the final pathology demonstrates sufficiently high-risk disease.

An important consideration is that removing a kidney can reduce renal function, potentially affecting the patient’s ability to receive certain chemotherapy drugs.

Treatment decisions are therefore ideally made by a multidisciplinary uro-oncology team.


Immunotherapy and Newer Treatments

The treatment of advanced urothelial carcinoma has changed considerably in recent years.

Depending upon the stage, previous treatment and molecular characteristics of the cancer, systemic therapy may include combinations of:

  • platinum-based chemotherapy;
  • immune checkpoint inhibitors;
  • antibody-drug conjugates; and
  • targeted treatments for selected molecular abnormalities such as FGFR alterations.

These treatments are particularly relevant to patients with locally advanced, recurrent or metastatic disease.

Treatment is increasingly individualised according to the biological characteristics of the tumour and the patient’s kidney function and overall health.


Treatment Placed Directly Into the Upper Urinary Tract

For carefully selected non-invasive disease, medication may sometimes be delivered directly into the renal pelvis and ureter.

Options can include topical chemotherapy or immunotherapy in selected circumstances.

A chemoablative gel formulation of mitomycin has also been developed for selected low-grade UTUC, allowing prolonged contact between chemotherapy and the tumour.

These treatments are specialised and are not suitable for every patient.


What Happens After Treatment?

Follow-up is particularly important because urothelial carcinoma has a characteristic ability to develop at another point along the urinary tract.

After treatment, surveillance may include:

  • cystoscopy;
  • urine cytology;
  • CT urography or other upper-tract imaging;
  • blood tests to assess kidney function;
  • ureteroscopy following kidney-sparing treatment.

The exact surveillance schedule depends upon whether the original tumour was low or high risk and what treatment was performed.


Can the Cancer Return in the Bladder?

Yes.

One of the distinctive features of UTUC is the significant risk of subsequently developing urothelial carcinoma within the bladder.

Published data have reported subsequent bladder tumours in a substantial proportion of patients following treatment of UTUC.

For this reason, regular cystoscopic surveillance remains important even when the original kidney or ureteric tumour has been completely removed.


What Is the Prognosis?

The outlook for UTUC depends predominantly upon:

  • tumour stage;
  • tumour grade;
  • lymph-node involvement;
  • metastatic spread;
  • tumour multifocality;
  • response to treatment; and
  • certain pathological and molecular characteristics.

The most important question is whether the cancer remains superficial or has invaded deeply through the wall of the renal pelvis or ureter.

Superficial, localised disease

The outlook can be excellent when a tumour is identified while still superficial and confined to the upper urinary tract. The National Cancer Institute reports that more than 90% of superficial cancers confined to the renal pelvis or ureter may be curable.

Invasive disease

Once a tumour has invaded deeply into the wall or surrounding tissues, the risk of lymph-node involvement and distant spread increases substantially.

High-grade and invasive tumours therefore usually require more aggressive treatment and closer surveillance.

Metastatic disease

When UTUC has spread to distant organs, treatment is generally systemic rather than surgical alone.

Although metastatic UTUC remains a serious disease, modern systemic treatments have expanded considerably and can provide meaningful cancer control for selected patients.


UTUC and Kidney Function

Preserving kidney function is an important part of treatment planning.

Removing one kidney is usually well tolerated when the opposite kidney is healthy, but kidney function can become particularly important in patients with:

  • pre-existing chronic kidney disease;
  • diabetes;
  • hypertension;
  • a solitary kidney;
  • bilateral upper-tract tumours; or
  • conditions likely to affect future kidney function.

The decision between kidney-sparing treatment and radical nephroureterectomy therefore involves balancing two priorities:

adequate cancer control and preservation of renal function.

Cancer safety remains the priority, but in appropriately selected low-risk disease these objectives can often coexist.


When Should You See a Urologist?

Seek medical assessment if you develop:

  • visible blood in the urine;
  • persistent microscopic haematuria;
  • unexplained flank or loin pain;
  • recurrent unexplained urinary symptoms;
  • abnormal findings on kidney imaging; or
  • haematuria with a previous history of urothelial cancer.

Blood in the urine should not automatically be attributed to prostate enlargement, infection, kidney stones or blood-thinning medication without appropriate investigation.


The Bottom Line

Upper tract urothelial carcinoma is an uncommon cancer arising from the lining of the renal pelvis or ureter.

Blood in the urine is its most important warning sign.

Investigation commonly involves CT urography, cystoscopy, urine cytology and, when required, ureteroscopy with biopsy.

Treatment is increasingly tailored to the biological risk of the tumour.

Small, low-grade tumours may sometimes be managed with kidney-sparing ureteroscopic laser treatment or segmental surgery, while high-risk invasive cancers generally require radical nephroureterectomy with removal of the bladder cuff, sometimes combined with lymph-node surgery and systemic treatment.

Long-term surveillance is essential because urothelial cancer can recur elsewhere within the urinary tract, particularly the bladder.

The reassuring part is that when UTUC is detected while still superficial and localised, the likelihood of successful treatment can be very high.


A Note for Patients

Every upper tract urothelial tumour is different. Treatment depends upon the tumour’s location, size, grade, stage, number of lesions, kidney function and your general health.

Management should therefore be individualised following discussion with your urologist and, for higher-risk disease, a multidisciplinary uro-oncology team.

This information is intended for general patient education and should not replace individual medical advice, examination or treatment recommendations from your treating specialist.

The current 2026 EAU guideline specifically incorporates updated risk stratification, kidney-sparing management, bladder-cuff and lymph-node considerations, systemic therapy, and follow-up recommendations.

Endoscopic vesico-ureteric reflux surgery (STING)

Indication:

  • Vesical-ureteric reflux. It is a minimally invasive procedure performed with endoscopy.
  • A synthetic material (Bulkamid) is injected at the ureteric opening to prevent reflux
  • Grade 3-4 Vesical-Ureteric Reflux where conservative management has failed with a progressive deterioration in renal function.

How is it done?

  • Patients will receive a general anaesthesia.
  • Prophylactic antibiotics is given.
  • The correct ureteric system is identified and marked while you are awake.
  • This will be an endoscopic procedure.
  • A cystoscopy will be done with injection of Bulkamid just under the affected ureteric orifice.
  • Enough Bulkamid will be injected to partially close the ureteric opening yet not obstructing the orifice.
  • An indwelling catheter is placed.

What next?

  • You may be in hospital the day or overnight.
  • As soon as you are comfortable with no signs of pain and emptying your bladder sufficiently, you will be discharged.
  • Review in 6 weeks.
  • DON’T SUFFER IN SILENCE, OR YOU WILL SUFFER ALONE!

Download Information Sheet

Wes Cystoscopy RGP and STING anti-reflux VUR procedure

Pelvi-Ureteric Junction Repair (PUJ) – Robotic Assisted

A congenital or acquired narrowing in the ureteric pelvis junction. This narrowing is excised with a reconnection. There are several techniques described in repairing this: I prefer the Dismembered Pyeloplasty

Why is it done?

  • High grade obstruction.
  • Causing deterioration of renal function.
  • Thinning of renal cortex.
  • Chronic pain.
  • Chronic infection.
  • Recurrent renal calculi.

Causes

  • Congenital lack of muscle, or neuro transmission in this area, causing a non-functioning part leading to obstruction.
  • Vesico-ureteric reflux, longstanding can also cause this.
  • Usually diagnosed in kids.
  • Crossing vessel.

How is it done?

Robotic assisted pyeloplasty.

  • Types
      • Dismembered.
      • Foley’s Y-V Pyeloplasty.
      • Culp-Dewierd.
      • Pelvi-calyceal pyeloplasty.
      • Endopyelotomy with laser.
    • Patients will receive a general anaesthesia.
    • Prophylactic antibiotics is given.
    • The correct ureteric system is identified and marked while you are awake.
    • This will be mostly a robotic / laparoscopic procedure.
    • The endoscopic procedure is reserved as a second line in my practice.
    • Laparoscopic ports are placed
    • The affected ureter is exposed, the defect cut out with a re-anastomosis of a spatulated ureter to a trimmed renal pelvis over a ureteric stent.
    • An indwelling catheter is placed. A drain is placed.

What next?

  • You may be in hospital for 3 days
  • Your drain will be removed when there is no urine draining.
  • Your catheter will be removed the following day.
  • As soon as you are comfortable with no signs of pain and emptying your bladder sufficiently, you will be discharged
  • A ward prescription may be issued on your discharge, for your own collection at any pharmacy.
  • A follow-up appointment will be scheduled for 6 weeks to remove your ureteric stent under local anaesthesia with a Flexible Cystoscope.
  • A review with a CT IVP will be scheduled 6 weeks after this to check on the end result of the ureter.
  • Any pain or signs of fever require an urgent review.
  • DON’T SUFFER IN SILENCE, OR YOU WILL SUFFER ALONE!

Possible Complications

  • Re-stenosis with recurrent obstruction.
  • Second procedure.
  • With further deterioration of renal function, you may require a nephrectomy where affected kidney contributes < 15-20% of total renal function.
  • Urine leak, Urinoma, requiring drainage.
  • Infection possible sepsis requiring long-term antibiotics.


Download Information Sheet

Wes RA reair

Laser Endo-Pyelotomy

Endoscopic opening of pelvi-ureteric junction stricture.

Endoscopic technique of incising a short stricture with a laser. A stent remains 6 weeks post operatively

Why is it done?

  • Stricturing or narrowing of the ureter causing significant hydronephrosis.
  • Leading to chronic infection.
  • End-result is loss of renal function.
  • An end-to-end anastomosis can be considered in the mid ureter.
  • A Reimplantation into the bladder with lower ureteric strictures.
  • A pelvi-ureteric junction repair in higher ureteric strictures.
  • A trans uretero-ureteric anastomosis joining one ureter to the other where long defects are present.
  • Renal Auto Transplantation where ureter is completely damaged or.
  • An ileal ureteric substitution where to whole ureter is damaged.

How is it done?

  • Endoscopic technique.
  • Patients will receive a general anesthesia.
  • Prophylactic antibiotics is given.
  • The correct ureteric system is identified and marked while you are awake.
  • This will be mostly an endoscopic procedure.
  • A cystoscopy will be done with placement of ureteric guidewires.
  • The affected ureter is entered with ureteroscopy. Laser is used to cut through the short stricture until peri-ureteric fat is observed.
  • This is not an advisable procedure where the stricture overlies vascular structures.
  • A ureteric stent is placed.
  • An indwelling catheter is placed.

What next?

  • You may be in hospital for 3 days.
  • Your drain will be removed when there is no urine draining.
  • Your catheter will be removed the following day.
  • As soon as you are comfortable with no signs of pain and emptying your bladder sufficiently, you will be discharged.
  • A follow-up appointment will be scheduled for 6 weeks to remove your ureteric stent under local anesthesia with a Flexible Cystoscope.
  • A review with a CT IVP will be scheduled 6 weeks after this to check on the end result of the ureter.
  • Any pain or signs of fever require an urgent review.
  • DON’T SUFFER IN SILENCE, OR YOU WILL SUFFER ALONE!

Download Information Sheet

Wes Laser Endo-Pyelotomy

Rigid Cystoscopy, Retrograde Pyelogram, Stent Management

A therapeutic procedure under general anaesthetic, where a rigid cystoscopy is done in the bladder via the urethra, ureteric catheters are placed to enable imaging of the upper tracts with/without insertion or removal of ureteric stents

Why is it done?

To investigate:

  • Hematuria (blood in the urine)
  • Recurrent upper urinary tract infections
  • Space occupying lesions in the kidneys and ureters
  • Abnormal cells suggestive of urothelial carcinoma, on urine cytology


Risk factors:

  • Strong family history of bladder cancer
  • Smokers or passive smokers
  • Factory workers: dyes, paints, etc
  • Exposure to Schistosoma (Bilharzia)
  • Renal stone disease, bladder stones


How is it done?

  • This is done under General anaesthesia.
  • A cystoscopy is performed by placing a camera in the urethra with the help of a lubricant gel and saline irrigation.
  • The bladder is then distended with saline.
  • The inside of the bladder is viewed for pathology.
  • A retrograde pyelogram is done at the same time, (placement of small silicone catheters up the kidney pipes). Through this iodine contrast is injected up into the kidney collecting systems. This facilitates the viewing of kidney pipes and kidney collecting systems on X-ray to exclude any upper tract pathology.
  • If any abnormalities are found in the kidney/ ureters, a ureteroscopy (which is the placement of a long thin camera up the ureter) will be performed.
  • If any suspicious lesions are seen, a biopsy will be taken.
  • A ureteric stent may be placed
  • Urine would have been sent for cytology, to rule out the existence of cancer.

Antibiotics may be given to prevent infection

Complications

What to expect after the procedure?

  • Pain on initial passing of urine
  • Bladder infection ranging from a burning sensation to, fever, to puss (rare)
  • Bloodstained urine
  • Lower abdominal discomfort which will persist for a few days
  • Pain radiating from bladder to renal angle associated with urinating.
  • An infection could present with a stent being present.


Indications for a Ureteric stent

· Hematuria from upper tracts

· Dis-obstruction of the ureter caused either calculus, blood clot or tumour

· External compression of the ureter by retro-peritoneal pathology i.e.: Fibrosis, retroperitoneal lymph node compression

· Reduced renal function associated with hydronephrosis

· Sepsis associated with hydronephrosis


Download Information Sheet

Wes Cystoscopy RGP and Ureteric stents

Copyright 2019 Dr Jo Schoeman

Uretero-Renoscopic Stone Extraction with Laser (URSE)

A ureteric or renal calculus is removed with technique and may require a laser. A rigid/ flexible ureteroscope can be used.

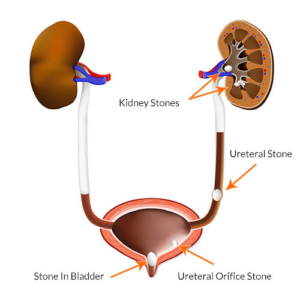
Stones in the kidney, urinary bladder and ureter. medical illustration with a cross section of the kidney and bladder. anatomy of the urinary system. Human kidney.

Why is it done?

  • Removal of renal or ureteric stones.
  • Ureteric stones can vary from 5mm to over 1 cm in size.
  • You may present with excruciating pain on the affected side. (This pain may be worse than childbirth).
  • Renal stones usually larger than 1cm obstructing the renal pelvis.
  • Or renal stones not causing any symptoms.
  • Any fevers or a single kidney is deemed an emergency!

Two Treatment Options

  • Ureteric Calculi.
    • Managed with rigid ureteroscopy.
    • Prior stenting with a ureteric stent,
    • 7-10 days after stenting the stent is removed, and the stone is addressed with laser
  • Renal Calculi.
    • Prior stenting for 7-10 days.
    • After stent removal the kidney is accessed with a flexible uretero-renoscope and the stone is fragmented with laser

How is it done?

    • Patients will receive a general anesthesia.
    • Prophylactic antibiotics is given.
    • The correct kidney is identified and marked while you are awake.
    • You would have had a cystoscopy with retrograde pyelogram 10 days prior with placement of ureteric stent to prepare your ureter.
    • A cystoscopy will be done first to remove the stent, and 2 guidewires will be placed to enable access up the ureter.
    • Depending on the position of the stone, either a rigid or flexible uretero-renoscope will be used.
    • If a stone is in the kidney a flexible uretero-renoscope will be used with access obtained with an access sheath to protect the ureter from damage.
    • Laser will be used to fragment the stone.
    • All fragments will be attempted to be cleared. Small 1-2 mm fragments may be left as “Clinically Insignificant Fragments (CISF)” and will pass spontaneously.
    • A Ureteric catheter with an indwelling catheter is left post-operatively overnight.
    • Catheters will be removed the next morning depending on the presence of blood in the urine.

What next?

  • You will spend at least one night in hospital.
  • You will have a catheter for that time.
  • On removal of your catheter, you may experience sharp colicky pain, exactly the same as your presenting renal colic. This is due to your ureter contracting back to its usual size. (The stent has dilated this to 5X its usual size).
  • You will be discharged as soon as your pain has stabilized and you can function independently.
  • Allow for a few days for stabilization of symptoms.
  • A ward prescription will be issued on your discharge, for your own collection at any pharmacy.
  • A follow-up appointment will be scheduled for 6 weeks. Stone analysis results will then be discussed in order to formulate a plan to proven recurrences
  • DON’T SUFFER IN SILENCE, OR YOU WILL SUFFER ALONE!


Types of Stones:

  • Calcium Oxalate.
  • Uric Acid.
  • Calcium Phosphate.
  • Struvite (Infection stones).
  • Cystine.


Download Information Sheet

Wes Uretero-Renoscopic Stone Extraction with Laser URSE

URSE with or without Laser

Ureteric Injury

Infrequently ureteric injuries can occur with other abdominal surgery i.e.:

  • Hysterectomy.
  • Ovarian mass resection.
  • Bowel resections.
  • Sacro Colpopexy.

If the injury is below the pelvic brim, then a re-implantation with is recommended with Boari-flap, otherwise a primary end-to-end anastomosis

Why is it done?

  • Stricturing or narrowing of the ureter causing significant hydronephrosis.
  • Injury to ureter with Urological surgery can cause this: Ureteroscopy.
  • Injury to the ureter from other surgeries: Colorectal, Gynecological.
  • This injury if not noted may lead to chronic infection, peritonitis, sepsis etc.
  • End-result is loss of renal function and an ICU stay.
  • An end-to-end anastomosis can be considered in the mid ureter.
  • A Reimplantation into the bladder with lower ureteric strictures.
  • A pelvi-ureteric junction repair in higher ureteric strictures.
  • A trans uretero-ureteric anastomosis joining one ureter to the other where long defects are present.
  • Renal Auto Transplantation where ureter is completely damaged or an ileal ureteric substitution where the whole ureter is damaged.

How is it done?

Robotic technique.

  • Patients will receive a general anesthesia.
  • Prophylactic antibiotics is given.
  • The correct ureteric system is identified and marked while you are awake.
  • Robotic ports are placed,
  • The affected ureter is exposed, the defect cut out with a re-anastomosis of a spatulated proximal ureter to the distal ureter over a ureteric stent.
  • An indwelling catheter is placed.
  • A drain is placed.

What next?

  • You may be in hospital for a few days
  • A drain will be left overnight and removed the next day if not draining any fluid.
  • Your catheter will be removed the following day. Or as soon as your urine is clear.
  • As soon as you are comfortable with no signs of pain and emptying your bladder sufficiently, you will be discharged.
  • A ward prescription may be issued on your discharge, for your own collection at any pharmacy.
  • A follow-up appointment will be scheduled for 6 weeks to remove your ureteric stent under local anesthesia with a Flexible Cystoscope.
  • A review with a CT IVP will be scheduled 6 weeks after this to check on the end result of the ureter.
  • DON’T SUFFER IN SILENCE, OR YOU WILL SUFFER ALONE!


Wes Ureteric Injury

Ureteric Reimplantation

  • Surgical repair of VUJ obstruction, robotic or open
  • Mainly a procedure for pediatric urology to correct grade 4-5 vesicoureteral reflux
  • Distal ureteric injuries.

Why is it done?

  • Grade 4-5 Vesical-Ureteric Reflux where conservative management has failed with a progressive deterioration in renal function.
  • Distal ureterectomy due to stricture disease.
  • Iatrogenic injury to lower ureter during surgical procedure: hysterectomy, colectomy, sacrocolpopexy etc.
  • Ureteric involvement in pelvic oncological (cancer) conditions, i.e.: colon cancer, rectal cancer, ovarian cancer, etc.
  • Ureteric involvement in pelvic inflammatory conditions: Diverticular abscesses, Pelvic Inflammatory disease etc.

How is it done?

  • Patients will receive a general anesthesia.
  • Prophylactic antibiotics is given.
  • The correct kidney is identified and marked while you are awake.
  • This will be a combined robotic and endoscopic procedure.
  • A cystoscopy will be done with placement of ureteric catheter or stent, if not already done.
  • Patients with complete closure of the ureter may have a nephrostomy tube into their kidney via the back.
  • An indwelling catheter is placed.
  • Robotic ports are placed, and the pelvic cavity is entered.
  • The ureter is identified, and the affected area of the lower ureter is identified and cut off above the injury / diseased area.
  • The bladder is opened, bi-valved and the ureter is re-implanted either as refluxing or non-refluxing.
  • A Psoas-hitch procedure will be performed where the bladder is fixed onto the affected side’s Psoas muscle as to take off tension from the anastomosis / reimplantation.
  • A Boari-flap may be considered with considerable length of defect.
  • In the case of VUR, the ureter is not cut, rather loosened in the bladder and re-tunneled in a non-refluxing technique under the mucosa of the bladder. Several techniques have been described.
  • A ureteric stent is placed for 6 weeks and an indwelling catheter for 10 days.
  • A drain is also placed for post-operative drainage for a couple of days.

What next?

  • You may be in hospital for at least 3-5 days.
  • You may have continuous intravenous antibiotics on board.
  • You will have a drain and an indwelling catheter.
  • The drain will be removed on D2-3 as soon as the drainage is less than 20-30cc per 24 hours.
  • The indwelling catheter will remain for 10-14 days until a cystogram reveals no leaks.
  • Your stent will be removed on a separate occasion in 6 weeks after all the fibrosis has settled.
  • A follow-up appointment will be scheduled for 6 weeks to remove the stent.
  • A further follow-up is arranged with a CT IVP to check on the end result of the ureter.
  • DON’T SUFFER IN SILENCE, OR YOU WILL SUFFER ALONE!

Possible complications:

  • Vesical Ureteric Reflux.
  • Stricturing / Narrowing of the implanted ureter.
  • Persistent Reflux.
  • Re-implantation.
  • VUR.
  • Stenosis and narrowing with persistent hydronephrosis.


Download Information Sheet

Wes Ureteric Reimplantation VUR