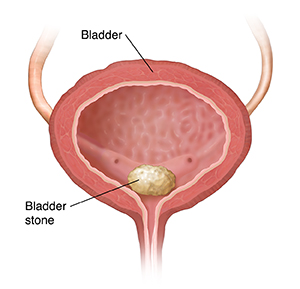
Hydronephrosis and Urinary Stones in Pregnancy What expectant mothers should know about flank pain, infection, premature labour and safe imaging

Pregnancy changes the urinary tract. The kidneys filter more blood, the hormone progesterone relaxes the ureters, and the enlarging uterus can compress them. As a result, the kidney drainage system and ureters often become dilated, a finding called hydronephrosis or hydroureter.

In most women this is a normal, temporary effect of pregnancy. However, hydronephrosis can also be caused by a kidney or ureteric stone, infection or, less commonly, another obstruction. The challenge is deciding whether the dilatation is physiological or whether the kidney is genuinely blocked and needs treatment.

Seek urgent medical assessment for flank pain accompanied by fever, chills, feeling faint or very unwell, persistent vomiting, difficulty passing urine, reduced fetal movement, contractions, vaginal bleeding or fluid loss. An infected, obstructed kidney is a urological emergency.

Why does hydronephrosis occur during pregnancy?

Physiological hydronephrosis usually develops during the second trimester, becomes most marked around 24–28 weeks and is often greater on the right. It results from:

  • progesterone-related relaxation of ureteric smooth muscle;
  • compression of the ureters by the growing uterus at the pelvic brim;
  • rotation of the uterus, which tends to place more pressure on the right ureter; and
  • increased urine production during pregnancy.

This dilatation commonly settles within several weeks after delivery. Physiological hydronephrosis is not itself a stone and does not automatically require a stent or operation.

Features that make pathological obstruction more likely include severe colicky flank pain, blood in the urine, a visible stone, dilatation extending below the pelvic brim, an absent or reduced ureteric jet on the symptomatic side, impaired kidney function, infection or worsening hydronephrosis. No single ultrasound sign is perfect; the symptoms, blood and urine tests, imaging and obstetric assessment must be considered together.

Kidney and ureteric calculi in pregnancy

Urinary calculi are stones located in the kidney or ureter. They are an important cause of non-obstetric abdominal or flank pain during pregnancy and occur most often in the second or third trimester. Typical symptoms include:

  • sudden pain in the loin, flank, abdomen or groin, which may come in waves;
  • nausea and vomiting;
  • visible or microscopic blood in the urine;
  • urinary frequency, urgency or burning; and
  • fever or rigors if infection is present.

Pregnancy increases urinary calcium and urate excretion, while other natural protective factors also rise. For this reason, pregnancy does not necessarily increase the overall number of stones, although the stone pattern may differ and calcium-phosphate stones are relatively more common.

Why infection matters

Pregnancy-related ureteric dilatation and slower urinary drainage encourage urinary stasis. A stone can worsen this by partly or completely blocking the ureter. Bacteria trapped above an obstruction may cause pyelonephritis, pyonephrosis, bacteraemia or sepsis.

All women with suspected renal colic should therefore have urinalysis and a urine culture. Blood tests commonly include a full blood count, kidney function, electrolytes and inflammatory markers. Antibiotics are selected according to pregnancy safety, local resistance patterns and culture results.

Antibiotics alone are not sufficient when infection is trapped behind an obstructed kidney. Urgent decompression with a ureteric stent or percutaneous nephrostomy is required, together with intravenous antibiotics and coordinated obstetric care. Definitive stone treatment is usually delayed until sepsis has resolved.

Is there a risk of premature labour?

Observational studies associate symptomatic stones and renal obstruction in pregnancy with higher rates of urinary infection, hospital admission, preterm contractions and preterm delivery. Severe pain, dehydration, inflammation and infection may all contribute. However, the absolute risk for an individual woman varies, and an association does not mean that every renal colic episode will trigger premature labour.

The condition requiring intervention may itself be responsible for some of the reported risk. For this reason, treatment decisions should not be based on procedure statistics alone. The balance is between allowing a stable stone time to pass and promptly treating uncontrolled pain, infection or threatened kidney function. Depending on gestational age and clinical circumstances, fetal monitoring and assessment for contractions may be appropriate.

How is it investigated?

1. Ultrasound first

Renal and bladder ultrasound is the preferred first-line test because it uses sound waves rather than ionising radiation. It can show hydronephrosis, some kidney or ureteric stones, ureteric jets and alternative diagnoses. Transvaginal ultrasound may help identify a distal ureteric stone.

Ultrasound has limitations: physiological hydronephrosis can resemble obstruction, and a small ureteric stone may not be visible. A normal or inconclusive scan does not always exclude a stone.

2. MRI or MR urography when uncertainty remains

MRI without gadolinium can identify the level and pattern of obstruction without ionising radiation. Stones usually appear as signal voids rather than being seen as clearly as on CT. MRI is therefore a useful second-line test, particularly when ultrasound is inconclusive and the patient is clinically stable. Gadolinium contrast is not routinely used during pregnancy.

3. Low-dose non-contrast CT only when clinically necessary

Low-dose CT is the most accurate test for a urinary stone, but it uses ionising radiation. European Association of Urology guidance places low-dose CT as a last-line option in pregnancy, after ultrasound and usually MRI, when diagnostic uncertainty could change urgent management.

The practical radiation principles are:

  • use imaging only when it will answer an important clinical question;
  • prefer ultrasound, followed by MRI without contrast, when suitable;
  • if CT is necessary, use a pregnancy-adapted low-dose protocol and limit the scanned area;
  • avoid repeated or multiphase CT examinations unless clearly justified; and
  • involve an experienced radiologist and document the risk–benefit discussion.

Diagnostic imaging should not be withheld when delay or uncertainty poses a greater risk to the mother or baby. The EAU notes that deterministic fetal effects require substantially higher exposure than most diagnostic studies and considers doses below 50 mGy safe in this context; nevertheless, any ionising-radiation examination must be justified and kept as low as reasonably achievable. Ultrasound and MRI do not use ionising radiation.

Management options

Treatment is individualised by symptoms, infection status, stone size and location, kidney function, gestational age, obstetric factors and local expertise. Close collaboration between urology, obstetrics, radiology, anaesthesia and neonatology may be needed.

Conservative management

Most uncomplicated cases are initially managed without surgery. This may include:

  • oral or intravenous fluids sufficient to correct dehydration, forced overhydration does not “flush out” a stone;
  • anti-nausea medication;
  • analgesia suitable for the stage of pregnancy;
  • urine culture and pregnancy-compatible antibiotics when infection is confirmed; and
  • follow-up to ensure symptoms resolve and kidney drainage and function remain satisfactory.

Paracetamol is commonly used first-line. Opioids may be used for severe pain under medical supervision. Non-steroidal anti-inflammatory drugs such as ibuprofen and diclofenac should not be self-administered in pregnancy; their fetal renal, amniotic-fluid and ductus arteriosus risks depend on gestation, dose and duration. The evidence for medical expulsive therapy with alpha-blockers during pregnancy is limited, and such treatment should only be considered after specialist discussion.

Conservative treatment is unsuitable when there is sepsis, deteriorating kidney function, a solitary obstructed kidney, bilateral obstruction, persistent vomiting, uncontrolled pain, severe or progressive hydronephrosis, renal forniceal rupture, threatened premature labour or failure of the stone to pass with ongoing clinically important obstruction.

Ureteric stent

A JJ stent bypasses the obstruction and drains urine from the kidney to the bladder. It can be inserted with minimal or no fluoroscopy, using ultrasound guidance where appropriate. Stents can cause urinary frequency, urgency, discomfort, blood in the urine, infection and encrustation. Encrustation develops faster in pregnancy, so regular review and sometimes exchange every 4–6 weeks are required. A stent must not be forgotten after delivery.

Percutaneous nephrostomy

A nephrostomy tube drains the kidney through the back and can often be placed with ultrasound guidance. It is particularly useful when retrograde stenting is not possible or when urgent drainage is required in selected circumstances. Disadvantages include an external bag, discomfort, blockage, displacement, infection and rapid encrustation, with possible repeat exchanges.

Ureteroscopy and laser treatment

Ureteroscopy allows a surgeon to pass a fine telescope through the bladder into the ureter, remove the stone or fragment it with a laser, often without fluoroscopy. It provides definitive treatment and avoids prolonged drainage in selected patients. If a non-urgent procedure is required, the second trimester is generally preferred, and it should be performed by an experienced team with obstetric and neonatal support available. Ureteroscopy is not the first step in an untreated septic obstruction; drainage and infection control come first.

Treatments generally avoided

Shock-wave lithotripsy is contraindicated during pregnancy. Percutaneous stone removal is rarely required and is reserved for carefully selected cases in highly experienced centres. Routine definitive treatment can often wait until after delivery when symptoms and kidney function permit.

After delivery

Follow-up should confirm that hydronephrosis has resolved, any stent or nephrostomy has been removed, the stone has passed or been treated, and kidney function is normal. A retrieved stone should be analysed. Women with recurrent stones, a strong family history, infection stones or other risk factors may benefit from a metabolic evaluation after pregnancy, when physiology and diet have stabilised.

The important message

Most hydronephrosis in pregnancy is physiological, and many stones pass with careful conservative management. The dangerous combination is obstruction plus infection. Fever, rigors or systemic illness with flank pain requires urgent assessment because prompt antibiotics and drainage can protect the mother, kidney and pregnancy. Imaging should follow a stepwise approach, ultrasound first, MRI second and low-dose CT only when the clinical benefit justifies it.


References

  1. European Association of Urology. EAU Guidelines on Urolithiasis: Diagnostic imaging during pregnancy; management of urinary stones during pregnancy. Current online guideline. https://uroweb.org/guidelines/urolithiasis/chapter/guidelines
  2. Lee MS, Fenstermaker MA, Naoum EE, et al. Management of nephrolithiasis in pregnancy: multi-disciplinary guidelines from an academic medical center. Front Surg. 2021;8:796876. https://doi.org/10.3389/fsurg.2021.796876
  3. Chan K, Shakir T, El-Taji O, et al. Management of urolithiasis in pregnancy. Curr Urol. 2023;17(1):1–6. https://doi.org/10.1097/CU9.0000000000000181
  4. American College of Obstetricians and Gynecologists. Guidelines for diagnostic imaging during pregnancy and lactation. Committee Opinion No. 723. Obstet Gynecol. 2017;130–e216. https://www.acog.org/clinical/clinical-guidance/committee-opinion/articles/2017/10/guidelines-for-diagnostic-imaging-during-pregnancy-and-lactation
  5. Drescher M, Blackwell RH, Patel PM, et al. Antepartum nephrolithiasis and the risk of preterm delivery. Urolithiasis. 2019;47:441–448. https://doi.org/10.1007/s00240-018-1085-3

This information is general education and does not replace individual medical or obstetric advice. Medication and imaging decisions in pregnancy should be made with the treating obstetric, urology and radiology teams.

Conservative Management of a Distal Ureteric Stone: When Can You Wait and When Is Surgery Needed?

A distal ureteric calculus is a stone located in the lower part of the ureter—the tube carrying urine from the kidney to the bladder. These stones are often close to the ureterovesical junction, where the ureter enters the bladder.

As the stone moves towards the bladder, it can cause severe intermittent pain known as renal colic. Pain commonly begins in the side or back and travels into the lower abdomen, groin, testicle or labia. Blood in the urine, nausea, vomiting, urinary urgency and frequency may also occur.

Many small distal ureteric stones pass naturally. However, conservative management is only safe when pain is controlled, infection is absent, kidney function is satisfactory and appropriate follow-up is arranged.

When is a ureteric stone an emergency?

A stone obstructing an infected kidney is a urological emergency. Antibiotics alone may be insufficient because infected urine cannot drain normally.

Seek urgent medical assessment if stone symptoms are accompanied by:

  • Fever or shaking chills
  • Feeling severely unwell, weak, confused or drowsy
  • Persistent vomiting or inability to drink
  • Pain that remains severe despite medication
  • Passing very little or no urine
  • Known poor kidney function
  • A solitary functioning kidney
  • Pregnancy with significant pain or fever

The obstructed kidney may need urgent drainage with a ureteric stent or nephrostomy tube. Definitive stone treatment is usually delayed until the infection has been controlled. The European Association of Urology recommends immediate antibiotics and urgent drainage for sepsis associated with an obstructing stone. EAU Guidelines on Urolithiasis

Australian Healthdirect similarly advises patients with renal colic and fever to attend a doctor or hospital emergency department promptly. Healthdirect Australia—Kidney stones

What determines whether a stone will pass naturally?

The likelihood of spontaneous passage depends mainly on:

  • Stone size
  • Position within the ureter
  • Degree of obstruction
  • Ureteric anatomy
  • Whether the stone is impacted
  • Previous stone history
  • Associated swelling and inflammation
  • The duration for which the stone has remained in the same position

Smaller stones located close to the bladder have the greatest likelihood of passing.

The EAU reports that distal ureteric stones collectively have a spontaneous passage rate of approximately 68–83%. A distal ureteric stone smaller than 5 mm has an estimated passage rate of approximately 89%. The likelihood decreases as stone size increases.

These percentages describe groups of patients and cannot predict exactly what will happen to an individual stone. A 4 mm stone may occasionally become impacted, while a larger stone may sometimes pass without surgery.

The average reported passage time is approximately 17 days, although passage can occur sooner or take several weeks. EAU Guidelines on Urolithiasis

Who may be suitable for conservative management?

Conservative management, also called observation, expectant management or a trial of passage, may be appropriate when:

  • The stone is small enough to have a reasonable chance of passing
  • The stone is in the distal ureter
  • Pain can be controlled with oral medication
  • There is no fever or evidence of urinary infection
  • Kidney function is stable
  • The patient can drink and keep medication down
  • There is no complete obstruction threatening kidney function
  • The patient is passing urine normally
  • There is no high-risk situation involving a solitary kidney or bilateral obstruction
  • The patient understands the warning symptoms
  • Follow-up and repeat imaging can be arranged
  • The patient is comfortable waiting for the stone to pass

Stones of 5 mm or less are particularly suitable for observation when no complications are present.

Selected distal stones between 5 and 10 mm may also be managed conservatively. These stones are less likely to pass than smaller stones, but some patients may avoid surgery with careful observation and medical expulsive therapy.

Stones larger than 10 mm are substantially less likely to pass naturally and are more commonly treated with an intervention.

What assessment is required?

Before recommending conservative management, the diagnosis and severity of obstruction should be established.

Assessment may include:

  • A detailed history and physical examination
  • Urine dipstick testing
  • Urine culture when infection is suspected
  • Kidney-function blood tests
  • Full blood count and inflammatory markers
  • Non-contrast CT scan of the kidneys, ureters and bladder
  • Ultrasound in selected patients
  • A plain abdominal X-ray when the stone is visible on X-ray
  • Pregnancy testing when clinically relevant

A low-dose non-contrast CT scan is often the most accurate test for determining the stone’s size and location. It can also assess hydronephrosis, the swelling of the kidney caused by obstruction and identify alternative causes of pain.

Ultrasound is particularly useful when radiation should be avoided, including during pregnancy, although it may not show every ureteric stone.

What does conservative management involve?

Pain relief

Non-steroidal anti-inflammatory medicines, NSAIDs, are often the most effective initial treatment for renal colic when they are medically safe.

Depending on the patient, treatment may include:

  • Ibuprofen
  • Diclofenac
  • Paracetamol
  • A prescribed opioid for breakthrough pain
  • Medication for nausea or vomiting

NSAIDs may be unsuitable for people with:

  • Reduced kidney function
  • Previous stomach ulcers or gastrointestinal bleeding
  • Certain cardiovascular conditions
  • Anticoagulant treatment
  • NSAID allergy
  • Some stages of pregnancy

Pain medication should be selected according to the patient’s medical history rather than taken indiscriminately.

Hydration

Patients should generally remain normally hydrated and avoid becoming dehydrated.

Drinking excessive volumes of water during an episode of acute obstruction does not necessarily force the stone through and may increase discomfort. The aim is steady, sensible fluid intake unless a doctor has advised otherwise.

Straining the urine

Passing urine through a stone strainer can help recover the calculus. A captured stone can be sent for laboratory analysis, which may guide future prevention.

Pain disappearing does not always prove that the stone has passed. Occasionally a stone stops causing pain while obstruction remains, so follow-up imaging may still be required.

Activity

Normal gentle activity is usually reasonable if the patient feels well. Some patients find walking helpful, although exercise cannot guarantee stone passage.

Driving, remote travel and hazardous work may be unsafe while unpredictable severe pain or medication-related drowsiness remains possible.

Medical expulsive therapy

Medical expulsive therapy—usually abbreviated to MET, uses medication to help a ureteric stone pass.

The most frequently used medicines are alpha-blockers, including:

  • Tamsulosin
  • Silodosin
  • Alfuzosin

Tamsulosin is commonly selected because it is widely available and familiar to urologists.

Alpha-blockers are primarily used to improve urinary symptoms caused by prostate enlargement. Their use for ureteric stone passage is generally off-label, meaning that stone passage is not necessarily the indication listed in the medicine’s formal registration.

Off-label use does not mean that treatment is experimental or prohibited. It means that the potential benefits, limitations and side effects should be discussed before prescribing it.

How do alpha-blockers affect the distal ureter?

The ureter contains smooth muscle and alpha-adrenergic receptors. These receptors are particularly relevant in the distal ureter.

When a stone enters the ureter, the surrounding muscle can contract and spasm. Swelling may develop around the stone, increasing resistance to its movement.

Alpha-blockers may:

  • Relax distal ureteric smooth muscle
  • Reduce ureteric spasm
  • Reduce pressure below and around the stone
  • Increase the ureter’s ability to accommodate the calculus
  • Improve the likelihood of stone passage
  • Shorten passage time in some patients
  • Reduce episodes of renal colic and analgesic requirements in selected cases

An alpha-blocker does not:

  • Dissolve most stones
  • Make the stone physically smaller
  • Treat a urinary infection
  • Remove a completely impacted stone
  • Protect a kidney from prolonged significant obstruction
  • Replace drainage of an infected obstructed kidney

How effective are alpha-blockers?

Research into alpha-blockers has produced mixed results.

When all ureteric stones are grouped together, some large studies have shown little or no overall benefit. This may be because very small stones frequently pass without medication and very large or impacted stones remain unlikely to pass despite treatment.

The clearest benefit appears to be in patients with distal ureteric stones between approximately 5 and 10 mm.

The EAU recommends offering an alpha-blocker as one treatment option for conservatively managed distal ureteric stones in this size range, while explaining that treatment is off-label. EAU Guidelines on Urolithiasis

For a stone smaller than 5 mm, the natural passage rate is already high, so an alpha-blocker may add relatively little benefit. Treatment decisions should therefore be individualised.

Side effects and precautions with alpha-blockers

Possible side effects include:

  • Dizziness
  • Light-headedness on standing
  • Low blood pressure
  • Weakness or fatigue
  • Headache
  • Nasal congestion
  • Palpitations
  • Reduced semen volume
  • Failure of ejaculation or retrograde ejaculation

Extra caution is required in patients who:

  • Already have low blood pressure
  • Have a history of fainting or falls
  • Take several blood-pressure medicines
  • Use medication for erectile dysfunction
  • Have significant cardiovascular disease
  • Are planning cataract or glaucoma surgery

Tamsulosin has been associated with intraoperative floppy iris syndrome during cataract surgery. Patients should tell their ophthalmologist about current or previous use.

Alpha-blocker treatment should be stopped and medical advice obtained if infection, uncontrollable pain or deterioration in kidney function develops.

How long can conservative management continue?

There is no single safe waiting period for every patient. The decision depends on symptoms, obstruction, kidney function, stone movement and the likelihood of passage.

Many stones that pass naturally do so within two to four weeks. A monitored trial of passage may sometimes continue for up to approximately four to six weeks, provided that:

  • Pain remains manageable
  • Infection does not develop
  • Kidney function remains stable
  • Obstruction is not causing progressive harm
  • Follow-up imaging is performed
  • The patient still prefers conservative treatment

Observation should not become open-ended. A painless obstructing stone can still impair kidney function.

Follow-up may involve an X-ray, ultrasound or low-dose CT scan. The most suitable test depends on whether the stone was visible on the original X-ray and whether ongoing obstruction needs to be assessed.

When has conservative management failed?

Conservative management should be reconsidered when:

  • The stone has not passed within an appropriate observation period
  • Repeat imaging shows that the stone has not moved
  • Pain remains severe despite adequate medication
  • Repeated emergency presentations are required
  • Nausea or vomiting prevents oral fluids or medication
  • Fever or urinary infection develops
  • Kidney function deteriorates
  • Hydronephrosis persists or worsens
  • Urine output falls significantly
  • The stone has a low likelihood of spontaneous passage
  • The patient has a solitary kidney or bilateral obstruction
  • The patient cannot safely continue waiting
  • Work, caring responsibilities or travel make unpredictable colic unacceptable
  • The patient prefers definitive removal

The EAU identifies persistent pain, persistent obstruction, impaired kidney function and a low likelihood of spontaneous passage as indications for active stone removal. EAU Guidelines on Urolithiasis

Failure of conservative management is not a personal failure. It usually means that the stone is too large, impacted, anatomically trapped or producing complications that make further waiting unsafe.

Surgical and procedural treatment

The two main definitive treatments for a distal ureteric calculus are:

  • Ureteroscopy with laser lithotripsy or stone extraction
  • Shock wave lithotripsy

The most appropriate option depends on stone size, density and position, as well as the patient’s anatomy, medical health, preferences and treatment availability.

Ureteroscopy and laser lithotripsy

Ureteroscopy is commonly used for distal ureteric stones and generally provides the best chance of becoming stone-free after one procedure.

Under anaesthesia, a small telescope is passed through:

  1. The urethra
  2. The bladder
  3. The opening of the ureter
  4. The ureter to the level of the stone

The stone may be removed intact with a small basket or fragmented using a holmium or thulium laser. The pieces are then extracted or allowed to pass naturally.

No external incision is usually required.

Is a ureteric stent required?

A temporary ureteric stent may be inserted when:

  • The ureter is swollen
  • Access was difficult
  • Infection is a concern
  • Stone fragments remain
  • There was ureteric trauma
  • Reliable drainage is required
  • Kidney function is vulnerable

A stent extends from the kidney to the bladder. It can cause:

  • Urinary frequency and urgency
  • Bladder discomfort
  • Pain in the kidney during urination
  • Blood in the urine
  • Discomfort during activity
  • A sensation of incomplete emptying

Stents must be removed or exchanged at the planned time. A forgotten stent can become encrusted and cause serious complications.

Risks of ureteroscopy

Possible complications include:

  • Urinary infection or sepsis
  • Bleeding
  • Failure to reach or remove the stone
  • Residual fragments
  • Ureteric perforation
  • Ureteric narrowing or stricture
  • Need for a further procedure
  • Anaesthetic complications

Major ureteric injury is uncommon but can require additional surgery.

Compared with shock wave treatment, ureteroscopy generally offers a higher chance of clearing the stone in one procedure, although it is more invasive and has a higher complication rate. EAU Guidelines on Urolithiasis

Shock wave lithotripsy

Shock wave lithotripsy, SWL or ESWL, uses externally generated shock waves focused onto the stone. These waves fragment the calculus into smaller pieces that can pass down the ureter.

Advantages may include:

  • No telescope passing up the ureter
  • No surgical incision
  • Lower procedural morbidity
  • Day-treatment suitability in many patients

Limitations include:

  • Lower single-treatment stone-free rates than ureteroscopy
  • Possible need for repeat treatment
  • Pain while fragments pass
  • Residual fragments
  • Difficulty targeting some distal stones
  • Reduced success with dense or impacted stones
  • Reduced effectiveness with greater skin-to-stone distance
  • Possible need for subsequent ureteroscopy

SWL may not be suitable during pregnancy, with untreated infection, uncorrected bleeding disorders, an aneurysm near the treatment field or an anatomical obstruction below the stone.

The American Urological Association recognises both ureteroscopy and shock wave lithotripsy as options when active treatment is required for a distal ureteric stone. AUA Surgical Management of Kidney and Ureteral Stones Guideline

Emergency drainage with a ureteric stent

A ureteric stent may be inserted urgently to bypass an obstructing stone and allow urine to drain from the kidney.

This is particularly important when there is:

  • Infection or sepsis
  • Deteriorating kidney function
  • A solitary obstructed kidney
  • Bilateral obstruction
  • Uncontrollable pain
  • Severe obstruction where immediate stone removal is unsuitable

Emergency stenting relieves the obstruction but does not always remove the stone. Definitive ureteroscopy or SWL may be scheduled later.

Percutaneous nephrostomy

A nephrostomy tube is inserted through the skin of the back directly into the kidney under imaging guidance.

It may be used when:

  • Rapid drainage of an infected kidney is required
  • A ureteric stent cannot be inserted
  • The patient is too unwell for a longer procedure
  • Ureteric anatomy prevents retrograde access

Both ureteric stenting and nephrostomy provide effective emergency drainage. The choice depends on clinical circumstances, local expertise and the patient’s condition.

Open, laparoscopic or robotic stone removal

Open or keyhole ureterolithotomy is now rarely required for an isolated distal ureteric stone.

It may occasionally be considered for:

  • A very large impacted stone
  • Unusual urinary anatomy
  • Failure of less invasive treatments
  • A stone requiring treatment during another planned reconstruction

Most distal stones can be treated successfully with ureteroscopy or SWL.

Which treatment is best?

There is no single procedure that is best for every patient.

Ureteroscopy may be preferred when:

  • Rapid and reliable stone clearance is important
  • The stone is impacted
  • The stone is dense or unlikely to fragment with SWL
  • Previous SWL has failed
  • The patient has significant obesity
  • The stone is difficult to target externally
  • The patient wishes to minimise the likelihood of repeat treatment

SWL may be preferred when:

  • The stone can be targeted clearly
  • The stone has favourable size and density
  • The patient wishes to avoid ureteroscopy
  • Anaesthetic considerations favour a less invasive approach
  • The patient accepts the possibility of repeat treatment

The decision should include a discussion of success rates, anaesthesia, stent requirements, recovery, complications and the possible need for another procedure.

Preventing another stone

Once the acute episode has resolved, prevention becomes important.

General measures may include:

  • Drinking enough fluid to produce at least 2–2.5 litres of urine daily, unless medically restricted
  • Reducing excessive salt intake
  • Maintaining normal dietary calcium rather than eliminating calcium
  • Moderating excessive animal-protein intake
  • Maintaining a healthy body weight
  • Avoiding recurrent dehydration
  • Capturing the stone for analysis
  • Completing blood and urine testing when indicated

Patients with recurrent stones, a solitary kidney, childhood stone disease, unusual stone types or a strong family history may require a formal metabolic evaluation, including 24-hour urine testing.

Prevention should be tailored to the stone composition and the patient’s metabolic risk factors.

The bottom line

Many small distal ureteric stones can be managed safely without surgery. Stones smaller than 5 mm near the bladder have the greatest likelihood of passing naturally.

Conservative treatment usually involves appropriate pain relief, sensible hydration, urine straining, follow-up imaging and—in selected patients—an alpha-blocker such as tamsulosin.

Alpha-blockers relax the smooth muscle of the distal ureter. Their greatest likely benefit is for distal stones between approximately 5 and 10 mm. They do not dissolve the stone and should not delay treatment when infection, uncontrolled pain, persistent obstruction or declining kidney function develops.

Ureteroscopy with laser treatment provides the most reliable single-procedure clearance for many distal stones. Shock wave lithotripsy is less invasive but may require repeat treatment. An infected obstructed kidney requires urgent drainage rather than continued observation.

This article provides general information and does not replace individual medical assessment. Anyone with renal colic and fever, inability to pass urine, persistent vomiting or uncontrollable pain should seek urgent medical care.

Need help deciding whether your ureteric stone can safely pass?

If you have been diagnosed with a distal ureteric calculus, appropriate management depends on more than its size alone. Stone position, pain, infection, kidney function and the degree of obstruction must all be considered.

Your local Brisbane urologist, Dr Jo Schoeman, can assess whether observation, medical expulsive therapy, ureteroscopy or shock wave treatment is the most appropriate option for you.

References and further reading

Kidney Stones: Understanding the Different Types of Renal Calculi and Their Treatment

Kidney stones, medically known as renal calculi or nephrolithiasis, are solid crystalline deposits that develop within the kidneys. Although we tend to talk about “a kidney stone” as if all stones are the same, there are several distinctly different types.

Knowing the composition of a kidney stone matters. Different stones have different causes, appearances, recurrence risks and, importantly, different strategies for prevention and treatment.

Modern management therefore involves more than simply removing the stone. The aim is to answer three questions:

What is the stone? Why did it form? And how can we prevent the next one?


What Are Kidney Stones Made Of?

The major types of urinary stones are:

  1. Calcium oxalate stones
  2. Calcium phosphate stones
  3. Uric acid stones
  4. Struvite or infection stones
  5. Cystine stones
  6. Rare metabolic and medication-related stones

Stones are not always chemically pure. Many contain a mixture of different crystalline components.

The European Association of Urology recommends reliable stone analysis and a basic metabolic evaluation in stone-forming patients, with more detailed metabolic investigation particularly important in patients at high risk of recurrence.


1. Calcium Oxalate Stones

The most common kidney stone

Calcium oxalate stones are the most frequently encountered urinary calculi.

They may consist predominantly of:

  • Calcium oxalate monohydrate, known as whewellite
  • Calcium oxalate dihydrate, known as weddellite

Calcium oxalate monohydrate stones can be particularly hard and resistant to fragmentation with shockwave lithotripsy.

Why do calcium oxalate stones form?

Contributing factors may include:

  • Low urine volume or dehydration
  • Excess urinary calcium
  • Excess urinary oxalate
  • Low urinary citrate
  • High dietary sodium intake
  • Excessive animal protein intake
  • Certain bowel diseases or previous intestinal surgery
  • Genetic predisposition
  • Metabolic abnormalities

Importantly, calcium stones do not necessarily mean that a patient is eating too much calcium.

Severely restricting normal dietary calcium can actually be counterproductive because calcium within the intestine binds oxalate and reduces its absorption.

Management

Small asymptomatic stones may sometimes simply be monitored.

When treatment is required, options include:

  • Shockwave lithotripsy (SWL)
  • Flexible ureteroscopy and laser lithotripsy
  • Percutaneous nephrolithotomy (PCNL)
  • Observation in appropriately selected patients

Prevention depends on the underlying metabolic abnormality and may include increased fluid intake, dietary modification, reduction in excessive sodium intake, potassium citrate for selected patients, thiazide therapy for hypercalciuria and treatment of hyperoxaluria or hyperuricosuria when identified.


2. Calcium Phosphate Stones

Calcium phosphate stones are less common than calcium oxalate stones.

They may contain:

  • Hydroxyapatite
  • Carbonate apatite
  • Brushite

Why do they form?

Calcium phosphate crystallisation is favoured by relatively alkaline urine.

They may be associated with:

  • Hypercalciuria
  • Renal tubular acidosis
  • Hyperparathyroidism
  • Urinary tract abnormalities
  • Certain metabolic disorders

Brushite stones deserve particular attention. They can be extremely hard and may respond poorly to shockwave treatment.

Management therefore needs to consider not only stone size and location, but also stone density and previous stone composition.


3. Uric Acid Stones

Uric acid stones behave very differently from calcium stones.

They are strongly associated with persistently acidic urine and may occur in patients with:

  • Gout
  • Metabolic syndrome
  • Diabetes
  • Obesity
  • High purine intake
  • High animal-protein intake
  • Chronic dehydration
  • Excessive uric acid production or excretion

Uric acid stones account for approximately 10% of renal stones and all uric acid stone formers are considered at increased risk of recurrence.

Why are uric acid stones special?

Because unlike most kidney stones, uric acid stones can potentially be dissolved.

Treatment involves increasing urinary pH, usually using an alkalinising medication such as potassium citrate.

For active oral dissolution therapy, urinary pH needs to be carefully monitored. Current EAU guidance describes targeting approximately pH 7.0–7.2 during chemolysis, while avoiding excessive alkalinisation because this may encourage calcium phosphate crystallisation.

This creates one of the happier conversations in stone management:

“You have a kidney stone, but we may be able to make it disappear without an operation.”

Not every uric acid stone will dissolve successfully, and obstructed or infected kidneys require separate and sometimes urgent treatment.


4. Struvite Stones: The Infection Stones

Struvite stones contain magnesium ammonium phosphate and are closely associated with urinary infections caused by certain urease-producing bacteria.

These bacteria change the chemistry of the urine, producing an alkaline environment favourable for rapid stone formation.

Struvite stones can become very large and occasionally form a branching staghorn calculus, occupying much of the kidney’s collecting system.

Why are these stones important?

The stone and infection can maintain one another.

Leaving significant infected stone material behind may therefore contribute to:

  • Recurrent urinary infection
  • Rapid stone regrowth
  • Kidney damage
  • Sepsis

Management generally involves treating the infection and achieving as complete a stone clearance as reasonably possible. Large stones frequently require PCNL, sometimes performed in more than one stage.

Infection stone formers are regarded as being at high risk of recurrence.


5. Cystine Stones

Cystine stones are uncommon and are caused by cystinuria, an inherited disorder affecting the transport of certain amino acids through the kidneys.

Cystine is relatively insoluble in urine and can crystallise to form stones.

These patients may start developing stones at a young age and can experience repeated stone episodes throughout life.

Treatment and prevention

Prevention is particularly important and may involve:

  • Very high fluid intake
  • Reduced dietary sodium
  • Urinary alkalinisation
  • Potassium citrate
  • Specialist medication such as tiopronin in selected recurrent cases

Current EAU guidance recommends aiming for a urine volume greater than 3 litres per day in adults with cystinuria and maintaining urinary pH above approximately 7.5 to improve cystine solubility.

Cystine stones are also relatively hard, which can make shockwave treatment less successful. Ureteroscopy with laser treatment or PCNL may therefore be required depending on stone burden.


6. Rare Kidney Stones

Much less commonly, stones may consist of substances such as:

  • Xanthine
  • 2,8-dihydroxyadenine
  • Ammonium urate
  • Matrix material
  • Medication-related crystalline material

These stones can sometimes provide the first clue to an underlying metabolic, genetic or medication-related disorder.

Recurrent unusual stones therefore deserve specialist investigation rather than simply repeated stone removal.


How Do Kidney Stones Present?

Some kidney stones sit quietly within the kidney and are discovered incidentally during an ultrasound or CT scan.

Others announce their arrival with considerably less subtlety.

A stone entering and obstructing the ureter may cause renal colic, producing severe pain from the loin toward the abdomen or groin.

Other symptoms can include:

  • Blood in the urine
  • Nausea and vomiting
  • Urinary urgency or frequency
  • Burning during urination
  • Recurrent urinary infection
  • Fever or chills
  • Intermittent loin discomfort

Fever plus an obstructed kidney is an emergency

An infected obstructed urinary system can progress rapidly to urosepsis.

Urgent drainage with a ureteric stent or nephrostomy tube, together with appropriate antibiotics and supportive treatment, may be required. Definitive stone treatment is generally delayed until the infection has been controlled.


How Are Kidney Stones Investigated?

CT Scan

A non-contrast CT scan of the kidneys, ureters and bladder provides detailed information regarding:

  • Stone size
  • Number of stones
  • Exact location
  • Degree of obstruction
  • Kidney anatomy
  • Stone density measured in Hounsfield units

CT density may also provide clues about stone composition and the likelihood of successful shockwave fragmentation.

Ultrasound

Ultrasound avoids radiation and is particularly useful for:

  • Surveillance
  • Detecting hydronephrosis
  • Monitoring known renal stones
  • Selected younger patients
  • Pregnancy

However, very small stones and ureteric stones can sometimes be difficult to identify accurately.

Plain X-ray

A KUB X-ray may be useful for monitoring certain radiopaque stones.

Calcium-containing stones are usually radiopaque, whereas uric acid stones are typically radiolucent on plain X-ray.


Do All Kidney Stones Need Treatment?

No.

A small, non-obstructing and asymptomatic kidney stone may sometimes be monitored with periodic imaging.

Treatment becomes more appropriate when there is:

  • Stone growth
  • Recurrent pain
  • Haematuria
  • Urinary obstruction
  • Recurrent infection
  • Declining renal function
  • Significant stone burden
  • High risk of future complications
  • Occupational or travel considerations
  • Patient preference

These factors are reflected in contemporary EAU recommendations.


Treatment Options for Kidney Stones

1. Active Surveillance

Small asymptomatic renal stones can sometimes be observed.

Follow-up may include ultrasound, X-ray or CT depending on the type, size and visibility of the stone.

The advantage is obvious: no procedure unless one becomes necessary.

The disadvantage is equally obvious: stones have not signed a contract promising to remain where they are.

They may enlarge, migrate into the ureter, cause obstruction or become symptomatic.


2. Shockwave Lithotripsy

Extracorporeal shockwave lithotripsy (SWL) uses externally generated shockwaves focused onto the stone.

The aim is to fragment the calculus into smaller pieces that can subsequently pass through the urinary tract.

Advantages

  • Non-invasive
  • Usually rapid recovery
  • No incision
  • Useful for appropriately selected renal stones

Limitations

Success depends on:

  • Stone size
  • Location
  • Density
  • Composition
  • Skin-to-stone distance
  • Renal anatomy

Hard stones such as calcium oxalate monohydrate, brushite and cystine stones may be less responsive.

More than one treatment session may be required.


3. Flexible Ureteroscopy and Laser Lithotripsy

A fine flexible telescope is passed through the urethra and bladder, up the ureter and into the kidney.

There are no external incisions.

The stone can then be fragmented or dusted using a laser, with larger fragments removed using tiny retrieval baskets.

Advantages

  • Minimally invasive
  • High stone clearance rates for appropriately selected stones
  • Can treat stones resistant to shockwave therapy
  • Allows direct visualisation
  • Suitable for many locations within the kidney

Possible disadvantages

  • Requires anaesthesia
  • Temporary ureteric stenting may be required
  • Stent discomfort
  • Bleeding or infection
  • Ureteric injury is uncommon but possible
  • Occasionally a second procedure is required

4. Percutaneous Nephrolithotomy

PCNL involves creating a small tract through the skin directly into the kidney.

It is particularly useful for:

  • Large renal calculi
  • Staghorn stones
  • Complex stones
  • Large-volume infection stones
  • Stones unlikely to respond adequately to less invasive techniques

Current EAU guidance recommends PCNL as the first-line treatment for renal stones larger than 2 cm in most suitable patients.

PCNL generally provides excellent clearance of large stone burdens but is more invasive than ureteroscopy or shockwave treatment.

Potential complications include bleeding, infection, injury to surrounding structures and the need for additional procedures.


5. Dissolution Therapy

This option is mainly relevant to uric acid stones.

Urinary alkalinisation can gradually dissolve the stone, potentially avoiding surgery.

Treatment requires:

  • Correct identification or strong suspicion of uric acid composition
  • Regular urine pH monitoring
  • Appropriate alkalinising medication
  • Follow-up imaging
  • Patient compliance

It is important not to assume that every radiolucent stone is uric acid, and treatment should be supervised appropriately.


Choosing the Right Treatment

There is no single “best” kidney stone operation.

The appropriate treatment depends on a combination of:

Stone factors

  • Size
  • Number
  • Location
  • Composition
  • Density
  • Previous growth

Kidney factors

  • Anatomy
  • Obstruction
  • Infection
  • Renal function

Patient factors

  • Symptoms
  • Medical conditions
  • Anticoagulant therapy
  • Previous stone procedures
  • Occupation
  • Travel requirements
  • Personal preference

Two patients with apparently similar 10 mm stones may therefore receive quite different recommendations.


Preventing the Next Kidney Stone

Removing a stone solves today’s problem.

Preventing another stone solves tomorrow’s problem.

Patients with recurrent stones, multiple stones, bilateral stones, unusual stone composition, young age at presentation or other high-risk features may benefit from metabolic investigation.

This may include blood testing and 24-hour urine collections assessing factors such as:

  • Urine volume
  • Calcium
  • Oxalate
  • Citrate
  • Uric acid
  • Sodium
  • Magnesium
  • Urinary pH

Stone analysis is particularly valuable whenever a stone can be retrieved. Current EAU guidance recommends reliable stone analysis and basic metabolic evaluation for stone formers, with specific metabolic assessment for high-risk patients.


General Kidney Stone Prevention

Although prevention should ultimately be tailored to stone composition, several principles apply to many stone formers.

Drink more water

Maintaining generous urine output dilutes the substances responsible for crystal formation.

Water remains wonderfully unexciting and remarkably effective.

Reduce excessive salt intake

High sodium intake can increase urinary calcium excretion and contribute to calcium stone formation.

Maintain normal dietary calcium

Patients with calcium stones should not automatically eliminate calcium-containing foods.

A balanced dietary calcium intake may actually reduce intestinal oxalate absorption.

Moderate excessive animal protein

Large amounts of meat and other purine-rich foods may contribute to increased urinary uric acid and more acidic urine in susceptible individuals.

Maintain a healthy weight

Obesity and metabolic syndrome are particularly associated with uric acid stone formation.

Investigate recurrent stones

Repeatedly removing stones without investigating why they keep forming can become a rather expensive game of geological whack-a-mole.


Can Medication Prevent Kidney Stones?

Yes, in appropriately selected patients.

Depending on the metabolic abnormality and stone composition, preventive medication may include:

  • Potassium citrate
  • Thiazide or thiazide-like medication
  • Allopurinol
  • Urinary alkalinising therapy
  • Tiopronin for selected cystinuria patients

Medication should ideally be guided by stone analysis, blood investigations and, when indicated, 24-hour urine testing rather than prescribed indiscriminately.


The Bottom Line

A kidney stone is not simply a kidney stone.

A calcium oxalate stone, uric acid stone, infection stone and cystine stone may look similar on a scan, but they can have very different causes and require very different long-term strategies.

Modern kidney stone management combines:

accurate imaging + appropriate stone removal + stone analysis + metabolic investigation + prevention.

Treatment may range from simple surveillance through to shockwave lithotripsy, flexible ureteroscopy and laser treatment, PCNL or, in selected uric acid stones, medical dissolution therapy.

The ultimate aim is not simply to leave the operating theatre stone-free.

It is to keep the patient stone-free.


When Should You See a Urologist?

Consider urological assessment if you have:

  • Recurrent kidney stones
  • Persistent loin or flank pain
  • Blood in the urine
  • Recurrent urinary infections
  • A stone associated with urinary obstruction
  • Increasing stone size on surveillance imaging
  • Multiple or bilateral kidney stones
  • A large renal calculus
  • Previous complex stone surgery

Severe pain associated with fever, chills or feeling systemically unwell requires urgent medical assessment, as an infected obstructed kidney can be a medical emergency.

So, come have a chat with me your local Brisbane urologist, Uro-Jo, to discuss your stones and possible management options.

This information is intended for general patient education and does not replace individual medical assessment. The appropriate investigation, surveillance and treatment of kidney stones should be tailored to the individual patient.

This blog is aligned with the current 2026 EAU Urolithiasis Guidelines, including the updated recommendations on stone composition, renal stone treatment and metabolic prevention.

EAU Guidelines on Urolithiasis

Calcium Oxalate Kidney Stones: Treatment, Surgery and Prevention

Calcium oxalate stones are the most common type of urinary tract stone. Although the name may suggest that eating too much calcium is the problem, the biology is considerably more complicated. Stone formation reflects the interaction between urine volume, calcium, oxalate, citrate, sodium, dietary factors, genetics and, in some patients, underlying metabolic or gastrointestinal conditions.

The encouraging news is that most calcium oxalate stones can be treated effectively, and the risk of forming further stones can often be substantially reduced with appropriate investigation and prevention.

This guide explains conservative management, imaging, surgical treatment, ureteric pre-stenting, laser fragmentation, recovery and long-term prevention.


What is a calcium oxalate stone?

Calcium oxalate crystals form when urine becomes sufficiently concentrated with calcium and oxalate for crystals to develop and grow.

Two principal forms occur:

  • Calcium oxalate monohydrate, which tends to be harder and more resistant to shock-wave fragmentation.
  • Calcium oxalate dihydrate, which is generally more readily fragmented.

Importantly, calcium oxalate stones cannot usually be dissolved with medication. This differs from uric acid stones, which can sometimes be dissolved by alkalinising the urine.

Treatment therefore involves either allowing a suitable stone to pass naturally, monitoring an asymptomatic stone, or physically removing or fragmenting it when intervention is required.


How do calcium oxalate stones present?

A stone sitting quietly inside the kidney may produce no symptoms at all and may be discovered incidentally during imaging performed for another reason.

When a stone moves into the ureter, symptoms can be dramatic and may include:

  • Severe loin or flank pain
  • Pain radiating towards the groin or testicle/labia
  • Nausea and vomiting
  • Blood in the urine
  • Urinary frequency or urgency
  • Burning with urination
  • Restlessness during an episode of renal colic

Fever or chills associated with an obstructing stone require urgent medical assessment. An infected obstructed kidney is a urological emergency and may require immediate drainage with a ureteric stent or nephrostomy rather than definitive stone treatment at that time.


Imaging calcium oxalate stones

CT scan

A non-contrast CT of the kidneys, ureters and bladder (CT KUB) is generally the most accurate investigation for suspected urinary tract calculi.

CT provides valuable information about:

  • Stone size
  • Exact location
  • Number of stones
  • Degree of urinary obstruction
  • Hydronephrosis
  • Stone density
  • Anatomy relevant to treatment planning

Stone density is measured in Hounsfield units (HU) and can sometimes help predict how readily a stone may fragment with shock-wave treatment.

The major disadvantage of CT is radiation exposure, although modern low-dose CT protocols can substantially reduce the radiation dose.


Ultrasound

Ultrasound avoids radiation and is particularly useful for:

  • Follow-up
  • Monitoring known renal stones
  • Detecting hydronephrosis
  • Pregnancy
  • Patients requiring repeated imaging

Its disadvantage is that small ureteric stones can be missed, and measurement of stone size is generally less accurate than CT.


Plain X-ray – KUB

Most calcium oxalate stones are radiopaque and therefore visible on a plain abdominal X-ray.

KUB imaging can consequently be useful for monitoring selected stones, particularly following treatment or when considering shock-wave lithotripsy.


Does every calcium oxalate stone require surgery?

No.

A small stone without infection, significant obstruction or uncontrolled pain can frequently be managed conservatively.

Small asymptomatic stones within the kidney may also simply be monitored.

Observation is reasonable when the potential risks and inconvenience of treatment exceed the likely benefit.

Current European guidelines recognise active surveillance as an option for selected asymptomatic renal stones, although stone growth, development of symptoms or obstruction may eventually prompt intervention.


Conservative management

For a small ureteric stone that is likely to pass spontaneously, treatment may include:

Hydration

Maintain normal good hydration. Trying to “flush” a painful obstructing stone through by drinking enormous quantities of water is generally unnecessary and can actually worsen discomfort.

Pain relief

Anti-inflammatory medication is frequently particularly effective for renal colic, provided there are no medical contraindications.

Additional analgesia or anti-nausea medication may occasionally be required.

Medical expulsive therapy

An alpha-blocker such as tamsulosin may be prescribed in selected patients to facilitate passage of a ureteric stone.

The greatest benefit appears to occur with distal ureteric stones larger than approximately 5 mm, although its use for stone passage is off-label in many jurisdictions.

Straining the urine

Catching the stone is surprisingly useful. Sending a retrieved stone for laboratory analysis confirms its composition and helps direct prevention.

The small pebble that caused an astonishing amount of trouble can therefore become an important diagnostic specimen.


When should a stone be removed?

Intervention may be recommended when there is:

  • Persistent or recurrent pain
  • Failure of the stone to progress
  • Significant urinary obstruction
  • Deterioration in renal function
  • Recurrent urinary infection
  • Increasing stone size
  • A low likelihood of spontaneous passage
  • A large renal stone burden
  • Occupational or lifestyle reasons where an unpredictable episode of renal colic would be problematic

Treatment is individualised according to stone size, location, density, renal anatomy, symptoms and patient preference.


Surgical treatment options

1. Extracorporeal Shock-Wave Lithotripsy – ESWL/SWL

Shock-wave lithotripsy focuses externally generated shock waves onto the stone, breaking it into smaller fragments that can subsequently pass through the urinary tract.

Advantages

  • No incision
  • Usually relatively rapid recovery
  • May avoid ureteroscopy
  • Useful for appropriately selected renal and ureteric stones

Disadvantages

  • Not all calcium oxalate stones fragment equally well
  • Hard calcium oxalate monohydrate stones may be resistant
  • Several treatment sessions may be required
  • Fragments still need to pass down the ureter
  • Residual fragments can remain
  • Temporary renal colic can occur
  • Less effective for some lower-pole renal stones and larger stones

The success of SWL is strongly influenced by stone size, location, composition, patient anatomy and stone hardness.


2. Ureteroscopy and laser lithotripsy

Ureteroscopy has transformed modern stone treatment.

A fine telescope is passed through the natural urinary tract:

urethra → bladder → ureter → kidney

There is therefore no external surgical incision.

Rigid or semi-rigid ureteroscopy can be used for ureteric stones, while flexible ureteroscopy allows access to stones within the kidney.


Laser fragmentation

Once the stone is identified, laser energy is delivered through an extremely fine fibre passed through the ureteroscope.

Modern systems include:

  • Holmium laser
  • Thulium fibre laser (TFL)

Both are highly effective technologies for flexible ureteroscopic stone treatment, and contemporary European guidelines recommend Ho or TFL for ureteroscopic laser lithotripsy.

The stone can be treated using several strategies.

Fragmentation and extraction

The stone is divided into several pieces, which are removed using a small basket.

Dusting

The laser progressively converts the stone into extremely small particles or “dust”, allowing much of the material to pass spontaneously.

Pop-dusting or further fragmentation

Larger fragments can be further reduced until they are sufficiently small to pass or be extracted.


Advantages of ureteroscopy and laser treatment

Ureteroscopy provides:

  • Direct visualisation of the stone
  • High stone-clearance rates
  • Treatment of stones resistant to shock-wave lithotripsy
  • Access to most areas of the ureter and kidney
  • Immediate fragmentation
  • Ability to retrieve fragments for stone analysis
  • No external incision
  • Usually short hospitalisation

Compared with shock-wave lithotripsy, ureteroscopy generally offers a greater likelihood of becoming stone-free after a single procedure, although this comes at the price of greater invasiveness and a somewhat higher complication rate.


Possible complications of ureteroscopy

Although generally safe, complications can include:

  • Blood in the urine
  • Urinary infection
  • Pain
  • Ureteric swelling
  • Temporary difficulty passing urine
  • Residual stone fragments
  • Need for repeat ureteroscopy
  • Ureteric perforation
  • Ureteric stricture
  • Sepsis

Major ureteric injury is uncommon.

The EAU reports overall ureteroscopy complication rates of approximately 4–25%, with most complications being minor. Urosepsis is an important but uncommon serious complication.

Pre-operative urine testing and treatment of urinary infection are therefore important components of safe stone surgery.


What is pre-stenting?

A ureteric stent is a thin flexible tube extending from the kidney to the bladder.

Sometimes the ureter is too narrow to safely introduce the instruments required for flexible ureteroscopy.

Instead of forcing access, a temporary stent can be inserted.

The stent gently allows passive dilatation of the ureter before definitive surgery.

Ureteroscopy is then performed at a later date, commonly after the ureter has had time to accommodate the stent.


Does everyone need pre-stenting?

No.

Routine pre-stenting before ureteroscopy is not necessary.

However, pre-stenting can be useful when:

  • The ureter is particularly narrow
  • Previous access has been unsuccessful
  • A large renal stone burden is anticipated
  • An access sheath is likely to be required
  • Staged ureteroscopy is planned
  • Emergency drainage was previously required because of infection or obstruction

Evidence suggests that pre-stenting can improve access and may improve stone-free outcomes for renal stones, although the benefit is less clear for ureteric stones.

The price of this convenience is that the patient has to live temporarily with a ureteric stent.


Ureteric stent side effects

Stents are useful pieces of equipment, but they rarely win popularity contests.

Possible symptoms include:

  • Urinary frequency
  • Urgency
  • Bladder discomfort
  • Burning during urination
  • Blood in the urine
  • Flank discomfort during urination
  • Pelvic or groin discomfort

Symptoms disappear after the stent is removed.

Alpha-blocker medication can reduce stent-related symptoms in selected patients.


Is a stent required after laser treatment?

Not always.

After straightforward uncomplicated ureteroscopy with complete stone clearance and no ureteric trauma, a postoperative stent may not be necessary.

A stent is more likely to be placed following:

  • Difficult ureteric access
  • Significant ureteric swelling
  • Ureteric trauma
  • Large stone burden
  • Residual fragments
  • Bleeding
  • Infection concerns
  • Prolonged surgery
  • Staged treatment

Current evidence supports avoiding routine postoperative stenting following uncomplicated ureteroscopy.


3. Percutaneous nephrolithotomy – PCNL

Very large renal stones are usually better approached directly through the back rather than attempting to remove the entire stone burden through the ureter.

PCNL involves creating a small tract through the skin into the kidney, through which instruments can fragment and extract the stone.

PCNL remains the standard treatment for large renal calculi, particularly stones greater than approximately 2 cm and complex or staghorn stone burdens.

Advantages

  • Excellent clearance of large stone burdens
  • Large fragments can be removed directly
  • Often more efficient than multiple ureteroscopies for large stones

Disadvantages

  • More invasive
  • Bleeding risk
  • Infection/sepsis risk
  • Longer recovery than routine ureteroscopy
  • Potential need for nephrostomy drainage
  • Rare injury to surrounding structures

Recovery after ureteroscopy and laser lithotripsy

Most patients recover relatively quickly.

It is common to experience:

  • Mild burning when passing urine
  • Pink or blood-stained urine
  • Urinary frequency
  • Mild flank discomfort
  • Stent-related symptoms

Many patients return to light activities within several days, although recovery depends on the extent of the procedure and whether a stent remains.

Heavy physical activity may need to be avoided for a short period.

Patients should seek medical attention for:

  • Fever or chills
  • Increasing severe pain
  • Persistent vomiting
  • Inability to pass urine
  • Heavy persistent bleeding
  • Feeling systemically unwell

Have we finished once the stone has gone?

Not quite.

Removing a stone treats today’s stone.

Preventing another one requires identifying why it formed.

This distinction is important because calcium oxalate stone disease can recur.

Current EAU data suggest approximately 26% of first-time stone formers experience recurrence within five years, while a smaller group develops highly recurrent disease.

Patients with recurrent stones, multiple stones, bilateral stones, young-onset stone disease or particular metabolic risk factors deserve more detailed investigation.


Metabolic investigation

Depending on the clinical situation, evaluation may include:

Blood tests

  • Calcium
  • Creatinine and renal function
  • Electrolytes
  • Uric acid
  • Bicarbonate
  • Parathyroid hormone when indicated

Stone analysis

Any retrieved stone should ideally be sent for formal analysis.

24-hour urine collection

This can measure:

  • Total urine volume
  • Calcium
  • Oxalate
  • Citrate
  • Sodium
  • Uric acid
  • Urinary pH
  • Other relevant metabolic parameters

The results allow prevention to be targeted rather than relying on a generic “kidney stone diet”.


Preventing calcium oxalate stones

1. Drink more fluid

For many patients, the single most important intervention is increasing urine volume.

Rather than concentrating stone-forming chemicals into a small volume of urine, additional fluid keeps them diluted.

Water should generally form the majority of fluid intake.

The required intake varies with climate, exercise, occupation and perspiration. Someone working outdoors during an Australian summer may require considerably more fluid than someone sitting in an air-conditioned office.


2. Do not automatically restrict calcium

This is one of the most common misconceptions about calcium oxalate stones.

Calcium in the stone does not mean calcium should disappear from the diet.

Normal dietary calcium is generally desirable because calcium within the intestine binds dietary oxalate. This reduces oxalate absorption and consequently reduces the amount reaching the urine.

The EAU specifically advises that dietary calcium should generally not be restricted unless there is a particular reason to do so.


3. Reduce excessive salt intake

A high sodium intake increases urinary calcium excretion.

Reducing dietary salt can therefore help reduce urinary calcium and forms an important part of recurrence prevention.

Pay particular attention to hidden salt in:

  • Processed foods
  • Takeaway meals
  • Processed meats
  • Sauces
  • Packaged snacks
  • Some breads and prepared foods

4. What about oxalate?

Traditional advice often involved handing patients an intimidating list of foods containing oxalate.

Contemporary Australian CARI guidance takes a more nuanced approach and recommends against a blanket low-oxalate diet for calcium oxalate stone prevention. Instead, maintaining appropriate dietary calcium and addressing excessive intake in patients with hyperoxaluria may be more useful.

Patients with documented high urinary oxalate may need individualised dietary advice.


5. Avoid excessive vitamin C supplementation

Vitamin C can be metabolised to oxalate.

For recurrent calcium oxalate stone formers, particularly those with elevated urinary oxalate, very high-dose vitamin C supplements should generally be avoided unless there is a specific medical indication.


6. Moderate excessive animal protein

Large amounts of animal protein can alter urinary chemistry in ways that encourage stone formation, including reducing urinary citrate and increasing acid and uric acid loads.

The aim is generally moderation rather than elimination.


7. What about cola and other soft drinks?

Patients frequently ask whether cola-type soft drinks contribute to kidney stones.

The answer is more nuanced than simply blaming carbonation. The bubbles themselves are not the problem. Of greater relevance are the acid composition, sugar content and the fact that regular soft-drink consumption can displace water and other more favourable fluids from the diet.

Cola-type drinks

Many dark cola-style beverages contain phosphoric acid. High consumption of these beverages has been associated in some studies with an increased risk of stone formation or recurrence.

One clinical trial examining patients with recurrent stones found that reducing soft-drink consumption lowered recurrence, with the benefit appearing particularly relevant among people whose preferred beverages were acidified with phosphoric acid.

This does not mean that an occasional cola-type drink will automatically produce a kidney stone. The concern is frequent or high-volume consumption, particularly in someone already predisposed to recurrent stones.

Sugar-sweetened soft drinks

Regular consumption of sugar-sweetened beverages may also be undesirable for stone prevention.

Large amounts of sugar, particularly fructose-containing sweeteners, may alter urinary chemistry and have been associated with a greater risk of kidney stone formation in observational studies.

There is another very practical issue: every large glass of soft drink may be replacing a glass of water.

For a recurrent stone former, that is not an especially favourable trade.

Are sugar-free versions better?

Removing sugar eliminates one potential problem, but it does not necessarily make a cola-type beverage ideal for someone with recurrent stones.

Sugar-free varieties may still contain phosphoric acid, and frequent consumption may still replace water in the daily fluid intake.

What should I drink instead?

For most calcium oxalate stone formers:

Water remains the preferred everyday drink.

Citrus-containing fluids may also be useful because citrate is a natural inhibitor of calcium stone formation, although the citrate content and sugar load of different beverages vary considerably.

The practical message is therefore not that a patient can never have another soft drink. Rather:

make water the routine drink and soft drinks the occasional one.

The kidneys are generally more interested in what happens every day than what happens at the occasional barbecue.


Preventative medication

Medication is not required for every patient.

Treatment should ideally be directed by stone analysis, metabolic assessment and 24-hour urine results.

Potassium citrate

Potassium citrate increases urinary citrate.

Citrate is helpful because it binds calcium and inhibits calcium crystal formation.

It can be particularly useful in patients with hypocitraturia.

Potential side effects include:

  • Gastrointestinal discomfort
  • Nausea
  • Diarrhoea
  • Elevated blood potassium in susceptible patients

It requires particular caution in patients with impaired renal function or medications that increase serum potassium.

Current Australian CARI guidance considers potassium citrate an important pharmacological option for prevention of recurrent stones when appropriately indicated.


Thiazide and thiazide-like diuretics

These medications reduce urinary calcium excretion and may be considered in patients with persistent hypercalciuria despite appropriate dietary measures.

Potential side effects include:

  • Low blood pressure
  • Dizziness
  • Low sodium
  • Low potassium
  • Increased uric acid
  • Changes in glucose metabolism

The evidence surrounding thiazides has become more nuanced following recent clinical trials, and treatment should therefore be individualised rather than automatically prescribed to every recurrent calcium stone former.


Allopurinol

Allopurinol is not a routine treatment for every calcium oxalate stone former.

It may have a role in selected patients with hyperuricosuria or other specific metabolic abnormalities.

Treatment should be guided by appropriate biochemical evaluation rather than simply by the presence of a calcium oxalate stone.


The pros and cons of the main approaches

Treatment Advantages Disadvantages
Observation No surgery or anaesthetic Stone may grow, move or cause future symptoms
Medical expulsive therapy May help selected ureteric stones pass Not suitable for infection, significant obstruction or large stones
Shock-wave lithotripsy Non-invasive, relatively quick recovery May require repeat treatment; fragments must pass; harder stones may resist fragmentation
Ureteroscopy + laser High clearance rate, direct visual treatment, no skin incision Anaesthetic, possible stent, infection and ureteric injury risks
PCNL Excellent treatment for large renal stone burdens More invasive with greater bleeding and recovery considerations
Preventative medication Can significantly alter relevant urinary risk factors Requires correct patient selection, monitoring and long-term adherence

How effective is treatment?

There is no single “best” treatment for every calcium oxalate stone.

A 5 mm distal ureteric stone, a 12 mm lower-pole renal stone and a 30 mm renal pelvic stone may all be made from exactly the same material, yet require completely different management.

The objective is therefore not simply to treat calcium oxalate, but to treat:

the right stone, in the right patient, with the least invasive treatment likely to achieve reliable clearance.

For appropriately selected ureteric and renal stones, modern flexible ureteroscopy and laser lithotripsy provide excellent clearance with rapid recovery. Larger stone burdens may be better managed with PCNL, while smaller asymptomatic stones may need nothing more than surveillance.


Reducing the risk of another stone

For most calcium oxalate stone formers, prevention revolves around a few principles:

  1. Maintain a high urine volume.
  2. Keep normal dietary calcium rather than unnecessarily restricting it.
  3. Reduce excessive dietary sodium.
  4. Avoid excessive animal protein and high-dose vitamin C supplementation.
  5. Investigate recurrent stone formers metabolically.
  6. Use potassium citrate, thiazide therapy or other preventative medication when a specific metabolic indication exists.
  7. Continue appropriate imaging surveillance.

Australian CARI guidelines emphasise nutrition therapy before pharmacological treatment for many stone formers, with earlier medication appropriate for selected high-risk metabolic abnormalities or patients with a high symptom burden.


The bottom line

Calcium oxalate stones are extremely common, but their treatment has become increasingly precise.

Small uncomplicated stones can often be observed or allowed to pass naturally. Stones requiring treatment can be managed with shock-wave lithotripsy, ureteroscopy with laser fragmentation, or PCNL, depending primarily on their size and location.

Ureteroscopic laser treatment offers excellent access to the urinary tract without an external incision, and modern holmium and thulium fibre lasers can fragment even very hard calcium oxalate calculi. Pre-stenting is useful in selected patients but is not routinely necessary.

Perhaps the most important message comes after the operation: removing the stone is only half the job.

Stone analysis, appropriate imaging and metabolic evaluation can identify why stones are forming. Increased fluid intake, sensible dietary modification and targeted preventative medication can then reduce the likelihood that another small crystal grows into the next large problem.


This information is intended for general patient education and does not replace individual assessment by a urologist. Management should be tailored to stone size and location, kidney function, infection risk, medical history and individual metabolic findings.

So, if you are in trouble with ureteric colic, attend your local Emergency Department for acute management and assessment for urgent stent placement. Further management will be discussed with you thereafter. Ask your GP for a referral to see your Brisbane Urologist, Uro-Jo to remove this nasty critter.

Further reading

Dissolution Therapy for Uric Acid Kidney Stones: Can You Really Dissolve a Stone?

Most kidney stones need to be passed, fragmented or surgically removed. Uric acid stones are different.

Unlike calcium-based stones, a true uric acid stone can often be chemically dissolved inside the urinary tract simply by changing the acidity of the urine. This treatment is known as oral dissolution therapy, urinary alkalinisation or oral chemolysis.

For appropriately selected patients, it can mean avoiding ureteroscopy, laser treatment, shock-wave lithotripsy or percutaneous surgery altogether.

What is a uric acid stone?

Uric acid stones account for approximately 10% of urinary stones, although their frequency varies considerably between populations. They tend to develop when the urine remains persistently acidic, particularly at a urinary pH below approximately 5.5.

Risk factors include:

  • persistently acidic urine
  • low fluid intake and concentrated urine
  • high intake of animal protein and purine-rich foods
  • gout or elevated uric acid
  • obesity and metabolic syndrome
  • diabetes and insulin resistance
  • chronic diarrhoea or intestinal disease
  • high urinary uric acid excretion
  • some haematological disorders and chemotherapy

Importantly, many people who form uric acid stones do not have dramatically elevated blood or urinary uric acid. The major problem is often simply that their urine is too acidic. This is why alkalinising the urine is usually more important than immediately prescribing allopurinol.

Why can uric acid stones be dissolved?

Uric acid is poorly soluble in acidic urine. As urinary pH rises, uric acid becomes increasingly ionised and substantially more soluble.

Think of the stone as a sugar cube sitting in the wrong cup of tea. Change the chemistry of the surrounding fluid and the solid material can gradually return into solution.

The aim of dissolution therapy is therefore to raise the urinary pH sufficiently and keep it elevated throughout the day, allowing the surface of the stone to gradually dissolve.

Current European Association of Urology guidance recommends oral chemolysis using alkaline citrate or sodium bicarbonate, with urine pH generally adjusted to approximately 7.0–7.2 during active dissolution therapy.

How is dissolution therapy performed?

The most commonly used medication is potassium citrate.

Alternative alkalinising agents include:

  • sodium bicarbonate
  • sodium citrate
  • other citrate preparations

Potassium citrate is generally preferred when appropriate because sodium-containing preparations increase sodium intake and may increase urinary calcium excretion. Sodium-based treatment can nevertheless be useful when potassium therapy is unsuitable, particularly when there is concern regarding hyperkalaemia.

The exact dose needs to be individualised according to kidney function, serum electrolytes and, most importantly, the patient’s urinary pH response.

Monitoring your urine pH

This is a crucial part of treatment.

Patients are usually asked to measure their urinary pH at home using suitable pH strips or a pH meter, often at several points during the day.

The dose of alkalinising medication can then be adjusted to keep the urine within the desired range. The EAU specifically recommends teaching patients to monitor their urine pH and modify alkalinising medication accordingly.

The objective is not simply to swallow tablets. It is to achieve and maintain the correct urinary pH.

How effective is dissolution therapy?

When the stone really is composed predominantly of uric acid and urinary alkalinisation is successfully achieved, dissolution therapy can be remarkably effective.

A systematic review involving 1,075 patients reported:

Outcome Approximate rate
Complete dissolution 61.7%
Partial dissolution 19.8%
Complete or partial response 80.5%
Treatment discontinued 10.2%
Required surgical intervention 15.7%

These figures are encouraging, but they also make an important point: dissolution therapy does not work for everyone.

Success depends heavily on correct stone identification, adequate urinary alkalinisation, patient compliance and the size and burden of the stones.

How quickly will the stone disappear?

This varies considerably.

Small stones may respond relatively quickly, while larger stones can require treatment over several months. Dissolution is generally a gradual process rather than an overnight disappearing act.

One clinical series assessing stone volume found that response was associated with achieving a higher urinary pH during treatment, reinforcing the importance of adequate alkalinisation.

Follow-up imaging is therefore important to determine whether the stone is shrinking rather than simply assuming that treatment is working.

How do we know that the stone is uric acid?

This is one of the most important questions.

There is little benefit in trying to dissolve a calcium oxalate stone with urinary alkalinisation. It will remain stubbornly unimpressed.

Evidence suggesting a uric acid stone includes:

  • previous analysis confirming a uric acid stone
  • persistently acidic urinary pH
  • radiolucency on plain X-ray
  • relatively low density on non-contrast CT
  • appropriate clinical and metabolic risk factors

Dual-energy CT can sometimes help differentiate uric acid from non-uric-acid stones.

Stone composition should therefore be assessed as accurately as possible before embarking on prolonged dissolution therapy.

Advantages of dissolution therapy

The biggest advantage is obvious: it is non-invasive.

Successful treatment may avoid anaesthesia and procedures such as ureteroscopy, laser lithotripsy, shock-wave lithotripsy or PCNL.

Other potential advantages include:

  • no surgical incision
  • no instrumentation of the urinary tract
  • usually no hospital admission
  • avoidance of anaesthetic risk
  • potentially useful for patients with significant medical comorbidities
  • treatment can simultaneously address the metabolic environment responsible for future uric acid stones
  • relatively inexpensive compared with surgery
  • can potentially treat multiple uric acid stones simultaneously

For the right patient, dissolution therapy can turn a surgical problem into a metabolic one.

What are the disadvantages?

The trade-off is that dissolution therapy requires time, patience and active participation.

Patients need to take medication consistently, maintain good fluid intake, monitor urinary pH and attend follow-up investigations.

Other disadvantages include:

  • dissolution can take weeks or months
  • treatment may fail
  • the stone may only partially dissolve
  • repeated imaging may be required
  • incorrectly identified non-uric-acid stones will not dissolve
  • excessively alkaline urine can encourage formation of calcium phosphate stones
  • patients with obstruction or infection may require urgent intervention rather than simply waiting for dissolution

In the systematic review discussed above, approximately 15.7% of patients ultimately required an intervention despite attempting dissolution therapy.

Side effects of potassium citrate

Potassium citrate is generally well tolerated, but side effects can occur.

The most common are gastrointestinal and may include:

  • nausea
  • abdominal discomfort
  • bloating
  • diarrhoea
  • vomiting

Taking the medication with food may improve gastrointestinal tolerance.

A more important potential complication is hyperkalaemia, meaning an excessively high potassium concentration in the blood.

This is particularly relevant in patients with:

  • impaired kidney function
  • medications that increase potassium
  • significant cardiac disease
  • other conditions affecting potassium regulation

For this reason, kidney function and electrolytes may need monitoring during therapy.

What about sodium bicarbonate?

Sodium bicarbonate can also effectively alkalinise the urine and is an alternative when potassium citrate is unsuitable.

However, the additional sodium load can be undesirable in patients with conditions such as hypertension, fluid retention or heart failure. Sodium-containing alkali may also increase urinary calcium excretion, which is one reason potassium citrate is generally preferred when clinically appropriate.

Can the urine become too alkaline?

Yes.

More alkaline is not endlessly better.

Although increasing urinary pH improves uric acid solubility, excessive alkalinisation can increase the risk of calcium phosphate stone formation. The EAU therefore recommends targeting rather than indiscriminately increasing urinary pH.

This is why home pH monitoring is so useful.

The aim is controlled chemistry, not turning the bladder into a miniature alkaline swimming pool.

What if the stone is obstructing the kidney?

An obstructed kidney requires more caution.

If a uric acid stone is causing significant obstruction, particularly in the presence of infection, deteriorating renal function or uncontrolled symptoms, simply waiting for the stone to dissolve may be inappropriate.

An infected obstructed urinary system is a urological emergency and requires urgent drainage.

Where an obstructing uric acid stone is otherwise suitable for dissolution, urinary drainage with a ureteric stent or nephrostomy may sometimes be performed first, followed by alkalinisation. The EAU recommends oral chemolysis together with urinary drainage where uric acid stones are obstructing the collecting system.

Does allopurinol dissolve uric acid stones?

Not directly in the same way that alkalinisation does.

Allopurinol reduces the production of uric acid and is particularly useful in patients with hyperuricosuria, gout or continued uric acid stone formation despite appropriate management.

However, most uric acid stone formers have excessively acidic urine as the dominant problem. The AUA therefore recommends potassium citrate as first-line therapy for urinary alkalinisation rather than routinely using allopurinol as first-line treatment for every patient with uric acid stones.

Allopurinol may be added when there is significant hyperuricosuria or recurrent stone formation despite appropriate urinary alkalinisation. The EAU similarly recommends allopurinol for hyperuricosuric urate stone formers.

Preventing the stone from coming back

Dissolving the existing stone is only half the job.

Uric acid stone formers are considered at high risk of recurrence, so the underlying metabolic environment should also be addressed.

Long-term prevention may include maintaining a generous fluid intake, moderating excessive animal protein and purine intake, weight and metabolic health management, continued urinary alkalinisation when indicated, and treatment of hyperuricosuria where appropriate.

A metabolic stone assessment, often including blood tests and 24-hour urine collections, can help identify the factors driving recurrent stone formation.

Dissolution therapy versus surgery

There is no universal winner.

Dissolution therapy is particularly attractive when:

  • the stone is highly likely to be uric acid
  • symptoms are controlled
  • there is no untreated infection
  • renal function is satisfactory
  • immediate stone clearance is unnecessary
  • the patient can reliably monitor urinary pH and attend follow-up

Surgical treatment may be preferable when:

  • the diagnosis of uric acid stone is uncertain
  • the stone is causing significant or persistent obstruction
  • infection is present
  • pain is difficult to control
  • rapid stone clearance is required
  • the stone fails to shrink despite adequate alkalinisation
  • the patient prefers definitive treatment

The bottom line

Uric acid stones have one rather convenient weakness: their chemistry can be used against them.

By raising urinary pH with medications such as potassium citrate, genuine uric acid calculi can often be progressively dissolved without an operation. Published evidence suggests that approximately 80% of appropriately treated patients achieve at least partial dissolution, although complete dissolution occurs in a smaller proportion and some patients will ultimately require surgery.

Successful treatment depends on three things: correctly identifying the stone, achieving the appropriate urinary pH, and monitoring the response.

For selected patients, dissolution therapy offers something unusual in stone surgery: rather than breaking the stone, extracting it or blasting it with a laser, we may simply persuade it to disappear.

So, if you are a stone sufferer and you are in need of help, come see your Brisbane urologist, Uro-Jo at the Wesley or Caboolture private hospitals.

This information is intended for general patient education and does not replace individual assessment by a urologist. Treatment and urinary pH targets should be individualised, particularly in patients with renal impairment, infection, obstruction or electrolyte abnormalities.

Ureteric Stents: Why They Are Used, Side Effects, Complications and Treatment Options

A ureteric stent is a thin, flexible tube placed inside the ureter, the channel that carries urine from the kidney to the bladder. Stents are commonly used in urology to maintain drainage of urine from the kidney when the ureter is blocked, narrowed, injured or at risk of becoming obstructed.

Most ureteric stents are intended to be temporary. However, some patients with chronic or recurrent ureteric obstruction require long-term stenting, with either regular stent changes or specialised longer-term stents.

Although ureteric stents can be extremely effective at protecting kidney function, they can also cause bothersome urinary symptoms. Understanding why a stent is required, how long it needs to remain in place and what symptoms to expect can make the experience considerably easier.


What Does a Ureteric Stent Look Like?

The most commonly used stent is called a double-J stent or JJ stent.

It has:

  • one curled end positioned within the kidney
  • a straight section passing down the ureter
  • another curled end positioned within the bladder

The curls help prevent the stent from migrating upwards or downwards.

Urine can drain through the hollow centre of the stent and around its outside, allowing urine to bypass an area of narrowing or obstruction.


Why Might I Need a Ureteric Stent?

There are several reasons for inserting a ureteric stent.

1. Kidney and Ureteric Stones

Urinary stones are among the most common reasons for ureteric stent placement.

A stone lodged within the ureter can obstruct urine drainage and cause:

  • severe renal colic
  • swelling of the kidney, known as hydronephrosis
  • deterioration in kidney function
  • infection behind the obstruction

A stent may be inserted urgently to relieve the obstruction.

Stents are also commonly placed temporarily following ureteroscopy and laser treatment of urinary stones, particularly when there has been swelling, instrumentation or trauma to the ureter.


2. Infection Associated With an Obstructed Kidney

An obstructed and infected kidney can represent a urological emergency.

Patients may develop:

  • fever
  • chills or rigors
  • flank pain
  • nausea or vomiting
  • low blood pressure
  • sepsis

Urgent drainage of the kidney may be required using either:

a ureteric stent

or

a percutaneous nephrostomy tube, which drains the kidney externally through the back.

The infection is generally treated before definitive treatment of the underlying stone or obstruction.


3. Ureteric Stricture

A ureteric stricture is an abnormal narrowing of the ureter.

It may occur following:

  • previous surgery
  • stone disease
  • ureteroscopy
  • radiotherapy
  • inflammation
  • endometriosis
  • retroperitoneal fibrosis
  • previous ureteric injury

A stent can maintain drainage while the underlying problem is investigated or treated.


4. Following Ureteric Surgery

Stents are frequently placed after surgery involving the ureter to allow healing while maintaining urinary drainage.

Examples include:

  • ureteroscopy
  • ureteric reconstruction
  • ureteric reimplantation
  • pyeloplasty
  • treatment of ureteric injuries

The stent effectively acts as an internal splint while the ureter heals.


5. Cancer-Related Ureteric Obstruction

Tumours within the pelvis or abdomen can compress or invade the ureters.

Examples include cancers involving the:

  • prostate
  • bladder
  • cervix
  • uterus
  • ovary
  • bowel
  • lymphatic system

Ureteric obstruction can also occur from metastatic disease or enlarged lymph nodes.

In these circumstances, long-term ureteric drainage may be required to preserve kidney function.


6. Retroperitoneal Fibrosis

Retroperitoneal fibrosis is an uncommon condition in which inflammatory or fibrotic tissue develops around structures behind the abdominal cavity.

This tissue can surround and compress one or both ureters.

Some patients require prolonged ureteric stenting while the underlying condition is treated.


What Does Having a Ureteric Stent Feel Like?

Experiences vary considerably.

Some patients hardly notice their stent.

Others experience significant symptoms.

Collectively, these are often referred to as ureteric stent-related symptoms.

Common symptoms include:

Urinary frequency

You may need to urinate more frequently than normal.

Urinary urgency

There may be a sudden and sometimes uncomfortable urge to urinate.

Bladder discomfort

The lower end of the stent can irritate the bladder and produce discomfort or pressure.

Blood in the urine

A small amount of blood in the urine is common, particularly following physical activity.

The urine may vary from slightly pink to more obviously blood-stained.

Kidney or flank discomfort

Some patients experience discomfort in the kidney when urinating.

This can occur because bladder pressure during urination may be transmitted back towards the kidney along the stent.

Pain during or after urination

Discomfort may occur in the bladder, groin, urethra or kidney.

Symptoms may fluctuate and are often worse following strenuous physical activity.


Managing Ureteric Stent Symptoms

Treatment depends upon the severity and type of symptoms.

Maintain Appropriate Hydration

Maintaining normal hydration is generally helpful.

Excessive fluid intake, however, can sometimes worsen urinary frequency, urgency and kidney discomfort. The aim is usually adequate rather than excessive hydration, unless your doctor has advised otherwise.


Simple Pain Relief

Paracetamol or anti-inflammatory medication may be appropriate for some patients.

Anti-inflammatory medications are not suitable for everyone, particularly patients with certain kidney, stomach, cardiovascular or bleeding problems.

Your treating doctor can advise which medications are appropriate.


Alpha-Blockers

Medications such as tamsulosin may reduce stent-related discomfort in selected patients.

These medications relax smooth muscle within the urinary tract and may improve:

  • flank discomfort
  • urinary frequency
  • urinary urgency
  • pain associated with the stent

Possible side effects include dizziness and lowering of blood pressure.


Medication for Bladder Overactivity

When urinary urgency and frequency are particularly troublesome, medications used for an overactive bladder may occasionally help.

These include selected:

  • antimuscarinic medications
  • beta-3 agonists

The appropriate medication depends upon the patient’s symptoms and other medical conditions.


Adjusting Physical Activity

Exercise is usually safe with a ureteric stent unless your surgeon advises otherwise.

However, strenuous exercise may increase:

  • blood in the urine
  • flank discomfort
  • bladder irritation

Reducing the intensity of activity temporarily can sometimes make symptoms considerably more manageable.


Possible Complications of Ureteric Stents

Most stents function without major problems, but complications can occur.

Urinary Infection

A stent is a foreign body within the urinary tract and bacteria may colonise its surface.

Seek medical attention if you develop:

  • fever
  • chills or rigors
  • worsening flank pain
  • feeling significantly unwell
  • persistent burning during urination

Urine testing and antibiotics may be required.


Stent Migration

Occasionally a stent moves from its intended position.

It can migrate towards the kidney or bladder and may no longer provide adequate drainage.

Imaging and repositioning or replacement may be required.


Stent Blockage

Stents can occasionally become blocked by:

  • blood clots
  • stone fragments
  • urinary debris
  • encrustation

If obstruction is significant, the stent may need to be replaced.


Encrustation and Stone Formation

Minerals within the urine gradually deposit onto the surface of a stent.

This process is known as encrustation.

The risk increases the longer a stent remains in place.

Severe encrustation can make stent removal considerably more complicated and may require additional endoscopic or stone procedures.


The Forgotten Stent

One of the most important complications is a stent inadvertently being left in place for much longer than intended.

A forgotten stent may become:

  • heavily encrusted
  • blocked
  • infected
  • fragmented
  • surrounded by stone formation

Removal can then require several procedures.

If you have a ureteric stent, you should know when it is expected to be removed or changed.

Many urology practices maintain a formal stent registry or reminder system for this reason.


When Should You Seek Urgent Medical Attention?

Contact your treating team or seek urgent medical assessment if you develop:

  • fever or rigors
  • severe or increasing kidney pain
  • inability to pass urine
  • persistent heavy bleeding or blood clots
  • persistent vomiting
  • significant deterioration in your general condition
  • severe pain that is not controlled with prescribed medication

Fever associated with an obstructed urinary system requires particularly prompt assessment.


How Long Can a Ureteric Stent Stay In?

There is no single answer because it depends upon:

  • why the stent was inserted
  • the type and material of the stent
  • stone-forming tendency
  • infection
  • pregnancy
  • cancer treatment
  • kidney function
  • the manufacturer’s recommended indwelling time

Some temporary stents remain in place for only a few days or weeks.

Other stents designed for longer-term drainage may remain for several months before planned replacement.

A stent should therefore never simply be assumed to be safe indefinitely. Follow the removal or replacement schedule provided by your urologist.


Temporary Ureteric Stents

The majority of ureteric stents are temporary polymer JJ stents.

They may be used:

  • after stone surgery
  • following ureteroscopy
  • after reconstructive surgery
  • while ureteric inflammation settles
  • while awaiting definitive treatment of an obstruction

Once the ureter has healed or the underlying obstruction has been treated, the stent is removed.


How Is a Ureteric Stent Removed?

Short-term stents may occasionally have a fine string attached to the end of the stent. This allows removal without another cystoscopic procedure in appropriately selected patients.

Most stents without strings are removed using flexible cystoscopy.

A small flexible telescope is passed through the urethra into the bladder. The lower end of the stent is identified, grasped and gently removed.

This is commonly performed as a short outpatient procedure using local anaesthetic gel.


What if Long-Term or Permanent Drainage Is Required?

Some causes of ureteric obstruction cannot easily be corrected.

In these circumstances, maintaining kidney drainage becomes a long-term management issue.

Options include:

Regularly Changed Polymer Stents

A conventional JJ stent can remain a long-term solution provided it is changed at appropriate intervals.

The disadvantage is the need for repeated procedures.

Long-Term or Metallic Ureteric Stents

Specialised metallic or reinforced stents may be considered in selected patients with chronic ureteric obstruction.

These are designed to resist external compression and, depending upon the particular device and clinical circumstances, may allow longer intervals between changes.

They can be particularly useful in selected cases of:

  • malignant ureteric obstruction
  • retroperitoneal fibrosis
  • recurrent benign ureteric strictures

They are not suitable for every patient and still require ongoing urological surveillance.

Percutaneous Nephrostomy

When a ureteric stent cannot be inserted, repeatedly fails or does not provide adequate drainage, a nephrostomy tube may be required.

This is inserted through the skin directly into the kidney and drains urine externally into a collection bag.

Definitive Reconstructive Surgery

For suitable patients with benign obstruction, correcting the underlying problem may be preferable to lifelong stenting.

Depending upon the location and length of the obstruction, options may include:

  • pyeloplasty
  • ureteric reimplantation
  • ureteroureterostomy
  • bladder flap reconstruction
  • bowel interposition
  • other specialised ureteric reconstruction

The aim is to restore natural urinary drainage and eliminate the need for a permanent stent.


Temporary Versus Long-Term Stenting

Temporary Stent Long-Term Stenting
Typical indication Stones, surgery, temporary obstruction Chronic benign or malignant obstruction
Common stent Polymer JJ stent Regularly changed polymer or specialised long-term stent
Duration Days to months Potentially years with planned surveillance/exchange
Replacement required? Usually removed once no longer needed Yes, according to stent type and clinical situation
Main concern Symptoms, infection, migration Encrustation, blockage, infection and repeated procedures
Alternative Removal after definitive treatment Reconstruction or nephrostomy in selected patients

Is There Really a “Permanent” Ureteric Stent?

The term permanent stent can be misleading.

A patient may require permanent ureteric drainage, but this does not necessarily mean that the same stent remains in place permanently.

Most long-term stent strategies require:

  • regular clinical review
  • monitoring of kidney function
  • periodic imaging when appropriate
  • surveillance for infection or obstruction
  • planned stent exchange according to the type of device being used

The objective is not simply to keep a stent in indefinitely, but to maintain safe and reliable drainage of the kidney.


Living With a Ureteric Stent

A ureteric stent can be an extremely useful device. It can relieve obstruction, control an emergency situation and protect kidney function while allowing definitive treatment to be planned.

Unfortunately, stents are not always comfortable.

Urinary frequency, urgency, blood in the urine and intermittent bladder or kidney discomfort are relatively common. These symptoms do not necessarily mean something is wrong with the stent, and several strategies and medications can make them easier to tolerate.

The most important questions to know after having a stent inserted are:

Why was my stent inserted?

When should it be removed or changed?

What symptoms should prompt me to seek medical attention?

If you are uncertain about any of these, contact your urologist or treating team.


This information is intended for general patient education and does not replace individual medical advice. The appropriate type and duration of ureteric stenting depends upon the cause of obstruction, kidney function, infection risk and individual patient circumstances.

Come chat to Dr Jo Schoeman your friendly Brisbane based Urologist to discuss your stent issues.

Cysto-Lithopaxy

Endoscopic procedure used for breaking up a bladder stone. Either with a stone crusher or laser

Why is it done?

  • To break up a bladder calculus (stone).


Risk factors:

  • Bladder outflow obstruction.
  • BPH with chronic retention.
  • Urethral stricture.
  • Neurogenic bladder.
  • Renal calculi disease.
  • Metabolic disorders.
  • Malnutrition.
  • Chronic infections.
  • Foreign objects in bladder.

How is it done?

  • A cystoscopy is performed by placing a camera in the urethra with the help of a lubricant jelly and an irrigate (fluid).
  • The bladder is then distended with fluid (saline).
  • The inside of the bladder is viewed for pathology.
  • If any suspicious lesions are seen, a biopsy will be taken.
  • Stone crushing is attempted with a lithotrite (a crushing device).
  • If the calculus is too large, laser will be utilized to fragment the stone and the smaller stones evacuated.
  • Antibiotics may be given to prevent infection.

What to expect after the procedure?

  • Hematuria (blood in your urine)
  • You will have a n indwelling catheter (IDC), which will remain in your bladder until your urine is clear.
  • You may have a continuous bladder irrigation with Saline to help clear the bleeding.
  • Pain on initial passing of urine when the catheter is removed.
  • Bladder infection ranging from a burning sensation to, fever, to pus (rare).
  • Lower abdominal discomfort which will persist for a few days.
  • NB! Each person is unique and for this reason symptoms vary.

What next?

  • This all depends on what is found during the procedure. All the options will be discussed in detail.
  • You may require further attention to your prostate or bladder outlet to prevent further stone formation.
  • There may be some blood in the urine. This can be remedied by drinking plenty of fluids until it clears.
  • Patients should schedule a follow-up appointment within 1 month to discuss the etiology of the calculus as well as what other procedures may be involved to prevent this from occurring again.
  • Please don’t hesitate to direct all further queries to Dr Schoeman.


Download Information Sheet

Wes Cysto-Lithopaxy Laser

Extra-Corporeal Shock Wave Lithotripsy – ESWL

ESWL

Non-invasive technique of shattering renal or ureteric calculi using sound waves. This service is provided by an external lithotripsy service who brings their lithotripter to the hospital chosen for your procedure.

Why is it done?

  • Renal stones of any size, usually larger than 1cm obstructing/ non-obstructing the renal pelvis or ureter.
  • Conservative form of treatment with external treatment administered through the skin with electromagnetic/ piezo-electric shock waves.
  • Shock waves compress and distract the stone and the stone crystal fragments at its weakest links.
  • Non-invasive.
  • 70% of patients are stone free after this procedure, depending on the size of the stone and consistency of the stone.
  • You may present with colicky pain on the affected side when stone fragments make their way down the ureter.

What to be aware of:

  • Colicky pain that persists.
  • Infection and fever.

Contact the rooms or your nearest Emergency Department ASAP

How is it done?

  • Patients will receive a general anaesthesia.
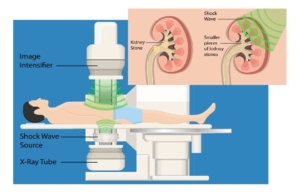
  • Prophylactic antibiotics is given.
  • The correct kidney is identified and marked while you are awake.
  • You are placed on a specifically designed table where a compartment in the bed underlying the affected kidney is removed to enable a large fluid containing probe to press up against your back.
  • With radiological imaging the shock waves are aimed onto the stone in 2, 90-degree angles.
  • The stone is then bombarded with the shock waves. A total of approx. 4000 shots are administered until the stone fragments and disappears.

What next?

  • As soon as you are awake and have kept some food down and emptied your bladder, you may leave for home.
  • You may experience blood in your urine.
  • You may experience colicky/crampy pains as you pass the fragments.
  • Allow for a few days for stabilization of symptoms.
  • A follow-up appointment will be scheduled for 3 months.
  • If any stones are caught and sent for evaluation, stone analysis results will be discussed at this consultation in order to formulate a plan to prevent recurrences.
  • DON’T SUFFER IN SILENCE, OR YOU WILL SUFFER ALONE!


Download Information Sheet

Wes Extra Corporeal Shock Wave Lithotripsy ESWL