Tag Archive for: Caboolture urologist

Microbiome of the Male Reproductive System: The Hidden Factor in Men’s Health

When most people think about the microbiome, they imagine gut bacteria affecting digestion and immunity. But did you know that the male reproductive system also has its own unique microbiome? This hidden ecosystem of microorganisms plays a surprising role in fertility, hormone balance, and overall sexual health.

What Is the Male Reproductive Microbiome?

The male reproductive microbiome refers to the community of bacteria and other microorganisms living in the penis, testes, prostate, and semen. While it’s less studied than the gut microbiome, research shows that these microbes are crucial for maintaining reproductive health.

A balanced microbiome supports sperm quality, prevents infections, and even influences the immune environment of the reproductive tract. On the other hand, imbalances sometimes caused by antibiotics, poor hygiene, infections, or lifestyle factors can lead to fertility issues and other complications.

How the Microbiome Affects Fertility

Studies suggest that an unhealthy male reproductive microbiome may contribute to:

  • Reduced sperm motility: making it harder for sperm to reach the egg.

  • Decreased sperm count: fewer sperm can lower the chance of conception.

  • DNA fragmentation: damaged sperm DNA can affect embryo quality.

  • Inflammation: chronic inflammation in the reproductive tract can impair fertility and sexual health.

Even small changes in microbial balance can have a measurable impact on reproductive outcomes, highlighting why men’s microbiomes deserve attention.

Factors That Influence the Male Microbiome

Several lifestyle and environmental factors can disrupt the delicate balance of microbes:

  • Antibiotic use: kills both harmful and beneficial bacteria.

  • Diet: processed foods, sugar, and alcohol can negatively impact microbial health.

  • Hygiene: poor genital hygiene can allow harmful bacteria to thrive.

  • Sexual activity: sexually transmitted infections can alter microbial balance.

  • Chronic stress: stress hormones can influence bacterial populations and immunity.

Maintaining healthy habits is essential for keeping the microbiome in check.

Supporting a Healthy Male Microbiome

Here are practical ways men can support their reproductive microbial health:

  1. Balanced diet: Include fiber-rich fruits, vegetables, fermented foods, and lean protein.

  2. Probiotics: Supplements or natural sources (like yogurt or kefir) can help maintain beneficial bacteria.

  3. Safe sexual practices: Use protection and get regular STI screenings.

  4. Gentle hygiene: Avoid harsh soaps; washing with mild cleansers is best.

  5. Lifestyle management: Reduce alcohol, quit smoking, manage stress, and exercise regularly.

Why It Matters

The male reproductive microbiome is more than just a scientific curiosity, it’s a critical component of sexual and reproductive health. By understanding and supporting this hidden ecosystem, men can improve fertility, reduce infection risk, and even support hormone balance and overall wellness.


Conclusion:
Men’s health isn’t just about testosterone, erections, or sperm count, it’s also about the microscopic world living inside the reproductive system. Paying attention to the male reproductive microbiome is a small step with potentially big benefits for fertility, sexual function, and overall health.

Subclinical Hypogonadism: Low Testosterone Without Obvious Symptoms

Low testosterone and “subclinical hypogonadism”: what do the results mean?

Testosterone contributes to sexual function, muscle and bone health, and other body processes. A man may wonder about testosterone when he notices a change in libido, energy or strength. Those symptoms deserve attention, but they have many possible causes. A blood result below a laboratory range does not, by itself, establish testosterone deficiency or mean that testosterone treatment will help.[1–3]

Is “subclinical hypogonadism” a hidden disease?

The term can be confusing. In specialist literature, compensated or subclinical hypogonadism may describe normal testosterone with an elevated luteinising hormone (LH). LH is the signal from the pituitary gland that stimulates the testes to make testosterone. The clinical significance of this laboratory pattern is uncertain; it should not be described as a predictable early stage that inevitably leads to complications.[2]

Established male hypogonadism is a clinical syndrome involving compatible symptoms or signs together with consistently low testosterone on appropriately collected tests. Some men have subtle symptoms, but fatigue, irritability and poor concentration are not specific to testosterone deficiency. Recent Endocrine Society guidance cautions against routine testosterone screening in men without symptoms and against applying vague “age-related” labels without a careful diagnosis.[1–3]

When might testosterone deficiency be considered?

A persistent reduction in sexual desire, fewer spontaneous morning erections, erectile difficulties, reduced body hair, small testes, loss of strength, infertility, unexplained anaemia or low-trauma fractures can prompt a clinician to consider testosterone deficiency. No one symptom proves it, and erectile dysfunction often has vascular, psychological, medication-related or other causes.[2, 3]

Potential causes include a disorder of the testes (primary hypogonadism) or of the hypothalamus or pituitary gland (secondary hypogonadism). Obesity, type 2 diabetes, chronic illness, sleep problems and medicines such as opioids or glucocorticoids may also be associated with lower measured testosterone. Acute illness can temporarily affect a test result. The aim is to find and address the cause rather than assume that a symptom is due to normal ageing or that testosterone is the answer.[1–3]

How is it investigated?

Assessment starts with the person’s symptoms, medical history, medicines, sleep, fertility plans and an examination when indicated. A clinician generally orders two separate early-morning testosterone tests, preferably fasting and when the person is otherwise well. Testosterone changes across the day, and assays and reference ranges vary. A single borderline result should be interpreted cautiously.[1–3]

LH and follicle-stimulating hormone (FSH) help distinguish testicular from pituitary or hypothalamic causes. Depending on the circumstances, a clinician may assess prolactin, other pituitary hormones, thyroid function, blood count or iron studies. Free testosterone may be helpful in selected cases when total testosterone is borderline or the protein that binds testosterone is altered; it is not an automatic replacement for a reliable total testosterone test. Further investigations, such as pituitary imaging or bone density assessment, are guided by the clinical findings.[2, 3]

A normal testosterone result with raised LH is not the same as confirmed low testosterone. It may warrant review in context, but there is no established reason to prescribe testosterone solely to “treat the number.”[2]

Does a borderline result predict future disease?

Confirmed, longstanding testosterone deficiency can affect bone density, body composition and sexual function. However, it is misleading to state that everyone with a borderline measurement or a compensated laboratory pattern will develop osteoporosis, diabetes or heart disease.[2]

Low testosterone is often found alongside obesity or poor health, but an association does not show that low testosterone caused a cardiovascular or metabolic condition. Likewise, testosterone treatment should not be offered as a way to prevent heart disease or treat diabetes. Benefits and risks depend on the person’s diagnosis and circumstances.[1, 3]

What can be done first?

If obesity, poor sleep, a medicine or another health condition may be contributing, addressing that issue is often a useful first step. A manageable programme of physical activity, including resistance exercise, a balanced diet and treatment of sleep problems can support overall health. These steps are valuable whether or not testosterone increases; they are not guaranteed to correct an underlying testicular or pituitary disorder. In men with obesity-related hypogonadism and no other identified cause, the Endocrine Society describes weight loss as the usual first-line approach.[1]

If low libido, fatigue or mood symptoms persist, assessment should also consider depression, sleep apnoea, relationship factors, diabetes, anaemia and other possible causes. The plan should follow the findings rather than a generic “testosterone boost” programme.[1–3]

When is testosterone treatment considered?

Testosterone replacement may be appropriate for a man with confirmed hypogonadism, clinically important symptoms and a discussion of likely benefits, uncertainties, alternatives and monitoring. An Australian registered product’s indication requires deficiency to be confirmed by clinical features and biochemical tests. Treatment is not routinely recommended for an otherwise well man because of age, a single borderline test or vague symptoms alone.[1, 3, 4]

Testosterone can suppress sperm production and may compromise fertility. Men planning children should discuss this before starting therapy; fertility-preserving management may require specialist input. Assessment before treatment also considers the blood count, prostate concerns, sleep apnoea, cardiovascular history and other conditions. Follow-up includes symptoms, testosterone level, haematocrit and prostate assessment as appropriate.[2, 3, 5]

The safety picture is nuanced. A large trial did not find a meaningful increase in heart attack or stroke over roughly one to four years in the men studied, but reported more pulmonary embolism and fractures in the testosterone group; long-term safety remains uncertain. Those findings do not justify declaring therapy either universally safe or universally harmful.[1]

The main message

If symptoms concern you, discuss them with your GP. A thoughtful assessment can identify testosterone deficiency when it is present and uncover other causes when it is not. “Subclinical hypogonadism” is not a reliable label for every man with tiredness or a borderline blood test. Treatment decisions should be based on a clear diagnosis and personal goals, especially future fertility.[1–3]

This article is general information, not an individual diagnosis or treatment recommendation. Do not start, stop or change prescribed hormones without advice from your treating clinician.

References

  1. Endocrine Society. Statement on Testosterone Replacement Therapy, 2026.
  2. European Association of Urology. Sexual and Reproductive Health Guidelines: Male Hypogonadism.
  3. Endocrine Society. Testosterone Therapy in Men With Hypogonadism: Clinical Practice Guideline.
  4. Therapeutic Goods Administration. ANDROFORTE 5 registration and approved indication.
  5. Healthy Male. Androgen deficiency clinical summary guide.

Living with an indwelling urethral catheter

An indwelling urethral catheter is a soft tube passed through the urethra into the bladder. A small balloon holds it in place and urine drains into a bag. It may be needed for a few days after an operation or for longer when the bladder cannot empty safely. The reason for the catheter and a plan for review should be clear to the patient and the people helping with their care.[1, 2]

Why might a catheter be needed?

Common reasons include acute urinary retention, an obstruction to urine flow, temporary drainage after surgery, and selected cases of chronic retention when other options are unsuitable. In hospital, a catheter may be used to monitor urine output in a critically ill person or manage bleeding and clots. It can occasionally support comfort at the end of life. A urethral catheter is generally not the first response to urinary leakage alone.[1]

When practical, the team should discuss whether the catheter can be removed after a trial of void, whether intermittent self-catheterisation is possible, or whether a suprapubic catheter may be more suitable for longer-term drainage. The best choice depends on bladder function, dexterity, the underlying condition and the person’s wishes.[1, 3]

What might it feel like, and what can go wrong?

Some people notice discomfort or a sense of needing to pass urine after insertion. Bladder spasms can cause cramping or urine to leak around the tube. Leakage can also mean that the catheter is kinked or blocked, so it should be checked rather than simply treated as incontinence. Other possible problems include blood in the urine after insertion or a change, skin irritation, accidental pulling or displacement, blockage from debris or encrustation, and infection.[2, 3]

A long-term urethral catheter can also cause pressure or trauma at the urethral opening; persistent soreness or a change in its appearance deserves review. Bladder stones and repeated blockages are further reasons to reassess the drainage plan. The longer a catheter remains, the more opportunity there is for bacteria to colonise it, so it should stay in place only while needed.[3, 4]

How often should a long-term catheter be changed?

There is no single safe change interval for every catheter and every patient. The plan depends on the catheter material and manufacturer’s instructions, local nursing policy, comfort, drainage, and whether it repeatedly blocks or becomes encrusted. Some community protocols plan changes approximately every four to eight weeks, but an individual plan may differ. The interval should not exceed the relevant product’s recommended duration.[1, 3]

Changing a catheter more frequently just to prevent infection has not been shown to help. A catheter may instead need an earlier change if it is blocked, damaged, displaced, causing problems, or as part of managing a symptomatic infection. People with a history of difficult insertion, urethral injury or bleeding should have a specific plan for who can safely perform the change.[1, 3]

At each review, it is worth asking: Is the catheter still necessary? Could a trial without it or another drainage method be considered?[1]

Day-to-day care at home

Keep the drainage bag below bladder level, avoid kinks in the tubing, and secure the catheter so it does not pull. Wash your hands before and after handling the bag. Follow the nurse’s instructions for emptying it and for cleaning the area where the catheter enters the body. Ordinary hygiene is usually enough; do not disconnect the closed drainage system, flush the catheter or take preventive antibiotics unless your treating team has given a specific instruction.[3, 5]

Drink according to your usual health advice. If you have a fluid restriction for heart or kidney disease, follow that plan rather than trying to drink extra to “flush” the catheter. Ask your nurse which supplies to keep at home and whom to call after hours if drainage stops.[2]

Bacteria in urine: when are antibiotics needed?

With a catheter in place, bacteria commonly grow on the catheter surface. After a month, bacteriuria is found in nearly everyone with a long-term catheter. A positive urine culture without symptoms usually reflects colonisation, not an infection requiring antibiotics. Routine screening or treatment of asymptomatic bacteriuria is generally discouraged because antibiotics can cause side effects and encourage resistant bacteria. Exceptions include pregnancy and certain invasive urological procedures, where the treating team will advise on testing and treatment.[4, 6]

Seek clinical assessment for possible infection if you develop fever, rigors, new pelvic or flank pain, feel distinctly unwell, or have other new symptoms that could indicate infection. In a frail person, a new change in function or confusion warrants assessment of several possible causes rather than automatically assuming a UTI. Cloudy or strong-smelling urine, sediment, or a positive dipstick on its own does not usually justify antibiotics.[4, 6, 7]

When a symptomatic catheter-associated UTI is suspected, a clinician should assess you and arrange a properly collected urine specimen if indicated—not from the drainage bag. Treatment is chosen in light of symptoms, culture results, allergies and local guidance. If the catheter has been in place for more than two weeks and still needs to remain, changing it as part of treatment is commonly recommended. Routine antibiotics at every scheduled catheter change are not recommended.[7, 8]

When to get help promptly

Contact your nurse or doctor promptly if urine stops draining, the catheter falls out, you have significant pain or new bleeding, or urine is leaking around the catheter with little in the bag. Check for a kink or a full bag, but do not forcefully flush or reinsert a catheter yourself unless specifically trained and instructed. Seek urgent medical care if drainage has stopped and you have a painful or swollen lower abdomen, or if you have fever, shaking chills or feel seriously unwell.[2]

Catheter support in Bundaberg

Some people can have catheter assessment and planned changes at home through a community nursing service. Ozcare and BlueCare provide home nursing in the Bundaberg area; whether a nurse can provide catheter care for an individual depends on referral, staffing, clinical needs, service area and funding arrangements. Ask the provider directly about availability and costs before relying on a visit.[9, 10]

For my Bundaberg patients, Sandra Ilett, a continence nurse with Community Nurse Service, is another local contact for bladder and catheter-related care. Sandra and her colleague Carla Kerr have also seen patients at the nurse-led clinic at The Friendlies Medical Suites. Patients can discuss a suitable referral and whether a home visit or clinic appointment is available. Community Nurse Service: (07) 4126 2002.[11] This mention recognises local nursing support; it is not a claim that one service is preferable for every patient.

A written catheter plan should record the reason for drainage, catheter details, the planned review or change, who will provide care, and whom to call if problems arise. Community nurses, the GP and urology team can then coordinate care across visits.

This article provides general information. Follow your individual catheter plan and seek clinical advice for new symptoms or a catheter that is not draining.

References

  1. Queensland Health. Urinary catheter insertion or change: indications and review.
  2. Healthdirect Australia. Catheter problems.
  3. Queensland Spinal Cord Injuries Service. Indwelling catheters.
  4. US Centers for Disease Control and Prevention. Indwelling urinary catheter culture stewardship.
  5. US Centers for Disease Control and Prevention. CAUTI prevention: summary of recommendations.
  6. Infectious Diseases Society of America. Management of asymptomatic bacteriuria.
  7. Queensland Spinal Cord Injuries Service. Management of urinary tract infection.
  8. US Centers for Disease Control and Prevention. Catheter urine culture collection guidance.
  9. Ozcare Bundaberg: home nursing and service area.
  10. BlueCare: community nursing at home; Bundaberg community service listing.
  11. Dr Jo Schoeman. Nurse-led urology clinic in Bundaberg: Sandra Ilett and Carla Kerr.

Renal angiomyolipoma (AML): when to watch, when to treat and when to seek urgent help

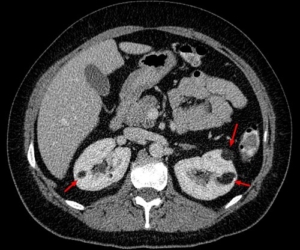
An angiomyolipoma, usually shortened to AML, is a growth in the kidney made up of blood vessels, muscle-like tissue and fat. Most are found by chance on a scan and never cause trouble. The main concern is that some AMLs can bleed, occasionally quite severely. The right plan depends on the diagnosis, the growth’s features and your circumstances, not its diameter alone. [1,2]

In this article, “AML” means angiomyolipoma, not acute myeloid leukaemia.

Is an AML cancer?

A classic renal AML is generally a benign tumour. Most occur on their own (sporadic AML). Some occur with tuberous sclerosis complex (TSC) or, less commonly, lymphangioleiomyomatosis (LAM); these can be multiple, affect both kidneys and require a different surveillance and treatment approach. A rare epithelioid AML can behave aggressively and needs specialist assessment. Not every solid renal mass presumed to be an AML can be confidently identified on a scan, particularly when little visible fat is present. [1,3,4]

What symptoms can it cause?

Many AMLs have no symptoms. Possible symptoms include aching or pain in the side, visible blood in the urine, or, less commonly, a palpable swelling. A sudden bleed into or around the kidney may cause abrupt, severe flank or abdominal pain, sometimes with dizziness, fainting, weakness or a racing heart. Blood in the urine and flank pain can also have other causes, including stones or cancer, so they should be assessed rather than attributed automatically to a known AML. [1–3]

Emergency warning: If you develop sudden severe side or abdominal pain, especially with faintness, collapse, a racing heart or visible bleeding, call 000 in Australia or attend an emergency department immediately. A bleeding AML can cause major blood loss even when blood is not visible in the urine. Do not wait for a routine appointment. [1,3]

How is it diagnosed?

An AML may first appear on an ultrasound performed for another reason. CT or MRI helps confirm whether it contains fat and assess its size, location, blood vessels and any evidence of bleeding. Contrast-enhanced imaging may be needed for an indeterminate lesion or procedural planning, with the choice adapted to kidney function, pregnancy and other factors. A classic fat-rich AML is often diagnosed on imaging alone. A fat-poor AML may resemble kidney cancer; specialist review, further imaging or a biopsy may be appropriate if the result would change management. Biopsy has limitations and is chosen case by case. [1,3,4]

The assessment may also include blood pressure, kidney function and a blood count if bleeding is suspected. Multiple or bilateral AMLs, especially in a younger person, should prompt consideration of TSC or LAM and appropriate specialist input. [3,5]

Is there a critical size that must be treated?

There is no single diameter at which every AML must be removed. The traditional rule to treat an AML once it reaches 4 cm is no longer considered an automatic trigger. The European Association of Urology (EAU) states that the relationship between size and bleeding risk is uncertain and that no universal intervention threshold exists. Some larger AMLs can still be watched safely; a smaller one may need treatment if it bleeds or causes persistent symptoms. [1,2]

Size remains one part of the discussion. The team may also consider growth, vascular features or aneurysms seen on imaging, prior bleeding, pain, kidney function, pregnancy plans, blood-thinning medicines and access to urgent care. An aneurysm measurement such as 5 mm has been proposed as a risk marker, but recent evidence questions how reliably it predicts bleeding on its own. These findings guide an individual discussion; they do not supply a stand-alone rule. [1,3,6]

Management options

Active surveillance

For a confidently diagnosed, symptom-free AML, monitoring is often appropriate. It avoids exposing people with stable lesions to procedure risks. A surveillance plan records the starting size and imaging characteristics, checks for new symptoms and uses ultrasound, MRI or CT when appropriate to look for change. There is no single imaging interval suitable for all sporadic AMLs. A small, stable lesion may need little or no ongoing imaging after specialist review; a larger or changing lesion usually needs closer follow-up. Agree on the next scan, who will review it and what changes should prompt earlier contact. [1–3]

Selective arterial embolisation

An interventional radiologist passes a catheter into the blood vessels feeding the AML and blocks selected branches. Embolisation can control active bleeding and can be considered in advance for selected higher-risk or symptomatic tumours, while preserving kidney tissue. Pain, fever and nausea can occur afterwards; infection, non-target embolisation and repeat treatment are possible. In the EAU systematic review, around 30% of embolised cases required a further intervention, although individual outcomes vary. [1,2]

Kidney-sparing surgery

A partial nephrectomy removes the AML while aiming to preserve the rest of the kidney. Open, laparoscopic or robotic approaches may be considered depending on anatomy and surgical expertise. Surgery may be useful when imaging is uncertain, symptoms persist, embolisation is unsuitable or a definitive removal is preferred. It carries anaesthetic, bleeding, urine leak and kidney-function risks. Removal of the whole kidney is generally reserved for situations where kidney-sparing care is not feasible, especially in an emergency. [1–3]

Ablation and medicines

Thermal ablation is used less often for AML, and the evidence is more limited than for surveillance, embolisation and surgery. For TSC-associated AML, specialist teams may use an mTOR inhibitor such as everolimus for an asymptomatic but growing lesion over 3 cm when treatment is appropriate. This TSC recommendation should not be applied automatically to an isolated sporadic AML. Medicines require monitoring for adverse effects and interactions. [1,2,5]

What happens if an AML bleeds?

In hospital, the immediate priorities are resuscitation, blood tests and imaging to locate the bleed. Treatment may include intravenous fluids, blood transfusion and urgent selective arterial embolisation to stop the bleeding. Surgery is considered if embolisation is unavailable, unsuccessful or otherwise unsuitable. After recovery, follow-up checks the AML, remaining kidney function and whether further treatment is needed. [1,3]

How is surveillance different with tuberous sclerosis?

TSC-related AMLs require a coordinated long-term plan because lesions may occur in both kidneys and kidney function needs protection over a lifetime. The 2021 international TSC recommendations advise abdominal MRI every 1–3 years, with blood pressure, kidney function and urine protein checked at least yearly; the interval is tailored to individual risk. Growing AMLs greater than 3 cm may merit first-line mTOR treatment when intervention is indicated, while acute bleeding is generally managed with embolisation. A TSC specialist team can help balance treatment against the need to preserve kidney tissue. [5]

Questions to bring to your appointment

  • Is the imaging diagnosis of a classic AML secure, or is more investigation needed?
  • What are its size, growth pattern and vascular features?
  • What is my personal risk of bleeding, and how does kidney function affect my options?
  • If we monitor it, when is my next scan and what result would change the plan?
  • If treatment is recommended, why is embolisation, surgery or another option best for me?

This article provides general information and does not replace individual assessment or advice.

References

  1. European Association of Urology. EAU Guidelines on Renal Cell Carcinoma, section on other renal tumours and AML. Accessed September 2026.
  2. Fernández-Pello S, et al. Management of sporadic renal angiomyolipomas: a systematic review to guide EAU recommendations. European Urology Oncology. 2020;3:57–72. doi:10.1016/j.euo.2019.04.005.
  3. Guo Y, et al. Canadian Urological Association best practice report: Diagnosis and management of sporadic angiomyolipomas. Canadian Urological Association Journal. 2020;14–E536. doi:10.5489/cuaj.6942.
  4. Wilson MP, et al. Diagnostic performance of MRI in detection of renal lipid-poor angiomyolipomas: systematic review and meta-analysis. Radiology. 2020;296:511–520.
  5. Northrup H, et al. Updated international TSC diagnostic criteria and surveillance and management recommendations. Pediatric Neurology. 2021;123:50–66. See also Tuberous Sclerosis Australia: Kidneys.
  6. Swärd J, et al. Renal angiomyolipoma: investigating radiological signs indicative of bleeding risk. Insights into Imaging. 2025.

Urethral Meatal Stenosis: Congenital, Acquired and Correct Management

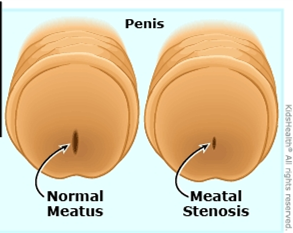
The urethral meatus is the opening through which urine leaves the body. Meatal stenosis means that this opening has become abnormally narrow and is interfering with urinary flow. It is most often discussed in boys and men, although narrowing of the female urethral opening can also occur.

An important point is that a meatus can look small without causing obstruction. Treatment should therefore be based on the complete picture, symptoms, the appearance of the opening, the urinary stream and, where appropriate, objective testing, not appearance alone.
What symptoms can it cause?

Typical symptoms include:

  • a thin, forceful or upward-deflected stream;
  • spraying or difficulty aiming the urine;
  • taking longer to pass urine or needing to strain;
  • burning or discomfort during urination;
  • a small spot of blood at the meatus;
  • urinary frequency, urgency or incomplete emptying; and
  • recurrent urinary infection in selected patients.

In toilet-trained boys, an abnormal stream is often the most useful clue. Published patient-reported data show that improvement after meatotomy is most predictable when the preoperative problem is an abnormal or deflected stream. Frequency, urgency, wetting or dysuria may have another cause and should not automatically be attributed to a narrow-looking meatus.

Complete inability to pass urine is uncommon but requires urgent medical attention.

Congenital meatal stenosis

Congenital meatal stenosis is present from birth. True isolated congenital narrowing is uncommon and should be distinguished from normal variation in meatal size. It may also occur as part of another developmental urethral condition, including hypospadias, or following congenital urethral reconstruction.

In a baby or young child, symptoms can be difficult to recognise. The diagnosis becomes more apparent after toilet training, when a persistently narrow, spraying or markedly deflected stream can be observed.

Not every anatomically small meatus needs surgery. An asymptomatic child with a satisfactory stream, no urinary infections and normal bladder emptying can often be observed. Symptomatic obstruction, however, should be assessed by a paediatric urologist.

Acquired meatal stenosis

Acquired stenosis develops after birth. Its causes vary with age.

In boys

Meatal stenosis is recognised after circumcision, although published estimates vary substantially because studies use different definitions and methods of examination. Proposed mechanisms include irritation and inflammation of the exposed meatus, contact with wet nappies, meatal ulceration and subsequent scar formation. It often becomes clinically obvious between early childhood and school age rather than immediately after circumcision.

Other causes include inflammation, trauma, catheterisation and previous surgery, particularly repair of hypospadias. Following hypospadias surgery, narrowing may involve more than the external opening and must be assessed in the context of the reconstructed urethra.

In adolescents and adults

Important causes include:

  • lichen sclerosus (also called balanitis xerotica obliterans or BXO), which can scar the foreskin, glans, meatus and more proximal urethra;
  • repeated urethral instrumentation, catheterisation or endoscopic surgery;
  • prior hypospadias repair or other penile surgery;
  • trauma, infection or chronic inflammation; and
  • previous radiotherapy or treatment affecting the urethra.

In adults, it is essential to determine whether narrowing is confined to the meatus or extends into the fossa navicularis or penile urethra. Treating only the visible opening will fail if more extensive scar disease has been overlooked.

Female meatal or urethral stenosis is uncommon. Symptoms may resemble recurrent urinary infection or other causes of bladder-outlet obstruction. Diagnosis should be made carefully, as urinary symptoms alone do not prove that the urethra is narrowed.

How is it diagnosed?

Assessment may include:

  1. A detailed history: including the direction and calibre of the stream, spraying, pain, infections, prior circumcision, catheterisation, surgery, trauma and skin disease.
  2. Examination: assessing the meatus and surrounding skin for scarring, pallor, inflammation, lichen sclerosus, hypospadias or surgical change.
  3. Observation of the urinary stream, particularly in a toilet-trained child.
  4. Uroflowmetry and post-void residual ultrasound when symptoms are unclear, the patient is older, or more extensive obstruction is suspected.
  5. Urinalysis or urine culture if pain, blood or infection is suspected.
  6. Urethral calibration, cystoscopy or urethrography selectively, especially in adults, recurrent disease, previous urethral surgery or suspected extension beyond the meatus.

Kidney and bladder ultrasound is not required for every straightforward case, but may be appropriate when there are recurrent infections, incomplete emptying, significant obstruction or concern about the upper urinary tract.

What is the correct management?

Management must match the patient’s symptoms, cause, age and extent of narrowing.

1. Observation

Observation is reasonable when the meatus is merely small in appearance but the patient has no relevant symptoms, passes a satisfactory stream and empties the bladder normally. Treating an incidental finding is unlikely to improve unrelated urgency, frequency or wetting.

2. Treat active skin or inflammatory disease

When lichen sclerosus or another inflammatory disorder is present, the underlying disease must be treated as well as the narrowing. Potent topical corticosteroid treatment is commonly used for genital lichen sclerosus under medical supervision. Circumcision may be indicated when the foreskin is affected, but established meatal or urethral scar may also require surgery.

Persistent or suspicious penile lesions may need biopsy. Long-term review can be appropriate because lichen sclerosus can recur, extend into the urethra and is associated with a small but important risk of penile malignancy.

3. Meatotomy or meatoplasty

For a short, symptomatic stenosis confined to the meatus, meatotomy or meatoplasty is usually the definitive treatment.

  • A meatotomy enlarges the opening with a controlled incision.
  • A meatoplasty reconstructs and sutures the edges to create a durable, appropriately shaped opening.

Both can provide excellent relief in appropriately selected children. A large paediatric series reported that meatotomy required more early manual spreading and had a higher reoperation rate than meatoplasty; technique and postoperative care therefore matter. In another study, 95% of families reported their child was at least somewhat improved after meatotomy, with the strongest benefit in boys treated for an abnormal stream.

The operation may be performed under local anaesthesia in selected cooperative patients or under general anaesthesia, particularly in younger children. Expected short-term effects include stinging, minor spotting of blood and temporary spraying while swelling settles. The surgeon may advise ointment and gentle separation of the meatal edges during early healing; instructions vary according to the procedure used.

4. Dilatation

Repeated blind dilatation is generally not a durable solution for dense scar-related meatal stenosis. It may cause further tearing and scarring and can commit a patient to repeated procedures. Carefully selected dilation or self-dilatation may have a role as temporary or palliative management, or as part of a specialist regimen for inflammatory disease, but it should not replace an appropriate reconstructive assessment in recurrent or complex disease.

5. Recurrent, adult or extended distal disease

If narrowing recurs, is associated with lichen sclerosus, or extends into the fossa navicularis/distal urethra, a simple repeat incision may not be sufficient. Options include formal meatoplasty or distal urethroplasty using an oral mucosal graft. The European Association of Urology recommends offering open meatoplasty or distal urethroplasty for meatal and distal urethral strictures; the precise operation should be individualised to stricture length, tissue quality and the patient’s priorities.

In lichen-sclerosus-related urethral disease, genital skin should not be used as a graft because the disease may recur in that tissue. Oral mucosa is generally preferred when graft reconstruction is required.

Follow-up and recurrence

Most patients with an isolated, properly treated meatal stenosis do well. Follow-up should assess:

  • improvement in stream direction and calibre;
  • pain, bleeding, infection or difficulty voiding;
  • bladder emptying when clinically indicated; and
  • restenosis or progression of an underlying condition such as lichen sclerosus.

Prompt reassessment is advisable if the stream narrows again, spraying persists after healing, voiding becomes painful or difficult, infections recur, or new skin changes appear.

The practical message

Meatal stenosis is not simply “a small hole.” Correct care begins by confirming that the narrowing is clinically important and identifying its cause and extent. A symptomatic, short stenosis confined to the meatus is usually treated successfully with meatotomy or meatoplasty. Recurrent stenosis, adult disease, previous hypospadias repair or lichen sclerosus requires a more detailed urethral assessment and sometimes formal reconstruction.

This article provides general educational information and does not replace an individual assessment. Seek urgent care if you or your child cannot pass urine, develops fever with urinary symptoms, or has significant bleeding or pain.

Selected references

  1. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Males. 2026. https://uroweb.org/guidelines/urethral-strictures/chapter/disease-management-in-males
  2. European Association of Urology. EAU Guidelines on Urethral Strictures: Definition, Epidemiology, Aetiology and Prevention. 2026. https://uroweb.org/guidelines/urethral-strictures/chapter/definition-epidemiology-aetiology-and-prevention
  3. Wessells H, et al. Urethral Stricture Disease Guideline Amendment (2023). Journal of Urology. 2023. doi:10.1097/JU.0000000000003482.
  4. Dothan D, et al. Surgical Treatment of Meatal Stenosis: Lessons Learned from the Pediatric Urology Practice. Urology. 2023;171:220–224. PMID: 35981660.
  5. Varda BK, et al. Minor procedure, major impact: patient-reported outcomes following urethral meatotomy. Journal of Pediatric Urology. 2018;14(2):165.e1–165.e5. doi:10.1016/j.jpurol.2017.11.018.
  6. Godley SP, et al. Meatal stenosis: a retrospective analysis of over 4000 patients. Journal of Pediatric Urology. 2015;11(1):38.e1–38.e6. doi:10.1016/j.jpurol.2014.09.016.
  7. Morris BJ, Krieger JN. Does circumcision increase meatal stenosis risk? A systematic review and meta-analysis. Urology. 2017;110:16–26. doi:10.1016/j.urology.2017.07.027.
  8. Wang MH. Surgical management of meatal stenosis with meatoplasty. Journal of Visualized Experiments. 2010;(45):2213. doi:10.3791/2213.

Prepared for patient education.

Mid-Urethral Slings for Stress Urinary Incontinence: What Is the Current Australian Position?

Patient information for Australian women | Reviewed 22 September 2026

The word “mesh” can understandably cause concern. Public discussion has often grouped together several very different products and operations. A mid-urethral sling used to treat female stress urinary incontinence is not the same operation as transvaginal mesh used to repair pelvic organ prolapse, and it is also different from a single-incision mini-sling.

The Urological Society of Australia and New Zealand (USANZ) supports the continued availability of mid-urethral slings in Australia as one treatment option for appropriately selected women. That support is not unconditional: USANZ emphasises appropriate clinical governance, surgeon credentialing, informed consent, multidisciplinary review where appropriate, and monitoring of patient outcomes.

What is stress urinary incontinence?

Stress urinary incontinence, or SUI, is leakage caused by an increase in abdominal pressure, for example when coughing, sneezing, laughing, exercising or lifting. It is different from urge incontinence, in which leakage is associated with a sudden compelling need to pass urine.

An accurate diagnosis matters. Some women have both stress and urgency symptoms, difficulty emptying the bladder, prolapse, recurrent infections or previous pelvic surgery. A consultation may therefore include a history, examination, bladder diary, urine testing, measurement of residual urine and, in selected or complex cases, urodynamic studies or cystoscopy.

What is a mid-urethral sling?

A mid-urethral sling is a narrow strip of permanent synthetic polypropylene mesh placed beneath the middle part of the urethra. It provides support during coughing, exercise and other activities that raise abdominal pressure.

The two established approaches are:

  • Retropubic sling: the tape passes behind the pubic bone.
  • Transobturator sling: the tape passes through the obturator region towards the groin.

These approaches have different risk profiles. The retropubic route has a greater risk of bladder perforation and short-term voiding difficulty, while the transobturator route has a greater association with groin or thigh pain. The most appropriate approach depends on the woman’s anatomy, previous operations, clinical circumstances and preferences.

What does USANZ say?

USANZ states that mid-urethral slings have an established evidence base for relative safety and effectiveness and should remain available in Australia for the treatment of female SUI. In its 2023 statement, USANZ specifically linked continued use to the clinical-governance improvements introduced in Australia since 2018, including:

  • appropriate surgeon credentialing
  • careful patient selection
  • discussion through multidisciplinary processes where indicated
  • genuine informed consent
  • monitoring of outcomes through the Australasian Pelvic Floor Procedure Registry.

This position supports patient choice, not routine surgery for every woman. Conservative care should usually be considered first, and non-mesh alternatives must be discussed when surgery is being considered.

What is the TGA position?

The Therapeutic Goods Administration (TGA) regulates medical devices in Australia. Surgical mesh is classified as a Class III medical device, the highest-risk classification, requiring more stringent evidence and regulatory assessment.

Following its safety reviews, the TGA removed certain transvaginal prolapse mesh products and single-incision mini-slings from routine supply. This did not amount to a ban on established retropubic and transobturator mid-urethral slings for SUI. The TGA’s current register includes eligible Class III urogynaecological mesh devices intended for SUI; the precise indication must always be checked in the device’s approved Instructions for Use.

The TGA requires manufacturers to provide patient information leaflets and implant cards for these devices. A woman receiving a sling should know the product used and should retain her implant card.

How effective is a mid-urethral sling?

Mid-urethral sling surgery is one of the most extensively studied operations for female SUI. Australian safety and quality guidance describes it as highly effective in the short and medium term, with long-term studies showing sustained patient satisfaction for many women.

No operation can guarantee a cure. Outcomes depend on the definition of success, length of follow-up, type of sling, surgeon experience and the individual patient. Stress leakage may persist or recur, and urgency symptoms may remain, improve or occasionally develop after surgery.

What are the risks?

Most women do not develop a serious complication, but complications can be significant and may occur early or years later. Potential risks include:

  • bleeding, infection and anaesthetic complications
  • temporary or persistent difficulty emptying the bladder, sometimes requiring catheterisation or further surgery
  • bladder or urethral injury
  • urinary tract infection
  • new or worsened urinary urgency or urge incontinence
  • persistent or recurrent stress incontinence
  • vaginal mesh exposure
  • mesh erosion into the urethra or bladder
  • pelvic, vaginal, groin or thigh pain
  • pain during intercourse
  • rarely, injury to major blood vessels, bowel or other pelvic structures.

Mesh is intended to remain permanently. If a mesh complication develops, partial or complete removal may be considered, but complete removal can be technically difficult or impossible and may require more than one operation. Removal may not fully resolve pain and can cause stress incontinence to recur.

Seek medical assessment if you develop persistent pelvic or groin pain, pain during intercourse, vaginal bleeding or discharge, recurrent urinary infections, difficulty passing urine, blood in the urine, or recurrent leakage after sling surgery.

What are the alternatives?

Treatment should be individualised. Options include:

  • no active treatment or the use of continence products
  • lifestyle measures, including weight management, treatment of constipation and chronic cough, and smoking cessation
  • supervised pelvic-floor muscle training, usually for at least three months
  • a continence pessary in suitable women
  • urethral bulking injections, which are less invasive but generally less durable and may need repeating
  • an autologous fascial sling using the patient’s own tissue
  • Burch colposuspension using sutures and native tissue.

Autologous fascial sling and colposuspension avoid permanent synthetic mesh but usually involve a longer operation and recovery and have their own risks, including voiding difficulty. There is no single best operation for every woman.

Shared decision-making and informed consent

Before proceeding, a woman should have enough time and balanced information to consider:

  • whether her symptoms are predominantly stress, urgency or mixed incontinence
  • conservative, mesh and non-mesh options
  • the expected benefits and limitations of each option
  • short- and long-term risks, including mesh-specific complications
  • the surgeon’s training and experience with the proposed procedure and alternatives
  • what follow-up will occur and how complications would be managed
  • the name and TGA registration status of the proposed device.

A second opinion is reasonable, particularly if symptoms are complex, previous continence surgery has failed, chronic pelvic pain is present, or the available options remain unclear.

The balanced Australian position

Mid-urethral slings are not appropriate for every woman, but neither are they prohibited in Australia. USANZ supports their continued availability for carefully selected patients within strong clinical-governance systems. The TGA continues to regulate eligible SUI sling devices as Class III medical devices and requires enhanced patient information and traceability.

The most important principles are an accurate diagnosis, consideration of conservative care, a balanced discussion of mesh and non-mesh alternatives, surgeon credentialing, informed consent and structured follow-up.

Important: This article provides general educational information and does not replace individual medical advice. It does not claim endorsement or approval by AHPRA, USANZ or the TGA. These organisations do not pre-approve individual practitioner website articles. Treatment recommendations must be based on personal assessment and shared decision-making.

References and further reading

  1. Urological Society of Australia and New Zealand. Vaginal mesh complications: USANZ submission, position statement and patient resources.
  2. Urological Society of Australia and New Zealand. USANZ supports pause on mesh stress urinary incontinence surgery in New Zealand. 23 August 2023.
  3. Therapeutic Goods Administration. Urogynaecological (transvaginal) surgical mesh hub. Updated 28 April 2025.
  4. Therapeutic Goods Administration. Australian transvaginal surgical mesh regulatory actions.
  5. Therapeutic Goods Administration. Current status of mesh products in Australia. Updated 9 June 2026.
  6. Australian Commission on Safety and Quality in Health Care. Treatment options for stress urinary incontinence: information for consumers. 2018.
  7. Australian Commission on Safety and Quality in Health Care. Care pathway for the management of stress urinary incontinence. 2018.
  8. Australian Health Practitioner Regulation Agency. Guidelines for advertising a regulated health service.
  9. Australian Health Practitioner Regulation Agency. Summary of the advertising requirements.

Why Self-Care Is Not Selfish: It’s Your Healing Tool

Making room for yourself: self-care during stressful times

Life can become so full of work, family needs and everyday responsibilities that rest starts to feel like something we have to earn. When stress or anxiety builds, even basic things—sleeping well, eating regularly, seeing a friend—can slip down the list. Making time to care for yourself is a practical way to protect your health and stay connected to what matters to you.

Self-care does not need to be expensive, time-consuming or tied to any particular belief. For one person, it might mean prayer or time with a faith community. For another, it might be quiet reflection, a walk outside, music or a conversation with a friend. There is no single right way to rest.

What does self-care actually mean?

Self-care includes ordinary habits that support physical and emotional wellbeing: enough sleep, regular meals, movement you enjoy, time with people you trust and breaks from constant demands. It can also mean setting a boundary, asking for help, attending a medical appointment or saying no when your capacity is stretched.

It is not another task to do perfectly. When you are exhausted, a small, realistic step may be more useful than an ambitious routine that adds pressure.

1. A pause can help you reset

Stress can narrow our attention to the next problem. Taking a few minutes to breathe slowly, step outdoors or notice what is happening around you can create space to respond more calmly. The World Health Organization offers short, practical exercises for coping with stress that can be used in everyday life. You might prefer stillness, meditation, prayer or simply putting your phone away while you drink a cup of tea.

Try asking yourself: What do I need in the next ten minutes? The answer might be a glass of water, a break, company or a chance to finish one manageable task.

2. Rest supports you when demands keep growing

Self-care cannot remove every source of stress, especially when caring responsibilities, financial pressure or work conditions are involved. It can, however, help you notice when the load has become too heavy. Persistent exhaustion, irritability, poor sleep or feeling detached from things you usually value are signs to slow down and seek support.

Sometimes the most helpful step is a practical change: sharing a task, taking leave, discussing workload or arranging help at home. You do not have to solve every problem by becoming better at coping with it alone.

3. Your needs matter too

People who care for others often feel guilty about taking time for themselves. Yet your need for rest, connection and support deserves attention in its own right. A quiet hour, a hobby or an appointment with a health professional is not a reward for completing everything else.

For those who draw strength from religion or spirituality, personal practices may be part of this care. Others find meaning through nature, relationships, creativity or community. Choose what feels supportive and consistent with your own values.

4. Caring for yourself can help your relationships

Rest does not guarantee patience or solve every conflict, but it may make it easier to listen, communicate and be present. It also gives others permission to be honest about their limits. Caring for yourself and caring for others can sit alongside each other.

A simple place to start

Choose one step that fits your life this week:

  • Take a short walk or spend a few minutes outdoors.
  • Keep a regular bedtime where possible.
  • Share how you are feeling with someone you trust.
  • Make space for prayer, reflection, mindfulness or quiet, if that helps you.
  • Reduce time spent on news or social media if it leaves you feeling overwhelmed.
  • Ask for help with one specific task.

If stress or anxiety persists, affects sleep or daily life, or feels difficult to manage, speak with your GP or a mental health professional. Self-care can support recovery, but it does not have to carry the whole burden of treatment. If you feel at risk of harming your

self or need immediate help in Australia, call 000 or visit the nearest emergency department. You can also contact Lifeline on 13 11 14.

This article is general wellbeing information, not a substitute for individual medical or mental health care.

Further reading

Food and urological health: what does the evidence say?

Food and drink can influence some urinary conditions, particularly recurrent kidney stones. A balanced eating pattern also supports general health. But the evidence does not support calling individual foods “urology-friendly” treatments or claiming that a berry, seed or spice will prevent urinary tract infections (UTIs), prostate enlargement or cancer. The useful advice depends on the diagnosis and the person.[1–4]


Start with the whole diet

The Australian Dietary Guidelines recommend a variety of vegetables, fruit, wholegrain foods and suitable protein foods, while limiting foods high in salt.[1] That is a more reliable starting point than a list of purported “superfoods.” People with kidney disease, recurrent stones or other medical conditions may need more specific advice from their treating team.

1. Berries and the cranberry question

Blueberries, strawberries and raspberries can be enjoyed as fruit, but evidence about cranberry products should not be extended to all berries. A Cochrane review of 50 trials found that cranberry juice, tablets or capsules probably reduce symptomatic, culture-confirmed UTIs in women with recurrent UTIs, and found benefit in some other groups. It found little or no clear benefit in several other populations. Product preparations and doses differ, and no standard effective dose has been established.[3]

Cranberry products are a possible prevention measure for selected people, not a treatment for an infection that is already present. Recurrent urinary symptoms also warrant assessment: not every episode of burning or urgency is caused by a bacterial UTI.[3]

2. Watermelon, water and kidney stones


Watermelon contributes fluid and can be part of a varied diet, but it has no special “detoxifying” action. The kidneys filter blood continuously; eating watermelon does not flush out a diagnosed infection or stone.

For many people with recurrent stones, adequate fluid intake is one of the better supported preventive measures. European Association of Urology (EAU) guidance recommends enough fluid, preferably water, to produce more than 2.5 litres of urine in 24 hours for stone prevention.[2] This is a urine output target, not an instruction for everyone to drink a fixed amount of water. Fluid needs vary with heat, activity and health conditions. People with a prescribed fluid restriction, including some with kidney or heart disease, should follow individual advice.[2, 8]

3. Leafy greens and oxalate

Vegetables are part of a healthy eating pattern. There is no reason for everyone to avoid spinach or other leafy greens. However, spinach contains substantial oxalate, which can matter for some people with calcium oxalate stones and high urinary oxalate. In that setting, limiting excessive intake of high-oxalate foods may be useful.[2]

Stone prevention is more nuanced than cutting out one vegetable. Stone composition, blood tests and sometimes a 24-hour urine collection can guide advice. EAU guidance generally discourages restricting normal dietary calcium, since adequate calcium intake can help reduce intestinal oxalate absorption; advice on supplements is different and should be individualised.[2]

4. Fish and dietary protein

fatty fish , urology food, urology brisbane,

Fish is one protein choice within the Australian Dietary Guidelines.[1] Oily fish contains omega-3 fats, but there is insufficient clinical evidence to claim that eating it treats bladder inflammation or prevents a particular urological disorder.

For some stone formers, the overall amount of animal protein may be more relevant than selecting one type of fish. Excess animal protein can change urine chemistry in ways that favour stone formation. Any change should fit the person’s nutritional needs and stone risk profile.[2]

5. Pumpkin seeds and prostate health

Pumpkin seeds can contribute nutrients, including zinc, to a varied diet. That does not mean they prevent benign prostate enlargement or prostate cancer, or replace assessment of urinary symptoms. Cancer Council Australia concludes that evidence about specific dietary factors is insufficient to recommend a food or supplement for prostate cancer prevention.[4]

“Natural” supplements are not automatically beneficial. For example, a large prevention trial found an increased prostate cancer risk in men assigned vitamin E alone, illustrating why a plausible biological theory is not enough to justify a prevention claim.[5]

6. Turmeric: food versus supplements

urogolgy food, tumeric

Turmeric is a spice; curcumin is one of its constituents. Laboratory findings about inflammation do not demonstrate that adding turmeric to meals prevents or treats urinary disease. The US National Center for Complementary and Integrative Health says there is not enough evidence to draw firm conclusions about many proposed health benefits of oral turmeric or curcumin.[6]

Concentrated supplements are different from ordinary culinary use. Some formulations designed to increase curcumin absorption have been associated with liver injury. Tell your treating clinician about supplements, particularly before an operation or when taking regular medicines.[6]

Practical steps if you have urinary symptoms

For someone with recurrent kidney stones, the strongest dietary starting points are usually appropriate fluid intake, avoiding excess salt and adjusting diet based on stone type and urine results. EAU guidance recommends a mixed diet and generally advises against restricting normal dietary calcium.[2] For someone with recurrent UTIs, the priority is to confirm the diagnosis and consider the full range of prevention options; cranberry is one possible measure for certain groups, with limits to the evidence.[3]

Diet cannot replace assessment of blood in the urine, persistent pain, fever with urinary symptoms, difficulty passing urine or repeated infections. If you have these symptoms, speak with your GP or treating clinician. Advice can then be tailored with input from a urologist or accredited practising dietitian where needed.

This is general educational information, not an individual treatment plan. No food or supplement discussed here is presented as a cure or as a substitute for appropriate medical care.

References

  1. National Health and Medical Research Council. Australian Dietary Guidelines.
  2. European Association of Urology. Guidelines on Urolithiasis: Metabolic Evaluation and Recurrence Prevention.
  3. Williams G, et al. Cranberries for preventing urinary tract infections. Cochrane Database of Systematic Reviews, 2023.
  4. Cancer Council Australia. Prostate cancer prevention.
  5. US National Cancer Institute. Selenium and Vitamin E Cancer Prevention Trial (SELECT).
  6. US National Center for Complementary and Integrative Health. Turmeric: Usefulness and Safety.
  7. Kidney Health Australia. Kidney stones.
  8. Healthdirect Australia. Drinking water and your health.