Tag Archive for: Caboolture urologist

Management Options for Benign Prostate Hyperplasia

What is BPH?

Benign Prostate Hyperplasia

(BPH) is a non-cancerous enlargement of the prostate gland that commonly affects men as they age.

As the prostate grows, it can press on the urethra and cause urinary symptoms such as:

  • Frequent or urgent need to urinate
  • Difficulty starting urination
  • Weak urine stream or dribbling
  • Getting up multiple times at night
  • Feeling the bladder hasn’t fully emptied

Watchful Waiting & Lifestyle Changes

Active Monitoring

  • Annual check-ups with your doctor
  • Symptom tracking using validated scores
  • Prostate size monitoring
  • ~79% of patients remain stable over 5 years

Lifestyle Adjustments

  • Reduce fluids before bedtime
  • Limit caffeine and alcohol
  • Avoid decongestants & antihistamines
  • Practice timed voiding
  • Stay active and maintain healthy weight

Medications

Alpha-Blockers

             Fast-acting relief
  • Relax prostate & bladder neck muscles
  • Improve urine flow within days
  • Examples: tamsulosin, alfuzosin
  • May cause dizziness or low blood pressure

5-Alpha Reductase Inhibitors

            Long-term shrinkage
  • Shrink prostate over 6-12 months
  • Best for larger prostates (>40 cc)
  • Examples: finasteride, dutasteride
  • Can be combined with alpha-blockers

PDE5 Inhibitors (Tadalafil)

          Dual benefit
  • Daily low-dose relaxes smooth muscle
  • Also treats erectile dysfunction
  • Newer AUA guidelines support combos
  • Preserves ejaculatory function

Minimally Invasive Procedures

  1. Rezum – Steam Therapy
  2. UroLift – Prostatic Lift
  3. iTIND – Temporary Implant

Surgical Options

  1. TURP
  2. HoLep
  3. Greenlight Vaporization (PVP)
  4. Robotic Simple Prostatectomy

TURP remains the traditional gold standard. HoLEP and RSP offers the best long-term durability, especially for larger prostates.

HoLEP: Lowest retreatment rate (2% at 10 years), works for all prostate sizes. GreenLight: Same-day discharge, safe on blood thinners.

Choosing the Right Treatment

Treatment depends on several individual factors. Discuss these with your doctor:

  1. Symptom severity and how much they bother you
  2. Prostate size (small, medium, or large)
  3. Whether medications have been tried already
  4. Recovery time and return-to-activity goals
  5. Sexual function priorities (ejaculation, erections)

Key Takeaways

  1. BPH is very common and not cancerous — effective treatments are available at every stage
  2. Mild symptoms often improve with simple lifestyle changes and regular monitoring
  3. Medications can significantly reduce symptoms; newer combinations offer added benefits.
  4. Minimally invasive procedures preserve sexual function with quick recovery times.
  5. Surgery provides the most durable results for larger prostates or severe symptoms.

Talk to your  urologist about which option is right for you


Urethral Meatal Stenosis: Congenital, Acquired and Correct Management

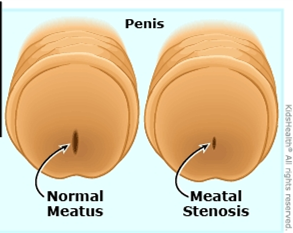
The urethral meatus is the opening through which urine leaves the body. Meatal stenosis means that this opening has become abnormally narrow and is interfering with urinary flow. It is most often discussed in boys and men, although narrowing of the female urethral opening can also occur.

An important point is that a meatus can look small without causing obstruction. Treatment should therefore be based on the complete picture, symptoms, the appearance of the opening, the urinary stream and, where appropriate, objective testing, not appearance alone.
What symptoms can it cause?

Typical symptoms include:

  • a thin, forceful or upward-deflected stream;
  • spraying or difficulty aiming the urine;
  • taking longer to pass urine or needing to strain;
  • burning or discomfort during urination;
  • a small spot of blood at the meatus;
  • urinary frequency, urgency or incomplete emptying; and
  • recurrent urinary infection in selected patients.

In toilet-trained boys, an abnormal stream is often the most useful clue. Published patient-reported data show that improvement after meatotomy is most predictable when the preoperative problem is an abnormal or deflected stream. Frequency, urgency, wetting or dysuria may have another cause and should not automatically be attributed to a narrow-looking meatus.

Complete inability to pass urine is uncommon but requires urgent medical attention.

Congenital meatal stenosis

Congenital meatal stenosis is present from birth. True isolated congenital narrowing is uncommon and should be distinguished from normal variation in meatal size. It may also occur as part of another developmental urethral condition, including hypospadias, or following congenital urethral reconstruction.

In a baby or young child, symptoms can be difficult to recognise. The diagnosis becomes more apparent after toilet training, when a persistently narrow, spraying or markedly deflected stream can be observed.

Not every anatomically small meatus needs surgery. An asymptomatic child with a satisfactory stream, no urinary infections and normal bladder emptying can often be observed. Symptomatic obstruction, however, should be assessed by a paediatric urologist.

Acquired meatal stenosis

Acquired stenosis develops after birth. Its causes vary with age.

In boys

Meatal stenosis is recognised after circumcision, although published estimates vary substantially because studies use different definitions and methods of examination. Proposed mechanisms include irritation and inflammation of the exposed meatus, contact with wet nappies, meatal ulceration and subsequent scar formation. It often becomes clinically obvious between early childhood and school age rather than immediately after circumcision.

Other causes include inflammation, trauma, catheterisation and previous surgery, particularly repair of hypospadias. Following hypospadias surgery, narrowing may involve more than the external opening and must be assessed in the context of the reconstructed urethra.

In adolescents and adults

Important causes include:

  • lichen sclerosus (also called balanitis xerotica obliterans or BXO), which can scar the foreskin, glans, meatus and more proximal urethra;
  • repeated urethral instrumentation, catheterisation or endoscopic surgery;
  • prior hypospadias repair or other penile surgery;
  • trauma, infection or chronic inflammation; and
  • previous radiotherapy or treatment affecting the urethra.

In adults, it is essential to determine whether narrowing is confined to the meatus or extends into the fossa navicularis or penile urethra. Treating only the visible opening will fail if more extensive scar disease has been overlooked.

Female meatal or urethral stenosis is uncommon. Symptoms may resemble recurrent urinary infection or other causes of bladder-outlet obstruction. Diagnosis should be made carefully, as urinary symptoms alone do not prove that the urethra is narrowed.

How is it diagnosed?

Assessment may include:

  1. A detailed history: including the direction and calibre of the stream, spraying, pain, infections, prior circumcision, catheterisation, surgery, trauma and skin disease.
  2. Examination: assessing the meatus and surrounding skin for scarring, pallor, inflammation, lichen sclerosus, hypospadias or surgical change.
  3. Observation of the urinary stream, particularly in a toilet-trained child.
  4. Uroflowmetry and post-void residual ultrasound when symptoms are unclear, the patient is older, or more extensive obstruction is suspected.
  5. Urinalysis or urine culture if pain, blood or infection is suspected.
  6. Urethral calibration, cystoscopy or urethrography selectively, especially in adults, recurrent disease, previous urethral surgery or suspected extension beyond the meatus.

Kidney and bladder ultrasound is not required for every straightforward case, but may be appropriate when there are recurrent infections, incomplete emptying, significant obstruction or concern about the upper urinary tract.

What is the correct management?

Management must match the patient’s symptoms, cause, age and extent of narrowing.

1. Observation

Observation is reasonable when the meatus is merely small in appearance but the patient has no relevant symptoms, passes a satisfactory stream and empties the bladder normally. Treating an incidental finding is unlikely to improve unrelated urgency, frequency or wetting.

2. Treat active skin or inflammatory disease

When lichen sclerosus or another inflammatory disorder is present, the underlying disease must be treated as well as the narrowing. Potent topical corticosteroid treatment is commonly used for genital lichen sclerosus under medical supervision. Circumcision may be indicated when the foreskin is affected, but established meatal or urethral scar may also require surgery.

Persistent or suspicious penile lesions may need biopsy. Long-term review can be appropriate because lichen sclerosus can recur, extend into the urethra and is associated with a small but important risk of penile malignancy.

3. Meatotomy or meatoplasty

For a short, symptomatic stenosis confined to the meatus, meatotomy or meatoplasty is usually the definitive treatment.

  • A meatotomy enlarges the opening with a controlled incision.
  • A meatoplasty reconstructs and sutures the edges to create a durable, appropriately shaped opening.

Both can provide excellent relief in appropriately selected children. A large paediatric series reported that meatotomy required more early manual spreading and had a higher reoperation rate than meatoplasty; technique and postoperative care therefore matter. In another study, 95% of families reported their child was at least somewhat improved after meatotomy, with the strongest benefit in boys treated for an abnormal stream.

The operation may be performed under local anaesthesia in selected cooperative patients or under general anaesthesia, particularly in younger children. Expected short-term effects include stinging, minor spotting of blood and temporary spraying while swelling settles. The surgeon may advise ointment and gentle separation of the meatal edges during early healing; instructions vary according to the procedure used.

4. Dilatation

Repeated blind dilatation is generally not a durable solution for dense scar-related meatal stenosis. It may cause further tearing and scarring and can commit a patient to repeated procedures. Carefully selected dilation or self-dilatation may have a role as temporary or palliative management, or as part of a specialist regimen for inflammatory disease, but it should not replace an appropriate reconstructive assessment in recurrent or complex disease.

5. Recurrent, adult or extended distal disease

If narrowing recurs, is associated with lichen sclerosus, or extends into the fossa navicularis/distal urethra, a simple repeat incision may not be sufficient. Options include formal meatoplasty or distal urethroplasty using an oral mucosal graft. The European Association of Urology recommends offering open meatoplasty or distal urethroplasty for meatal and distal urethral strictures; the precise operation should be individualised to stricture length, tissue quality and the patient’s priorities.

In lichen-sclerosus-related urethral disease, genital skin should not be used as a graft because the disease may recur in that tissue. Oral mucosa is generally preferred when graft reconstruction is required.

Follow-up and recurrence

Most patients with an isolated, properly treated meatal stenosis do well. Follow-up should assess:

  • improvement in stream direction and calibre;
  • pain, bleeding, infection or difficulty voiding;
  • bladder emptying when clinically indicated; and
  • restenosis or progression of an underlying condition such as lichen sclerosus.

Prompt reassessment is advisable if the stream narrows again, spraying persists after healing, voiding becomes painful or difficult, infections recur, or new skin changes appear.

The practical message

Meatal stenosis is not simply “a small hole.” Correct care begins by confirming that the narrowing is clinically important and identifying its cause and extent. A symptomatic, short stenosis confined to the meatus is usually treated successfully with meatotomy or meatoplasty. Recurrent stenosis, adult disease, previous hypospadias repair or lichen sclerosus requires a more detailed urethral assessment and sometimes formal reconstruction.

This article provides general educational information and does not replace an individual assessment. Seek urgent care if you or your child cannot pass urine, develops fever with urinary symptoms, or has significant bleeding or pain.

Selected references

  1. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Males. 2026. https://uroweb.org/guidelines/urethral-strictures/chapter/disease-management-in-males
  2. European Association of Urology. EAU Guidelines on Urethral Strictures: Definition, Epidemiology, Aetiology and Prevention. 2026. https://uroweb.org/guidelines/urethral-strictures/chapter/definition-epidemiology-aetiology-and-prevention
  3. Wessells H, et al. Urethral Stricture Disease Guideline Amendment (2023). Journal of Urology. 2023. doi:10.1097/JU.0000000000003482.
  4. Dothan D, et al. Surgical Treatment of Meatal Stenosis: Lessons Learned from the Pediatric Urology Practice. Urology. 2023;171:220–224. PMID: 35981660.
  5. Varda BK, et al. Minor procedure, major impact: patient-reported outcomes following urethral meatotomy. Journal of Pediatric Urology. 2018;14(2):165.e1–165.e5. doi:10.1016/j.jpurol.2017.11.018.
  6. Godley SP, et al. Meatal stenosis: a retrospective analysis of over 4000 patients. Journal of Pediatric Urology. 2015;11(1):38.e1–38.e6. doi:10.1016/j.jpurol.2014.09.016.
  7. Morris BJ, Krieger JN. Does circumcision increase meatal stenosis risk? A systematic review and meta-analysis. Urology. 2017;110:16–26. doi:10.1016/j.urology.2017.07.027.
  8. Wang MH. Surgical management of meatal stenosis with meatoplasty. Journal of Visualized Experiments. 2010;(45):2213. doi:10.3791/2213.

Prepared for patient education.

Mid-Urethral Slings for Stress Urinary Incontinence: What Is the Current Australian Position?

Patient information for Australian women | Reviewed 22 September 2026

The word “mesh” can understandably cause concern. Public discussion has often grouped together several very different products and operations. A mid-urethral sling used to treat female stress urinary incontinence is not the same operation as transvaginal mesh used to repair pelvic organ prolapse, and it is also different from a single-incision mini-sling.

The Urological Society of Australia and New Zealand (USANZ) supports the continued availability of mid-urethral slings in Australia as one treatment option for appropriately selected women. That support is not unconditional: USANZ emphasises appropriate clinical governance, surgeon credentialing, informed consent, multidisciplinary review where appropriate, and monitoring of patient outcomes.

What is stress urinary incontinence?

Stress urinary incontinence, or SUI, is leakage caused by an increase in abdominal pressure, for example when coughing, sneezing, laughing, exercising or lifting. It is different from urge incontinence, in which leakage is associated with a sudden compelling need to pass urine.

An accurate diagnosis matters. Some women have both stress and urgency symptoms, difficulty emptying the bladder, prolapse, recurrent infections or previous pelvic surgery. A consultation may therefore include a history, examination, bladder diary, urine testing, measurement of residual urine and, in selected or complex cases, urodynamic studies or cystoscopy.

What is a mid-urethral sling?

A mid-urethral sling is a narrow strip of permanent synthetic polypropylene mesh placed beneath the middle part of the urethra. It provides support during coughing, exercise and other activities that raise abdominal pressure.

The two established approaches are:

  • Retropubic sling: the tape passes behind the pubic bone.
  • Transobturator sling: the tape passes through the obturator region towards the groin.

These approaches have different risk profiles. The retropubic route has a greater risk of bladder perforation and short-term voiding difficulty, while the transobturator route has a greater association with groin or thigh pain. The most appropriate approach depends on the woman’s anatomy, previous operations, clinical circumstances and preferences.

What does USANZ say?

USANZ states that mid-urethral slings have an established evidence base for relative safety and effectiveness and should remain available in Australia for the treatment of female SUI. In its 2023 statement, USANZ specifically linked continued use to the clinical-governance improvements introduced in Australia since 2018, including:

  • appropriate surgeon credentialing
  • careful patient selection
  • discussion through multidisciplinary processes where indicated
  • genuine informed consent
  • monitoring of outcomes through the Australasian Pelvic Floor Procedure Registry.

This position supports patient choice, not routine surgery for every woman. Conservative care should usually be considered first, and non-mesh alternatives must be discussed when surgery is being considered.

What is the TGA position?

The Therapeutic Goods Administration (TGA) regulates medical devices in Australia. Surgical mesh is classified as a Class III medical device, the highest-risk classification, requiring more stringent evidence and regulatory assessment.

Following its safety reviews, the TGA removed certain transvaginal prolapse mesh products and single-incision mini-slings from routine supply. This did not amount to a ban on established retropubic and transobturator mid-urethral slings for SUI. The TGA’s current register includes eligible Class III urogynaecological mesh devices intended for SUI; the precise indication must always be checked in the device’s approved Instructions for Use.

The TGA requires manufacturers to provide patient information leaflets and implant cards for these devices. A woman receiving a sling should know the product used and should retain her implant card.

How effective is a mid-urethral sling?

Mid-urethral sling surgery is one of the most extensively studied operations for female SUI. Australian safety and quality guidance describes it as highly effective in the short and medium term, with long-term studies showing sustained patient satisfaction for many women.

No operation can guarantee a cure. Outcomes depend on the definition of success, length of follow-up, type of sling, surgeon experience and the individual patient. Stress leakage may persist or recur, and urgency symptoms may remain, improve or occasionally develop after surgery.

What are the risks?

Most women do not develop a serious complication, but complications can be significant and may occur early or years later. Potential risks include:

  • bleeding, infection and anaesthetic complications
  • temporary or persistent difficulty emptying the bladder, sometimes requiring catheterisation or further surgery
  • bladder or urethral injury
  • urinary tract infection
  • new or worsened urinary urgency or urge incontinence
  • persistent or recurrent stress incontinence
  • vaginal mesh exposure
  • mesh erosion into the urethra or bladder
  • pelvic, vaginal, groin or thigh pain
  • pain during intercourse
  • rarely, injury to major blood vessels, bowel or other pelvic structures.

Mesh is intended to remain permanently. If a mesh complication develops, partial or complete removal may be considered, but complete removal can be technically difficult or impossible and may require more than one operation. Removal may not fully resolve pain and can cause stress incontinence to recur.

Seek medical assessment if you develop persistent pelvic or groin pain, pain during intercourse, vaginal bleeding or discharge, recurrent urinary infections, difficulty passing urine, blood in the urine, or recurrent leakage after sling surgery.

What are the alternatives?

Treatment should be individualised. Options include:

  • no active treatment or the use of continence products
  • lifestyle measures, including weight management, treatment of constipation and chronic cough, and smoking cessation
  • supervised pelvic-floor muscle training, usually for at least three months
  • a continence pessary in suitable women
  • urethral bulking injections, which are less invasive but generally less durable and may need repeating
  • an autologous fascial sling using the patient’s own tissue
  • Burch colposuspension using sutures and native tissue.

Autologous fascial sling and colposuspension avoid permanent synthetic mesh but usually involve a longer operation and recovery and have their own risks, including voiding difficulty. There is no single best operation for every woman.

Shared decision-making and informed consent

Before proceeding, a woman should have enough time and balanced information to consider:

  • whether her symptoms are predominantly stress, urgency or mixed incontinence
  • conservative, mesh and non-mesh options
  • the expected benefits and limitations of each option
  • short- and long-term risks, including mesh-specific complications
  • the surgeon’s training and experience with the proposed procedure and alternatives
  • what follow-up will occur and how complications would be managed
  • the name and TGA registration status of the proposed device.

A second opinion is reasonable, particularly if symptoms are complex, previous continence surgery has failed, chronic pelvic pain is present, or the available options remain unclear.

The balanced Australian position

Mid-urethral slings are not appropriate for every woman, but neither are they prohibited in Australia. USANZ supports their continued availability for carefully selected patients within strong clinical-governance systems. The TGA continues to regulate eligible SUI sling devices as Class III medical devices and requires enhanced patient information and traceability.

The most important principles are an accurate diagnosis, consideration of conservative care, a balanced discussion of mesh and non-mesh alternatives, surgeon credentialing, informed consent and structured follow-up.

Important: This article provides general educational information and does not replace individual medical advice. It does not claim endorsement or approval by AHPRA, USANZ or the TGA. These organisations do not pre-approve individual practitioner website articles. Treatment recommendations must be based on personal assessment and shared decision-making.

References and further reading

  1. Urological Society of Australia and New Zealand. Vaginal mesh complications: USANZ submission, position statement and patient resources.
  2. Urological Society of Australia and New Zealand. USANZ supports pause on mesh stress urinary incontinence surgery in New Zealand. 23 August 2023.
  3. Therapeutic Goods Administration. Urogynaecological (transvaginal) surgical mesh hub. Updated 28 April 2025.
  4. Therapeutic Goods Administration. Australian transvaginal surgical mesh regulatory actions.
  5. Therapeutic Goods Administration. Current status of mesh products in Australia. Updated 9 June 2026.
  6. Australian Commission on Safety and Quality in Health Care. Treatment options for stress urinary incontinence: information for consumers. 2018.
  7. Australian Commission on Safety and Quality in Health Care. Care pathway for the management of stress urinary incontinence. 2018.
  8. Australian Health Practitioner Regulation Agency. Guidelines for advertising a regulated health service.
  9. Australian Health Practitioner Regulation Agency. Summary of the advertising requirements.