
Tag Archive for: urology brisbane

Prostate Abscess: A Rare but Serious Infection

A prostate abscess is a collection of pus within the prostate gland. It usually develops as a complication of acute bacterial prostatitis when infection progresses despite treatment or when treatment has been delayed.

Prostate abscesses are uncommon, but they can become life-threatening if the infection spreads into the bloodstream. Early diagnosis, intravenous antibiotics and, when necessary, drainage of the abscess are essential.

What causes a prostate abscess?

Most prostate abscesses develop when bacteria enter the prostate from the urinary tract. The infection may begin in the bladder or urethra and travel backwards through the prostatic ducts.

Common bacteria include:

  • Escherichia coli
  • Klebsiella species
  • Pseudomonas species
  • Proteus species
  • Enterococcus species
  • Staphylococcus aureus, including resistant strains such as MRSA

Less commonly, bacteria reach the prostate through the bloodstream from an infection elsewhere in the body. Fungal and tuberculosis-related abscesses are rare but may occur in people with significant immune suppression.

Who is at increased risk?

A prostate abscess is more likely to develop in men with:

  • Diabetes, particularly when blood glucose is poorly controlled
  • A weakened immune system
  • Long-term corticosteroid or immunosuppressive treatment
  • HIV or another significant immune disorder
  • Difficulty emptying the bladder
  • Benign prostate enlargement
  • A urethral stricture
  • A long-term urinary catheter
  • Recent urinary tract instrumentation
  • Recent prostate biopsy or prostate surgery
  • Recurrent urinary tract infections
  • Chronic kidney disease or dialysis
  • Intravenous drug use
  • Acute bacterial prostatitis that is not improving with appropriate antibiotics

Diabetes is one of the most frequently identified risk factors. High blood glucose can impair the immune response and make infection more difficult to control.

How does a prostate abscess present?

The symptoms often resemble acute prostatitis or a severe urinary tract infection. A man may experience:

  • Fever, chills or shaking
  • Pain or burning when passing urine
  • Frequent or urgent urination
  • Difficulty starting or maintaining the urinary stream
  • Inability to pass urine
  • Pain in the pelvis, perineum, groin or lower back
  • Painful ejaculation
  • Blood in the urine
  • Cloudy or unpleasant-smelling urine
  • General weakness, nausea or confusion

On examination, the prostate may be enlarged, tender or feel unusually soft or fluctuant. However, the absence of a typical prostate examination does not exclude an abscess.

Forceful prostate massage should be avoided in someone with acute prostatitis or a suspected abscess because it may push bacteria into the bloodstream.

When should a prostate abscess be suspected?

A prostate abscess should be considered when a patient with acute prostatitis:

  • Remains febrile after approximately 48–72 hours of appropriate antibiotics
  • Becomes more unwell despite treatment
  • Develops urinary retention
  • Has persistent pelvic or perineal pain
  • Has recurrent infection with the same organism
  • Has diabetes, immune suppression or another major risk factor

Symptoms alone cannot reliably distinguish an abscess from uncomplicated prostatitis. Imaging is usually needed to confirm the diagnosis.

How is it diagnosed?

Initial investigations may include:

  • Urine microscopy and culture
  • Blood cultures, preferably before antibiotics when this does not delay treatment
  • Full blood count
  • Kidney function and electrolyte tests
  • Inflammatory markers
  • Blood glucose testing
  • Blood lactate and other sepsis investigations when the patient is seriously unwell

Imaging may be performed using:

Transrectal ultrasound

Transrectal ultrasound can demonstrate one or more fluid-filled cavities within the prostate. It can also be used to guide needle drainage.

CT scan

A CT scan of the pelvis is particularly useful when the patient is very unwell or when infection may have spread beyond the prostate. It can also identify urinary obstruction, stones or another source of infection.

MRI

MRI provides detailed images of the prostate and surrounding tissues. It may be helpful when ultrasound or CT findings are unclear, but it is not always the most practical first investigation in an emergency.

Is a prostate abscess an emergency?

A prostate abscess can lead to bloodstream infection, sepsis and septic shock. Patients with fever, shaking chills, confusion, low blood pressure, rapid breathing, severe weakness or inability to pass urine require urgent hospital assessment.

Emergency management may involve:

  • Immediate assessment for sepsis
  • Blood and urine cultures
  • Intravenous fluids
  • Prompt intravenous antibiotics
  • Pain relief
  • Monitoring of blood pressure, urine output and kidney function
  • Treatment of uncontrolled diabetes
  • Urgent urinary drainage if the bladder cannot empty
  • Early consultation with a urologist and, when appropriate, an infectious diseases physician

Antibiotics should not be delayed in a patient who is septic while waiting for scans or culture results.

If urinary retention is present, bladder drainage is required. A urethral catheter may sometimes be used carefully, but a suprapubic catheter inserted through the lower abdomen may be preferred when urethral catheterisation is difficult or likely to cause significant prostate irritation. The best approach depends on the patient’s condition and anatomy.

Treatment with antibiotics

All prostate abscesses require antibiotic treatment.

A patient who is systemically unwell will usually begin treatment with broad-spectrum intravenous antibiotics. The initial antibiotic choice depends on:

  • The likely source of infection
  • Local bacterial resistance patterns
  • Previous urine culture results
  • Recent hospital admission or antibiotic exposure
  • Recent catheterisation or urinary surgery
  • Kidney function
  • Drug allergies
  • The possibility of resistant bacteria or Staphylococcus aureus

Once culture results become available, treatment can be narrowed to an antibiotic that targets the identified organism and penetrates prostate tissue effectively.

After clear clinical improvement, intravenous treatment may be changed to an appropriate oral antibiotic. Treatment is usually longer than for a simple bladder infection and commonly continues for several weeks. The exact duration depends on the organism, abscess size, success of drainage, immune status and response to treatment.

Follow-up urine cultures and repeat imaging may be required to confirm that the infection and abscess have resolved.

Can antibiotics alone cure a prostate abscess?

Occasionally, a small abscess in a clinically stable patient can be treated with antibiotics and close observation. This is more likely to succeed when the collection is small, often less than approximately 1 cm, and drains naturally into the prostatic ducts.

There is no single size threshold that applies to every patient. Larger, multiloculated or persistent abscesses are less likely to resolve with antibiotics alone.

Drainage should be considered when:

  • The patient is septic or clinically deteriorating
  • Fever persists despite appropriate antibiotics
  • The abscess is relatively large
  • There are several abscess cavities
  • The abscess is not shrinking on repeat imaging
  • Urinary obstruction is present
  • The infecting organism is difficult to eradicate
  • The patient has diabetes or significant immune suppression
  • The infection repeatedly returns

Current European guidance recognises that both conservative treatment and drainage may be appropriate in selected patients, with abscess size and clinical response helping to guide the decision. EAU Guidelines on Urological Infections

How is a prostate abscess drained?

Several drainage techniques are available. The method chosen depends on the size and position of the abscess, whether it has multiple compartments, the patient’s condition and local expertise.

Transrectal ultrasound-guided aspiration

A needle is passed through the rectum into the abscess under ultrasound guidance, and the pus is aspirated.

Advantages include:

  • Minimally invasive treatment
  • Usually limited anaesthesia
  • Collection of pus for culture

However, the abscess may refill, particularly if it is large, thick-walled or divided into several compartments. Repeat aspiration may be needed.

Transperineal drainage

A needle or drain is inserted through the skin between the scrotum and anus under ultrasound or imaging guidance.

This approach avoids passing through the rectal wall and may allow a drainage catheter to remain temporarily. It can be useful for appropriately positioned abscesses or when repeated drainage is anticipated.

Transurethral drainage

A telescope is passed through the urethra, and the abscess cavity is opened internally so that it can drain into the urinary channel. This may be performed by incision, deroofing or limited resection of the involved prostate tissue.

Transurethral drainage is often considered when:

  • The abscess is large
  • There are multiple or deep cavities
  • Needle aspiration has failed
  • The abscess has recurred
  • Prostate enlargement is contributing to obstruction
  • Rapid and complete drainage is required

Possible complications include bleeding, urinary infection, temporary worsening of urinary symptoms, retrograde ejaculation, urethral stricture and, less commonly, urinary incontinence or injury to surrounding structures.

Open or laparoscopic surgery

Open, laparoscopic or robotic drainage is rarely required. It may be considered if the abscess extends outside the prostate, cannot be reached by less invasive methods or is associated with another condition requiring surgery.

Antibiotics plus effective drainage remain the central principles of treatment. Management of prostate abscess in the absence of guidelines and MSD Manual: Prostate Abscess

What happens after drainage?

The drained fluid is sent for microbiological testing. This is important because the organism within the abscess may differ from that found in the urine.

Following drainage, the patient usually continues antibiotics. Clinical improvement is monitored by checking:

  • Temperature and general wellbeing
  • Pain and urinary symptoms
  • White blood cell count and inflammatory markers
  • Kidney function
  • Blood glucose in patients with diabetes
  • Urine and blood culture results
  • Follow-up ultrasound, CT or MRI when indicated

Any contributing problem, such as bladder obstruction, a urethral stricture, a catheter or poorly controlled diabetes, should also be addressed to reduce the risk of recurrence.

What is the outlook?

With early recognition, appropriate antibiotics and adequate drainage, most prostate abscesses can be successfully treated.

Delayed treatment may result in:

  • Sepsis or septic shock
  • Spread of infection beyond the prostate
  • Fistula formation into nearby structures
  • Recurrent urinary infection
  • Chronic pelvic discomfort
  • Prolonged difficulty passing urine
  • Rarely, death from overwhelming infection

A prostate abscess should therefore be regarded as a potentially serious complication of prostatitis rather than an ordinary urinary infection.

When should you seek urgent medical attention?

Attend an emergency department urgently if you develop:

  • Fever or shaking chills with urinary symptoms
  • Confusion, faintness or severe weakness
  • Inability to pass urine
  • Severe pelvic or perineal pain
  • Rapid breathing or a racing heartbeat
  • Persistent fever despite antibiotics
  • Worsening symptoms after treatment for prostatitis

Early assessment is particularly important for men with diabetes, immune suppression, a urinary catheter or recent urinary tract surgery.

This information is intended for general education and does not replace individual medical assessment. A suspected prostate abscess requires urgent assessment by a medical practitioner and usually early involvement of a urologist.

So, if this is happening to you, attend your local Emergency Department ASAP, or if you are still OK, ask your GP for an urgent referral to see your local Brisbane Urologist Dr Jo Schoeman ASAP

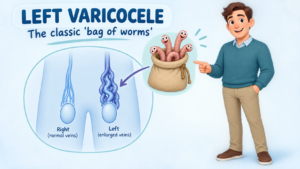
‘Bag-of-Worms” Varicocele: Causes, Symptoms, Fertility and Treatment Options

A varicocele is an enlargement of the veins surrounding the testicle. It is similar to a varicose vein in the leg, although it occurs within the scrotum.

Varicoceles are common and often harmless. However, in some men they may cause discomfort, reduce the size or function of the affected testicle, or contribute to fertility problems. Most varicoceles do not require treatment, and the decision to intervene depends on symptoms, testicular development, semen quality and plans for future fertility.

What causes a varicocele?

Blood leaves each testicle through a network of small veins called the pampiniform plexus. These veins normally carry blood upwards towards larger veins in the abdomen.

A varicocele develops when blood pools within these veins. This is usually related to poorly functioning venous valves, together with the anatomy and pressure within the testicular veins.

Around 80–90% of clinically detected varicoceles occur on the left side. This is because the left testicular vein is longer and enters the left renal vein at a right angle, making venous drainage less efficient. A varicocele may occur on both sides, while an isolated right-sided varicocele is much less common.

Most varicoceles develop gradually during puberty and have no dangerous underlying cause.

A new varicocele in an older man, particularly one that is right-sided, develops suddenly or does not disappear when lying down, may require abdominal imaging to exclude obstruction of the vein by an abdominal or retroperitoneal condition. This is uncommon but important to recognise.

How common are varicoceles?

A varicocele is found in approximately 15% of adolescent and adult men. Many men never know that they have one.

Varicoceles are more frequently identified among men being investigated for infertility. They may be present in approximately:

  • 35–40% of men with primary infertility
  • Up to 70–80% of men with secondary infertility, where a previous pregnancy has occurred, but the couple is now having difficulty conceiving

Importantly, most men with a varicocele remain fertile. Finding a varicocele does not automatically mean that it is causing infertility.

What are the symptoms?

Many varicoceles cause no symptoms and are discovered during a routine examination, fertility assessment or scrotal ultrasound.

When symptoms occur, they may include:

  • A dull ache, dragging sensation or heaviness in the scrotum
  • Discomfort that becomes worse after standing, exercising or later in the day
  • Improvement in discomfort when lying down
  • Visible or enlarged veins above the testicle
  • A soft swelling sometimes described as feeling like a “bag of worms”
  • Reduced size or slower growth of the affected testicle
  • Abnormal semen-analysis results
  • Difficulty conceiving with a partner

A varicocele generally does not cause erectile dysfunction or difficulty urinating. Its relationship with testosterone production remains under investigation, although some men with a clinically significant varicocele may have impaired testicular function.

Sudden severe testicular pain is not typical of a varicocele and requires urgent medical assessment to exclude testicular torsion or another acute scrotal condition. An abdominal ultrasound is also required to exclude a possible lesion in the abdomen obstructing the veins.

How is a varicocele diagnosed?

Diagnosis usually begins with a physical examination. The scrotum is examined while the patient is standing and lying down. You may be asked to take a breath and gently bear down, the Valsalva manoeuvre, to make enlarged veins easier to feel.

Clinical varicoceles are commonly graded as:

  • Grade 1: Felt only during the Valsalva manoeuvre
  • Grade 2: Felt while standing without straining
  • Grade 3: Easily visible through the scrotal skin

A scrotal ultrasound may be recommended if the examination is uncertain, the testicles differ in size, pain is present, or another scrotal problem needs to be excluded. Ultrasound can measure the veins, assess backward blood flow and examine the testicles.

For fertility assessment, investigations may include:

  • One or more semen analyses
  • Testicular volume measurement
  • Hormone tests when indicated
  • Assessment of both partners, because fertility is a shared consideration

An ultrasound-only or “subclinical” varicocele that cannot be felt on examination is not usually treated for infertility.

How can a varicocele affect fertility?

The testicles work best at a temperature slightly below core body temperature. The pampiniform veins help cool the arterial blood entering the testicle.

Pooling of warm blood in a varicocele may interfere with this cooling system. Increased temperature, venous pressure, oxidative stress and altered blood flow may affect sperm production and testicular function.

Possible semen changes include:

  • Reduced sperm concentration
  • Reduced sperm movement or motility
  • Increased abnormal sperm forms
  • Increased sperm DNA damage

The degree of impact varies considerably. A large varicocele can be associated with normal fertility, while a smaller palpable varicocele may be significant in another man. The diagnosis must therefore be interpreted together with semen results, the couple’s fertility history, the female partner’s age and other fertility factors.

Does every varicocele require treatment?

No. Observation is appropriate when a varicocele:

  • Causes no troublesome symptoms
  • Is not affecting testicular growth
  • Is associated with normal semen parameters
  • Is found incidentally on ultrasound but cannot be felt
  • Is unlikely to be the main cause of the couple’s fertility difficulty

Simple measures such as supportive underwear, avoiding activities that consistently aggravate discomfort and occasional appropriate pain relief may help mild symptoms. Regular review may be recommended for adolescents with a difference in testicular size.

When should treatment be considered?

Treatment may be considered when there is:

Infertility with abnormal semen parameters

Repair is most likely to benefit a couple when the man has:

  • A varicocele that can be felt on examination
  • Difficulty conceiving
  • One or more abnormal semen parameters
  • No better explanation for the infertility
  • A reasonable opportunity for natural conception following treatment

Both the AUA/ASRM and European guidance support considering repair in men attempting conception who have a palpable varicocele and abnormal semen parameters. Treatment is not routinely recommended for a varicocele detected only by ultrasound. AUA/ASRM male infertility guideline and EAU male infertility guideline

Persistent scrotal pain

Repair may be reasonable when typical varicocele-related discomfort persists despite conservative measures and other causes of scrotal pain have been excluded.

Reduced testicular growth in an adolescent

Treatment may be discussed if the affected testicle is persistently smaller, growth is impaired, the varicocele is large or semen parameters are abnormal in an appropriately selected older adolescent.

Progressive testicular dysfunction

Selected men with deteriorating semen quality or evidence of impaired testicular function may benefit from repair after individual assessment.

What treatment procedures are available?

Treatment works by blocking or dividing the abnormal veins. Blood then returns through healthy alternative veins while the testicular artery and lymphatic drainage are preserved.

Management option How it is performed Advantages Disadvantages and risks
Observation Clinical review, with semen analysis or testicular measurements when appropriate No procedure or anaesthetic; suitable for most asymptomatic men; avoids unnecessary treatment Does not correct the varicocele; symptoms or testicular changes may require future review
Conservative symptom management Scrotal support, activity modification and appropriate pain relief Simple and non-invasive; may adequately control mild discomfort Does not remove the varicocele or improve abnormal semen parameters; long-term anti-inflammatory medication may not be suitable for everyone
Microsurgical subinguinal varicocelectomy A small incision is made near the groin. An operating microscope helps identify and divide abnormal veins while protecting the testicular artery and lymphatics Usually the lowest recurrence and hydrocele rates; no abdominal incision; effective for unilateral or bilateral disease; commonly preferred for fertility treatment Requires an anaesthetic and microsurgical expertise; temporary bruising, swelling or discomfort; uncommon risks include infection, recurrence, hydrocele or testicular artery injury
Microsurgical inguinal varicocelectomy Similar microsurgical repair through a slightly higher groin incision Good visualisation and low recurrence when performed microsurgically Requires opening the external oblique fascia; recovery may involve slightly more groin discomfort
Laparoscopic varicocelectomy Veins are clipped or divided through small abdominal keyhole incisions Both sides can be treated during the same procedure; useful in selected cases General anaesthetic; entry into the abdomen; generally higher hydrocele risk than lymphatic-sparing microsurgery; rare abdominal or vascular complications
Open high ligation The testicular vein is divided through an abdominal or groin incision without microsurgical magnification Established technique; may be effective where microsurgery is unavailable Higher recurrence and hydrocele rates than modern microsurgical repair; less precise preservation of small arteries and lymphatics
Radiological embolisation or sclerotherapy An interventional radiologist passes a catheter into the testicular vein and blocks it using coils, plugs or a sclerosant No surgical incision in the scrotum or groin; often performed with local anaesthesia or sedation; relatively quick recovery; useful for recurrence after surgery The vein cannot always be accessed; radiation and contrast exposure; recurrence or persistence may occur; coils can rarely migrate; availability depends on local expertise

How effective is treatment?

The results depend on why treatment is being performed, the technique used and whether other fertility or pain-related factors are present.

Improvement in semen quality

Following repair of a clinically significant varicocele, approximately 60–80% of appropriately selected men demonstrate improvement in at least one semen parameter. Improvement is not guaranteed, and some men show little or no measurable change.

Because sperm production takes approximately three months, semen analysis is usually repeated about three months after treatment and may be reassessed again at six months.

Pregnancy and fertility outcomes

Varicocele repair may increase the chance of natural pregnancy in selected infertile couples, but it does not guarantee conception. Studies commonly report spontaneous pregnancy in roughly 25–40% of couples after repair, although rates vary substantially according to female partner factors, duration of infertility, baseline semen quality and study design.

Treatment may also improve semen quality sufficiently to allow a couple to use a less invasive assisted-reproduction option. In other cases, IVF or intracytoplasmic sperm injection may still be required.

The couple’s overall fertility timeline is important. If the female partner has reduced ovarian reserve or advancing reproductive age, waiting several months for semen improvement may not be appropriate. Varicocele repair and assisted reproductive treatment should therefore be considered as part of a shared plan.

Relief of pain

When pain is typical of a varicocele, a dull ache or heaviness made worse by standing or activity, approximately 70–90% of appropriately selected men experience meaningful improvement after repair.

Surgery is less predictable when pain is sharp, constant or atypical, and pain may occasionally persist despite technically successful treatment.

Testicular growth

In adolescents with a persistently smaller affected testicle, repair may allow “catch-up” growth. Decisions should be based on repeated measurements rather than a single ultrasound result.

What are the possible complications?

Varicocele procedures are generally safe, but potential complications include:

  • Bruising, swelling or wound discomfort
  • Infection or bleeding
  • Persistence or recurrence of the varicocele
  • Hydrocele, caused by fluid collecting around the testicle
  • Ongoing or occasionally altered scrotal pain
  • Injury to the testicular artery, which is uncommon but potentially serious
  • Testicular shrinkage, which is rare
  • Anaesthetic complications
  • Technical failure, contrast reaction, radiation exposure or coil-related problems following embolisation

Using microsurgical magnification and preserving the lymphatic vessels usually reduces the risks of recurrence, hydrocele and arterial injury.

Recovery after varicocele repair

Most men return home on the day of treatment. Bruising, mild swelling and groin or scrotal discomfort are expected during the early recovery period.

Patients are commonly advised to:

  • Wear supportive underwear
  • Keep the wound clean and dry
  • Avoid heavy lifting and strenuous exercise for the period advised by the surgeon
  • Resume sexual activity when comfortable and medically cleared
  • Attend follow-up to assess healing and symptom improvement
  • Repeat semen analysis after approximately three months when fertility is the reason for treatment

Specific recovery instructions vary according to the procedure and the individual patient.

When should you seek medical advice?

Arrange a medical assessment if you notice:

  • A new lump or swelling in the scrotum
  • Persistent scrotal discomfort or heaviness
  • A difference in testicular size
  • Difficulty conceiving
  • A new right-sided varicocele
  • A swelling that remains when lying down

Seek urgent medical attention for sudden severe testicular pain, rapid swelling, nausea or a high-riding testicle. These features may indicate testicular torsion, which is an emergency.

The bottom line

A varicocele is common and, for most men, causes no significant harm. Treatment is not based on the ultrasound appearance alone. The most important considerations are symptoms, testicular development, semen quality and the couple’s overall fertility situation.

For men with persistent typical pain, impaired testicular growth or a palpable varicocele associated with infertility and abnormal semen parameters, treatment can be worthwhile. Microsurgical varicocelectomy generally offers the most favourable balance between effectiveness, recurrence and complication risk, while embolisation is an effective minimally invasive alternative in selected patients.

A consultation with a urologist allows the varicocele—and the patient rather than simply the scan—to be assessed before deciding whether observation, surgery or embolisation is the most appropriate approach.

This article provides general information and does not replace an individual medical assessment. Treatment recommendations depend on examination findings, semen results, symptoms, age and the fertility circumstances of both partners.

So, if this is something that you have found on your regular scrotal examinations, and you have concerns, come see your Brisbane urologist, Dr Jo Schoeman for advice.

Conservative Management of a Distal Ureteric Stone: When Can You Wait and When Is Surgery Needed?

A distal ureteric calculus is a stone located in the lower part of the ureter—the tube carrying urine from the kidney to the bladder. These stones are often close to the ureterovesical junction, where the ureter enters the bladder.

As the stone moves towards the bladder, it can cause severe intermittent pain known as renal colic. Pain commonly begins in the side or back and travels into the lower abdomen, groin, testicle or labia. Blood in the urine, nausea, vomiting, urinary urgency and frequency may also occur.

Many small distal ureteric stones pass naturally. However, conservative management is only safe when pain is controlled, infection is absent, kidney function is satisfactory and appropriate follow-up is arranged.

When is a ureteric stone an emergency?

A stone obstructing an infected kidney is a urological emergency. Antibiotics alone may be insufficient because infected urine cannot drain normally.

Seek urgent medical assessment if stone symptoms are accompanied by:

  • Fever or shaking chills
  • Feeling severely unwell, weak, confused or drowsy
  • Persistent vomiting or inability to drink
  • Pain that remains severe despite medication
  • Passing very little or no urine
  • Known poor kidney function
  • A solitary functioning kidney
  • Pregnancy with significant pain or fever

The obstructed kidney may need urgent drainage with a ureteric stent or nephrostomy tube. Definitive stone treatment is usually delayed until the infection has been controlled. The European Association of Urology recommends immediate antibiotics and urgent drainage for sepsis associated with an obstructing stone. EAU Guidelines on Urolithiasis

Australian Healthdirect similarly advises patients with renal colic and fever to attend a doctor or hospital emergency department promptly. Healthdirect Australia—Kidney stones

What determines whether a stone will pass naturally?

The likelihood of spontaneous passage depends mainly on:

  • Stone size
  • Position within the ureter
  • Degree of obstruction
  • Ureteric anatomy
  • Whether the stone is impacted
  • Previous stone history
  • Associated swelling and inflammation
  • The duration for which the stone has remained in the same position

Smaller stones located close to the bladder have the greatest likelihood of passing.

The EAU reports that distal ureteric stones collectively have a spontaneous passage rate of approximately 68–83%. A distal ureteric stone smaller than 5 mm has an estimated passage rate of approximately 89%. The likelihood decreases as stone size increases.

These percentages describe groups of patients and cannot predict exactly what will happen to an individual stone. A 4 mm stone may occasionally become impacted, while a larger stone may sometimes pass without surgery.

The average reported passage time is approximately 17 days, although passage can occur sooner or take several weeks. EAU Guidelines on Urolithiasis

Who may be suitable for conservative management?

Conservative management, also called observation, expectant management or a trial of passage, may be appropriate when:

  • The stone is small enough to have a reasonable chance of passing
  • The stone is in the distal ureter
  • Pain can be controlled with oral medication
  • There is no fever or evidence of urinary infection
  • Kidney function is stable
  • The patient can drink and keep medication down
  • There is no complete obstruction threatening kidney function
  • The patient is passing urine normally
  • There is no high-risk situation involving a solitary kidney or bilateral obstruction
  • The patient understands the warning symptoms
  • Follow-up and repeat imaging can be arranged
  • The patient is comfortable waiting for the stone to pass

Stones of 5 mm or less are particularly suitable for observation when no complications are present.

Selected distal stones between 5 and 10 mm may also be managed conservatively. These stones are less likely to pass than smaller stones, but some patients may avoid surgery with careful observation and medical expulsive therapy.

Stones larger than 10 mm are substantially less likely to pass naturally and are more commonly treated with an intervention.

What assessment is required?

Before recommending conservative management, the diagnosis and severity of obstruction should be established.

Assessment may include:

  • A detailed history and physical examination
  • Urine dipstick testing
  • Urine culture when infection is suspected
  • Kidney-function blood tests
  • Full blood count and inflammatory markers
  • Non-contrast CT scan of the kidneys, ureters and bladder
  • Ultrasound in selected patients
  • A plain abdominal X-ray when the stone is visible on X-ray
  • Pregnancy testing when clinically relevant

A low-dose non-contrast CT scan is often the most accurate test for determining the stone’s size and location. It can also assess hydronephrosis, the swelling of the kidney caused by obstruction and identify alternative causes of pain.

Ultrasound is particularly useful when radiation should be avoided, including during pregnancy, although it may not show every ureteric stone.

What does conservative management involve?

Pain relief

Non-steroidal anti-inflammatory medicines, NSAIDs, are often the most effective initial treatment for renal colic when they are medically safe.

Depending on the patient, treatment may include:

  • Ibuprofen
  • Diclofenac
  • Paracetamol
  • A prescribed opioid for breakthrough pain
  • Medication for nausea or vomiting

NSAIDs may be unsuitable for people with:

  • Reduced kidney function
  • Previous stomach ulcers or gastrointestinal bleeding
  • Certain cardiovascular conditions
  • Anticoagulant treatment
  • NSAID allergy
  • Some stages of pregnancy

Pain medication should be selected according to the patient’s medical history rather than taken indiscriminately.

Hydration

Patients should generally remain normally hydrated and avoid becoming dehydrated.

Drinking excessive volumes of water during an episode of acute obstruction does not necessarily force the stone through and may increase discomfort. The aim is steady, sensible fluid intake unless a doctor has advised otherwise.

Straining the urine

Passing urine through a stone strainer can help recover the calculus. A captured stone can be sent for laboratory analysis, which may guide future prevention.

Pain disappearing does not always prove that the stone has passed. Occasionally a stone stops causing pain while obstruction remains, so follow-up imaging may still be required.

Activity

Normal gentle activity is usually reasonable if the patient feels well. Some patients find walking helpful, although exercise cannot guarantee stone passage.

Driving, remote travel and hazardous work may be unsafe while unpredictable severe pain or medication-related drowsiness remains possible.

Medical expulsive therapy

Medical expulsive therapy—usually abbreviated to MET, uses medication to help a ureteric stone pass.

The most frequently used medicines are alpha-blockers, including:

  • Tamsulosin
  • Silodosin
  • Alfuzosin

Tamsulosin is commonly selected because it is widely available and familiar to urologists.

Alpha-blockers are primarily used to improve urinary symptoms caused by prostate enlargement. Their use for ureteric stone passage is generally off-label, meaning that stone passage is not necessarily the indication listed in the medicine’s formal registration.

Off-label use does not mean that treatment is experimental or prohibited. It means that the potential benefits, limitations and side effects should be discussed before prescribing it.

How do alpha-blockers affect the distal ureter?

The ureter contains smooth muscle and alpha-adrenergic receptors. These receptors are particularly relevant in the distal ureter.

When a stone enters the ureter, the surrounding muscle can contract and spasm. Swelling may develop around the stone, increasing resistance to its movement.

Alpha-blockers may:

  • Relax distal ureteric smooth muscle
  • Reduce ureteric spasm
  • Reduce pressure below and around the stone
  • Increase the ureter’s ability to accommodate the calculus
  • Improve the likelihood of stone passage
  • Shorten passage time in some patients
  • Reduce episodes of renal colic and analgesic requirements in selected cases

An alpha-blocker does not:

  • Dissolve most stones
  • Make the stone physically smaller
  • Treat a urinary infection
  • Remove a completely impacted stone
  • Protect a kidney from prolonged significant obstruction
  • Replace drainage of an infected obstructed kidney

How effective are alpha-blockers?

Research into alpha-blockers has produced mixed results.

When all ureteric stones are grouped together, some large studies have shown little or no overall benefit. This may be because very small stones frequently pass without medication and very large or impacted stones remain unlikely to pass despite treatment.

The clearest benefit appears to be in patients with distal ureteric stones between approximately 5 and 10 mm.

The EAU recommends offering an alpha-blocker as one treatment option for conservatively managed distal ureteric stones in this size range, while explaining that treatment is off-label. EAU Guidelines on Urolithiasis

For a stone smaller than 5 mm, the natural passage rate is already high, so an alpha-blocker may add relatively little benefit. Treatment decisions should therefore be individualised.

Side effects and precautions with alpha-blockers

Possible side effects include:

  • Dizziness
  • Light-headedness on standing
  • Low blood pressure
  • Weakness or fatigue
  • Headache
  • Nasal congestion
  • Palpitations
  • Reduced semen volume
  • Failure of ejaculation or retrograde ejaculation

Extra caution is required in patients who:

  • Already have low blood pressure
  • Have a history of fainting or falls
  • Take several blood-pressure medicines
  • Use medication for erectile dysfunction
  • Have significant cardiovascular disease
  • Are planning cataract or glaucoma surgery

Tamsulosin has been associated with intraoperative floppy iris syndrome during cataract surgery. Patients should tell their ophthalmologist about current or previous use.

Alpha-blocker treatment should be stopped and medical advice obtained if infection, uncontrollable pain or deterioration in kidney function develops.

How long can conservative management continue?

There is no single safe waiting period for every patient. The decision depends on symptoms, obstruction, kidney function, stone movement and the likelihood of passage.

Many stones that pass naturally do so within two to four weeks. A monitored trial of passage may sometimes continue for up to approximately four to six weeks, provided that:

  • Pain remains manageable
  • Infection does not develop
  • Kidney function remains stable
  • Obstruction is not causing progressive harm
  • Follow-up imaging is performed
  • The patient still prefers conservative treatment

Observation should not become open-ended. A painless obstructing stone can still impair kidney function.

Follow-up may involve an X-ray, ultrasound or low-dose CT scan. The most suitable test depends on whether the stone was visible on the original X-ray and whether ongoing obstruction needs to be assessed.

When has conservative management failed?

Conservative management should be reconsidered when:

  • The stone has not passed within an appropriate observation period
  • Repeat imaging shows that the stone has not moved
  • Pain remains severe despite adequate medication
  • Repeated emergency presentations are required
  • Nausea or vomiting prevents oral fluids or medication
  • Fever or urinary infection develops
  • Kidney function deteriorates
  • Hydronephrosis persists or worsens
  • Urine output falls significantly
  • The stone has a low likelihood of spontaneous passage
  • The patient has a solitary kidney or bilateral obstruction
  • The patient cannot safely continue waiting
  • Work, caring responsibilities or travel make unpredictable colic unacceptable
  • The patient prefers definitive removal

The EAU identifies persistent pain, persistent obstruction, impaired kidney function and a low likelihood of spontaneous passage as indications for active stone removal. EAU Guidelines on Urolithiasis

Failure of conservative management is not a personal failure. It usually means that the stone is too large, impacted, anatomically trapped or producing complications that make further waiting unsafe.

Surgical and procedural treatment

The two main definitive treatments for a distal ureteric calculus are:

  • Ureteroscopy with laser lithotripsy or stone extraction
  • Shock wave lithotripsy

The most appropriate option depends on stone size, density and position, as well as the patient’s anatomy, medical health, preferences and treatment availability.

Ureteroscopy and laser lithotripsy

Ureteroscopy is commonly used for distal ureteric stones and generally provides the best chance of becoming stone-free after one procedure.

Under anaesthesia, a small telescope is passed through:

  1. The urethra
  2. The bladder
  3. The opening of the ureter
  4. The ureter to the level of the stone

The stone may be removed intact with a small basket or fragmented using a holmium or thulium laser. The pieces are then extracted or allowed to pass naturally.

No external incision is usually required.

Is a ureteric stent required?

A temporary ureteric stent may be inserted when:

  • The ureter is swollen
  • Access was difficult
  • Infection is a concern
  • Stone fragments remain
  • There was ureteric trauma
  • Reliable drainage is required
  • Kidney function is vulnerable

A stent extends from the kidney to the bladder. It can cause:

  • Urinary frequency and urgency
  • Bladder discomfort
  • Pain in the kidney during urination
  • Blood in the urine
  • Discomfort during activity
  • A sensation of incomplete emptying

Stents must be removed or exchanged at the planned time. A forgotten stent can become encrusted and cause serious complications.

Risks of ureteroscopy

Possible complications include:

  • Urinary infection or sepsis
  • Bleeding
  • Failure to reach or remove the stone
  • Residual fragments
  • Ureteric perforation
  • Ureteric narrowing or stricture
  • Need for a further procedure
  • Anaesthetic complications

Major ureteric injury is uncommon but can require additional surgery.

Compared with shock wave treatment, ureteroscopy generally offers a higher chance of clearing the stone in one procedure, although it is more invasive and has a higher complication rate. EAU Guidelines on Urolithiasis

Shock wave lithotripsy

Shock wave lithotripsy, SWL or ESWL, uses externally generated shock waves focused onto the stone. These waves fragment the calculus into smaller pieces that can pass down the ureter.

Advantages may include:

  • No telescope passing up the ureter
  • No surgical incision
  • Lower procedural morbidity
  • Day-treatment suitability in many patients

Limitations include:

  • Lower single-treatment stone-free rates than ureteroscopy
  • Possible need for repeat treatment
  • Pain while fragments pass
  • Residual fragments
  • Difficulty targeting some distal stones
  • Reduced success with dense or impacted stones
  • Reduced effectiveness with greater skin-to-stone distance
  • Possible need for subsequent ureteroscopy

SWL may not be suitable during pregnancy, with untreated infection, uncorrected bleeding disorders, an aneurysm near the treatment field or an anatomical obstruction below the stone.

The American Urological Association recognises both ureteroscopy and shock wave lithotripsy as options when active treatment is required for a distal ureteric stone. AUA Surgical Management of Kidney and Ureteral Stones Guideline

Emergency drainage with a ureteric stent

A ureteric stent may be inserted urgently to bypass an obstructing stone and allow urine to drain from the kidney.

This is particularly important when there is:

  • Infection or sepsis
  • Deteriorating kidney function
  • A solitary obstructed kidney
  • Bilateral obstruction
  • Uncontrollable pain
  • Severe obstruction where immediate stone removal is unsuitable

Emergency stenting relieves the obstruction but does not always remove the stone. Definitive ureteroscopy or SWL may be scheduled later.

Percutaneous nephrostomy

A nephrostomy tube is inserted through the skin of the back directly into the kidney under imaging guidance.

It may be used when:

  • Rapid drainage of an infected kidney is required
  • A ureteric stent cannot be inserted
  • The patient is too unwell for a longer procedure
  • Ureteric anatomy prevents retrograde access

Both ureteric stenting and nephrostomy provide effective emergency drainage. The choice depends on clinical circumstances, local expertise and the patient’s condition.

Open, laparoscopic or robotic stone removal

Open or keyhole ureterolithotomy is now rarely required for an isolated distal ureteric stone.

It may occasionally be considered for:

  • A very large impacted stone
  • Unusual urinary anatomy
  • Failure of less invasive treatments
  • A stone requiring treatment during another planned reconstruction

Most distal stones can be treated successfully with ureteroscopy or SWL.

Which treatment is best?

There is no single procedure that is best for every patient.

Ureteroscopy may be preferred when:

  • Rapid and reliable stone clearance is important
  • The stone is impacted
  • The stone is dense or unlikely to fragment with SWL
  • Previous SWL has failed
  • The patient has significant obesity
  • The stone is difficult to target externally
  • The patient wishes to minimise the likelihood of repeat treatment

SWL may be preferred when:

  • The stone can be targeted clearly
  • The stone has favourable size and density
  • The patient wishes to avoid ureteroscopy
  • Anaesthetic considerations favour a less invasive approach
  • The patient accepts the possibility of repeat treatment

The decision should include a discussion of success rates, anaesthesia, stent requirements, recovery, complications and the possible need for another procedure.

Preventing another stone

Once the acute episode has resolved, prevention becomes important.

General measures may include:

  • Drinking enough fluid to produce at least 2–2.5 litres of urine daily, unless medically restricted
  • Reducing excessive salt intake
  • Maintaining normal dietary calcium rather than eliminating calcium
  • Moderating excessive animal-protein intake
  • Maintaining a healthy body weight
  • Avoiding recurrent dehydration
  • Capturing the stone for analysis
  • Completing blood and urine testing when indicated

Patients with recurrent stones, a solitary kidney, childhood stone disease, unusual stone types or a strong family history may require a formal metabolic evaluation, including 24-hour urine testing.

Prevention should be tailored to the stone composition and the patient’s metabolic risk factors.

The bottom line

Many small distal ureteric stones can be managed safely without surgery. Stones smaller than 5 mm near the bladder have the greatest likelihood of passing naturally.

Conservative treatment usually involves appropriate pain relief, sensible hydration, urine straining, follow-up imaging and—in selected patients—an alpha-blocker such as tamsulosin.

Alpha-blockers relax the smooth muscle of the distal ureter. Their greatest likely benefit is for distal stones between approximately 5 and 10 mm. They do not dissolve the stone and should not delay treatment when infection, uncontrolled pain, persistent obstruction or declining kidney function develops.

Ureteroscopy with laser treatment provides the most reliable single-procedure clearance for many distal stones. Shock wave lithotripsy is less invasive but may require repeat treatment. An infected obstructed kidney requires urgent drainage rather than continued observation.

This article provides general information and does not replace individual medical assessment. Anyone with renal colic and fever, inability to pass urine, persistent vomiting or uncontrollable pain should seek urgent medical care.

Need help deciding whether your ureteric stone can safely pass?

If you have been diagnosed with a distal ureteric calculus, appropriate management depends on more than its size alone. Stone position, pain, infection, kidney function and the degree of obstruction must all be considered.

Your local Brisbane urologist, Dr Jo Schoeman, can assess whether observation, medical expulsive therapy, ureteroscopy or shock wave treatment is the most appropriate option for you.

References and further reading

Enlarged Prostate (BPH): Understanding Prescription Combination Therapy

Benign prostatic hyperplasia (BPH), also called benign prostate enlargement, becomes more common as men get older. An enlarged prostate may narrow the urethra or affect the way the bladder works.

Possible symptoms include:

  • a slow or intermittent urinary stream
  • difficulty starting urination
  • straining to urinate
  • a feeling that the bladder has not emptied fully
  • urinary frequency or urgency
  • waking at night to urinate
  • dribbling after urination
  • urinary retention

These symptoms are not always caused by an enlarged prostate. Infection, overactive bladder, urethral narrowing, bladder stones, neurological conditions and prostate or bladder cancer can sometimes produce similar symptoms. An appropriate clinical assessment is therefore important before treatment is selected.

What treatments are available?

Management depends on symptom severity, prostate size, bladder emptying, general health and personal preferences. Options may include:

  • monitoring and lifestyle measures
  • prescription medicines
  • minimally invasive procedures
  • prostate surgery

No single option is best for every patient. A treatment that improves symptoms in one man may be unsuitable for another.

How prescription combination therapy works

For selected men, a doctor may prescribe two types of medicine together:

  1. An alpha blocker, such as tamsulosin, relaxes smooth muscle in the prostate and bladder neck. This may improve urine flow and symptoms relatively quickly, although response varies.
  2. A 5-alpha-reductase inhibitor, such as dutasteride or finasteride, alters the hormonal pathway involved in prostate growth. Over time, it may reduce prostate volume and lower the risk of urinary retention or BPH-related surgery in appropriately selected men.

These medicines are available only on prescription. They may be prescribed separately or, in some circumstances, in a fixed-dose combination. This article does not recommend a particular medicine or brand.

The prostate-reducing component acts gradually. Any benefit is generally assessed over months rather than days. Combination therapy is commonly considered as a longer-term treatment, but regular review remains important.

Who might be considered for combination therapy?

A doctor may consider combination treatment for a man who has moderate-to-severe urinary symptoms associated with a demonstrably enlarged prostate and an increased risk of BPH progression.

The decision may take account of:

  • how troublesome the symptoms are
  • prostate size and shape
  • PSA results, interpreted in clinical context
  • urinary flow rate
  • the amount of urine left in the bladder after voiding
  • previous urinary retention
  • the expected benefits, limitations and adverse effects of treatment
  • other illnesses and medicines
  • the patient’s preferences, including the importance of preserving sexual and ejaculatory function

Prostate size alone should not determine treatment. Some men with large prostates have few symptoms, while a smaller prostate can still cause obstruction because of its shape, a tight bladder neck or another condition.

Assessment before treatment

Depending on the individual, assessment may include:

  • a urinary, medical and medication history
  • a validated symptom questionnaire
  • physical examination, which may include a digital rectal examination
  • urine testing
  • PSA testing after discussion of its benefits and limitations
  • kidney-function blood tests
  • urinary flow measurement
  • ultrasound assessment of prostate size and post-void residual urine
  • a bladder diary
  • cystoscopy or urodynamic testing in selected cases

The purpose is to confirm the likely cause of the symptoms and identify complications or conditions that require a different approach.

Possible benefits and limitations

An alpha blocker may improve urine flow and some symptoms within days or weeks. It does not substantially shrink the prostate.

A 5-alpha-reductase inhibitor works more slowly. In men with prostate enlargement, it may reduce prostate volume and lower the long-term risk of acute urinary retention or BPH-related surgery. Not every patient will experience a worthwhile improvement.

Combination treatment may improve symptoms more than either medicine alone in appropriately selected patients, but it also exposes the patient to the adverse effects of both medicine classes. It controls BPH rather than permanently curing it. Symptoms may recur or progress, and a procedure may still be required.

Clinical-trial averages cannot predict an individual patient’s result. Benefits and harms should be reviewed with the prescribing doctor.

Possible adverse effects

Adverse effects differ between people. The Consumer Medicine Information supplied with the prescribed medicine should be read, and new or troublesome symptoms should be discussed with the prescriber or pharmacist.

Sexual and ejaculatory effects

Possible effects include:

  • reduced semen volume or absent ejaculation
  • semen passing backwards into the bladder
  • reduced sexual desire
  • difficulty achieving or maintaining an erection
  • changes in fertility or semen characteristics

Some sexual adverse effects have been reported to persist after a 5-alpha-reductase inhibitor is stopped, although their frequency, cause and predictors remain uncertain. Persistent symptoms deserve appropriate assessment.

Dizziness and low blood pressure

Alpha blockers may cause dizziness, light-headedness, weakness or, less commonly, fainting—particularly when standing up. The risk may be greater when treatment begins or when combined with other medicines that lower blood pressure. Patients who become dizzy should take care to avoid falls and seek medical advice.

Breast and other changes

5-alpha-reductase inhibitors may cause breast tenderness or enlargement. A breast lump, nipple discharge or persistent one-sided change requires medical assessment rather than being assumed to be a medicine effect.

Other reported adverse effects can include headache, tiredness, palpitations, nasal congestion, gastrointestinal discomfort, skin reactions, testicular symptoms and mood changes. The exact safety information depends on the medicine prescribed.

Seek urgent help

Urgent medical attention is appropriate for symptoms such as:

  • swelling of the face, tongue or throat, or difficulty breathing
  • collapse or fainting
  • a painful, prolonged erection
  • a severe blistering or peeling skin reaction
  • suicidal thoughts or severe psychological distress
  • inability to pass urine, especially with increasing lower abdominal pain

In Australia, call Triple Zero (000) in an emergency. Lifeline is available on 13 11 14 for crisis support. These services do not replace assessment by the treating clinician.

PSA monitoring

5-alpha-reductase inhibitors commonly lower PSA. This does not eliminate the possibility of prostate cancer.

A new PSA baseline may need to be established after treatment begins. Later results must be interpreted with knowledge that the patient is taking this type of medicine. A confirmed increase from the lowest PSA reached may require further assessment, even if the result falls within a laboratory’s usual reference range.

Patients should tell any clinician ordering or interpreting a PSA test about all current and recent prostate medicines.

Cataract or glaucoma surgery

Tamsulosin and some other alpha blockers are associated with intraoperative floppy iris syndrome, which may complicate cataract or glaucoma surgery.

Patients should tell their ophthalmologist about current or previous alpha-blocker use. They should not stop a prescribed medicine solely for an eye operation unless advised by the relevant treating clinicians, because stopping it may not remove the surgical risk.

Mood and persistent symptoms

Sexual, cognitive and mood symptoms have been reported during or after treatment with 5-alpha-reductase inhibitors. The evidence about persistent syndromes, their frequency and causation continues to evolve.

This uncertainty should be discussed without either assuming that persistent symptoms will occur or dismissing symptoms that a patient experiences. New depression, marked anxiety or sexual dysfunction should be reviewed. Suicidal thoughts require urgent assistance.

Monitoring treatment

Follow-up may include review of:

  • symptom response and quality of life
  • dizziness and postural blood pressure
  • sexual and ejaculatory function
  • mood changes
  • urinary flow and post-void residual urine
  • PSA results
  • kidney function when clinically indicated

Lack of early improvement does not necessarily mean the slower-acting component has failed. However, severe or worsening symptoms should not be managed by continuing medicine indefinitely without reassessment.

When might a procedure or surgery be considered?

A procedure may be discussed when there is:

  • recurrent or persistent urinary retention
  • catheter dependence
  • recurrent infection associated with poor bladder emptying
  • bladder stones
  • recurrent visible bleeding attributed to BPH
  • kidney or upper urinary tract effects from obstruction
  • a high or increasing post-void residual volume
  • persistent troublesome symptoms despite appropriate conservative treatment
  • unacceptable medicine adverse effects
  • a preference for a procedural option after informed discussion

Procedural choices include established operations and selected minimally invasive treatments. Suitability depends on prostate anatomy, bladder function, general health, bleeding risk, expected durability and the importance of preserving ejaculation. Each option has potential benefits, limitations and complications.

Questions to discuss with your doctor

  • What is the most likely cause of my urinary symptoms?
  • Is my prostate enlarged, and am I at risk of progression?
  • What are the reasonable alternatives, including observation, medicines and procedures?
  • How likely is each option to help in my circumstances?
  • What sexual, ejaculatory, blood-pressure and mood effects should I consider?
  • How will treatment affect the interpretation of my PSA?
  • When should treatment be reviewed or changed?
  • Which symptoms require urgent assessment?

The bottom line

Prescription combination therapy can be one option for selected men with bothersome urinary symptoms, prostate enlargement and a risk of BPH progression. It is not suitable for every urinary problem and does not guarantee that surgery will be avoided.

The choice should follow an individual assessment and a balanced discussion of expected benefit, possible harm, alternatives and the option of no immediate treatment. Do not start, stop or change a prescription medicine without advice from the prescribing clinician.

This article provides general educational information. It is not medical advice and does not promote or recommend a particular prescription medicine or brand. Treatment decisions should be made with an appropriately qualified health professional after individual assessment.

References and further reading


Penile Cancer: Symptoms, Diagnosis and Treatment in Australia

Penile cancer is rare, but early diagnosis matters

Penile cancer is an uncommon cancer affecting the skin and tissues of the penis. In Australia, approximately 165 men were estimated to be diagnosed with penile cancer in 2025, with the average age at diagnosis around 68 years. About 95% of penile cancers are squamous cell carcinomas (SCC).

Although the diagnosis can understandably be frightening, there is an important message:

When penile cancer is detected early, treatment is frequently curative and, in many men, much or all of the penis can be preserved.

Modern treatment has therefore moved increasingly towards penile-preserving therapy whenever this can be achieved safely.

Treatment in Australia will depend on:

  • whether the abnormality is precancerous or invasive cancer
  • the size and location of the tumour
  • how deeply it has invaded
  • the grade of the cancer
  • whether lymph nodes in the groin are involved
  • whether cancer has spread elsewhere
  • the man’s general health and personal preferences.

Because penile cancer is rare, patients with invasive or complicated disease benefit from discussion by a multidisciplinary team (MDT) involving urology, medical oncology, radiation oncology, radiology, pathology and specialist nursing.


What causes penile cancer?

There is rarely one single identifiable cause.

Important risk factors include:

  • infection with human papillomavirus (HPV)
  • smoking
  • phimosis, where the foreskin cannot be retracted
  • chronic inflammation of the penis
  • penile intraepithelial neoplasia (PeIN)
  • increasing age
  • some chronic penile skin disorders
  • immunosuppression.

HPV plays an important role in a proportion of penile cancers, although penile cancer can certainly occur without HPV infection.


What symptoms should men look for?

Penile cancer often begins as a visible or palpable abnormality, particularly involving the glans or foreskin.

Symptoms can include:

  • a red or discoloured area that does not disappear
  • persistent irritation or inflammation
  • thickening of the skin
  • a lump
  • a wart-like growth
  • an ulcer or sore that does not heal
  • bleeding
  • persistent discharge
  • an unpleasant smell from beneath the foreskin
  • increasing difficulty retracting the foreskin
  • pain or tenderness
  • swelling of the end of the penis
  • a lump beneath the foreskin
  • enlarged lymph nodes or lumps in the groin.

More advanced disease can occasionally cause difficulty passing urine, fatigue or unexplained weight loss.

A persistent penile lesion deserves examination

Most rashes, spots and lumps on the penis are not cancer. Infection, inflammation, dermatitis and benign skin conditions are much more common.

The important issue is persistence.

A penile ulcer, lump, bleeding area or unusual skin change that does not resolve should not be hidden away in the hope that it will disappear.

Embarrassment is considerably easier to treat than advanced cancer.


How is penile cancer diagnosed?

Examination

The first step is careful examination of the penis and foreskin.

The urologist will assess:

  • the site of the lesion
  • its size
  • whether it involves the glans, foreskin or shaft
  • whether deeper tissues appear involved
  • whether the foreskin can be retracted
  • whether there are enlarged lymph nodes in either groin.

Both groins are particularly important because penile cancer usually spreads first through the lymphatic system to the inguinal lymph nodes.


Biopsy

The diagnosis usually requires a biopsy.

A small piece of the abnormal tissue is removed and examined by a pathologist.

Depending upon the lesion, this may be:

  • a punch biopsy
  • an incisional biopsy, taking part of the lesion
  • an excisional biopsy, removing the whole small lesion.

A biopsy determines whether cancer is present and, importantly, identifies the type and grade of the tumour.

Histological confirmation is particularly important before treatments such as topical therapy, laser treatment or radiotherapy.


What is PeIN?

Penile intraepithelial neoplasia (PeIN) is a precancerous or very early cancerous change confined to the surface epithelium.

It has previously been described using terms such as carcinoma in situ.

PeIN is important because it can progress to invasive squamous cell carcinoma. Current European guidelines estimate progression to invasive disease despite treatment in approximately 2.6–13% of patients.

The good news is that PeIN can often be treated without removing part of the penis.


Treatment: from creams to major surgery

There is no single operation or treatment for penile cancer.

Modern management follows a ladder, beginning with the least invasive treatment capable of reliably controlling the cancer.

1. Circumcision

For abnormalities confined to the foreskin, circumcision may remove the lesion completely.

Circumcision is also frequently an important first step when PeIN involves the glans and foreskin because it allows the glans to be properly examined and treated.

For superficial disease, contemporary guidelines regard circumcision as an important primary surgical treatment.


2. Treatment with creams

Selected cases of biopsy-confirmed PeIN can be treated with medication applied directly to the penis.

The two most commonly used treatments are:

5-fluorouracil (5-FU)

5-FU is a topical chemotherapy medication.

It destroys abnormal rapidly dividing cells in the superficial layers of the penis.

Treatment usually produces inflammation of the treated area, which can include:

  • redness
  • burning
  • crusting
  • discomfort
  • erosion of the surface skin.

Imiquimod

Imiquimod is different. Rather than being conventional chemotherapy, it stimulates the local immune system to attack abnormal cells.

It can similarly cause substantial redness, swelling, ulceration or crusting during treatment.

These reactions can look alarming but often indicate that the medication is producing its intended biological effect.

Current EAU-ASCO guidance supports either 5-FU or imiquimod for appropriately selected biopsy-confirmed PeIN.

Importantly, the area must be reassessed after treatment.

If the abnormality persists, repeat biopsy or alternative treatment may be necessary. Repeated courses of topical treatment should not simply continue indefinitely when the lesion has failed to respond, because invasive cancer may be hiding beneath the surface.


3. Laser and other local treatments

Very superficial lesions can sometimes be treated using laser therapy.

Depending upon expertise and availability, other local treatments such as photodynamic therapy or cryotherapy have also been used.

These approaches can preserve the penis but require careful long-term surveillance because local recurrence is possible.


4. Penile-preserving surgery

One of the major changes in penile cancer surgery has been the move away from automatically removing a substantial portion of the penis.

Whenever oncologically safe, the aim is:

remove the cancer, obtain clear margins and preserve as much normal penis as possible.

Operations may include:

Wide local excision

The cancer and a margin of surrounding tissue are removed.

The defect may be closed directly or reconstructed with a skin graft.

Glans resurfacing

The abnormal surface layer of the glans is removed while preserving the deeper erectile tissue.

A skin graft is then placed over the glans.

This can be particularly useful for extensive superficial disease.

Glansectomy

If cancer is confined to the glans but is too extensive or invasive for simpler treatment, part or all of the glans may be removed.

Reconstruction can then be performed, often using a skin graft to create a new glans-like surface.

Current guidelines favour organ-preserving surgery for appropriately selected PeIN and T1–T2 tumours involving the glans or prepuce, provided the patient understands the need for careful follow-up.


5. Partial penectomy

More deeply invasive cancer may require removal of part of the penis.

This is called a partial penectomy.

The surgeon attempts to retain enough penile length to permit comfortable urination and, where possible, sexual function.

This may be necessary when cancer extends more deeply into the erectile tissues and cannot be reliably removed using penile-preserving techniques.


6. Total penectomy

Occasionally a cancer is too large, too proximal or too deeply invasive for part of the penis to be safely preserved.

A total penectomy may then provide the best opportunity for cure.

This understandably sounds confronting. It is generally reserved for circumstances in which less radical treatment would compromise cancer control.

Current EAU-ASCO recommendations support total penectomy with perineal urethrostomy for large invasive tumours that cannot safely be treated by partial penectomy.


What is a perineal urethrostomy?

This is sometimes mistakenly referred to as a “perineotomy”.

Following total removal of the penis, urine still needs a pathway from the bladder to the outside world.

The urethra is therefore brought to the skin of the perineum, the area between the scrotum and anus.

This opening is called a:

Perineal urethrostomy

The patient subsequently passes urine through this opening while sitting on the toilet.

A catheter is generally left temporarily while the area heals.

Once healed, most men can empty their bladder normally through the new opening and do not require a permanent catheter.

Potential problems include:

  • narrowing or stenosis of the opening
  • spraying
  • infection
  • wound complications
  • occasionally the need for further surgery.

A perineal urethrostomy does not mean that the bladder or kidneys have stopped functioning. It simply changes the final few centimetres of the urinary plumbing.


The lymph nodes are extremely important

Treating the penis itself is only one half of penile cancer management.

The other half is determining whether cancer has reached the inguinal lymph nodes in the groin.

Penile cancer generally spreads in a predictable sequence:

Penis → inguinal lymph nodes → pelvic lymph nodes → distant organs

Lymph-node involvement is the single most important prognostic factor in penile cancer.


What if there are no enlarged lymph nodes?

Unfortunately, normal-feeling groins do not completely exclude microscopic cancer.

Men with higher-risk primary tumours may therefore require further lymph-node assessment despite having no palpable lumps.

This may involve:

  • ultrasound of the groins
  • ultrasound-guided needle biopsy of abnormal nodes
  • dynamic sentinel lymph-node biopsy
  • inguinal lymph-node dissection in selected circumstances.

Current EAU-ASCO guidance recommends surgical lymph-node staging for patients at significant risk of microscopic metastatic disease, particularly T1b disease or higher.


What if a groin lymph node is enlarged?

An abnormal lymph node may be assessed using ultrasound and needle biopsy.

If metastatic penile cancer is confirmed, treatment may involve:

  • inguinal lymph-node dissection
  • pelvic lymph-node dissection in selected patients
  • chemotherapy
  • radiotherapy
  • combinations of these treatments.

Patients with clinically node-positive disease are generally staged with CT or FDG-PET/CT to assess pelvic and distant disease before definitive treatment.

Early treatment of lymph-node disease is extremely important.


Radiation therapy

Radiotherapy has an important but selective role in penile cancer.

Treatment of the primary cancer

Selected smaller T1 or T2 cancers can potentially be treated with radiation instead of surgery.

Treatment can involve:

External beam radiotherapy

Radiation is directed at the tumour from outside the body.

Brachytherapy

Radioactive sources are temporarily positioned within or very close to the tumour, allowing a concentrated radiation dose to be delivered while limiting exposure to surrounding tissues.

Radiotherapy may therefore provide another means of preserving the penis in appropriately selected patients.

Potential complications can include:

  • skin irritation
  • ulceration
  • fibrosis
  • narrowing of the urethra
  • changes in penile sensation
  • erectile dysfunction
  • tissue damage or necrosis in uncommon circumstances.

Radiotherapy is also used in selected patients for regional lymph-node disease, as part of chemoradiotherapy for advanced disease, or for palliation of symptoms from metastatic cancer.


Chemotherapy

Chemotherapy is generally reserved for more advanced penile cancer, particularly when significant lymph-node disease or metastatic disease is present.

In Australia, contemporary treatment may involve platinum-based combination chemotherapy.

One regimen used in advanced disease is:

TIP: paclitaxel + ifosfamide + cisplatin

Australia’s eviQ cancer treatment resource includes TIP as an option in neoadjuvant, adjuvant and metastatic penile cancer settings.

For bulky or fixed inguinal lymph-node disease or pelvic lymph-node involvement, chemotherapy may be given before surgery.

This is called neoadjuvant chemotherapy.

The aim is to:

  1. treat microscopic disease throughout the body,
  2. shrink the cancer in the lymph nodes,
  3. determine whether the cancer is responding,
  4. make subsequent surgery more effective or technically achievable.

Current international guidance recommends cisplatin- and taxane-based neoadjuvant chemotherapy for suitable patients with extensive inguinal or pelvic nodal disease, followed by surgery when appropriate.


Chemoradiotherapy

Radiotherapy and chemotherapy can sometimes be combined.

This may be considered for selected patients with:

  • locally advanced disease
  • unresectable cancer
  • extensive lymph-node disease
  • disease where major surgery is unsuitable
  • palliative treatment requirements.

The evidence is evolving, and these decisions should generally be made through a specialist penile cancer MDT.


What about immunotherapy?

Immunotherapy is an exciting area of cancer treatment, but its role in penile cancer is still developing.

Checkpoint inhibitors such as pembrolizumab and related drugs have demonstrated activity in some patients with advanced penile cancer, and newer combinations of chemotherapy and immunotherapy are being investigated.

However, response rates to checkpoint inhibitors alone are relatively modest and there is not yet sufficient evidence to use biomarkers such as HPV or PD-L1 routinely to determine which penile cancer patients should receive immunotherapy.

Clinical trials are particularly important for men whose cancer progresses despite standard platinum-based chemotherapy.


What happens to sexual function?

This depends enormously on treatment.

After topical treatment, circumcision, laser therapy, glans resurfacing or limited local excision, satisfactory sexual function may often be preserved.

After glansectomy or partial penectomy, intercourse may remain possible depending upon remaining penile length, erectile function and reconstruction.

After total penectomy, penetrative intercourse using the penis is no longer possible.

This does not mean that intimacy, sexual sensation or orgasm automatically disappears.

Sexual rehabilitation, psychological support and discussion with the patient and his partner can be an important component of recovery.

These conversations should ideally begin before treatment, not after it.


What is the prognosis?

Penile cancer is potentially highly curable when diagnosed before it has spread to lymph nodes.

The most important predictor of survival is not simply the size of the penile lesion but whether cancer has reached the lymph nodes.

Current EAU-ASCO data report approximate five-year cancer-specific survival according to nodal stage of:

Lymph-node stage Approximate 5-year cancer-specific survival
N0 – no lymph-node metastases 95%
N1 80%
N2 65%
N3 – advanced nodal disease 35%

These are population figures, not predictions for an individual patient.

Prognosis depends upon the tumour’s stage and grade, lymph-node involvement, response to treatment, general health and other pathological features.

The figures do, however, demonstrate why early diagnosis and appropriate assessment of the groin lymph nodes are so important.


Follow-up after treatment

Penile cancer requires ongoing surveillance.

Follow-up may include:

  • examination of the penis or reconstructed area
  • examination of both groins
  • assessment of the perineal urethrostomy where applicable
  • imaging in higher-risk patients
  • biopsy of suspicious recurrent lesions
  • monitoring urinary and sexual function
  • psychological and sexual-health support.

Penile-preserving treatment requires particularly careful surveillance because local recurrence can occur.

Importantly, a local recurrence identified early can often still be successfully treated.


Do not ignore a change in the penis

Penile cancer is uncommon, and most penile skin problems are benign.

Nevertheless, a persistent:

lump, ulcer, red patch, bleeding area, discharge, thickened foreskin or lesion that simply will not heal deserves examination.

There should be no embarrassment in asking your GP or urologist to have a look.

For early disease, treatment may be surprisingly conservative: sometimes circumcision, a cream, laser treatment or limited surgery is all that is required.

Even when invasive cancer is present, modern penile cancer surgery increasingly focuses on preserving penile tissue, urinary function and quality of life whenever this can be achieved without compromising cure.

For advanced disease, treatment becomes more complex and may involve partial or total penectomy, perineal urethrostomy, lymph-node surgery, radiotherapy and chemotherapy.

The crucial message is simple:

The earlier penile cancer is diagnosed, the greater the opportunity to cure it while preserving the penis.

Australian and international resources

Cancer Council Australia: Penile Cancer

Cancer Institute NSW: Penile Cancer

eviQ Australian Penile Cancer Chemotherapy Protocol

2026 EAU-ASCO Penile Cancer Guidelines


This information is intended for patient education and does not replace individual medical assessment. Treatment of penile cancer should be tailored to the tumour stage, pathology, lymph-node status, general health and preferences of the individual patient.

So, if you have noticed a lesion on your penis and it is growing, don’t ignore it and hope it will go away, go see your GP.

Kidney Stones: Understanding the Different Types of Renal Calculi and Their Treatment

Kidney stones, medically known as renal calculi or nephrolithiasis, are solid crystalline deposits that develop within the kidneys. Although we tend to talk about “a kidney stone” as if all stones are the same, there are several distinctly different types.

Knowing the composition of a kidney stone matters. Different stones have different causes, appearances, recurrence risks and, importantly, different strategies for prevention and treatment.

Modern management therefore involves more than simply removing the stone. The aim is to answer three questions:

What is the stone? Why did it form? And how can we prevent the next one?


What Are Kidney Stones Made Of?

The major types of urinary stones are:

  1. Calcium oxalate stones
  2. Calcium phosphate stones
  3. Uric acid stones
  4. Struvite or infection stones
  5. Cystine stones
  6. Rare metabolic and medication-related stones

Stones are not always chemically pure. Many contain a mixture of different crystalline components.

The European Association of Urology recommends reliable stone analysis and a basic metabolic evaluation in stone-forming patients, with more detailed metabolic investigation particularly important in patients at high risk of recurrence.


1. Calcium Oxalate Stones

The most common kidney stone

Calcium oxalate stones are the most frequently encountered urinary calculi.

They may consist predominantly of:

  • Calcium oxalate monohydrate, known as whewellite
  • Calcium oxalate dihydrate, known as weddellite

Calcium oxalate monohydrate stones can be particularly hard and resistant to fragmentation with shockwave lithotripsy.

Why do calcium oxalate stones form?

Contributing factors may include:

  • Low urine volume or dehydration
  • Excess urinary calcium
  • Excess urinary oxalate
  • Low urinary citrate
  • High dietary sodium intake
  • Excessive animal protein intake
  • Certain bowel diseases or previous intestinal surgery
  • Genetic predisposition
  • Metabolic abnormalities

Importantly, calcium stones do not necessarily mean that a patient is eating too much calcium.

Severely restricting normal dietary calcium can actually be counterproductive because calcium within the intestine binds oxalate and reduces its absorption.

Management

Small asymptomatic stones may sometimes simply be monitored.

When treatment is required, options include:

  • Shockwave lithotripsy (SWL)
  • Flexible ureteroscopy and laser lithotripsy
  • Percutaneous nephrolithotomy (PCNL)
  • Observation in appropriately selected patients

Prevention depends on the underlying metabolic abnormality and may include increased fluid intake, dietary modification, reduction in excessive sodium intake, potassium citrate for selected patients, thiazide therapy for hypercalciuria and treatment of hyperoxaluria or hyperuricosuria when identified.


2. Calcium Phosphate Stones

Calcium phosphate stones are less common than calcium oxalate stones.

They may contain:

  • Hydroxyapatite
  • Carbonate apatite
  • Brushite

Why do they form?

Calcium phosphate crystallisation is favoured by relatively alkaline urine.

They may be associated with:

  • Hypercalciuria
  • Renal tubular acidosis
  • Hyperparathyroidism
  • Urinary tract abnormalities
  • Certain metabolic disorders

Brushite stones deserve particular attention. They can be extremely hard and may respond poorly to shockwave treatment.

Management therefore needs to consider not only stone size and location, but also stone density and previous stone composition.


3. Uric Acid Stones

Uric acid stones behave very differently from calcium stones.

They are strongly associated with persistently acidic urine and may occur in patients with:

  • Gout
  • Metabolic syndrome
  • Diabetes
  • Obesity
  • High purine intake
  • High animal-protein intake
  • Chronic dehydration
  • Excessive uric acid production or excretion

Uric acid stones account for approximately 10% of renal stones and all uric acid stone formers are considered at increased risk of recurrence.

Why are uric acid stones special?

Because unlike most kidney stones, uric acid stones can potentially be dissolved.

Treatment involves increasing urinary pH, usually using an alkalinising medication such as potassium citrate.

For active oral dissolution therapy, urinary pH needs to be carefully monitored. Current EAU guidance describes targeting approximately pH 7.0–7.2 during chemolysis, while avoiding excessive alkalinisation because this may encourage calcium phosphate crystallisation.

This creates one of the happier conversations in stone management:

“You have a kidney stone, but we may be able to make it disappear without an operation.”

Not every uric acid stone will dissolve successfully, and obstructed or infected kidneys require separate and sometimes urgent treatment.


4. Struvite Stones: The Infection Stones

Struvite stones contain magnesium ammonium phosphate and are closely associated with urinary infections caused by certain urease-producing bacteria.

These bacteria change the chemistry of the urine, producing an alkaline environment favourable for rapid stone formation.

Struvite stones can become very large and occasionally form a branching staghorn calculus, occupying much of the kidney’s collecting system.

Why are these stones important?

The stone and infection can maintain one another.

Leaving significant infected stone material behind may therefore contribute to:

  • Recurrent urinary infection
  • Rapid stone regrowth
  • Kidney damage
  • Sepsis

Management generally involves treating the infection and achieving as complete a stone clearance as reasonably possible. Large stones frequently require PCNL, sometimes performed in more than one stage.

Infection stone formers are regarded as being at high risk of recurrence.


5. Cystine Stones

Cystine stones are uncommon and are caused by cystinuria, an inherited disorder affecting the transport of certain amino acids through the kidneys.

Cystine is relatively insoluble in urine and can crystallise to form stones.

These patients may start developing stones at a young age and can experience repeated stone episodes throughout life.

Treatment and prevention

Prevention is particularly important and may involve:

  • Very high fluid intake
  • Reduced dietary sodium
  • Urinary alkalinisation
  • Potassium citrate
  • Specialist medication such as tiopronin in selected recurrent cases

Current EAU guidance recommends aiming for a urine volume greater than 3 litres per day in adults with cystinuria and maintaining urinary pH above approximately 7.5 to improve cystine solubility.

Cystine stones are also relatively hard, which can make shockwave treatment less successful. Ureteroscopy with laser treatment or PCNL may therefore be required depending on stone burden.


6. Rare Kidney Stones

Much less commonly, stones may consist of substances such as:

  • Xanthine
  • 2,8-dihydroxyadenine
  • Ammonium urate
  • Matrix material
  • Medication-related crystalline material

These stones can sometimes provide the first clue to an underlying metabolic, genetic or medication-related disorder.

Recurrent unusual stones therefore deserve specialist investigation rather than simply repeated stone removal.


How Do Kidney Stones Present?

Some kidney stones sit quietly within the kidney and are discovered incidentally during an ultrasound or CT scan.

Others announce their arrival with considerably less subtlety.

A stone entering and obstructing the ureter may cause renal colic, producing severe pain from the loin toward the abdomen or groin.

Other symptoms can include:

  • Blood in the urine
  • Nausea and vomiting
  • Urinary urgency or frequency
  • Burning during urination
  • Recurrent urinary infection
  • Fever or chills
  • Intermittent loin discomfort

Fever plus an obstructed kidney is an emergency

An infected obstructed urinary system can progress rapidly to urosepsis.

Urgent drainage with a ureteric stent or nephrostomy tube, together with appropriate antibiotics and supportive treatment, may be required. Definitive stone treatment is generally delayed until the infection has been controlled.


How Are Kidney Stones Investigated?

CT Scan

A non-contrast CT scan of the kidneys, ureters and bladder provides detailed information regarding:

  • Stone size
  • Number of stones
  • Exact location
  • Degree of obstruction
  • Kidney anatomy
  • Stone density measured in Hounsfield units

CT density may also provide clues about stone composition and the likelihood of successful shockwave fragmentation.

Ultrasound

Ultrasound avoids radiation and is particularly useful for:

  • Surveillance
  • Detecting hydronephrosis
  • Monitoring known renal stones
  • Selected younger patients
  • Pregnancy

However, very small stones and ureteric stones can sometimes be difficult to identify accurately.

Plain X-ray

A KUB X-ray may be useful for monitoring certain radiopaque stones.

Calcium-containing stones are usually radiopaque, whereas uric acid stones are typically radiolucent on plain X-ray.


Do All Kidney Stones Need Treatment?

No.

A small, non-obstructing and asymptomatic kidney stone may sometimes be monitored with periodic imaging.

Treatment becomes more appropriate when there is:

  • Stone growth
  • Recurrent pain
  • Haematuria
  • Urinary obstruction
  • Recurrent infection
  • Declining renal function
  • Significant stone burden
  • High risk of future complications
  • Occupational or travel considerations
  • Patient preference

These factors are reflected in contemporary EAU recommendations.


Treatment Options for Kidney Stones

1. Active Surveillance

Small asymptomatic renal stones can sometimes be observed.

Follow-up may include ultrasound, X-ray or CT depending on the type, size and visibility of the stone.

The advantage is obvious: no procedure unless one becomes necessary.

The disadvantage is equally obvious: stones have not signed a contract promising to remain where they are.

They may enlarge, migrate into the ureter, cause obstruction or become symptomatic.


2. Shockwave Lithotripsy

Extracorporeal shockwave lithotripsy (SWL) uses externally generated shockwaves focused onto the stone.

The aim is to fragment the calculus into smaller pieces that can subsequently pass through the urinary tract.

Advantages

  • Non-invasive
  • Usually rapid recovery
  • No incision
  • Useful for appropriately selected renal stones

Limitations

Success depends on:

  • Stone size
  • Location
  • Density
  • Composition
  • Skin-to-stone distance
  • Renal anatomy

Hard stones such as calcium oxalate monohydrate, brushite and cystine stones may be less responsive.

More than one treatment session may be required.


3. Flexible Ureteroscopy and Laser Lithotripsy

A fine flexible telescope is passed through the urethra and bladder, up the ureter and into the kidney.

There are no external incisions.

The stone can then be fragmented or dusted using a laser, with larger fragments removed using tiny retrieval baskets.

Advantages

  • Minimally invasive
  • High stone clearance rates for appropriately selected stones
  • Can treat stones resistant to shockwave therapy
  • Allows direct visualisation
  • Suitable for many locations within the kidney

Possible disadvantages

  • Requires anaesthesia
  • Temporary ureteric stenting may be required
  • Stent discomfort
  • Bleeding or infection
  • Ureteric injury is uncommon but possible
  • Occasionally a second procedure is required

4. Percutaneous Nephrolithotomy

PCNL involves creating a small tract through the skin directly into the kidney.

It is particularly useful for:

  • Large renal calculi
  • Staghorn stones
  • Complex stones
  • Large-volume infection stones
  • Stones unlikely to respond adequately to less invasive techniques

Current EAU guidance recommends PCNL as the first-line treatment for renal stones larger than 2 cm in most suitable patients.

PCNL generally provides excellent clearance of large stone burdens but is more invasive than ureteroscopy or shockwave treatment.

Potential complications include bleeding, infection, injury to surrounding structures and the need for additional procedures.


5. Dissolution Therapy

This option is mainly relevant to uric acid stones.

Urinary alkalinisation can gradually dissolve the stone, potentially avoiding surgery.

Treatment requires:

  • Correct identification or strong suspicion of uric acid composition
  • Regular urine pH monitoring
  • Appropriate alkalinising medication
  • Follow-up imaging
  • Patient compliance

It is important not to assume that every radiolucent stone is uric acid, and treatment should be supervised appropriately.


Choosing the Right Treatment

There is no single “best” kidney stone operation.

The appropriate treatment depends on a combination of:

Stone factors

  • Size
  • Number
  • Location
  • Composition
  • Density
  • Previous growth

Kidney factors

  • Anatomy
  • Obstruction
  • Infection
  • Renal function

Patient factors

  • Symptoms
  • Medical conditions
  • Anticoagulant therapy
  • Previous stone procedures
  • Occupation
  • Travel requirements
  • Personal preference

Two patients with apparently similar 10 mm stones may therefore receive quite different recommendations.


Preventing the Next Kidney Stone

Removing a stone solves today’s problem.

Preventing another stone solves tomorrow’s problem.

Patients with recurrent stones, multiple stones, bilateral stones, unusual stone composition, young age at presentation or other high-risk features may benefit from metabolic investigation.

This may include blood testing and 24-hour urine collections assessing factors such as:

  • Urine volume
  • Calcium
  • Oxalate
  • Citrate
  • Uric acid
  • Sodium
  • Magnesium
  • Urinary pH

Stone analysis is particularly valuable whenever a stone can be retrieved. Current EAU guidance recommends reliable stone analysis and basic metabolic evaluation for stone formers, with specific metabolic assessment for high-risk patients.


General Kidney Stone Prevention

Although prevention should ultimately be tailored to stone composition, several principles apply to many stone formers.

Drink more water

Maintaining generous urine output dilutes the substances responsible for crystal formation.

Water remains wonderfully unexciting and remarkably effective.

Reduce excessive salt intake

High sodium intake can increase urinary calcium excretion and contribute to calcium stone formation.

Maintain normal dietary calcium

Patients with calcium stones should not automatically eliminate calcium-containing foods.

A balanced dietary calcium intake may actually reduce intestinal oxalate absorption.

Moderate excessive animal protein

Large amounts of meat and other purine-rich foods may contribute to increased urinary uric acid and more acidic urine in susceptible individuals.

Maintain a healthy weight

Obesity and metabolic syndrome are particularly associated with uric acid stone formation.

Investigate recurrent stones

Repeatedly removing stones without investigating why they keep forming can become a rather expensive game of geological whack-a-mole.


Can Medication Prevent Kidney Stones?

Yes, in appropriately selected patients.

Depending on the metabolic abnormality and stone composition, preventive medication may include:

  • Potassium citrate
  • Thiazide or thiazide-like medication
  • Allopurinol
  • Urinary alkalinising therapy
  • Tiopronin for selected cystinuria patients

Medication should ideally be guided by stone analysis, blood investigations and, when indicated, 24-hour urine testing rather than prescribed indiscriminately.


The Bottom Line

A kidney stone is not simply a kidney stone.

A calcium oxalate stone, uric acid stone, infection stone and cystine stone may look similar on a scan, but they can have very different causes and require very different long-term strategies.

Modern kidney stone management combines:

accurate imaging + appropriate stone removal + stone analysis + metabolic investigation + prevention.

Treatment may range from simple surveillance through to shockwave lithotripsy, flexible ureteroscopy and laser treatment, PCNL or, in selected uric acid stones, medical dissolution therapy.

The ultimate aim is not simply to leave the operating theatre stone-free.

It is to keep the patient stone-free.


When Should You See a Urologist?

Consider urological assessment if you have:

  • Recurrent kidney stones
  • Persistent loin or flank pain
  • Blood in the urine
  • Recurrent urinary infections
  • A stone associated with urinary obstruction
  • Increasing stone size on surveillance imaging
  • Multiple or bilateral kidney stones
  • A large renal calculus
  • Previous complex stone surgery

Severe pain associated with fever, chills or feeling systemically unwell requires urgent medical assessment, as an infected obstructed kidney can be a medical emergency.

This information is intended for general patient education and does not replace individual medical assessment. The appropriate investigation, surveillance and treatment of kidney stones should be tailored to the individual patient.

This blog is aligned with the current 2026 EAU Urolithiasis Guidelines, including the updated recommendations on stone composition, renal stone treatment and metabolic prevention.

EAU Guidelines on Urolithiasis

Intravesical Therapy for High-Risk Bladder Cancer

BCG treatment, what is it?

BCG, short for Bacillus Calmette–Guérin, is one of the most effective treatments available for high-risk non-muscle-invasive bladder cancer (NMIBC).

BCG is best known as a vaccine originally developed against tuberculosis. In bladder cancer, however, it is used in a very different way. Rather than being injected as a vaccination, a solution containing BCG is placed directly into the bladder through a fine urinary catheter.

BCG is not conventional chemotherapy. It is a form of local immunotherapy. Its purpose is to stimulate the body’s immune system inside the bladder so that immune cells recognise and attack remaining bladder cancer cells.

For appropriately selected patients, BCG can significantly reduce the risk of bladder cancer returning and, importantly, reduce the risk of progression to more invasive disease.


Which bladder cancers are treated with BCG?

BCG is primarily used for high-risk or locally aggressive non-muscle-invasive urothelial carcinoma following adequate transurethral resection of the bladder tumour (TURBT).

Typical indications include:

  • Carcinoma in situ (CIS or Tis)
  • High-grade Ta urothelial carcinoma, particularly when large, multifocal or recurrent
  • High-grade T1 urothelial carcinoma
  • Recurrent high-grade non-muscle-invasive bladder cancer
  • Selected patients with multiple adverse pathological features
  • Selected patients with urothelial CIS involving the prostatic urethra as part of a bladder-preserving strategy

Current international guidelines recommend a six-week induction course of BCG for high-risk NMIBC, followed by maintenance treatment in patients who respond.

BCG is generally not required for a solitary low-risk, low-grade Ta bladder tumour. These cancers have a different biological behaviour and are usually managed with TURBT, sometimes combined with immediate intravesical chemotherapy and subsequent surveillance.


Why is BCG particularly important for carcinoma in situ?

Carcinoma in situ (CIS) deserves special attention.

Unlike the familiar papillary bladder tumour that projects into the bladder cavity, CIS can appear as a relatively flat, red or velvety abnormality of the bladder lining. Despite looking less dramatic, it is biologically aggressive.

CIS has a significant risk of recurrence and progression to muscle-invasive bladder cancer if inadequately treated. It cannot simply be “scraped away” by TURBT and forgotten.

For this reason, CIS generally requires either:

BCG immunotherapy
or, in selected very-high-risk circumstances,
radical cystectomy.

BCG produces substantially better response rates for CIS than intravesical chemotherapy in appropriate patients and has been shown to reduce the risk of progression.


How does BCG actually work?

The mechanism is fascinating because BCG does not simply poison cancer cells in the way traditional chemotherapy does.

Think of it less as dropping a bomb on the tumour and more as turning on the bladder’s local security system.

After BCG is introduced into the bladder, organisms interact with the urothelial surface and tumour cells. This produces a strong local inflammatory and immune response.

The process includes:

BCG attachment and internalisation

BCG interacts with urothelial cells, tumour cells and immune cells within the bladder.

Activation of innate immunity

Neutrophils, macrophages, dendritic cells and other immune cells are recruited into the bladder.

Cytokine release

A complex inflammatory signalling response develops, involving multiple cytokines and chemokines.

Activation of adaptive immunity

T lymphocytes and other components of the immune system become involved in recognising and destroying malignant urothelial cells.

The end result is an intentionally stimulated immune environment that makes the bladder a considerably less comfortable neighbourhood for residual cancer cells.


Before starting BCG

Successful BCG treatment starts with adequate staging and tumour clearance.

Patients will usually have undergone TURBT with pathological assessment confirming the tumour grade and stage.

In high-grade T1 disease, a repeat or second-look TURBT is frequently recommended to ensure complete resection and exclude previously unrecognised muscle-invasive disease.

Depending upon the tumour characteristics, assessment may also include:

  • Urine cytology
  • CT urography or other upper urinary tract imaging
  • Repeat cystoscopy
  • Re-resection of the original tumour site
  • Assessment of the prostatic urethra in selected patients
  • Review of pathology where variant histology or unusual findings are present

Very-high-risk cases are increasingly appropriate for multidisciplinary discussion because some patients may benefit more from early radical cystectomy than prolonged attempts at bladder preservation.


How is BCG given?

BCG is administered as an outpatient procedure.

A small catheter is gently passed through the urethra into the bladder. After the bladder has been drained, the BCG solution is instilled through the catheter.

The catheter is then removed unless there is a particular reason for it to remain temporarily.

The BCG solution is generally retained within the bladder for approximately two hours, where tolerated.

Patients receive specific instructions regarding fluid intake before treatment and safe handling of urine afterwards because BCG contains live attenuated Mycobacterium bovis.


The standard induction course

The traditional induction course consists of:

BCG once weekly for six weeks

This remains the standard initial regimen for high-risk disease.

Importantly, attempts to substantially reduce the number of induction and maintenance instillations have resulted in inferior cancer control. The six-week induction course therefore remains an important part of established treatment.


What happens after the first six treatments?

Following induction BCG, the bladder is reassessed.

This will generally involve:

  • Cystoscopy
  • Urinary cytology
  • Biopsy or repeat TURBT if an abnormality is detected
  • Additional investigation when cytology remains suspicious despite a normal-looking bladder

The key question is simple:

Has the cancer responded?

If it has, the next step is usually maintenance BCG.


Maintenance BCG

BCG works better in high-risk bladder cancer when appropriate maintenance treatment is added rather than simply giving six doses and stopping.

A widely used maintenance schedule consists of:

Induction

Once weekly × 6 weeks

followed by:

Maintenance

Once weekly × 3 weeks at:

  • 3 months
  • 6 months
  • 12 months
  • 18 months
  • 24 months
  • 30 months
  • 36 months

This is often referred to as a SWOG-style maintenance schedule.

Current European guidance recommends full-dose BCG for one to three years in high-risk disease, with the benefit of years two and three balanced against toxicity, patient tolerance and BCG availability. Three years of maintenance provides additional protection against recurrence in high-risk patients compared with one year.

Not every patient will receive every planned dose. Treatment may need to be delayed, reduced or discontinued because of side effects, infection, BCG availability or changes in the cancer.


When should BCG NOT be given?

Because BCG contains live attenuated bacteria, certain precautions are essential.

BCG should not be administered:

  • Within the first two weeks after TURBT
  • When there is visible haematuria
  • Following traumatic catheterisation
  • In the presence of a symptomatic urinary tract infection

Treatment should instead be delayed until it can be administered safely.

Additional caution is required in significantly immunocompromised patients, and individual circumstances should be discussed with the treating urologist.


Common side effects of BCG

BCG deliberately produces inflammation within the bladder, so some urinary symptoms are expected.

The most common side effects include:

Urinary frequency and urgency

Patients may feel the need to urinate frequently or suddenly.

Burning during urination

Mild-to-moderate dysuria is common for a day or two following treatment.

Blood in the urine

A small amount of haematuria can occur.

Bladder discomfort

Some patients describe suprapubic discomfort, cramping or a sensation resembling cystitis.

Flu-like symptoms

Fatigue, muscle aches, chills and a low-grade temperature can occur as the immune system responds to treatment.

These symptoms usually settle within approximately 24–48 hours.

The bladder may complain rather loudly about BCG, but mild short-lived irritation is usually part of the intended inflammatory response rather than evidence that something has gone wrong.


When should you contact your urologist?

Patients should contact their treating team if symptoms are unusually severe or fail to settle.

Particular attention should be paid to:

  • Persistent fever
  • High fever or rigors
  • Severe urinary symptoms
  • Inability to pass urine
  • Persistent or heavy haematuria
  • Significant deterioration in general wellbeing
  • Symptoms continuing substantially longer than expected

Persistent fever after BCG deserves particular attention.


Serious complications of BCG

Serious complications are uncommon, but they are important because BCG contains viable attenuated bacteria.

Potential complications include:

Severe BCG cystitis

Persistent bladder inflammation may occasionally become sufficiently troublesome that treatment needs to be delayed or discontinued.

Granulomatous prostatitis

BCG can produce an inflammatory reaction within the prostate. This can occasionally produce an abnormal prostate examination or elevated PSA and may mimic prostate cancer clinically.

Epididymo-orchitis

Rarely, BCG-related inflammation or infection can involve the epididymis or testis.

Upper urinary tract involvement

Granulomatous infection of the kidney is uncommon but recognised.

BCG infection

Localised or systemic infection with Mycobacterium bovis can occur.

BCG sepsis

This is a rare but potentially life-threatening complication.

A patient who becomes systemically unwell with persistent high fever, rigors, hypotension, respiratory symptoms or other features of sepsis following BCG requires urgent medical assessment.

Treatment may require hospital admission, infectious diseases involvement, anti-mycobacterial therapy and other supportive treatment.

BCG should therefore be respected. It is an extraordinarily useful treatment, but it is not simply another bladder wash.


What if BCG is poorly tolerated?

Treatment does not always have to proceed according to the calendar regardless of symptoms.

Depending upon severity, management can include:

  • Postponing the next instillation
  • Symptomatic treatment
  • Investigation for bacterial urinary infection
  • Assessment for BCG-related infection
  • Dose modification in selected circumstances
  • Discontinuation of BCG when toxicity becomes unacceptable

Persistent significant symptoms should be assessed rather than repeatedly giving further BCG and hoping the bladder eventually stops protesting.


What if the cancer returns after BCG?

This is one of the most important aspects of BCG treatment.

Not every recurrence after BCG means the same thing. The timing, pathology and amount of previous BCG exposure all matter.

Terms such as:

  • BCG-exposed
  • BCG-relapsing
  • BCG-refractory
  • BCG-unresponsive

describe different clinical situations.

Of these, BCG-unresponsive disease is particularly important because these tumours are unlikely to benefit from simply giving more BCG.

Current guidelines recommend radical cystectomy as the oncologically preferred treatment for appropriate patients with BCG-unresponsive high-grade disease.


When should radical cystectomy be considered?

BCG is intended to preserve the bladder, but preserving the bladder should never become more important than controlling the cancer.

Early radical cystectomy should be discussed in patients with very-high-risk features such as:

  • Persistent high-grade T1 disease
  • Recurrent high-grade disease despite adequate BCG
  • BCG-unresponsive disease
  • T1 disease associated with CIS
  • Certain variant histologies
  • Lymphovascular invasion
  • Extensive or multifocal high-grade disease
  • Other features suggesting a particularly high risk of progression

For very-high-risk NMIBC, current EAU guidance recommends discussing radical cystectomy upfront. BCG for one to three years remains an option for appropriately selected patients, particularly those who decline cystectomy or are medically unsuitable for major surgery.

Delaying cystectomy in a biologically aggressive tumour that is clearly failing BCG may compromise cancer outcomes.


Are there alternatives when BCG fails?

For patients with BCG-unresponsive disease who are unable or unwilling to undergo radical cystectomy, bladder-preserving alternatives are evolving rapidly.

Depending upon availability, tumour characteristics and local regulatory approval, options may include:

  • Sequential intravesical gemcitabine/docetaxel
  • Other intravesical chemotherapy combinations
  • Novel intravesical therapies
  • Systemic immunotherapy for selected CIS
  • Gene-based intravesical therapy in jurisdictions where available
  • Device-assisted intravesical therapy
  • Clinical trials

These treatments should not automatically be considered equivalent substitutes for radical cystectomy in a surgically fit patient with genuinely BCG-unresponsive aggressive disease. The risk of progression needs to remain at the centre of the decision.


Surveillance after BCG

BCG treatment does not eliminate the need for careful surveillance.

High-risk bladder cancer requires long-term follow-up because recurrence can occur even after an excellent initial response.

Follow-up generally involves:

Cystoscopy + urine cytology

initially at approximately 3 months, with subsequent surveillance determined by tumour risk and previous findings.

High-risk patients typically undergo frequent cystoscopy during the first two years, with gradually increasing intervals thereafter if they remain disease-free.

Periodic upper urinary tract imaging is also appropriate because high-risk urothelial carcinoma can occasionally develop within the ureters or kidneys.

Surveillance is usually long term and, for high-risk disease, often lifelong.


A practical BCG pathway

A typical pathway for high-risk non-muscle-invasive urothelial carcinoma is:

TURBT

↓

Histological confirmation of high-risk NMIBC

↓

Repeat TURBT when indicated, particularly high-grade T1 disease

↓

BCG induction: weekly × 6

↓

Cystoscopy + cytology and assessment of response

↓

If responding:

Maintenance BCG

3 weekly treatments at 3, 6 and 12 months, with continued maintenance to as long as 36 months in appropriate high-risk patients.

↓

Long-term cystoscopic surveillance

If persistent or recurrent high-grade disease:

Re-stage the bladder and determine whether the tumour represents BCG-unresponsive disease.

↓

Discuss radical cystectomy versus carefully selected bladder-preserving alternatives/clinical trials where appropriate.


The bottom line

Intravesical BCG remains a cornerstone of treatment for high-risk non-muscle-invasive urothelial carcinoma of the bladder.

Its strength lies in stimulating a powerful local immune response that reduces recurrence and helps prevent progression of aggressive superficial bladder cancer.

The usual treatment begins with six weekly instillations, followed by maintenance therapy for appropriately responding high-risk patients.

But BCG is not appropriate for every bladder tumour, and it should not be continued indefinitely when aggressive cancer is clearly failing treatment.

The most important principle is therefore not simply:

“Can we preserve the bladder?”

It is:

“Can we preserve the bladder safely without compromising cancer control?”

For patients with very-high-risk or BCG-unresponsive disease, timely discussion of radical cystectomy can be every bit as important as the BCG treatment itself.


This information is intended as general patient education and does not replace individual assessment by a urologist. BCG protocols, product availability and management of BCG-resistant disease may vary between patients and treatment centres.

Superficial Urothelial Carcinoma of the Bladder

Understanding non-muscle-invasive bladder cancer, TURBT, intravesical therapy and long-term surveillance

Being told that you have a bladder tumour is understandably alarming. The reassuring part is that many bladder cancers are discovered while they are still confined to the inner layers of the bladder and have not invaded the bladder muscle.

This is called non-muscle-invasive bladder cancer (NMIBC), historically referred to as superficial bladder cancer. NMIBC includes Ta tumours, T1 tumours and carcinoma in situ (CIS). These tumours behave very differently depending on their stage, grade and other pathological features, so treatment is tailored according to the risk of the cancer coming back (recurrence) or becoming more aggressive (progression).

The good news is that most NMIBC can initially be treated through the urethra without making an incision in the abdomen. The less convenient news is that bladder cancer has a habit of returning, which is why careful surveillance becomes an important part of treatment.


What is urothelial carcinoma?

The inside of the bladder is lined by specialised cells called urothelial cells. Cancer arising from these cells is known as urothelial carcinoma.

Urothelial carcinoma can develop anywhere along the urinary tract, including the:

  • renal collecting system
  • ureters
  • bladder
  • urethra

The bladder is by far the most common site.

When a bladder tumour has not invaded the muscular wall of the bladder, it is classified as non-muscle-invasive bladder cancer.

https://images.openai.com/static-rsc-4/y3Nkc3nnwnLWbduLwtOBo9wlGDPYvlRZ3hqmZmerWsmC4HUjhpIEvsXgWPs9IwZOQ9PLgJllQH1edLQmAni1U_538dO2IEbu48myP0AM4El4gyVQqzEuJjxyZdTq2Ak6qThyv190dh_MhP59fXKNJByHY8EL-AhSnzHK3LUJq2tbc5vhmHhLL8WBeJitn-Wb?purpose=fullsize


What causes bladder cancer?

There is rarely one identifiable cause. Instead, bladder cancer develops following genetic changes within urothelial cells, often influenced by environmental exposures over many years.

Smoking

Cigarette smoking is the most important preventable risk factor for bladder cancer.

Chemicals absorbed through cigarette smoke enter the bloodstream, are filtered by the kidneys and eventually become concentrated in the urine. The bladder lining is therefore repeatedly exposed to these carcinogens.

Stopping smoking after a bladder cancer diagnosis is strongly encouraged.

Other risk factors

These include:

  • increasing age
  • occupational exposure to certain industrial chemicals
  • previous pelvic radiotherapy
  • previous treatment with cyclophosphamide
  • chronic urinary tract irritation in selected circumstances
  • a personal history of urothelial carcinoma

Sometimes there is no obvious risk factor at all.


How does bladder cancer present?

Blood in the urine

The classic presentation is haematuria, or blood in the urine.

This may be:

Visible haematuria

The urine may suddenly become:

  • pink
  • red
  • burgundy
  • tea-coloured
  • or contain blood clots

Importantly, bleeding from a bladder tumour is frequently painless and intermittent.

The bleeding may disappear completely for days, weeks or even months. Its disappearance does not necessarily mean that the underlying problem has resolved.

Unexplained visible haematuria should always be investigated.

Microscopic haematuria

Sometimes blood is detected only on urine testing and cannot be seen with the naked eye.


Other possible symptoms

Some patients, particularly those with carcinoma in situ (CIS), may experience bladder irritation rather than obvious bleeding.

Symptoms can include:

  • urinary frequency
  • urgency
  • burning when passing urine
  • nocturia
  • pelvic or bladder discomfort
  • recurrent symptoms resembling a urinary tract infection

Persistent urinary symptoms with repeatedly negative urine cultures may therefore warrant further investigation.


Investigating suspected bladder cancer

The investigation usually involves a combination of urine testing, imaging and direct examination of the bladder.

Urine testing

A urine sample may be checked for:

  • blood
  • infection
  • inflammatory cells
  • abnormal malignant cells

Urine cytology

Urine cytology examines cells shed from the urinary tract under a microscope.

It is particularly useful for detecting high-grade urothelial carcinoma and CIS, but is considerably less sensitive for low-grade tumours.

A negative cytology therefore does not exclude bladder cancer.


Imaging the urinary tract

Patients with haematuria may require imaging of the kidneys, ureters and bladder.

Depending on the clinical circumstances, this may include:

  • renal tract ultrasound
  • CT urinary tract imaging
  • CT urography

CT urography is particularly useful when investigating haematuria because urothelial carcinoma can occasionally arise within the renal collecting system or ureters as well as the bladder.


Cystoscopy

A cystoscopy allows the urologist to look directly inside the bladder.

A thin flexible telescope is passed through the urethra, usually under local anaesthetic.

Most bladder tumours have a characteristic appearance. They may resemble delicate fronds, seaweed or a tiny underwater cauliflower attached to the bladder wall.

Flat lesions such as CIS can be much more difficult to see.

If a suspicious lesion is identified, the next step is usually a transurethral resection of bladder tumour (TURBT).


TURBT: biopsy and removal of the bladder tumour

TURBT stands for:

Transurethral Resection of Bladder Tumour

This procedure serves two important purposes:

  1. Treatment: removing all visible tumour where possible.
  2. Diagnosis and staging: providing tissue for the pathologist to determine exactly what type of tumour is present and how deeply it has invaded.

The procedure is usually performed under general or spinal anaesthesia.

A telescope called a resectoscope is passed through the urethra into the bladder. The tumour is carefully removed, usually using an electrical or bipolar resection system.

There is therefore generally no external incision or abdominal scar.


Why obtaining bladder muscle matters

An adequate TURBT should establish how deeply the tumour extends.

For many tumours, particularly T1 and high-grade lesions, the specimen should contain muscularis propria (detrusor muscle) so that the pathologist can determine whether the cancer has reached the muscle layer. The pathological report should document the presence and involvement of muscularis propria where applicable.

This distinction dramatically changes treatment.


Understanding bladder cancer staging

A simplified view of the bladder wall is:

Urine

↓

Urothelium

↓

Lamina propria

↓

Detrusor muscle

↓

Fat surrounding the bladder

The important early stages are:

Ta

The tumour is confined to the urothelial surface and has not invaded the supporting tissue underneath.

Tis: carcinoma in situ

CIS is a flat, high-grade malignant lesion confined to the urothelium.

Unlike the typical papillary bladder tumour, CIS may be difficult to identify visually.

Despite being superficial anatomically, CIS is biologically aggressive and requires appropriate treatment.

T1

The tumour has invaded into the lamina propria, but has not invaded the muscularis propria.

T1 disease, particularly high-grade T1 disease, carries a greater risk of recurrence and progression.

T2

The cancer has invaded the bladder muscle.

Once muscle invasion is identified, the disease is no longer classified as NMIBC and requires a different treatment pathway.


Stage and grade are not the same thing

This distinction frequently causes confusion.

Stage describes how deeply the cancer has travelled into the bladder wall.

Grade describes how abnormal and biologically aggressive the cancer cells appear under the microscope.

A tumour may therefore be superficial but still be high grade.

Broadly, urothelial tumours are classified as:

Low grade

These generally grow more slowly and have a relatively low risk of progressing to muscle-invasive cancer, although they may recur.

High grade

These cells look significantly abnormal and have a greater potential for:

  • recurrence
  • invasion
  • progression
  • spread beyond the bladder

Risk stratification

Following TURBT, the tumour is classified into a risk category.

Risk assessment considers factors such as:

  • stage
  • grade
  • tumour size
  • number of tumours
  • previous recurrence rate
  • presence of CIS
  • T1 disease
  • pathological features including lymphovascular invasion
  • certain variant histological subtypes

This classification helps determine whether the patient requires:

TURBT alone → intravesical chemotherapy → BCG → or, in selected very-high-risk situations, consideration of radical cystectomy.

Modern guidelines emphasise risk-adapted rather than one-size-fits-all management.


Do I need another TURBT?

Sometimes.

A second-look or re-staging TURBT may be recommended when:

  • the initial tumour was incompletely removed
  • adequate muscle was not present in an important specimen
  • high-grade disease is present in selected circumstances
  • T1 disease is identified
  • there is concern that the original tumour may have been understaged
  • certain variant histologies are identified

The aim is to ensure that residual tumour has not been left behind and, crucially, that muscle-invasive disease has not been missed.


Intravesical treatment

Intravesical simply means that medication is placed directly into the bladder through a catheter.

This allows the treatment to come into direct contact with the bladder lining while reducing systemic exposure compared with intravenous chemotherapy.

Two important treatments are:

Mitomycin C

and

BCG

They are not interchangeable and are used for different risk groups.


Intravesical Mitomycin C

Mitomycin C is a chemotherapy drug that can be placed directly into the bladder.

Immediate Mitomycin C following TURBT

For appropriate patients with suspected low- or intermediate-risk NMIBC, a single postoperative instillation of intravesical chemotherapy may be given soon after TURBT.

Current guidelines recommend that, when used, the immediate instillation should generally occur within 24 hours of TURBT.

Its purpose is to destroy microscopic tumour cells remaining in the bladder and tumour cells released during the resection.

This reduces the risk of recurrence.

When should immediate Mitomycin C be avoided?

It should generally not be administered if there is:

  • suspected bladder perforation
  • significant bleeding requiring bladder irrigation
  • an extensive or very deep resection where perforation is a concern

This is important because chemotherapy leaking outside the bladder can cause significant local tissue injury.


Further courses of intravesical chemotherapy

Selected patients with recurrent or intermediate-risk low-grade NMIBC may receive a course of intravesical chemotherapy rather than simply a single postoperative dose.

The exact drug, schedule and duration depend upon the tumour risk profile and local treatment protocols.


Side effects of intravesical Mitomycin C

Most patients tolerate treatment reasonably well.

Possible side effects include:

  • urinary frequency
  • urgency
  • burning
  • bladder discomfort
  • haematuria
  • chemical cystitis
  • skin irritation if the medication contacts the genital skin

Rarely, severe bladder inflammation or tissue injury can occur.


Intravesical BCG

BCG stands for Bacillus Calmette-Guérin.

Yes, it originated as a tuberculosis vaccine. In the bladder it performs a completely different job.

BCG stimulates a powerful local immune response against urothelial cancer cells and remains one of the most effective bladder-preserving treatments for high-risk NMIBC.


Who should receive BCG?

BCG is principally considered for patients with:

  • high-grade Ta tumours
  • high-grade T1 tumours
  • carcinoma in situ
  • other appropriately selected high-risk or intermediate-risk NMIBC

For high-risk NMIBC, full-dose BCG with maintenance treatment for one to three years remains a guideline-supported treatment, while immediate radical cystectomy should also be discussed in appropriate high-risk and particularly very-high-risk disease.


How is BCG given?

BCG is inserted into the bladder through a small catheter.

A typical induction course consists of:

One treatment per week for six weeks.

The solution is retained within the bladder for a prescribed period and then passed out in the urine.

Patients who respond may subsequently receive maintenance BCG.

A commonly used maintenance approach involves three weekly treatments at defined intervals after induction. In high-risk disease, guideline schedules may continue maintenance for up to three years depending upon tumour risk, treatment tolerance and BCG availability.


When should BCG not be given?

BCG is a live attenuated organism and must be administered carefully.

Treatment should generally be postponed in patients with:

  • visible haematuria
  • symptomatic urinary tract infection
  • traumatic catheterisation
  • very recent TURBT

The EAU lists the first two weeks following TURBT, visible haematuria, traumatic catheterisation and symptomatic urinary infection as absolute contraindications to an intravesical BCG instillation.


Side effects of BCG

A degree of bladder irritation is common.

Patients may experience:

  • frequency
  • urgency
  • burning
  • bladder discomfort
  • mild haematuria
  • fatigue
  • low-grade fever
  • flu-like symptoms

These symptoms usually settle.

Rarely, BCG can cause a more significant systemic infection or inflammatory reaction.

Persistent high fever, chills, marked deterioration or severe illness following BCG requires urgent medical assessment.


What if BCG does not work?

Persistent or recurrent high-grade cancer despite adequate BCG treatment requires careful reassessment.

This situation should not simply be managed by repeatedly giving more BCG indefinitely.

Patients meeting criteria for BCG-unresponsive NMIBC should be counselled regarding further treatment, and radical cystectomy remains the oncological standard for suitable patients with BCG-unresponsive high-risk disease. Bladder-preserving alternatives may be considered for patients who are medically unsuitable for cystectomy or decline surgery, ideally within appropriate specialist or clinical-trial pathways.


When should radical cystectomy be considered?

Most patients with superficial bladder cancer will never require removal of their bladder.

However, early radical cystectomy may be discussed for very-high-risk disease, including selected patients with:

  • aggressive high-grade T1 disease
  • associated CIS
  • variant histology
  • lymphovascular invasion
  • persistent high-grade disease
  • BCG-unresponsive disease
  • other features associated with a high risk of progression

The decision involves balancing the risks of major surgery against the danger of allowing biologically aggressive disease to progress.


Surveillance after treatment

Removing the tumour is only the first chapter.

NMIBC has a significant tendency to recur, and some high-risk tumours can progress. Consequently, regular cystoscopic surveillance is essential.

The first surveillance cystoscopy is generally performed approximately three months after TURBT.

After this, surveillance is tailored to the patient’s risk category.

A practical risk-adapted surveillance framework

Risk group Typical cystoscopy schedule Cytology Upper tract imaging
Low risk 3 months, 12 months, then annually Usually not routinely required Not routinely required
Intermediate risk 3 months, then approximately every 6 months for 2 years, then annually Risk-dependent Selected patients
High / very high risk Approximately every 3 months initially, with intervals gradually extended Usually included Periodic upper urinary tract imaging

The 2026 EAU guidance continues to recommend that follow-up intensity and duration be determined by the patient’s risk category, with the first cystoscopy at three months.

Individual surveillance schedules may differ depending on pathology, previous recurrences, treatment response, age, comorbidities and the treating urologist’s protocol.


Why is surveillance so important?

A recurrence does not automatically mean that treatment has failed or that the cancer has become life-threatening.

Low-grade papillary tumours may recur while remaining superficial and biologically low risk.

The purpose of surveillance is to identify recurrence early, while it can still be treated appropriately.

High-grade disease requires closer attention because the consequences of missing progression are considerably greater.


Can bladder cancer come back after years?

Yes.

This is why follow-up for intermediate- and particularly high-risk NMIBC can continue for many years.

The frequency of cystoscopy usually decreases when repeated examinations remain clear, but high-risk patients generally require prolonged surveillance.


What can I do after a diagnosis?

One of the most important modifiable factors is:

Stop smoking

Smoking cessation reduces exposure to the carcinogens responsible for many urothelial cancers and provides substantial additional cardiovascular, respiratory and general health benefits.

Patients should also:

  • attend every scheduled cystoscopy
  • report recurrent visible haematuria
  • complete prescribed intravesical treatment
  • report significant side effects from BCG or chemotherapy
  • maintain appropriate hydration unless medically restricted
  • discuss occupational chemical exposure where relevant

The bottom line

Non-muscle-invasive urothelial carcinoma is bladder cancer that has not invaded the muscular wall of the bladder.

The pathway typically involves:

Haematuria or urinary symptoms
↓
Urine tests + imaging
↓
Cystoscopy
↓
TURBT and pathological examination
↓
Stage + grade + risk classification
↓
Risk-adapted treatment

For some patients, TURBT followed by surveillance may be sufficient.

Others benefit from intravesical Mitomycin C or another intravesical chemotherapy to reduce recurrence.

Patients with high-grade disease, T1 cancer or CIS frequently require intravesical BCG, usually incorporating induction and maintenance treatment.

Very-high-risk or BCG-unresponsive disease may require consideration of radical cystectomy.

Most importantly, bladder cancer treatment does not finish when the initial tumour has been removed. Long-term cystoscopic surveillance is an integral part of treatment.

A final word

Bladder cancer can be a persistent visitor, but surveillance means we do not leave the front door unattended.

Early detection, complete TURBT, accurate pathological staging, appropriate intravesical therapy and structured follow-up provide the best opportunity to keep non-muscle-invasive bladder cancer under control.

This information is intended as general patient education and does not replace individual assessment or treatment advice from your urologist. Management should be tailored to the pathology, tumour risk category, general health and individual circumstances of each patient.

Pelvic Floor Rehabilitation Before and After Prostate Surgery

Preparing the Pelvic Floor for Recovery

Urinary leakage is one of the most common concerns men have when preparing for prostate surgery, particularly radical prostatectomy for prostate cancer. Fortunately, urinary control usually improves progressively after surgery, and pelvic floor rehabilitation can play an important role in helping men regain continence.

Pelvic floor rehabilitation is more than simply “doing Kegels”. It involves learning which muscles to use, how to contract them correctly, when to relax them, and how to incorporate them into everyday activities.

Importantly, more exercise is not necessarily better. The aim is a pelvic floor that is strong, coordinated and responsive, rather than one that is constantly clenched.


What Is the Male Pelvic Floor?

The pelvic floor is a group of muscles forming a supportive sling beneath the pelvis. These muscles contribute to:

  • urinary continence;
  • bowel control;
  • support of the pelvic organs;
  • sexual function; and
  • control of pressure generated during coughing, lifting and physical activity.

After radical prostatectomy, the anatomy of the urinary continence mechanism changes. The prostate and prostatic urethra are removed and the bladder is reconnected to the remaining urethra. Urinary control consequently becomes more dependent upon the remaining urinary sphincter and its supporting pelvic floor musculature.

This is why pelvic floor rehabilitation is particularly relevant after prostate cancer surgery.


Why Start Pelvic Floor Rehabilitation Before Surgery?

Ideally, pelvic floor rehabilitation begins before the operation.

The principal advantage of pre-operative training is not necessarily building dramatically stronger muscles. Rather, it gives the patient an opportunity to identify and correctly activate the pelvic floor before surgery, when there is no catheter, discomfort or postoperative urinary leakage.

Evidence regarding whether pre-operative pelvic floor muscle training independently improves long-term continence rates is mixed. Current European guidelines conclude that pre-operative training has not consistently demonstrated an additional long-term benefit. However, pelvic floor muscle training after radical prostatectomy may shorten the time taken to recover continence.

For many patients, a consultation with a physiotherapist experienced in men’s pelvic health before surgery is therefore useful.


Finding the Correct Pelvic Floor Muscles

A pelvic floor contraction should feel as though you are trying to:

stop yourself passing wind while simultaneously shortening or drawing the penis slightly inward and lifting the scrotum.

The movement should be subtle.

During the contraction:

  • continue breathing normally;
  • avoid holding your breath;
  • keep the abdomen relatively relaxed;
  • avoid strongly squeezing the buttocks;
  • avoid excessive tightening of the thighs; and
  • completely relax the pelvic floor between contractions.

Some men find the correct muscles immediately. Others inadvertently brace their abdominal, buttock or thigh muscles.

This is one reason why an assessment by a pelvic floor physiotherapist can be valuable.

Should I stop my urine flow to find the muscles?

Stopping the urinary stream once can sometimes help identify the muscles involved, but repeatedly practising pelvic floor exercises by interrupting urination is generally not recommended.

Regularly stopping and starting the stream can interfere with normal bladder emptying.


A Practical Pelvic Floor Exercise Programme

There is no single exercise prescription that is perfect for every man. Pelvic floor strength, endurance, coordination and postoperative continence vary considerably.

A physiotherapist may therefore modify the programme according to your examination and progress.

A typical programme contains several components.

1. Slow contractions: strength and endurance

Gently contract and lift the pelvic floor.

Hold the contraction for approximately:

5–10 seconds

Then relax completely for approximately:

5–10 seconds

Repeat approximately:

8–10 times

The quality of the contraction is more important than achieving a particular number.

If you can only maintain a good contraction for three seconds initially, three good seconds are preferable to ten seconds of straining.


2. Quick contractions

The urinary sphincter also needs to react rapidly.

Contract the pelvic floor firmly for approximately one second, then completely release it.

Repeat:

5–10 times

These faster contractions help train the pelvic floor to respond to sudden increases in abdominal pressure.


3. The “Knack”

One of the most useful techniques is learning to contract the pelvic floor immediately before an activity that normally produces leakage.

For example, gently activate the pelvic floor just before:

  • coughing;
  • sneezing;
  • standing from a chair;
  • bending;
  • lifting;
  • getting out of a car; or
  • performing physical exercise.

This anticipatory contraction is sometimes called the Knack.

It turns pelvic floor training from an isolated exercise into a functional skill.


How Often Should I Exercise?

This is where the principle of quality rather than quantity becomes important.

For many men, a structured programme performed two to three times per day is sufficient during active rehabilitation.

A session might consist of:

8–10 controlled slow contractions followed by 5–10 quick contractions.

However, this should not be regarded as a universal prescription. Your physiotherapist or surgeon may recommend a different programme according to your muscle strength, continence and ability to relax the pelvic floor.

The pelvic floor is skeletal muscle. Like other muscles, it needs work, recovery and progression.

Doing hundreds of contractions every day is rarely necessary.


Can You Do Too Many Pelvic Floor Exercises?

Yes.

One of the common misconceptions after prostate surgery is:

“If ten exercises are good, one hundred must be better.”

Unfortunately, pelvic floor muscles can become fatigued just like any other muscle.

Excessive training or constantly holding the pelvic floor contracted can potentially cause:

  • pelvic or perineal discomfort;
  • difficulty relaxing the pelvic floor;
  • urinary urgency;
  • difficulty starting urination;
  • interrupted urinary flow;
  • a sensation of incomplete bladder emptying;
  • pelvic muscle fatigue; and
  • occasionally worsening leakage later in the day as the muscles tire.

A healthy pelvic floor needs to be able to contract strongly and relax completely.

Continence does not require walking around all day with the pelvic floor permanently switched on.


How Do I Know When I Am Doing Enough?

Your programme is probably adequate when you can:

  • identify the pelvic floor reliably;
  • contract it without excessive abdominal or buttock activity;
  • maintain several controlled contractions without losing strength;
  • completely relax between contractions;
  • activate the muscles quickly before coughing or lifting; and
  • progressively incorporate pelvic floor control into normal activities.

Progress after prostatectomy is often better measured by continence rather than the number of exercises performed.

Useful measures include:

  • number of pads used each day;
  • degree of pad wetness;
  • a 24-hour pad-weight test;
  • leakage during walking or exercise;
  • ability to remain dry overnight;
  • ability to reach the toilet without leakage; and
  • changes over several weeks rather than from one day to the next.

When Should Exercises Restart After Surgery?

Follow the instructions given by your surgeon.

Pelvic floor contractions are usually stopped while the urinary catheter is in place.

Training can generally recommence after catheter removal once your surgical team considers it appropriate. European guidance notes that pelvic floor muscle training is commonly started approximately 7–10 days after catheter removal, although individual postoperative protocols vary.

Early exercises should be gentle.

This is not the time to test how hard you can squeeze.

As healing progresses, the programme can gradually move from basic contractions to functional training while standing, walking, coughing, lifting and exercising.


What Should I Expect After the Catheter Comes Out?

The first few days can be confronting.

Some men have relatively little leakage immediately. Others experience considerable leakage, particularly when:

  • standing;
  • walking;
  • coughing;
  • exercising;
  • getting out of a chair; or
  • becoming tired later in the day.

This does not necessarily predict the final outcome.

Continence often improves substantially during the first weeks and months following radical prostatectomy.

Recovery is a marathon measured in millilitres rather than kilometres.


How Successful Is Pelvic Floor Physiotherapy?

This question is more complicated than it initially appears.

Urinary continence frequently improves naturally following prostatectomy, making it difficult for studies to separate the effect of pelvic floor physiotherapy from normal postoperative recovery.

The research is consequently mixed.

The European Association of Urology notes that systematic reviews and trials suggest pelvic floor muscle training can shorten the time to continence recovery, although the evidence regarding supervised training, biofeedback and additional therapies remains inconsistent.

For example, one randomised study cited by the EAU compared supervised physiotherapist-directed pelvic floor training with verbal and written instructions. At 12 months, complete pad-free continence was reported in 65.2% of the supervised group versus 31.6% of the comparison group. This result should not be interpreted as the expected success rate for every patient, because continence definitions, surgical techniques and rehabilitation programmes differ considerably between studies.

A 2023 Cochrane review was considerably more cautious. After reviewing 25 trials, the authors concluded that uncertainty remains regarding the magnitude of benefit from conservative treatments because studies vary considerably in their techniques, combinations of treatments and methodological quality.

The practical message is therefore:

Pelvic floor rehabilitation is an important first-line treatment and may accelerate recovery, but it cannot guarantee continence.


What If Pelvic Floor Exercises Are Not Working?

Persistent leakage does not automatically mean you need to exercise harder.

If continence is failing to improve, the first question should be:

Why am I leaking?

Post-prostatectomy urinary incontinence may result from:

  • weakness of the urinary sphincter;
  • bladder overactivity;
  • urinary urgency;
  • incomplete bladder emptying;
  • bladder-neck or urethral narrowing;
  • a combination of stress and urgency incontinence; or
  • less commonly, other urinary tract problems.

The AUA guideline emphasises distinguishing stress incontinence, where leakage occurs with coughing, walking, lifting or exertion, from urgency incontinence, where leakage accompanies a sudden compelling desire to urinate.

No amount of extra squeezing will correct every one of these problems.


When Should Further Investigation Be Considered?

Further assessment may be appropriate when urinary leakage is:

  • severe;
  • worsening rather than improving;
  • associated with difficulty urinating;
  • associated with significant urgency or frequency;
  • persistent despite appropriate rehabilitation; or
  • sufficiently troublesome that surgical treatment is being considered.

Assessment may include:

Bladder diary

Records fluid intake, urinary frequency, urinary volumes and leakage episodes.

Pad-weight testing

Provides an objective measurement of the amount of urine being lost.

Urinary flow measurement and bladder ultrasound

Can identify poor urinary flow or incomplete bladder emptying.

Cystoscopy

May be recommended when urethral or bladder-neck pathology is suspected.

Urodynamic studies

Can sometimes help distinguish sphincter weakness from bladder dysfunction when the cause of persistent leakage is uncertain or before further treatment.


What Alternatives Are Available if Physiotherapy Is Not Enough?

Pelvic floor rehabilitation is only one part of managing post-prostatectomy incontinence.

Lifestyle and bladder strategies

These may include:

  • appropriate fluid intake;
  • reducing excessive caffeine;
  • avoiding constipation;
  • weight management where appropriate;
  • bladder training;
  • management of urinary urgency; and
  • modifying activities that provoke significant leakage during early recovery.

Continence pads

Modern male continence pads provide discreet protection while continence is recovering.

Using pads does not mean rehabilitation has failed. They are simply a tool for allowing normal activity during recovery.

Penile compression devices

A penile clamp can temporarily reduce leakage in selected men, although these devices must be fitted and used correctly and released regularly to avoid excessive pressure or tissue injury.

Medication

Medication does not generally correct true post-prostatectomy sphincter weakness.

However, medication may be useful when overactive bladder or urinary urgency contributes significantly to leakage.

Biofeedback

Biofeedback can help some patients understand whether they are contracting the correct muscles and how effectively they are doing so.

Electrical stimulation

Electrical stimulation has also been investigated. Some studies suggest an early benefit when combined with pelvic floor training, although evidence remains inconsistent.


When Is Surgery Considered?

A small proportion of men continue to experience significant stress urinary incontinence despite adequate healing and rehabilitation.

If the leakage remains bothersome, further treatment should be discussed rather than simply continuing increasingly intensive pelvic floor exercises indefinitely.

The two principal surgical options are:

Male Sling

A male sling supports and repositions the urethral continence mechanism.

It is generally most suitable for selected men with mild to moderate stress urinary incontinence and adequate residual sphincter function.

Results tend to be less favourable when incontinence is severe. The AUA guideline specifically notes that male sling outcomes are poorer in men with severe sphincteric incontinence.

Artificial Urinary Sphincter

The artificial urinary sphincter (AUS) remains an important treatment for moderate to severe post-prostatectomy stress urinary incontinence.

A fluid-filled cuff is placed around the urethra and controlled by a small pump positioned within the scrotum. The patient operates the pump when he wishes to urinate.

Both male sling surgery and artificial urinary sphincter implantation can significantly reduce pad use and improve quality of life in appropriately selected men.


When Should I Stop Pelvic Floor Rehabilitation?

There is rarely a precise finishing date.

Once continence has returned and pelvic floor control is good, intensive rehabilitation can usually be reduced.

Many men transition from a rehabilitation programme to a simple maintenance programme, incorporating occasional pelvic floor exercises and functional contractions during activities that generate abdominal pressure.

If you are completely dry, have good pelvic floor control and can cough, lift and exercise without leakage, performing increasingly large numbers of exercises is unlikely to provide additional benefit.

The goal is not to become a professional Kegel athlete.

The goal is normal function.


The Bottom Line

Pelvic floor rehabilitation is an important component of recovery following radical prostatectomy.

Learning the technique before surgery can make it easier to identify and activate the correct muscles after the catheter is removed. Following surgery, a structured programme focusing on strength, endurance, rapid contractions, relaxation and functional activation may help accelerate the return of urinary control. Current evidence supports pelvic floor muscle training as part of postoperative management, while acknowledging that the precise additional benefit of intensive supervised physiotherapy remains uncertain.

Just as importantly, more is not always better. Persistent leakage should not automatically be treated with ever-increasing numbers of pelvic floor contractions.

If urinary incontinence remains troublesome despite appropriate rehabilitation, further assessment can determine whether the problem is persistent sphincter weakness, bladder dysfunction or another cause. Treatments ranging from bladder therapy and medication to a male sling or artificial urinary sphincter can then be considered.

A useful rule

Train the pelvic floor, don’t exhaust it.

Correct technique, consistency and functional control matter far more than the number of contractions performed.


This information is intended for general patient education and does not replace individual medical advice. The timing and intensity of pelvic floor rehabilitation should be discussed with your surgeon and/or a physiotherapist experienced in male pelvic health.