
Tag Archive for: urology brisbane

Movember and the digital rectal examination: does it still matter?

The digital rectal examination (DRE) has been part of prostate assessment for generations. It is also one of the tests men are most likely to dread, joke about, or avoid. As Movember prompts conversations about prostate health, it is worth asking what a DRE can actually tell us today and when it is useful.

The short answer: a DRE still has a place in clinical assessment, but it is not recommended as a routine add-on to PSA testing for every asymptomatic man. PSA blood testing is the main early-detection test. A DRE can add physical information in selected situations, and it remains one part of monitoring some men with known prostate cancer.

What is a DRE?

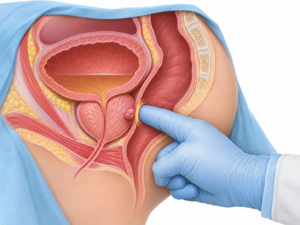
A DRE is a brief examination in which a clinician gently inserts a gloved, lubricated finger into the rectum to feel the back surface of the prostate. The clinician assesses features such as the prostate’s size, shape, firmness, symmetry and any distinct lump or irregular area. It may also give information about tenderness or other rectal findings.

The prostate sits in front of the rectum, so the examination can only feel part of the gland. It cannot reliably assess the whole prostate, and some cancers, particularly those in areas that cannot be reached by touch, may not be felt. A normal DRE therefore does not rule out prostate cancer.
What extra information can it provide?

PSA is a blood marker produced by prostate tissue. It helps estimate risk, but PSA alone does not show where a possible cancer is or how the prostate feels. A DRE gives the clinician a physical finding to interpret alongside the PSA result, symptoms, family history and, when indicated, MRI and biopsy.

A firm nodule, marked asymmetry, or an unusually hard or fixed-feeling area can increase concern and prompt further assessment, even if the PSA is not markedly raised. An abnormal DRE may also help estimate the clinical extent of a cancer and its likelihood of being more significant. But it is not a cancer diagnosis: benign enlargement, inflammation and examiner variation can affect what is felt. A suspicious finding usually needs further assessment, often including MRI and possibly biopsy.

DRE is not a substitute for PSA, MRI or biopsy. Nor does a normal examination provide a guarantee that cancer is absent.

Can it find cancers that produce little PSA?

Occasionally, prostate cancer is found after a suspicious DRE even when PSA is low. Some uncommon or poorly differentiated cancers can produce less PSA than expected. In the 2026 European Association of Urology guideline, a suspicious DRE with PSA at or below 4 ng/mL was associated with a positive predictive value ranging widely from 5% to 30% in the cited evidence. This shows why a distinctly abnormal examination should not automatically be dismissed because of a reassuring PSA.

That does not mean DRE is a dependable way to screen for low-PSA cancers. Many cancers cannot be felt, and DRE’s performance as a stand-alone screening test is limited. If symptoms, imaging or other clinical features raise concern, the clinician should consider the full picture rather than rely on either a normal PSA or a normal DRE alone.

Should every man having a PSA test also have a DRE?

No. The NHMRC-approved 2026 Guidelines for the Early Detection of Prostate Cancer in Australia suggest that DRE not be offered in primary care as a routine addition to PSA testing and risk assessment for asymptomatic men. The RACGP Red Book also advises against routine DRE as an addition to PSA testing in asymptomatic men seeking early detection.

This reflects evidence that routine DRE adds little to population early-detection pathways compared with PSA-based assessment, while it can create discomfort and deter some men from discussing testing. PSA testing itself is a choice to make after discussing potential benefits and harms with a GP; it is not an automatic test for everyone.

A DRE may still be appropriate when a person has symptoms, a concerning PSA result, an abnormality on imaging, or another clinical reason for a physical examination. A clinician should explain why it may help in that specific situation and discuss alternatives where appropriate.

What about men already on active surveillance?

Active surveillance is a monitoring approach for selected men with lower-risk prostate cancer, intended to identify evidence of meaningful change while avoiding or delaying treatment side effects when it is safe to do so.

The 2026 Australian guideline proposes periodic DRE alongside PSA measurements, MRI where appropriate and repeat biopsy when clinically indicated. A change in the examination may be one reason to bring forward MRI or biopsy. It is not, by itself, usually enough to decide that treatment should start. The European Association of Urology also includes DRE in surveillance protocols, while recognising that its frequency may be reduced in selected men with stable MRI and other reassuring findings. Monitoring plans vary with the cancer’s features, prior tests and the person’s circumstances.

Why is the DRE so famous, and why are some men apprehensive?

For many years, before PSA testing and prostate MRI were available, clinicians had fewer ways to assess the prostate. The DRE was a quick bedside examination that could identify a large or locally advanced abnormality. It became closely associated with “getting your prostate checked,” and popular culture has kept it in the spotlight.

When I discuss it with patients, I sometimes call DRE the “dreaded rectal examination” a little wordplay that can break the ice. It acknowledges the test’s reputation, but it is not a request to grin and bear it: I explain what I’m doing, ask permission, and stop if you ask.

The examination can feel intimate or embarrassing. Some men worry it will hurt, feel exposed, or be judged. Others have heard jokes that link the test to masculinity or sexuality. These concerns are understandable, but a DRE is a clinical examination; it says nothing about a person’s identity or sexuality. Many people find it awkward or uncomfortable rather than painful, although experiences differ.

You can ask the clinician to explain each step before starting, request a chaperone, discuss positioning, and ask them to stop at any time. Consent matters. You do not need to agree to an examination simply because you have come to talk about PSA testing.

What should I do this Movember?

If you are thinking about prostate testing, speak with your GP about your age, family history, health and preferences. Ask whether PSA testing is suitable for you and whether an examination would add useful information in your circumstances. If you have urinary symptoms, blood in your urine or semen, persistent unexplained pain, or another concern, arrange an assessment rather than waiting for a routine screening test.

Movember is a chance to make the conversation easier. The aim is not to insist that every man must have a DRE. It is to help each person understand the available tests, feel able to ask questions, and make an informed decision with their clinician.

This article provides general information and is not a substitute for personal medical advice.

References and further information

  1. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia. NHMRC-approved recommendations, 18 May 2026. See Recommendations 4.1 and 8.2.1.
  2. The Royal Australian College of General Practitioners. Guidelines for preventive activities in general practice, 10th edition — prostate cancer. Recommendations updated 28 June 2024.
  3. European Association of Urology. EAU Guidelines on Prostate Cancer: Diagnostic Evaluation, 2026 edition.
  4. European Association of Urology. EAU Guidelines on Prostate Cancer: Treatment and active-surveillance follow-up, 2026 edition.
  5. Sajjad W, et al. Comparing the Performance of Digital Rectal Examination and Prostate-specific Antigen as a Screening Test for Prostate Cancer: A Systematic Review and Meta-analysis. European Urology Oncology. 2024. PubMed.
Movember: Men’s mental health

Movember: Men’s mental health and suicide prevention in Australia

Content note: This article discusses suicide. If you are in immediate danger, call 000. Support contacts are listed below.

Movember gives us a visible reminder to talk about men’s health. The moustache can start a conversation, but the more important work is noticing when someone is struggling, listening without judgement and helping them connect with support.

Mental health difficulties are common, treatable and not a personal failure. Suicide is complex: it rarely has one cause, and a difficult period does not mean a person is destined to reach crisis. Timely support, connection and practical help can make a difference.

The Australian picture

The latest Australian Bureau of Statistics (ABS) release available for this article covers deaths registered in 2025. It recorded 3,283 deaths by suicide, including 2,425 males—73.9% of the total. The male age-standardised rate was 17.3 deaths per 100,000 males. The 2025 figures are preliminary and may be revised as coronial investigations are completed. [1]

Age-standardised rates allow comparisons between populations with different age structures. The age-specific rates below are deaths per 100,000 people in the same age group; they describe population patterns, not an individual’s likelihood of suicide.

Age group Male suicide rate in 2025 (per 100,000) What the ABS reported about recorded risk factors
15–24 9.5–18.1 (15–19: 9.5; 20–24: 18.1) Suicide ideation was the most commonly recorded risk factor for people under 25. For children aged 5–17, recorded factors also included education, family and peer relationships, social environment and prior self-harm.
25–44 19.7–26.0 (25–29: 19.7; 30–34: 23.1; 35–39: 26.0; 40–44: 23.3) Relationship circumstances were the most commonly recorded risk factor in this age range. Psychoactive substance use was also frequently recorded.
45–64 23.0–26.8 (45–49 was the peak at 26.8) Mood disorders, including depression, were the most commonly recorded risk factor for people aged 45–84.
65–84 16.2–22.8 Rates varied across these age bands; mood disorders were commonly recorded. Illness, pain and disability may also affect wellbeing and quality of life.
85 and over 24.9 Limitation of activities due to illness or disability was the most commonly recorded risk factor in this age group.

These age bands summarise the ABS’s five-year age data. In 2025, the highest male age-specific rate was among men aged 45–49 (26.8 per 100,000); the largest proportion of male deaths occurred among men aged 35–39 (10.7%). Both figures matter, but they measure different things. [1]

The ABS also records risk factors mentioned in preliminary death registrations. In 2025, the most frequently recorded factors across all people who died by suicide were mood disorders (35.8%), suicidal ideation (30.7%), problems in spousal relationship circumstances (26.7%), a personal history of self-harm (24.3%), and anxiety or stress-related disorders (21.9%). Several factors can be recorded for one person. These are not proof that any single factor caused a death, and the data may change as investigations are finalised. [1]

Mental health concerns can look different from one man to another

In the ABS National Study of Mental Health and Wellbeing, conducted in 2020–2022, 18.3% of males aged 16–85 reported a 12-month mental disorder. Anxiety disorders were reported by 13.3%, affective disorders (including depression) by 6.5%, and substance-use disorders by 4.4%. The equivalent substance-use figure for females was 2.1%. The survey found the highest prevalence of any 12-month mental disorder among males aged 16–24 (32.4%); prevalence declined across older age groups. These are survey estimates, not current-year suicide rates, and they do not mean that everyone with a mental disorder is suicidal. [2]

Depression and anxiety may involve persistent low mood, loss of interest, worry, panic, irritability, poor concentration, sleep changes or feeling overwhelmed. Some men describe distress mainly through anger, pulling away from family or friends, working excessively, taking more risks, or relying more heavily on alcohol or other drugs. These signs are not a diagnosis, but a lasting change from someone’s usual self is a good reason to check in. [3]

There is no single cause

Mental health and suicide risk develop through an interaction of individual, social and economic circumstances. A person may be affected by one issue or many at once. Factors that can contribute to distress include:

  • depression, anxiety, trauma, other mental health conditions or a previous episode of self-harm;
  • relationship conflict, separation, family stress, loneliness or bereavement;
  • financial pressure, unemployment, job insecurity, workplace stress or legal problems;
  • harmful alcohol or other drug use, which can worsen mood, judgement and coping;
  • chronic illness, pain, disability, sleep problems or loss of independence;
  • discrimination, bullying, violence, social exclusion or barriers to culturally safe care;
  • limited social support, or feeling unable to ask for help.

These are possible contributors, not a checklist that predicts what one person will do. A 2025 analysis of the Australian Ten to Men longitudinal study found that the onset of suicidal thoughts was associated with depressive symptoms, disability, financial stress, lower education, sexual orientation and a history of partner violence. The study also found that suicidal thoughts remitted for many men over time, an important reminder that suicidal thinking can change and support can help. Associations in a study do not establish that a factor causes an outcome. [4]

Ideas about having to cope alone or always appear strong can make it harder for some men to talk openly or seek help. This is not true of every man, and strength, responsibility and care for others can also support recovery. A 2025 Australian review found a broad range of formal and informal services for men, while noting that evidence about their effectiveness remains uneven. Services are more useful when they are accessible, respectful and responsive to the person in front of them. [5]

How to support a mate, partner or family member

Movember shares the ALEC approach, developed by R U OK?, as a simple guide for a supportive conversation: [6]

  • Ask how he is going and mention a change you have noticed: “You haven’t seemed yourself lately. How are things really going?”
  • Listen without judgement or rushing to solve everything. Give him time to speak.
  • Encourage action: offer to help contact a GP, counsellor or trusted person, or to go with him to an appointment.
  • Check in again. A message or planned catch-up can show that your support continues after the first conversation.

If you are worried he may be thinking about suicide, ask clearly and calmly whether he is thinking about suicide. Take the answer seriously. You do not need to manage the situation alone: involve a trusted person and contact a crisis service or health professional. If there is immediate danger, call 000 or go to an emergency department.

Getting help in Australia

  • Immediate danger: call 000 or attend an emergency department.
  • Lifeline: call 13 11 14 for 24/7 crisis support. [7]
  • Suicide Call Back Service: call 1300 659 467 for 24/7 telephone and online counselling. [8]
  • MensLine Australia: call 1300 78 99 78 for telephone and online counselling for men. [9]
  • Beyond Blue: call 1300 22 4636 for mental health support and information. [10]
  • Your GP: can discuss symptoms, safety, treatment options and referrals. If you are not sure where to start, a GP appointment is a practical first step.

If you are supporting someone, stay connected and help them access care. If you are struggling yourself, you deserve support too. You do not have to wait until things feel unbearable before reaching out.

A Movember conversation can matter

Movember’s focus on prevention, early intervention and social connection is a useful invitation to check in, not only during November, but throughout the year. The first conversation does not need to be perfect. Ask, listen, help with one next step and follow up.

This article is general information and is not a substitute for individual medical or mental health advice.

References

  1. Australian Bureau of Statistics. Intentional self-harm (suicide) deaths, 2025. Preliminary registered-death data; includes age-specific rates and risk factors.
  2. Australian Bureau of Statistics. National Study of Mental Health and Wellbeing, 2020–2022.
  3. Movember. Spot the signs of poor mental health.
  4. Haregu T, Armstrong G. Understanding the onset and remission of suicidal thoughts in Australian men: Findings from the Ten to Men study. Australian & New Zealand Journal of Psychiatry. 2025. doi:10.1177/00048674251333572.
  5. Slade A, Reily NM, Fujimoto H, et al. Men’s mental health and suicide prevention service landscape in Australia: a scoping review. BMC Public Health. 2025;25:1593. doi:10.1186/s12889-025-22676-6.
  6. Movember. ALEC conversation strategy. Movember credits R U OK? for developing the ALEC model.
  7. Lifeline Australia. Lifeline Crisis Support.
  8. Suicide Call Back Service. Get support.
  9. MensLine Australia. Contact MensLine.
  10. Beyond Blue. Men’s mental health.

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

A moustache can start a conversation. A conversation can sometimes save a life.

Every November, moustaches begin appearing on faces around Australia and across the world. Some are magnificent. Some are questionable. Some probably deserve their own urological assessment.

But behind the facial hair lies an important message.

Movember is about getting men talking about their health.

What began in Melbourne in 2003 with 30 men growing moustaches has developed into an international men’s health movement focusing particularly on prostate cancer, testicular cancer, mental health and suicide prevention. Movember reports that it has funded more than 1,320 men’s health projects around the world.

And few recent stories demonstrate the importance of men paying attention to their health better than that of King Charles III.


First, an important clarification: King Charles does NOT have prostate cancer

This point has frequently been confused in media and social-media discussions.

In January 2024, Buckingham Palace announced that King Charles was receiving treatment for an enlarged prostate.

This was benign prostatic enlargement, commonly called benign prostatic hyperplasia or BPH. It is extremely common as men get older and is not prostate cancer.

The King underwent a planned hospital procedure for his enlarged prostate.

During this episode of care, however, doctors identified a separate abnormality. Further investigations subsequently diagnosed a form of cancer.

Buckingham Palace specifically confirmed that the King’s cancer was not prostate cancer. The precise type of cancer has remained private.

That distinction matters.

But so does what happened next.


A prostate problem led to something else being discovered

The King’s story provides an interesting lesson for men’s health.

He sought medical attention for a prostate problem.

He underwent investigation and treatment.

During that process, doctors discovered another potentially important medical condition.

In February 2024 Buckingham Palace announced that the King had begun a programme of regular cancer treatments and temporarily reduced his public-facing duties.

By April 2024, following treatment and recuperation, he was able to return to public-facing duties.

The exact cancer treatment has never been publicly disclosed, and it would therefore be inappropriate to speculate whether he has received surgery, radiotherapy, chemotherapy, immunotherapy or another form of treatment.

More recently, the King has continued to speak publicly about his cancer experience. In December 2025 he announced that, following early diagnosis, treatment and adherence to medical advice, his treatment schedule could be reduced in the following year.

In June 2026 he and Queen Camilla hosted a reception marking the 125th anniversary of Cancer Research UK, of which the King has been Patron since 2024.

His message has increasingly centered on a simple theme:

Early diagnosis matters.


The other royal problem: an enlarged prostate

For a urologist, the first part of the King’s story is equally important.

An enlarged prostate is extraordinarily common.

As the prostate enlarges, it can compress the urethra and interfere with the passage of urine.

Men may notice:

  • a slower urinary stream
  • difficulty starting urination
  • stopping and starting
  • straining
  • feeling that the bladder has not emptied completely
  • getting up several times during the night
  • urgency or frequency
  • occasionally an inability to pass urine at all.

These symptoms do not automatically mean prostate cancer.

Most commonly they are associated with benign prostate enlargement.

But that does not mean they should simply be accepted as part of getting older.


“It’s probably just my prostate”

Possibly.

But that is precisely why it is worth having it checked.

Assessment of urinary symptoms may include a discussion about symptoms and medications, examination, urine testing, kidney function, PSA testing where appropriate, urinary flow measurement, ultrasound assessment of bladder emptying and occasionally further investigations.

The objective is not simply to find prostate cancer.

It is to work out why the urinary system is behaving differently.


What about prostate cancer?

This is where Movember becomes particularly relevant.

Prostate cancer remains the most commonly diagnosed cancer in Australian men. Australian Institute of Health and Welfare data indicate that prostate cancer accounted for approximately 28% of cancers diagnosed in Australian males in 2024.

AIHW’s updated projections estimate approximately 26,397 prostate cancer diagnoses in Australia during 2026, although it is important to recognise that this is a projection rather than a final observed case count.

Movember estimates that approximately one in five Australian men will be diagnosed with prostate cancer during their lifetime.

And there is another important difference between prostate cancer and benign enlargement:

Early prostate cancer frequently causes no urinary symptoms at all.

Waiting until something hurts or the urine flow deteriorates is therefore not an effective prostate cancer detection strategy.


The PSA conversation

A PSA blood test can help identify men who may require further investigation for prostate cancer.

But PSA is not simply a “cancer test”.

PSA can be elevated for several reasons, including:

  • benign prostate enlargement
  • prostatitis or inflammation
  • urinary infection
  • recent instrumentation
  • urinary retention
  • and prostate cancer.

An abnormal PSA therefore does not automatically mean cancer.

Similarly, decisions about PSA testing should consider a man’s age, family history, previous PSA results, general health and individual risk factors.

The important step is having the conversation with your GP or urologist rather than avoiding the subject altogether.


And if prostate cancer is found?

Modern prostate cancer treatment is no longer a simple choice between “operate” and “do nothing”.

Depending upon the PSA, MRI findings, biopsy grade, tumour volume, stage, age and general health of the patient, options may include:

Active surveillance for suitable low-risk disease.

Robotic-assisted radical prostatectomy for appropriate localised cancers.

Radiation therapy, sometimes combined with hormonal treatment.

Focal therapies in carefully selected patients and specialised settings.

Androgen deprivation and newer androgen-receptor targeted treatments for more advanced disease.

Chemotherapy and radioligand therapies for selected advanced cancers.

The right treatment is increasingly personalised to both the biology of the cancer and the priorities of the man sitting in front of us.


Treatment is not only about surviving cancer

This is another area in which organisations such as Movember have made an important contribution.

Men understandably want their cancer controlled.

But they also care about what happens afterwards.

Will I leak urine?

Will I still have erections?

What happens to ejaculation and orgasm?

Can I continue working?

How will treatment affect my relationship?

Will I still feel like myself?

Movember has invested not only in prostate cancer research but also in projects examining quality of life, urinary function, sexual function and outcomes following treatment. The Prostate Cancer Outcomes Registry Australia and New Zealand, for example, collects patient-reported outcomes including urinary, bowel and sexual function after prostate cancer diagnosis and treatment.

These aren’t embarrassing side issues.

They are part of treating the whole man.


So what does King Charles have to do with Movember?

Quite a lot, despite the fact that he does not have prostate cancer.

His story began with something millions of older men experience:

an enlarged prostate.

Instead of ignoring it, he sought treatment.

That interaction with the healthcare system resulted in another cancer being discovered.

And by publicly announcing his prostate treatment and subsequent cancer diagnosis, the King did something particularly useful for men’s health:

he made it easier to talk about it.

That is essentially what Movember has been trying to achieve for more than two decades.

A moustache is simply the billboard.

The conversation is the important bit.


My Movember message to men

If your urinary stream isn’t what it used to be, get it checked.

If you’re getting up repeatedly during the night, ask why.

If you’re struggling with erections, don’t be embarrassed to mention it.

If you notice a testicular lump, don’t wait.

If prostate cancer runs in your family, discuss your individual risk.

And if you’ve been putting off that conversation about PSA testing, perhaps Movember is a good time to have it.

Men are remarkably good at servicing cars, replacing batteries, checking tyre pressures and investigating strange noises coming from engines.

We are sometimes considerably less enthusiastic when the strange noise is coming from ourselves.

This Movember, grow the moustache if you wish.

But more importantly:

Have the conversation.
Know your prostate.
Know your risk.
And don’t ignore a change in your body simply because it’s embarrassing to talk about.

Your prostate may be small.

Its ability to cause trouble is disproportionately ambitious.


References and further reading

  1. The Royal Family. A Statement from Buckingham Palace. 5 February 2024. Buckingham Palace confirmed that a separate cancer was discovered during treatment for benign prostate enlargement.
  2. The Royal Family. The King returns to public-facing duties. April 2024.
  3. The Royal Family. A message from The King in support of Stand Up To Cancer. December 2025.
  4. The Royal Family. The King and Queen host a reception for Cancer Research UK. June 2026.
  5. Australian Institute of Health and Welfare. The health of men in Australia. Prostate cancer statistics and Australian cancer burden.
  6. Australian Institute of Health and Welfare. Cancer data in Australia: Prostate cancer projection method changes and updated long-term projections. Updated July 2026.
  7. Movember. Prostate Cancer: Prostate Cancer Action, Innovation & Collaboration. Australian prostate cancer statistics and research programs.
  8. Movember. Our Story. History of the Movember movement from Melbourne in 2003.
  9. Movember. Prostate Cancer Outcomes Registry Australia and New Zealand. Patient outcomes and quality-of-life research.

Medical disclaimer

This article provides general information and should not replace individual medical assessment. Urinary symptoms, an abnormal PSA or concerns about prostate cancer should be discussed with your GP or urologist.

Your Bladder and Your Bowels: The Connection Nobody Talks About

The bowel–bladder connection: how good bowel habits can support bladder health

When urinary urgency or leakage is troubling you, bowel habits may be the last thing on your mind. Yet the bowel and bladder share the limited space of the pelvis, the pelvic floor muscles and parts of their nerve supply. Constipation can contribute to urinary symptoms in some people, so bowel health is often worth discussing during a bladder assessment.

This does not mean that constipation explains every bladder problem. Infection, prostate or pelvic floor conditions, medication effects, neurological conditions and other causes may need to be considered too.

How can constipation affect the bladder?

A full rectum can press on the bladder and change the space available for it to fill. In some people this may increase urinary urgency or frequency, contribute to urgency leakage, or make it harder to empty the bladder comfortably. Constipation and bladder symptoms may also occur together because of shared pelvic floor or neurological problems.

The relationship is not the same for everyone, and constipation is only one possible contributor. Bladder symptoms should be assessed on their own merits, especially if they are new, persistent or worsening.

Some medicines used for bladder symptoms, including anticholinergic medicines, can make constipation worse. Pain medicines, iron and some other medicines can also affect bowel habits. If you think a medicine may be contributing, discuss it with your doctor or pharmacist rather than stopping it yourself.

The pelvic floor connection

The pelvic floor is a group of muscles and connective tissues that supports the bladder, bowel and other pelvic organs. It helps maintain urinary and bowel control, and it must also relax and coordinate when you empty your bladder or bowel.

Repeated straining to pass hard stool can place ongoing pressure on the pelvic floor. A pelvic floor that is weak, painful, tense or poorly coordinated may affect both bladder and bowel emptying or control. Treatment therefore depends on what the muscles are doing: strengthening is useful for some forms of leakage, while people who cannot relax or coordinate the pelvic floor may need a different approach, sometimes with a pelvic health physiotherapist.

How are the bladder and bowel nerves connected?

The bladder and rectum have different jobs, but their nerve pathways meet and interact through the spinal cord, pelvic nerve networks and the brain. The pathways below are a simplified guide; the actual nerve networks are interconnected.

Nerve pathway Main spinal levels Role in bladder and bowel function
Pelvic splanchnic nerves (parasympathetic) S2–S4 Help the bladder contract to empty and contribute to rectal activity and bowel emptying. They also carry important sensation from the lower urinary tract and rectum.
Hypogastric nerves (sympathetic) About T11–L2 Support bladder storage by relaxing the bladder wall and helping maintain outlet closure. They also contribute to bowel storage and internal anal sphincter function.
Pudendal nerves (somatic) S2–S4 Provide voluntary control of the external urethral sphincter, external anal sphincter and parts of the pelvic floor. These muscles help maintain continence and must coordinate with relaxation during emptying.

Bladder filling and emptying, bowel filling and defecation are coordinated with pelvic floor activity and brain control. Because some of these pathways and muscles are shared, neurological conditions or injuries affecting the brain, spinal cord or sacral nerves can affect both bladder and bowel function. A full rectum can also alter the local pressure and sensory environment around the bladder.

Constipation is not only about how often you go

Bowel frequency varies. Not having a bowel motion every day does not, by itself, mean you are constipated. It is also important to mention:

  • hard or lumpy stools;
  • needing to strain or push repeatedly;
  • discomfort or pain when passing stool;
  • a feeling that the bowel has not emptied completely; or
  • needing to use your fingers or change position to help stool pass.

A short bowel diary, used alongside a bladder diary, can help identify whether urinary urgency or leakage changes when constipation is worse.

Good bowel habits to support pelvic health

A few practical habits may help maintain regular, comfortable bowel movements:

  1. Respond to the urge. Try not to repeatedly postpone a bowel motion. Many people find it helpful to allow unhurried time after a meal, when the bowel may be more active.
  2. Use a comfortable position. Sit with your feet supported on a small footstool so your knees are a little higher than your hips. Lean forward with your forearms on your thighs and keep your abdomen relaxed.
  3. Avoid prolonged straining. Breathe out gently rather than holding your breath and pushing hard. If stool will not pass, get up and try again later instead of sitting and straining for a long time.
  4. Eat a varied, fibre-containing diet. Whole grains, vegetables, fruit, legumes, nuts and seeds can help. Increase fibre gradually to reduce bloating. Adults’ fibre needs vary; one commonly used guide is around 22–34 grams a day, adjusted for age, health and tolerance.
  5. Drink an appropriate amount. Adequate fluid helps fibre work and can soften stool. Your needs vary, and people who have been advised to restrict fluids because of heart, kidney or other conditions should follow their treating clinician’s advice. Restricting fluids to manage urinary frequency may worsen constipation.
  6. Keep moving regularly. Walking and other suitable physical activity can support bowel function.
  7. Review medicines and ongoing symptoms. Ask your doctor or pharmacist whether medicines may be contributing. Persistent constipation may need tailored treatment; a clinician can advise whether dietary changes, a laxative or pelvic floor assessment is appropriate.

If you have difficulty relaxing the pelvic floor or feel that stool is blocked despite soft stools, simply adding more fibre or doing repeated pelvic floor squeezes may not solve the problem. Ask about an assessment of bowel emptying and pelvic floor coordination.

Looking beyond the bladder

Improving bowel habits may reduce one contributor to bladder symptoms, but it is not a substitute for investigating persistent urinary problems. A clinician may ask about both bladder and bowel symptoms, review medications, test the urine and check how well the bladder empties. Further assessment depends on the symptoms and medical history.

Seek medical advice for ongoing or worsening urgency, leakage, difficulty passing urine or constipation. Blood in the urine or stool, severe abdominal pain, vomiting, inability to pass urine, or a sudden major change in bowel or bladder control needs prompt medical attention.

This article provides general information and is not a substitute for individual medical advice.

References

  1. Queensland Spinal Cord Injuries Service. Bowel and bladder relationship.
  2. Continence Health Australia. Constipation.
  3. Australian Government Department of Health, Disability and Ageing. Bladder and bowel health: recognising a problem.
  4. National Institute of Diabetes and Digestive and Kidney Diseases. Eating, diet and nutrition for constipation and prevention of bladder control problems.
  5. de Groat WC, Griffiths D, Yoshimura N. Neural control of the lower urinary tract. Comprehensive Physiology. 2015;5(1):327–396. doi:10.1002/cphy.c130056.
  6. StatPearls. Anatomy, abdomen and pelvis: pelvic floor.


Painful Ejaculation: The Symptom Men Rarely Talk About

Painful ejaculation: causes, assessment and treatment

Pain during or after ejaculation can be difficult to mention, even to a doctor. Some men hope it will disappear; others avoid sex because they worry the pain will return.

Painful ejaculation, sometimes called dysejaculation or dysorgasmia, is a symptom, not a diagnosis. It can have several causes, including infection, inflammation, pelvic floor problems, medication effects or, less commonly, a blockage in the passages that carry semen. The pattern of symptoms and the findings on assessment help guide the next steps.

What can painful ejaculation feel like?

The experience varies. Pain may be burning, sharp, cramping or a deeper ache. It can be felt in the penis, testicles, scrotum, perineum (the area between the scrotum and anus), lower abdomen or pelvis.

It may begin during orgasm or ejaculation, just afterwards, or continue for minutes or hours. It may occur every time or only occasionally. Some men also notice urinary symptoms, blood in the semen, changes in the amount of semen, erection or orgasm changes, or pain with bowel movements.

The details are useful: where the pain is, when it starts, how long it lasts, whether it is linked to urination or a particular activity, and whether it is changing over time.

What can cause painful ejaculation?

Prostate or pelvic pain conditions

Inflammation or infection of the prostate can cause painful ejaculation, sometimes with pelvic discomfort, urinary frequency, burning when passing urine or difficulty urinating. Acute bacterial prostatitis may cause fever and feeling unwell and needs prompt medical assessment.

Many men with persistent pelvic pain have chronic prostatitis/chronic pelvic pain syndrome (CP/CPPS). This is not necessarily a bacterial infection. Symptoms can involve the perineum, penis, testicles or lower abdomen and may include urinary or sexual symptoms. Pelvic floor muscle tension, nerve sensitivity and other factors can contribute. Repeated antibiotic courses are not appropriate when there is no evidence of a bacterial infection. Painful ejaculation is a recognised feature of chronic pelvic pain, but it can have other causes too. Oxford Academic

Urethral or genital infection

Urethritis, including a sexually transmitted infection (STI), can cause pain or burning during urination and ejaculation. Infection or inflammation involving the epididymis or testicle can also be painful. Discharge, a new sexual partner, testicular tenderness, fever or urinary burning may guide testing.

Pelvic floor muscle tension or poor coordination

The pelvic floor muscles contract and coordinate during ejaculation. If they are tender, overactive or unable to relax, ejaculation may trigger pelvic or perineal pain. This may occur on its own or as part of a broader chronic pelvic pain syndrome. A pelvic health physiotherapist can assess muscle coordination and tenderness when indicated.

Narrowing or obstruction in the semen pathway

A narrowing of the urethra, ejaculatory duct obstruction, or a problem involving the seminal vesicles may cause pain in selected cases. A previous vasectomy or surgery affecting the prostate, bladder, urethra or pelvis may also be relevant. These causes are less common and usually require targeted investigation rather than assuming that obstruction is present.

Medicines, procedures and radiotherapy

Some medicines have been reported to cause painful ejaculation or changes in orgasm. The timing of symptoms in relation to starting or changing a medicine can be helpful. Do not stop a prescribed medicine without discussing it with the prescriber.

Pain may also follow pelvic surgery, instrumentation or radiotherapy. The cause and appropriate assessment depend on the procedure and when the symptoms began.

Other contributors

Nerve-related pain, chronic medical conditions and psychological or relationship stress can influence the experience of pain. This does not mean the pain is “all in your head.” Pain is real, and several physical, nervous-system and emotional factors can interact.

Sometimes no single cause is identified. Even then, a structured assessment can help select reasonable symptom-management options.

How is painful ejaculation investigated?

Testing is guided by the history and examination. Not every man needs a scan, cystoscopy or extensive testing. Current sexual-medicine recommendations advise assessing painful ejaculation along established pelvic-pain pathways, with tests and imaging chosen according to symptoms. Oxford Academic

1. A detailed history

Your doctor may ask about:

  • where the pain occurs, when it starts and how long it lasts;
  • whether it happens with every ejaculation or only in certain situations;
  • urinary symptoms such as burning, urgency, weak stream or difficulty emptying;
  • blood in the urine or semen, discharge, fever or testicular swelling;
  • recent sexual partners or possible STI exposure;
  • previous infections, vasectomy, pelvic surgery, radiotherapy or urinary procedures;
  • medicines and recent dose changes; and
  • how the symptoms affect sexual activity, fertility plans and quality of life.

You do not need technical language. Describing what happens in your own words is a good starting point.

2. Examination

Depending on the symptoms, examination may include the abdomen, penis, testicles, epididymides and groin. A prostate or pelvic floor examination may be considered when it is likely to help identify the cause. The examination should be explained and performed with your consent.

3. Urine and infection testing

A urine test and culture may be used to look for a urinary infection. STI testing, often using a urine sample or swab, may be appropriate based on symptoms and sexual history. Blood tests are sometimes used if there are signs of systemic infection or another specific concern.

Antibiotics should be directed at a suspected or confirmed bacterial infection. Painful ejaculation alone does not prove that an infection is present.

4. Tests for urinary or structural problems

If there are urinary symptoms, a clinician may measure urine flow or check the amount left in the bladder after urination. Further investigations are selected according to the suspected cause:

  • Ultrasound or other imaging may be considered for testicular symptoms, suspected seminal vesicle or ejaculatory duct problems, or persistent unexplained pain.
  • Cystoscopy or urethral imaging may be appropriate if a urethral narrowing, bleeding or another urethral problem is suspected.
  • Prostate-specific antigen (PSA) testing is considered selectively based on age, examination and prostate-cancer risk. It is not a test for painful ejaculation itself and may be misleading during active infection or inflammation.
  • Semen testing is not routinely required for every man with painful ejaculation, but may be considered when fertility or a specific semen-pathway problem is part of the question.

How is painful ejaculation managed?

Treatment depends on the cause and on how much the symptom affects you. There is no single treatment that suits everyone. Guidelines recommend tailoring care to the likely cause; procedures are generally reserved for selected cases with a demonstrated structural problem because evidence for surgery for unexplained pain is limited. Uroweb

  • Confirmed or strongly suspected infection: treatment may include the appropriate antibiotic or other infection-specific care. If an STI is diagnosed, partner testing or treatment and avoiding sex until treatment is complete may be advised.
  • Medication-related symptoms: the prescriber may review the timing, dose or alternatives. Do not change medication on your own.
  • Chronic pelvic pain or pelvic floor tenderness: care may include pelvic floor physiotherapy focused on relaxation and coordination, pain-management strategies, and selected medicines. Strengthening exercises are not automatically appropriate if the muscles are already tight or painful.
  • Urinary symptoms: treatment may be directed at an identified urinary condition. For some men, a clinician may consider an alpha-blocker or other targeted treatment.
  • A defined obstruction or structural problem: a urologist may discuss a procedure if investigations confirm a cause and symptoms justify it. Procedures are not routine for unexplained pain, and potential effects on ejaculation and fertility should be discussed.
  • No clear cause found: trigger modification, review of sexual activity patterns, supportive counselling or a multidisciplinary chronic-pain approach may help. The plan can be adjusted over time.

The evidence for specific treatments of painful ejaculation is limited, so decisions are usually tailored to the likely cause and the individual’s priorities.

When should you seek urgent care?

Seek prompt medical attention if painful ejaculation occurs with fever or shaking chills, feeling very unwell, inability to pass urine, sudden severe testicular pain or swelling, or visible blood in the urine. These symptoms may need urgent assessment. Blood in the semen should also be discussed with a doctor, particularly if it recurs or occurs with other symptoms. NHS

Starting the conversation

You do not need medical terminology. You can simply say: “I have pain when I ejaculate.” If it is recurring, worsening or affecting intimacy, speak with your GP. They can begin the assessment and arrange urology referral if needed.

This article provides general information and is not a substitute for individual medical advice.

References

  1. Shindel AW, Serefoglu EC, et al. Review of recent data on disorders of ejaculation and orgasm in men: recommendations from the Fifth International Consultation on Sexual Medicine. Sexual Medicine Reviews. 2025;13(3):318–337. doi:10.1093/sxmrev/qeaf016.
  2. European Association of Urology. Guidelines on Sexual and Reproductive Health: Disorders of Ejaculation.
  3. American Urological Association. Diagnosis and Management of Male Chronic Pelvic Pain: AUA Guideline (2025).
  4. Donatucci CF, et al. Contemporary management of ejaculatory dysfunction. Translational Andrology and Urology. 2018. Full text.
  5. Acharya S, et al. Painful ejaculation—an ignored symptom. Sexual Medicine Reviews. 2020. Full text.
  6. NHS. Prostatitis and Blood in semen.

Renal cysts: when to reassure, when to investigate and when to treat

Renal cysts are fluid-filled sacs within or on the kidney. Finding a “cyst” on a scan can be worrying, but many are harmless. The important questions are whether the cyst has a simple or complex appearance, whether it is causing symptoms, and whether it affects urine drainage or kidney function.

A large simple cyst is not automatically cancerous, and a small complex cyst is not automatically harmless. Imaging features and the clinical situation guide management.

What types of renal cysts are there?

Simple cysts have a thin, smooth wall and contain fluid. They become more common with age and usually cause no symptoms or loss of kidney function. Most need no treatment.[1]

Complex cystic masses have additional features, such as internal partitions called septa, thickened walls or tissue nodules. “Complex” describes their appearance; it does not establish a cancer diagnosis.[2]

Parapelvic cysts lie beside the renal pelvis, the funnel that collects urine before it enters the ureter. Their location can make diagnosis and treatment more difficult.[6]

Polycystic kidney disease is a separate condition, often inherited, in which multiple cysts may enlarge the kidneys and affect kidney function. Numerous cysts in both kidneys, especially with a family history, merit assessment for cystic kidney disease rather than being assumed to be ordinary simple cysts.[9]

How do renal cysts present?

Most simple cysts are discovered incidentally during an ultrasound, CT or MRI performed for another reason.

Occasionally, a cyst causes a dull ache in the flank or back, pressure or discomfort, or obstruction to urine drainage. Bleeding, infection or rupture can cause more acute symptoms. Fever with flank pain may indicate infection.[1]

Pain and blood in the urine have many possible causes, including stones and other urinary tract conditions. Finding a cyst does not prove that it caused the symptoms. Visible blood in the urine should be assessed rather than attributed to a known cyst.

What investigations are needed?

Ultrasound often identifies an uncomplicated simple cyst. If the lesion is uncertain or complex, a dedicated contrast-enhanced CT or MRI can assess its wall, septa and any solid tissue. Contrast-enhanced ultrasound is another option in centres with appropriate expertise.[3]

An important finding is enhancement: tissue becomes brighter after contrast, indicating a blood supply. Enhancement in thickened or irregular tissue or a nodule raises concern.

Urine testing and blood tests for kidney function may be appropriate. Infection symptoms may require a urine culture. Contrast choices are individualised according to kidney function, allergies and other circumstances.

Ordinary ultrasound alone may not adequately classify a complex cyst. A radiology report should ideally state which version of the Bosniak classification has been used.[2,3]

Bosniak classification: understanding the scan report

The Bosniak system groups cystic renal masses by imaging appearance. The 2019 version incorporates CT and MRI criteria. It estimates concern for malignancy; it is not a cancer stage or a substitute for specialist assessment.[2]

Category Simplified meaning Usual approach
I Simple fluid-filled cyst with a thin, smooth wall Benign; no routine follow-up if confidently classified
II Benign features, such as a few thin septa or certain non-enhancing blood/protein-containing cysts Usually no routine follow-up
IIF More septa or mild smooth thickening; “F” means follow-up Scheduled imaging to check for change
III Enhancing thick or irregular walls or septa Indeterminate; specialist discussion of surveillance or treatment
IV An enhancing tissue nodule Strong concern for cancer; specialist assessment and treatment planning

This table is deliberately simplified. Calcification or blood within a cyst does not by itself establish cancer. The pattern of enhancement and tissue architecture matters.[2,3]

When should cancer be a concern?

Concern increases with enhancing nodules, irregular or thick enhancing walls/septa, or progression to a more suspicious category on follow-up.

Bosniak III masses include both benign and malignant lesions. Bosniak IV masses have a high likelihood of malignancy. Published percentages vary with the classification version and which patients undergo surgery, so a single percentage should not be treated as an individual prediction.[3,4]

Absence of symptoms does not exclude cancer. Conversely, enlargement of an otherwise simple cyst does not alone prove malignant change.

Follow-up and active surveillance

For Bosniak IIF lesions, the Canadian Urological Association suggests imaging at 6–12 months during the first year, then annually if stable, for a total of five years without progression.

Its 2023 guideline also supports active surveillance as a preferred option for selected Bosniak III/IV masses measuring 2 cm or less; surveillance or surgery for those measuring 2–4 cm; and surgery generally for those larger than 4 cm. These recommendations have limited-certainty evidence and require shared decision-making.[4]

Other guidelines differ in emphasis. The EAU allows surveillance for selected Bosniak III lesions and generally manages Bosniak IV lesions as localised kidney cancer.[8] Age, overall health, kidney function, imaging features and patient preferences all matter.

Surveillance means planned scans and reassessment, with treatment considered if concern increases. Biopsy may help when there is a targetable solid component and the result would change management; sampling a mainly fluid-filled lesion often has a low diagnostic yield.[4]

When should a benign cyst be treated?

Treatment may be considered for persistent symptoms convincingly attributable to the cyst, obstruction, or complications such as infection. There is no universal size threshold requiring treatment for a confidently benign simple cyst.[1]

Before intervention, the team should establish that the lesion is benign and discuss whether treatment is likely to relieve the symptoms.

Treatment options

Interventional radiology: aspiration and sclerotherapy

An interventional radiologist can use ultrasound or CT to guide a needle or catheter into a suitable simple cyst. The fluid is drained, usually under local anaesthetic, sometimes with sedation.

Aspiration alone can provide temporary relief, but the cyst may refill. Sclerotherapy adds an agent to damage the fluid-producing lining and reduce recurrence. The team must exclude communication with the urine collecting system before using a sclerosant.

A systematic review of 57 studies reported treatment success in approximately 88% of patients receiving aspiration with sclerotherapy, defined as symptom resolution together with more than 50% cyst-size reduction. Techniques and study quality varied; this is not a guarantee for an individual patient.[5]

Risks include pain, bleeding, infection, leakage of the agent, injury to nearby structures and recurrence. Repeat treatment may be needed.

Laparoscopic cyst deroofing

Deroofing, also called decortication, removes part of the cyst wall so it cannot readily reform as a closed sac. The removed tissue is usually sent for pathology.

Performed through small incisions under general anaesthesia, it may suit large, accessible symptomatic cysts or cysts that recur after percutaneous treatment.

A comparative meta-analysis found lower treatment-failure rates with laparoscopic deroofing than aspiration with sclerotherapy, while percutaneous treatment generally involved shorter procedures, shorter hospital stays and fewer complications.[7]

Surgical risks include bleeding, infection, injury to nearby organs or the collecting system, urine leakage, persistent pain and recurrence. Recovery depends on the procedure and the patient’s health.

Robotic-assisted deroofing

Robotic assistance is another way to perform minimally invasive cyst surgery. It may help with dissection in selected cases, but the robot is operated by the surgeon. Its availability does not mean it is necessary or offers a better result for every cyst. Location, complexity, expertise and cost should guide the choice.[7]

If the cyst is suspicious for cancer

Simple drainage or deroofing is not an appropriate cancer operation. Management may involve surveillance, partial nephrectomy to remove the lesion while preserving kidney tissue, or occasionally removal of the whole kidney. Ablation may be considered in selected patients, although evidence for complex cystic lesions is limited.[4,8]

I no longer perform nephrectomies. If partial or radical nephrectomy is indicated, I will refer you to a colleague who performs this surgery.

Parapelvic cysts: a special situation

Parapelvic cysts are beside the kidney’s central urine collecting system and usually do not communicate with it. They can mimic hydronephrosis, a dilated collecting system, on ultrasound. Contrast imaging, sometimes including delayed images, can distinguish the two and show whether a cyst is compressing urine drainage.[6]

Many asymptomatic benign parapelvic cysts can be observed. Treatment may be considered when a cyst causes pain or demonstrable obstruction.

Options include carefully planned laparoscopic or robotic deroofing, or ureteroscopic internal drainage in selected cases. With ureteroscopy, a telescope passes through the urethra, bladder and ureter into the kidney; a laser opens the cyst into the collecting system. A temporary ureteric stent may be required. Published studies support feasibility, but long-term comparative evidence remains limited.[6,10]

Sclerotherapy is generally avoided for parapelvic cysts because leakage or inflammation near the collecting system can cause scarring and obstruction. Any proposed percutaneous approach requires specialist assessment; routine simple-cyst treatment should not be applied automatically.[6]

Their proximity to blood vessels and the collecting system also increases the technical difficulty of surgery. Risks include bleeding, urine leakage, infection, narrowing and recurrence.

When to seek prompt medical attention

Seek urgent assessment for severe flank pain with fever or rigors, significant bleeding or clots in the urine, difficulty passing urine, or pain accompanied by faintness or marked illness. Persistent visible blood in the urine also requires medical review.

References

  1. National Institute of Diabetes and Digestive and Kidney Diseases. Simple kidney cysts.
  2. Silverman SG, et al. Bosniak Classification of Cystic Renal Masses, Version 2019: An Update Proposal and Needs Assessment. Radiology. 2019;292:475–488. Article.
  3. European Association of Urology. Renal Cell Carcinoma Guidelines: Diagnostic evaluation.
  4. Canadian Urological Association. 2023 update: Management of cystic renal lesions. Canadian Urological Association Journal. Guideline.
  5. Brown D, et al. Radiologically guided percutaneous aspiration and sclerotherapy of symptomatic simple renal cysts: a systematic review of outcomes. Abdominal Radiology. 2021. PubMed.
  6. Ureteroscopic management of asymptomatic and symptomatic simple parapelvic renal cysts. BMC Urology. 2015. Article.
  7. Comparison of aspiration with sclerotherapy and laparoscopic deroofing for the treatment of symptomatic simple renal cysts: a systematic review and meta-analysis. Updates in Surgery. 2021. PubMed.
  8. European Association of Urology. Renal Cell Carcinoma Guidelines: Epidemiology, aetiology and pathology and Disease management.
  9. NIDDK. What is polycystic kidney disease?.
  10. Transurethral flexible ureteroscopic incision and drainage with holmium laser in the treatment of parapelvic renal cysts. International Brazilian Journal of Urology. 2022. Article.

General patient education. Individual management depends on imaging findings, symptoms, kidney function and discussion with the treating team. Reviewed October 2026.

PUJ obstruction: when urine cannot drain freely from the kidney

Understanding pelvi-ureteric junction obstruction, its symptoms, investigations and treatment, including robotic-assisted pyeloplasty.

The kidneys produce urine, which collects in a funnel-shaped area called the renal pelvis before travelling down the ureter to the bladder. The pelvi-ureteric junction (PUJ) is where this funnel joins the ureter.

PUJ obstruction means urine does not pass freely through this junction. It is also called ureteropelvic junction obstruction, or UPJ obstruction. The collecting system can enlarge, a finding called hydronephrosis, and significant obstruction may eventually damage the affected kidney. However, a dilated collecting system does not automatically mean surgery is needed. Assessment must establish whether drainage is impaired and whether kidney function is at risk. [1,2]

What causes PUJ obstruction?

Some people are born with a short segment that is narrow or does not propel urine normally. Other anatomical causes include kinking or a ureter that joins the renal pelvis unusually high up. A blood vessel supplying the lower part of the kidney may cross the junction and contribute to compression. Seeing a crossing vessel on a scan does not, by itself, prove that it is causing obstruction.

A congenital problem may first become apparent in adulthood. Acquired narrowing can follow scarring, inflammation or previous surgery. Stones and other causes of upper urinary tract blockage must also be considered during investigation. [2,12]

How does it present?

Symptoms range from none at all to episodes of significant pain. Possible presentations include:

  • Aching or intermittent pain in the flank, the side of the back below the ribs.
  • Episodes of more severe pain, sometimes with nausea or vomiting.
  • Pain after a large fluid intake, when urine production increases.
  • Recurrent urinary infections, including infection of the kidney.
  • Blood in the urine or kidney stones.
  • An incidental finding of hydronephrosis on a scan.

Intermittent painful distension is sometimes called a Dietl’s crisis. These symptoms can also have other causes, so pain or blood in the urine should not simply be attributed to a known PUJ problem. [3,12]

Children may be diagnosed following an antenatal ultrasound. Childhood assessment and treatment decisions differ from those in adults and should involve a paediatric urology team. [3]

Which investigations are useful?

The investigation plan answers three questions: What does the anatomy look like? How well does each kidney function? Is urine drainage genuinely obstructed?

Urine and blood tests

Urine testing looks for blood and evidence of infection; a urine culture is useful when infection is suspected. Blood tests include creatinine and estimated glomerular filtration rate (eGFR). These assess overall kidney function, but can remain normal when the other kidney compensates for an affected kidney. [2,10]

Ultrasound

Ultrasound shows collecting-system dilatation and assesses the thickness of the kidney tissue. It is useful for follow-up because it does not involve radiation. Ultrasound alone cannot reliably establish the functional significance of a PUJ narrowing. [2,3]

CT or MR urography

CT urography can define the junction, identify stones and assess surrounding structures, including crossing vessels. The use of intravenous contrast depends on kidney function and other clinical factors.

MR urography is an alternative in selected patients, particularly when avoiding radiation is desirable. The choice of scan is individualised. [1,2]

MAG3 diuretic renogram

This nuclear medicine scan follows a small injected tracer through the kidneys. A diuretic, usually furosemide, helps assess drainage.

It measures:

  • Differential or split renal function: the proportion contributed by each kidney.
  • Drainage: how effectively tracer leaves the collecting system.

Interpretation considers the images, drainage curves, kidney function, hydration and bladder emptying. A slow drainage number alone is insufficient to diagnose clinically significant obstruction: a large collecting system or poorly functioning kidney can make interpretation difficult. [4]

Further tests in selected cases

A retrograde pyelogram introduces contrast into the ureter during a telescopic bladder examination. It can clarify anatomy when other imaging is incomplete. It is not routinely needed in every patient. [2]

Does every PUJ obstruction need treatment?

No. Observation can be appropriate when symptoms are absent or minor, kidney function is stable, and assessment does not suggest harmful obstruction. Monitoring may include symptoms, ultrasound and repeat functional imaging when indicated. The interval depends on the findings. [5]

Intervention is more likely to be recommended for persistent or troublesome symptoms, recurrent kidney infections, associated stones, or deteriorating function. Decisions use the overall clinical picture rather than the ultrasound appearance alone. [2]

What are the treatment options?

Option When it may be considered Main limitation
Observation Stable function with few symptoms Requires planned follow-up
Ureteric stent or nephrostomy Urgent drainage or temporary management Usually does not permanently correct the narrowing
Endopyelotomy or balloon dilatation Selected narrowings or recurrent obstruction Generally less durable than reconstructive repair
Pyeloplasty A significant obstruction requiring reconstruction Requires an operation and recovery

Temporary or emergency drainage

A ureteric stent passes internally from the kidney to the bladder. A nephrostomy drains the kidney through a tube placed through the skin of the back. These can relieve obstruction while infection is treated or definitive surgery is planned. [5,9]

An infected obstructed kidney is an emergency. Antibiotics may be needed together with urgent drainage. Definitive reconstruction is usually considered after the acute problem has been controlled. [9,10]

Endoscopic treatment

Endopyelotomy opens the narrowed segment from inside the urinary tract; balloon dilatation stretches it. Suitability depends on the anatomy, kidney function and previous treatment.

A large observational study found more repeat procedures after endopyelotomy than after pyeloplasty. Because patients were not randomly assigned to treatment, these results inform discussion but cannot predict an individual outcome. [1,6]

Robotic-assisted pyeloplasty: how is the repair performed?

Pyeloplasty reconstructs the junction to improve drainage. It can be performed through an open incision, conventional laparoscopic keyhole surgery, or robotic-assisted keyhole surgery.

The commonly used Anderson–Hynes dismembered pyeloplasty removes the narrowed segment. The surgeon opens the ureter more widely and stitches it back to the renal pelvis, creating a broader connection. Where a crossing vessel contributes to obstruction, the reconstruction can be positioned in front of it while preserving the vessel. [3]

During robotic-assisted surgery, the surgeon controls the instruments from a console. Magnified three-dimensional vision and articulated instruments assist dissection and suturing. The robot does not operate independently. [7]

A temporary internal stent is commonly placed to support healing. A bladder catheter and, sometimes, a drain may also be used initially. [5,7]

How successful is pyeloplasty, and is robotic surgery better?

Published literature commonly reports success above 90% for primary pyeloplasty, including open, laparoscopic and robotic approaches. Success may mean symptom relief, improved drainage or freedom from further surgery; definitions and follow-up differ between studies. These figures are not a guarantee. [1]

Robotic surgery is an established option, but it should not be presented as necessary or universally superior. Comparative research supports good outcomes with both conventional laparoscopic and robotic repair. Much of the evidence is observational, with differences in patient selection, surgical experience and follow-up. The choice should consider anatomy, surgeon expertise, availability and cost. [8]

The goals are to improve drainage, relieve attributable symptoms and preserve function. Previously lost kidney function may not fully recover, even after a technically successful operation. [11]

What are the risks and recovery expectations?

Risks include bleeding, infection, urine leakage, injury to nearby structures, recurrent narrowing, persistent pain and the need for another procedure. Anaesthetic complications and blood clots are also possible. Occasionally, conversion to open surgery is required. [5,7]

Stents can cause urinary frequency, urgency, blood in the urine and discomfort. Their removal must be arranged. Many patients leave hospital after approximately one to three days following uncomplicated keyhole repair, but recovery varies. Stents are often removed after four to six weeks. [5,7]

Follow-up may include ultrasound and a repeat drainage scan. Residual dilatation does not automatically mean the repair has failed; symptoms, drainage and function are assessed together. [4]

What if the kidney already functions poorly?

A low split-function result does not automatically mean the kidney must be removed. Selected patients may benefit from reconstruction or temporary drainage followed by reassessment. A systematic review found that pyeloplasty may relieve symptoms and stabilise function in poorly functioning kidneys, but the evidence was limited and recovery was unpredictable. [11]

Nephrectomy may be considered if the kidney has negligible useful function and causes ongoing pain or infection. This requires an individual discussion, including the health of the other kidney.

When should I seek urgent help?

Seek urgent medical assessment for fever or shaking chills with flank pain, severe uncontrolled pain, persistent vomiting, markedly reduced urine output, or feeling seriously unwell. The threshold for urgent assessment is particularly low if you have a single functioning kidney. [9,10]

This page provides general education and does not replace an individual assessment. The most suitable investigation and treatment depend on symptoms, anatomy, kidney function and overall health.

References

  1. Khan F, Ahmed K, Lee N, et al. Management of ureteropelvic junction obstruction in adults. Nature Reviews Urology. 2014;11:629–638. doi:10.1038/nrurol.2014.240.
  2. Borin JF. Ureteropelvic Junction Obstruction in Adults. Reviews in Urology. 2017;19(4):261–264. Full text.
  3. Oxford University Hospitals NHS Foundation Trust. PUJ Obstruction and Pyeloplasty: information for parents and carers. 2025. Patient leaflet. Used for congenital presentation and reconstruction principles; adult management differs.
  4. SNMMI/EANM. Procedure Standard/Practice Guideline for Diuretic Renal Scintigraphy in Adults With Suspected Upper Urinary Tract Obstruction 1.0. 2018. Guideline.
  5. British Association of Urological Surgeons. Keyhole reconstruction of the kidney pelvis: laparoscopic pyeloplasty. 2023. Patient leaflet.
  6. Jacobs BL, Lai JC, Seelam R, et al. The comparative effectiveness of treatments for ureteropelvic junction obstruction. Urology. 2018;111:72–77. doi:10.1016/j.urology.2017.09.002.
  7. Kingston and Richmond NHS Foundation Trust. Kidney obstruction removal with robot. Patient information.
  8. Uhlig A, Uhlig J, Trojan L, et al. Surgical approaches for treatment of ureteropelvic junction obstruction—a systematic review and network meta-analysis. BMC Urology. 2019;19:112. doi:10.1186/s12894-019-0544-7.
  9. Guy’s and St Thomas’ NHS Foundation Trust. Nephrostomy catheter to drain urine from the kidney. Patient information.
  10. NHS. Hydronephrosis. Patient information.
  11. Pyeloplasty in Adults With Ureteropelvic Junction Obstruction in Poorly Functioning Kidneys: A Systematic Review. 2021. PubMed.
  12. Cleveland Clinic. Ureteropelvic Junction Obstruction. Reviewed 2024. Patient information.

Prepared October 2026.

Ureteroceles: symptoms, investigations and treatment

A ureterocoele (also spelt ureterocele) is a balloon-like swelling at the lower end of a ureter: the tube carrying urine from the kidney to the bladder. The swelling usually projects into the bladder. Its opening may be narrow, slowing urine drainage and sometimes causing infection, stones or pressure on the kidney.

Some ureterocoeles cause no problems and are found incidentally. Others need treatment to improve drainage and protect kidney function. [1,2]

Congenital or acquired?

Most true ureteroceles are congenital, meaning they develop before birth. They may be detected on pregnancy ultrasound, during childhood or much later in adult life. A diagnosis in adulthood does not necessarily mean the ureterocele developed recently.

A ureterocoele can occur with a single ureter or a duplex collecting system, in which a kidney has two drainage systems. In a duplex kidney, the ureterocoele commonly involves the ureter draining the upper part of the kidney.

An intravesical or orthotopic ureterocoele lies within the bladder. An ectopic ureterocoele extends into the bladder neck or urethra and may interfere with bladder emptying. Adults more often have an intravesical ureterocoele associated with a single drainage system. [1,3]

The term “acquired ureterocoele” needs care. An acquired swelling of the lower ureter that resembles a ureterocoele is often called a pseudoureterocoele. A stone or a lesion involving the bladder near the ureteric opening can cause this appearance. An irregular or unusual swelling should therefore be investigated rather than assumed to be a harmless congenital abnormality. [4]

Presentation and symptoms

A ureterocoele may be discovered during investigations for an unrelated problem. When symptoms occur, they can include:

  • Recurrent urinary tract infections.
  • Pain in the side, back or lower abdomen.
  • Burning, urgency or frequent urination, particularly with infection.
  • Blood in the urine.
  • Stones trapped within the ureterocoele.
  • Difficulty emptying the bladder or, occasionally, urinary retention.

Children may present with unexplained fever, feeding difficulties or poor growth associated with infection. Rarely, a large ureterocoele can prolapse through the urethra.

Symptoms depend on whether the swelling obstructs drainage, contains a stone or affects the bladder outlet. Prolonged obstruction and repeated kidney infections can damage kidney function. [2,5]

What investigations are needed?

Investigations establish the anatomy, assess drainage and kidney function, and look for infection or reflux. Not everyone needs every test.

Investigation What it helps assess
Urine testing and culture Infection and the appropriate antibiotic
Blood tests Kidney function; inflammatory markers when infection is suspected
Kidney and bladder ultrasound The ureterocoele, stones and swelling of the kidney or ureter
CT, sometimes CT urography Stones and detailed urinary tract anatomy, particularly in adults
MR urography Complex anatomy, including duplicated drainage systems
MAG3 or DMSA kidney scan Drainage and relative function, or functioning kidney tissue and scarring
Micturating cystourethrogram (MCUG/VCUG) Urine flowing backwards from the bladder into a ureter
Cystoscopy Direct inspection of the bladder and ureteric openings

CT involves radiation; contrast use depends on kidney function and the clinical question. Reflux testing is particularly relevant in children or when infection, complex anatomy or postoperative concerns warrant it. Cystoscopy can clarify an uncertain diagnosis and allow treatment during the same procedure. [1,3,5]

Does every ureterocoele need surgery?

No. Observation with planned follow-up may be appropriate when there are no troublesome symptoms, significant obstruction or recurrent infections, and kidney function is satisfactory.

Monitoring may include ultrasound and review of symptoms. Antibiotics treat infection but do not correct the swelling. Preventive antibiotics are considered selectively, particularly in children at increased infection risk. [6]

An infected, obstructed kidney requires urgent assessment and drainage, alongside antibiotics. Drainage may involve endoscopic opening of the ureterocoele or a nephrostomy, a tube placed through the skin into the kidney. Antibiotics alone may be insufficient when infected urine cannot drain. [1]

Endoscopic incision or deroofing

Treatment can often be performed through a telescope passed along the urethra into the bladder, usually under general anaesthesia.

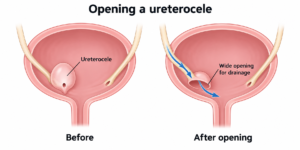
Incision or puncture creates an opening in the wall of the ureterocoele. Deroofing removes part of its wall to create a broader opening. Both aim to let urine drain freely and reduce the balloon-like swelling.

The choice depends on anatomy, obstruction and associated stones. Instruments using electrical energy or a laser may be used. A stone within the sac can sometimes be fragmented and removed at the same operation.

A bladder catheter may be needed temporarily. Endoscopic treatment can be sufficient for a straightforward adult intravesical ureterocoele, while complex duplex or ectopic cases may need further surgery. [5,7,8]

Where does a ureteric stent fit in?

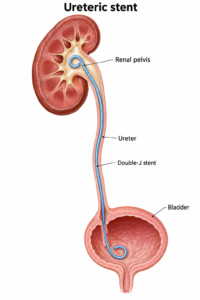
A double-J stent is a soft internal tube extending from the kidney to the bladder. It may be used selectively to support drainage after treatment, during associated stone surgery or while swelling settles. It is not required in every case and does not necessarily provide a permanent solution to the ureterocoele. [8]

Stents can cause frequency, urgency, bladder discomfort, blood in the urine and flank pain, sometimes after urination. Infection, displacement and mineral encrustation are other possible problems.

Every temporary stent needs a clear removal or exchange plan. The duration depends on the procedure and clinical circumstances. Contact the treating team if the removal date is unclear or overdue. [9]

Possible complications, including vesicoureteric reflux

Possible complications of endoscopic treatment include bleeding, infection, discomfort, injury to nearby urinary tract structures, persistent obstruction or narrowing as the opening heals. Repeat treatment or reconstructive surgery may be needed. [3,5,7]

Vesicoureteric reflux (VUR) means urine travels backwards from the bladder towards the kidney. It may already be present before treatment, particularly in a duplex system, or develop after opening the ureterocoele alters the natural anti-reflux mechanism.

Reflux does not automatically mean kidney damage or another operation. Its significance depends on its severity, infections, kidney function and bladder function. Monitoring may be appropriate; persistent significant reflux with recurrent infections can require further treatment, including ureteric reimplantation.

Risk varies with anatomy and technique. Ectopic ureterocoeles and duplex systems have higher rates of postoperative reflux and additional surgery than simpler intravesical cases. [1,7]

In one small adult study, reflux was detected in two of 23 patients followed after endoscopic incision, persisting in one at six months. These results illustrate the possibility of reflux; they do not predict an individual patient’s risk. Adult evidence largely comes from small studies. [7]

Further surgery and follow-up

Reconstructive options include reimplanting the ureter into the bladder or joining it to another healthy ureter in a duplex system. Occasionally, a severely damaged, poorly functioning kidney segment causing problems may require removal. Specialist assessment determines whether reconstruction, observation or removal is appropriate. [1]

Follow-up checks that drainage has improved and looks for recurrent infection, obstruction or reflux. Ultrasound is commonly used; further imaging is selected according to the findings. Symptom improvement alone does not confirm that drainage is normal. [5,7]

Seek urgent medical care for fever or shaking chills with flank pain, inability to pass urine, severe worsening pain, persistent vomiting or feeling seriously unwell. These symptoms may indicate infection or obstruction, including after treatment or with a stent in place. [1,9]

This article provides general education. Treatment should be tailored to the patient’s anatomy, symptoms and kidney function in consultation with their urologist.

References

  1. European Association of Urology. EAU Guidelines on Paediatric Urology: Ureterocele and ectopic ureter. Current online guideline, accessed 5 October 2026. https://uroweb.org/guidelines/paediatric-urology/chapter/ureterocele-and-ectopic-ureter
  2. European Association of Urology. Patient information: Ureterocele. https://patients.uroweb.org/condition/duplex-congenital-malformations-of-the-urinary-tract/ureterocele
  3. The Outcome of Transurethral Electro-Endoscopic Resection of Orthotopic Single System Ureterocoeles in Adults Nigerians. https://pmc.ncbi.nlm.nih.gov/articles/PMC11073836/
  4. Thornbury JR, Silver TM, Vinson RK. Ureteroceles vs. pseudoureteroceles in adults. Urographic diagnosis. Radiology. 1977;122(1):81–84. doi:10.1148/122.1.81. https://pubmed.ncbi.nlm.nih.gov/830358/
  5. An adult ureterocele complicated by a large stone: A case report. International Journal of Surgery Case Reports. 2018. https://pmc.ncbi.nlm.nih.gov/articles/PMC5927814/
  6. European Association of Urology. Watchful waiting for ureterocele. https://patients.uroweb.org/condition/duplex-congenital-malformations-of-the-urinary-tract/ureterocele/wait-and-see-ureterocele
  7. Vijay MK, et al. The safety and efficacy of endoscopic incision of orthotopic ureterocele in adult. Saudi Journal of Kidney Diseases and Transplantation. 2011;22(6):1169–1174. https://pubmed.ncbi.nlm.nih.gov/22089776/
  8. A Large Stone Within a Ureteroceles: A Diagnostic Pitfall and the Utility of Holmium Laser Deroofing as a Viable Surgical Option. https://pubmed.ncbi.nlm.nih.gov/29468199/
  9. British Association of Urological Surgeons. Information about your ureteric stent. https://www.baus.org.uk/_userfiles/pages/files/Patients/Leaflets/Stent%20advice.pdf

Coffee Break

Coffee, oat milk and the start of my day at the Wesley

By Dr Jo Schoeman

Before a busy day of consultations or operating at the Wesley, I enjoy a small ritual: stopping for a coffee with oat milk at Steamtrain Espresso Bar and Kitchen, beside Auchenflower train station and just outside the hospital. It gives me a moment to gather my thoughts before the day begins. I also simply enjoy a good coffee.

 “A quiet coffee before the working day.” 

What is good about coffee?

For many of us, caffeine helps us feel more alert and focused in the morning. Coffee also contains a range of naturally occurring plant compounds. Large reviews have found that people who drink moderate amounts of coffee tend to have lower rates of several health problems than people who do not drink it. These are mostly associations: they do not prove that coffee itself prevents disease, and they are no reason to start drinking it if you do not enjoy it.[1]

The amount that suits one person may be too much for another. Coffee can disturb sleep or cause jitters and palpitations, especially in people who are sensitive to caffeine. I prefer mine early in the day, when I can enjoy the lift without letting it interfere with the night ahead.

Why oat milk?

I like its taste and the creamy texture it brings to coffee. It is a practical dairy-free option for people who avoid cow’s milk. If oat milk is a regular replacement for dairy, however, it pays to check the carton: products vary, and oat milk usually provides less protein than cow’s milk. Choosing an unsweetened product fortified with calcium can help, while vitamin B12 and iodine are also worth considering in the context of your overall diet.[2,3] A splash in a coffee is a pleasure, rather than a nutritional strategy in itself.

A urologist’s small caveat

I cannot write about coffee without mentioning the bladder. Caffeine can make urinary urgency, frequency or night-time trips to the toilet worse for some people. If that sounds familiar, try a smaller coffee, have it earlier, or see whether decaf makes a difference. Keep drinking an appropriate amount of water; cutting fluids too far can make bladder symptoms worse. Persistent symptoms deserve an assessment rather than being blamed on your morning coffee alone.[4]

For me, that oat milk coffee at Steamtrain marks the start of the working day. It is a pleasant pause, a familiar stop by the station, and a chance to arrive at the Wesley ready to see my patients. Like most good habits, it works best with a little balance.

References and further reading

  1. Poole R, et al. Coffee consumption and health: umbrella review of meta-analyses of multiple health outcomes. BMJ. 2017;359. https://www.bmj.com/content/359/bmj.j5024
  2. Dietitians Australia. Plant-based milks. https://dietitiansaustralia.org.au/health-advice/plant-based-milks
  3. Food Standards Australia New Zealand. Plant-based milk alternatives. https://www.foodstandards.gov.au/consumer/nutrition/milkaltern
  4. Continence Health Australia. Caring for your bladder at night (nocturia). https://www.continence.org.au/about-incontinence/urinary-incontinence/nocturia/caring-for-your-bladder-at-night-nocturia/

This article offers general information and reflects my personal routine. Individual nutrition and bladder needs vary.

Penile Fracture: Presentation, Investigation, Treatment and Long-Term Outlook

Penile fracture is a urological emergency. Despite its name, no bone is broken. The injury is a tear in the tunica albuginea, the tough sleeve surrounding one or both erectile cylinders (corpora cavernosa) while the penis is erect. Bleeding then occurs within and around the erectile tissues.

If you hear or feel a crack or pop during intercourse or other bending of an erect penis, followed by pain, loss of the erection, swelling or bruising, stop sexual activity and attend the nearest emergency department immediately. Do not wait to see whether it settles, and do not eat or drink until assessed in case an anaesthetic is required.

This article provides general education. It cannot diagnose an injury, replace examination, or provide individual medical advice.

How does a penile fracture happen?

During an erection, the tunica albuginea becomes much thinner and is vulnerable to sudden buckling. The most frequent mechanism is an erect penis slipping out during intercourse and striking the partner’s pubic bone or perineum. It can also occur during masturbation, intentional forceful bending, rolling onto an erect penis, or less commonly through other trauma.

Penile fracture can happen in any sexual position. It is an accident rather than evidence of wrongdoing, and embarrassment should never delay treatment.

The urethra, the tube carrying urine through the penis, may be injured at the same time. The 2026 European Association of Urology (EAU) guideline reports associated corpus spongiosum or urethral injury in approximately 10–22% of cases; rates vary among populations and mechanisms of injury.[1]

Typical presentation

The classic sequence is:

  • a sudden crack, snap or popping sensation;
  • immediate pain;
  • rapid loss of the erection (detumescence);
  • quickly developing swelling and bruising;
  • bending or deformity of the penis, often away from the injured side; and
  • sometimes a palpable defect in the tunica.

Bruising may spread into the scrotum, perineum or lower abdominal wall. The dramatic “aubergine” appearance described in medical literature is not present in every case.

Warning signs of urethral injury

Tell the treating team immediately if there is:

  • blood at the urinary opening;
  • blood in the urine;
  • pain or difficulty passing urine;
  • inability to pass urine; or
  • a weak or interrupted urinary stream after the injury.

The absence of these findings does not completely exclude urethral injury. Clinical assessment remains important.

Conditions that can look similar

Not every swollen or bruised penis after intercourse has a tunical tear. Rupture of a superficial vein or artery, injury to the suspensory ligament, or bleeding beneath the skin can produce a “false penile fracture.” Slow rather than immediate loss of erection and absence of the characteristic crack may make a true fracture less likely, but no single feature is conclusive.

Because missing a fracture can have lasting consequences, significant swelling, pain or deformity after trauma to an erect penis requires urgent medical assessment.

How is it investigated?

History and examination

When the history and examination are classic, penile fracture is primarily a clinical diagnosis. Testing should not unnecessarily delay repair. The clinician will assess the penis, scrotum and perineum and ask specifically about the mechanism, the speed of detumescence, urination and visible blood. A urine test is generally performed.

Ultrasound

Ultrasound can help locate a tear and haematoma, particularly when the diagnosis is uncertain. It is quick and widely available, but its accuracy depends on the operator, the size and position of the tear, and the amount of swelling. A negative or inconclusive ultrasound does not necessarily exclude fracture when the clinical findings are convincing.

MRI

MRI gives excellent soft-tissue detail and is generally more accurate than ultrasound for detecting a tunical tear. It may be useful in equivocal cases, but availability, cost and delay can limit its emergency use. It is not routinely required when the diagnosis is already clear.[1]

Assessment of the urethra

If urethral injury is suspected, evaluation may include retrograde urethrography (contrast imaging of the urethra) or flexible cystoscopy. Visible haematuria, blood at the meatus, difficulty voiding and bilateral corporal injury increase concern. The EAU and American Urological Association (AUA) both recommend evaluating for associated urethral injury when indicated.[1,2]

CT is not the preferred test for an isolated penile fracture, although it may be obtained when wider pelvic or abdominal trauma is suspected.

Recommended management

Prompt surgical repair

Current EAU and AUA guidance recommends prompt surgical exploration and repair for an acute penile fracture.[1,2] The operation is usually performed under general or regional anaesthesia and involves:

  1. exposing the injured erectile tissue through a circumferential degloving incision or a targeted incision over the tear;
  2. evacuating the clot and controlling bleeding;
  3. identifying and closing the tunica albuginea tear with sutures; and
  4. inspecting and repairing the urethra if it is injured.

A urinary catheter may be used, especially when the urethra has been assessed or repaired. The exact incision, catheter duration, hospital stay and follow-up depend on the injury and the surgeon’s findings.

The EAU guideline advises repair within 24 hours of presentation when feasible, but late presentation is not a reason to withhold assessment or repair.[1] A person presenting after a delay should still seek urgent urological review.

Why is conservative treatment generally avoided?

Ice, compression, pain relief, erection-suppressing medication and observation were historically used. Conservative treatment may occasionally be appropriate when imaging and specialist assessment confirm that the tunica is intact, but it is not the standard treatment for a confirmed fracture.

A meta-analysis of 58 studies involving 3,213 patients found significantly fewer overall complications and less erectile dysfunction, curvature and painful erections with surgery than with conservative management.[3] Non-operative treatment of a true fracture carries greater risks of persistent haematoma, infection or abscess, missed urethral injury, fibrosis, penile curvature and erectile dysfunction.[1,3]

Recovery after repair

Patients should follow their treating surgeon’s instructions, which may include:

  • wound and catheter care;
  • simple analgesia and other prescribed medicines;
  • avoiding strenuous activity until reviewed;
  • avoiding intercourse and masturbation, commonly for about six weeks or until healing is confirmed; and
  • follow-up to assess erections, curvature, pain and urinary function.

Night-time or spontaneous erections during healing may be uncomfortable. Medication is sometimes used selectively, but there is no universal post-operative drug regimen. Do not start or stop prescription medicines without advice.

Seek urgent review after treatment for fever, increasing redness or swelling, wound discharge, worsening pain, inability to urinate, heavy bleeding, or a catheter that stops draining.

Possible complications

Most patients do well after prompt repair, but no treatment can guarantee a complication-free outcome. Possible early or late problems include:

  • wound infection, bleeding or haematoma;
  • altered penile sensation, palpable stitches, scar or nodules;
  • painful erections;
  • penile curvature, indentation or shortening;
  • erectile dysfunction;
  • urethral narrowing (stricture), urinary spraying or reduced flow;
  • urethrocutaneous fistula after a significant urethral injury or repair;
  • need for further investigation or surgery; and
  • anxiety, avoidance of intimacy or relationship distress.

The EAU guideline summarises reported post-surgical rates of plaques or nodules, curvature and erectile dysfunction as approximately 13.9%, 2.8% and 1.9%, respectively, while noting that complications overall have been reported in up to 20% of cases.[1] These pooled figures are not a personalised prediction: published studies differ in injury severity, definitions, follow-up and measurement. Risk is higher with extensive or bilateral tears, associated urethral injury, delayed or missed diagnosis, and in some studies age over 50.[1,4]

What is the risk of erectile dysfunction?

Erectile dysfunction after a fracture may result from corporal scarring, impaired blood trapping, arterial or nerve injury, pain, anxiety, or a combination of physical and psychological factors. Prompt repair markedly reduces the risk compared with conservative management, but does not eliminate it.[1,3]

Persistent difficulty should be assessed rather than endured in silence. Evaluation can include a sexual and medical history, validated questionnaires, examination and, when indicated, penile Doppler ultrasound. Treatment is individualised and may include counselling, oral erectile-dysfunction medication when safe, vacuum therapy, injections or, rarely, reconstructive surgery or a penile prosthesis.

Does penile fracture cause Peyronie’s disease?

Healing after a penile fracture can produce a local scar, palpable nodule or post-traumatic curvature. These findings may resemble Peyronie’s disease, which is an acquired fibrotic disorder of the tunica albuginea. However, a curve after fracture should not automatically be labelled Peyronie’s disease: it may arise directly from the repaired tear, asymmetric healing or corporal fibrosis.

The distinction is made through history, examination and, if needed, photographs of the erect penis or ultrasound. Review is advisable if there is a new or worsening bend, a hard plaque, painful erections, loss of length, narrowing, instability or difficulty with intercourse. Management depends on whether the deformity is changing or stable, its severity, erectile function and how much it affects the patient. Options may include observation, penile traction in selected cases, treatment of erectile dysfunction, or reconstructive surgery once the deformity is stable. Treatment should be discussed with a urologist experienced in penile reconstruction or andrology.

The essential message

A suspected penile fracture is time-sensitive. A crack or pop followed by immediate loss of erection, swelling and bruising warrants immediate emergency assessment. Diagnosis is often clinical; ultrasound or MRI is reserved mainly for uncertainty, and the urethra must be assessed when injury is suspected. Prompt surgical repair offers the best prospect of preserving penile shape, erections and urinary function.


References

  1. European Association of Urology. EAU Guidelines on Urological Trauma. 2026 edition, sections on genital trauma and penile fracture. https://uroweb.org/guidelines/urological-trauma/chapter/urogenital-trauma-guidelines
  2. Morey AF, Brandes S, Dugi DD III, et al. Urotrauma: AUA Guideline. J Urol. 2014;192(2):327–335; amended guideline statements available from the American Urological Association. doi:10.1016/j.juro.2014.05.004. https://www.auanet.org/guidelines-and-quality/guidelines/urotrauma-guideline
  3. Amer T, Wilson R, Chlosta P, et al. Penile fracture: a meta-analysis. Urol Int. 2016;96(3):315–329. doi:10.1159/000444884.
  4. Barros R, Schulze L, Ornellas AA, Koifman L, Favorito LA. Impact of surgical treatment of penile fracture on sexual function. Urology. 2019;126:128–133. doi:10.1016/j.urology.2018.11.027.
  5. Wong NC, Dason S, Bansal RK, Davies TO, Braga LH. Can it wait? A systematic review of immediate vs delayed surgical repair of penile fractures. Can Urol Assoc J. 2017;11(1–2):53–60. doi:10.5489/cuaj.4032.
  6. Koifman L, Barros R, Júnior RAS, Cavalcanti AG, Favorito LA. Penile fracture: diagnosis, treatment and outcomes of 150 patients. Urology. 2010;76(6):1488–1492. doi:10.1016/j.urology.2010.05.043.

Website publication note

This material is general health information and was prepared from the sources listed above. It is not a substitute for emergency assessment, diagnosis, informed consent or personalised advice from a qualified practitioner. Outcomes and risks vary between individuals.
