Tag Archive for: dr jo schoeman

Movember: PSA testing: what it can tell you, and what it can’t

An informed conversation with your GP can help you decide whether a PSA test is right for you. Your age, family history, general health and preferences all matter.

Movember is a good time to talk about men’s health, including prostate cancer. One of the most useful steps is often a simple conversation with your GP about prostate-specific antigen (PSA) testing. A PSA blood test can help identify men who may need further assessment, but it is not a yes-or-no cancer test. Understanding what it can and cannot show helps you make an informed choice.

What is PSA?

PSA is a protein made by cells in the prostate. A small amount normally enters the bloodstream, where it can be measured with a blood test. PSA is prostate-specific, but not cancer-specific: a higher result can occur with prostate cancer, but also with benign prostate enlargement, inflammation or infection, urinary retention, or after some urinary procedures. PSA levels also tend to rise with age.

A PSA test is different from a digital rectal examination (DRE). The blood test measures PSA. A DRE is an examination in which a clinician feels the prostate through the rectum. A DRE is not routinely required as an addition to PSA testing for an asymptomatic man under RACGP guidance, although examination may be useful when symptoms or other findings make it appropriate.

Why do we use PSA?

Prostate cancer may cause no symptoms in its early stages. PSA testing can identify a result that deserves a closer look before symptoms develop. Used thoughtfully, early detection may help find clinically significant cancer while treatment or monitoring options remain available.

There are limits and possible harms. PSA can be raised when cancer is not present, leading to anxiety, repeat tests, scans and sometimes biopsy. It can also find a slow-growing cancer that would never have caused a problem during a person’s lifetime. Diagnosis and treatment can have side effects, including changes to urinary continence and sexual function. The chance of benefit depends on a person’s risk, health and life expectancy. That is why Australian guidance recommends an informed discussion before testing rather than testing everyone automatically.

Is PSA a good marker for prostate disease or prostate cancer?

PSA is a useful risk marker, not a diagnosis. It can help estimate the chance of prostate cancer and guide whether further assessment is sensible. It is not a reliable general test for every prostate problem, and it cannot by itself distinguish cancer from benign enlargement or inflammation.

A low PSA lowers the chance of prostate cancer but does not make it zero. A raised PSA does not mean that cancer is present. If the result is higher than expected for a person’s age and risk, the GP will usually consider the whole picture and repeat the test before acting on a single result. Infection, inflammation, retention and recent instrumentation can affect the result, so timing and clinical context matter.

If PSA remains elevated, further assessment may include a clinical review, examination when appropriate, and prostate MRI. Current Australian guidance recommends multiparametric MRI before biopsy. A biopsy, when indicated, is what confirms whether cancer is present and provides information about its grade. Not everyone with a raised PSA needs a biopsy.

How often should PSA be tested?

Australia’s guidance has evolved. The RACGP’s Guidelines for preventive activities in general practice (Red Book, 10th edition, 2024) recommends offering informed men at average risk aged 50–69 PSA testing every two years if they choose regular testing. It recommends testing every two years from age 45 for men at moderately increased risk because of family history, and from age 40 for those at high risk due to family history, through age 69.

USANZ’s published PSA position statement is described as an interim document pending updates to the PCFA and RACGP guidelines. It supports an individualised, risk-based discussion for well-informed men over 50 with an adequate life expectancy, earlier testing from over 45 for men with a family history or higher-risk ethnicity, and from over 40 for men with a BRCA2 mutation.

Since those documents, the NHMRC approved the 2026 Guidelines for the Early Detection of Prostate Cancer in Australia. These are the latest national recommendations and give the following general pathway for people who decide to test after discussion with their GP:

Age and risk General testing approach
Average risk, age 50–69 Offer PSA testing every two years.
Higher risk, age 45 and over Offer testing every two years, using lower PSA levels to trigger a repeat test and possible referral.
Age 70 and over Individualise the decision. The guideline generally considers testing when estimated life expectancy is more than seven years.
Age 45–49, not at higher risk Routine testing is not recommended; an initial test may be discussed if the person is interested.

The 2026 guideline defines higher risk to include having a brother with prostate cancer; a father diagnosed before age 65; two or more second-degree relatives who died from prostate cancer; Black sub-Saharan ancestry; or a confirmed BRCA2 mutation. Family-history details and other health factors still need to be discussed with a GP. The guideline uses age- and risk-specific PSA action levels; a result at or above an action level is generally repeated within one to three months, rather than treated as a cancer diagnosis.

These recommendations guide discussion; they are not a substitute for individual advice. Screening recommendations apply to people without symptoms. If you have symptoms, your GP may recommend assessment regardless of your age or the usual testing interval.

How important is family history?

Family history can make a real difference. Prostate cancer in a close relative, especially a brother, or a father diagnosed at a younger age, can increase a person’s risk and may mean discussing PSA testing earlier than age 50. Multiple affected relatives can also point to an inherited risk. A known BRCA2 mutation is another important risk factor.

If you know that prostate cancer has affected your family, tell your GP which relative was affected and how old they were when diagnosed. Also mention any known breast, ovarian, pancreatic or other cancers in the family, as these may help the GP decide whether genetic counselling or testing should be discussed. Do not wait for symptoms before raising a strong family history.

When should I see a urologist?

Your GP is usually the right first contact. A referral to a urologist may be appropriate if a repeat PSA remains at or above the age- and risk-based action level, if the prostate examination is concerning, or if MRI or other findings suggest that specialist assessment is needed. A urologist can discuss the benefits and limits of further tests, including MRI and biopsy, and help decide on next steps.

Make an appointment with your GP if you notice persistent or new urinary problems, blood in your urine or semen, or ongoing unexplained pain. These symptoms can have many causes and do not automatically mean prostate cancer, but they deserve assessment. Do not wait for a routine PSA check if you have a concerning symptom. If you cannot pass urine, seek urgent medical care.

A useful Movember conversation

Ask your GP: “Given my age, health and family history, should I have a PSA test? If we test, how often should I repeat it, and what would we do if it is raised?” Knowing your family history and discussing the possible benefits and harms can make the decision more useful than simply ordering a blood test without a plan.

Movember is a reminder to look out for one another. Start the conversation, share what you know about your family history, and encourage the men in your life to seek advice when something does not feel right.

This article provides general information and is not a substitute for personal medical advice. PSA testing is a shared decision between you and your healthcare professional.

References and further information

  1. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia: summary and recommendations. NHMRC approved 18 May 2026.
  2. The Royal Australian College of General Practitioners. Guidelines for preventive activities in general practice, 10th edition — prostate cancer, recommendations updated 28 June 2024.
  3. Urological Society of Australia and New Zealand. PSA Testing position statement. Interim guidance pending updated guidelines.
  4. Huang S, Chen DC, Crowe J, et al. Navigating the shift: New RACGP Red Book guidelines for prostate-specific antigen testing in general practice. Australian Journal of General Practice. 2025;54(12). Article PDF.

Movember: Men’s mental health

Movember: Men’s mental health and suicide prevention in Australia

Content note: This article discusses suicide. If you are in immediate danger, call 000. Support contacts are listed below.

Movember gives us a visible reminder to talk about men’s health. The moustache can start a conversation, but the more important work is noticing when someone is struggling, listening without judgement and helping them connect with support.

Mental health difficulties are common, treatable and not a personal failure. Suicide is complex: it rarely has one cause, and a difficult period does not mean a person is destined to reach crisis. Timely support, connection and practical help can make a difference.

The Australian picture

The latest Australian Bureau of Statistics (ABS) release available for this article covers deaths registered in 2025. It recorded 3,283 deaths by suicide, including 2,425 males—73.9% of the total. The male age-standardised rate was 17.3 deaths per 100,000 males. The 2025 figures are preliminary and may be revised as coronial investigations are completed. [1]

Age-standardised rates allow comparisons between populations with different age structures. The age-specific rates below are deaths per 100,000 people in the same age group; they describe population patterns, not an individual’s likelihood of suicide.

Age group Male suicide rate in 2025 (per 100,000) What the ABS reported about recorded risk factors
15–24 9.5–18.1 (15–19: 9.5; 20–24: 18.1) Suicide ideation was the most commonly recorded risk factor for people under 25. For children aged 5–17, recorded factors also included education, family and peer relationships, social environment and prior self-harm.
25–44 19.7–26.0 (25–29: 19.7; 30–34: 23.1; 35–39: 26.0; 40–44: 23.3) Relationship circumstances were the most commonly recorded risk factor in this age range. Psychoactive substance use was also frequently recorded.
45–64 23.0–26.8 (45–49 was the peak at 26.8) Mood disorders, including depression, were the most commonly recorded risk factor for people aged 45–84.
65–84 16.2–22.8 Rates varied across these age bands; mood disorders were commonly recorded. Illness, pain and disability may also affect wellbeing and quality of life.
85 and over 24.9 Limitation of activities due to illness or disability was the most commonly recorded risk factor in this age group.

These age bands summarise the ABS’s five-year age data. In 2025, the highest male age-specific rate was among men aged 45–49 (26.8 per 100,000); the largest proportion of male deaths occurred among men aged 35–39 (10.7%). Both figures matter, but they measure different things. [1]

The ABS also records risk factors mentioned in preliminary death registrations. In 2025, the most frequently recorded factors across all people who died by suicide were mood disorders (35.8%), suicidal ideation (30.7%), problems in spousal relationship circumstances (26.7%), a personal history of self-harm (24.3%), and anxiety or stress-related disorders (21.9%). Several factors can be recorded for one person. These are not proof that any single factor caused a death, and the data may change as investigations are finalised. [1]

Mental health concerns can look different from one man to another

In the ABS National Study of Mental Health and Wellbeing, conducted in 2020–2022, 18.3% of males aged 16–85 reported a 12-month mental disorder. Anxiety disorders were reported by 13.3%, affective disorders (including depression) by 6.5%, and substance-use disorders by 4.4%. The equivalent substance-use figure for females was 2.1%. The survey found the highest prevalence of any 12-month mental disorder among males aged 16–24 (32.4%); prevalence declined across older age groups. These are survey estimates, not current-year suicide rates, and they do not mean that everyone with a mental disorder is suicidal. [2]

Depression and anxiety may involve persistent low mood, loss of interest, worry, panic, irritability, poor concentration, sleep changes or feeling overwhelmed. Some men describe distress mainly through anger, pulling away from family or friends, working excessively, taking more risks, or relying more heavily on alcohol or other drugs. These signs are not a diagnosis, but a lasting change from someone’s usual self is a good reason to check in. [3]

There is no single cause

Mental health and suicide risk develop through an interaction of individual, social and economic circumstances. A person may be affected by one issue or many at once. Factors that can contribute to distress include:

  • depression, anxiety, trauma, other mental health conditions or a previous episode of self-harm;
  • relationship conflict, separation, family stress, loneliness or bereavement;
  • financial pressure, unemployment, job insecurity, workplace stress or legal problems;
  • harmful alcohol or other drug use, which can worsen mood, judgement and coping;
  • chronic illness, pain, disability, sleep problems or loss of independence;
  • discrimination, bullying, violence, social exclusion or barriers to culturally safe care;
  • limited social support, or feeling unable to ask for help.

These are possible contributors, not a checklist that predicts what one person will do. A 2025 analysis of the Australian Ten to Men longitudinal study found that the onset of suicidal thoughts was associated with depressive symptoms, disability, financial stress, lower education, sexual orientation and a history of partner violence. The study also found that suicidal thoughts remitted for many men over time, an important reminder that suicidal thinking can change and support can help. Associations in a study do not establish that a factor causes an outcome. [4]

Ideas about having to cope alone or always appear strong can make it harder for some men to talk openly or seek help. This is not true of every man, and strength, responsibility and care for others can also support recovery. A 2025 Australian review found a broad range of formal and informal services for men, while noting that evidence about their effectiveness remains uneven. Services are more useful when they are accessible, respectful and responsive to the person in front of them. [5]

How to support a mate, partner or family member

Movember shares the ALEC approach, developed by R U OK?, as a simple guide for a supportive conversation: [6]

  • Ask how he is going and mention a change you have noticed: “You haven’t seemed yourself lately. How are things really going?”
  • Listen without judgement or rushing to solve everything. Give him time to speak.
  • Encourage action: offer to help contact a GP, counsellor or trusted person, or to go with him to an appointment.
  • Check in again. A message or planned catch-up can show that your support continues after the first conversation.

If you are worried he may be thinking about suicide, ask clearly and calmly whether he is thinking about suicide. Take the answer seriously. You do not need to manage the situation alone: involve a trusted person and contact a crisis service or health professional. If there is immediate danger, call 000 or go to an emergency department.

Getting help in Australia

  • Immediate danger: call 000 or attend an emergency department.
  • Lifeline: call 13 11 14 for 24/7 crisis support. [7]
  • Suicide Call Back Service: call 1300 659 467 for 24/7 telephone and online counselling. [8]
  • MensLine Australia: call 1300 78 99 78 for telephone and online counselling for men. [9]
  • Beyond Blue: call 1300 22 4636 for mental health support and information. [10]
  • Your GP: can discuss symptoms, safety, treatment options and referrals. If you are not sure where to start, a GP appointment is a practical first step.

If you are supporting someone, stay connected and help them access care. If you are struggling yourself, you deserve support too. You do not have to wait until things feel unbearable before reaching out.

A Movember conversation can matter

Movember’s focus on prevention, early intervention and social connection is a useful invitation to check in, not only during November, but throughout the year. The first conversation does not need to be perfect. Ask, listen, help with one next step and follow up.

This article is general information and is not a substitute for individual medical or mental health advice.

References

  1. Australian Bureau of Statistics. Intentional self-harm (suicide) deaths, 2025. Preliminary registered-death data; includes age-specific rates and risk factors.
  2. Australian Bureau of Statistics. National Study of Mental Health and Wellbeing, 2020–2022.
  3. Movember. Spot the signs of poor mental health.
  4. Haregu T, Armstrong G. Understanding the onset and remission of suicidal thoughts in Australian men: Findings from the Ten to Men study. Australian & New Zealand Journal of Psychiatry. 2025. doi:10.1177/00048674251333572.
  5. Slade A, Reily NM, Fujimoto H, et al. Men’s mental health and suicide prevention service landscape in Australia: a scoping review. BMC Public Health. 2025;25:1593. doi:10.1186/s12889-025-22676-6.
  6. Movember. ALEC conversation strategy. Movember credits R U OK? for developing the ALEC model.
  7. Lifeline Australia. Lifeline Crisis Support.
  8. Suicide Call Back Service. Get support.
  9. MensLine Australia. Contact MensLine.
  10. Beyond Blue. Men’s mental health.

Support Movember

Help stop men dying too young: support Movember

Every November, the moustache gives us a reason to start a conversation. But Movember is about much more than facial hair. It brings attention to the health issues that affect men and boys, and supports work in prostate cancer, testicular cancer, mental health and suicide prevention.

I’m raising funds for these causes because they touch the lives of our dads, brothers, sons, partners, friends and mates. A diagnosis, a difficult period with mental health, or the loss of someone to suicide can affect an entire family and community.

Why this matters

You may have seen the message that men die, on average, six years earlier than women. The figure depends on the population and source: Movember’s current Australian campaign reports around four years in Australia and 4.5 years globally. The difference is a reminder that men’s health deserves attention throughout the year, not only when a problem becomes hard to ignore.

Movember focuses on prostate cancer, testicular cancer, mental health and suicide prevention. Donations support programs and research across these areas. The charity also encourages men to look after their health, stay connected and reach out when they need support.

How you can help

If you’re able, please consider making a donation through my Mo Space. Every contribution helps support Movember’s work. Sharing the page or talking about men’s health with someone you care about also helps keep these issues in view.

Donate via my Mo Space:


QR Code


Thank you for supporting this cause: for all the dads, brothers, sons and mates in your life.

Together, we can help stop men dying too young.


Movember’s current information and cause areas: Movember Australia – Our cause and Movember Australia – FAQs.

Hydronephrosis: what it means and how it is treated

Finding out that a kidney is swollen on a scan can be worrying. The word hydronephrosis sounds like a diagnosis, but it describes an appearance: urine is collecting and stretching the drainage system of one or both kidneys. It is a sign that needs to be understood in context. It does not, by itself, tell us why it has happened, whether a cancer is present, or whether an operation is needed.

Many causes are treatable, and some cases can be monitored safely. The right approach depends on the cause, the degree and duration of blockage, kidney function, symptoms, overall health and, when cancer is involved, what matters most to the person receiving care.

What are unilateral and bilateral hydronephrosis?

Each kidney drains urine through a tube called a ureter into the bladder. Unilateral hydronephrosis affects one kidney; bilateral hydronephrosis affects both. A blockage may be within the kidney or ureter, or lower down where it affects the bladder outlet. A full bladder or difficulty emptying can sometimes cause dilation on both sides.

One healthy kidney can often maintain overall kidney function when the other side is obstructed. This can mean that a person with a one-sided blockage has few symptoms and normal blood tests. With obstruction affecting both kidneys, or a person who has only one functioning kidney, kidney function can become impaired more quickly. The scan appearance alone does not show how well each kidney is working.

What can cause hydronephrosis?

Causes may be benign (non-cancerous) or malignant (related to cancer). They include:

  • Kidney or ureteric stones, which may block urine flow and cause pain, blood in the urine or infection.
  • Narrowing or scarring of the ureter (a stricture), sometimes following previous surgery, instrumentation, infection or radiation treatment.
  • Bladder outlet obstruction or poor bladder emptying, including from an enlarged prostate before prostate surgery, urethral narrowing, a tight bladder-neck/anastomotic scar after surgery, or a bladder that does not contract effectively.
  • Anatomical or functional conditions, such as a narrowing where the kidney joins the ureter (a pelvi-ureteric junction obstruction), reflux of urine towards the kidney, or in some circumstance, pregnancy.
  • Blood clots or inflammation, which can temporarily obstruct drainage.
  • Cancer, either growing in the urinary tract or pressing on a ureter from nearby tissues or lymph nodes. Possible cancers include prostate, bladder, bowel, gynaecological and other pelvic or abdominal cancers. A cancer-related cause is only one possibility; imaging and clinical assessment are needed to establish the cause.

Prostate cancer and hydronephrosis

Prostate cancer can affect urine drainage in different ways. A locally advanced tumour may involve the bladder outlet or the area where the ureters enter the bladder. Cancer in pelvic or abdominal lymph nodes can press on one or both ureters. These problems are more likely with locally advanced or recurrent disease than with an early cancer confined to the prostate, but each person’s situation is different.

Hydronephrosis in someone who has had prostate cancer does not automatically mean the cancer has returned. Stones, infection, scarring, bladder-emptying problems and unrelated conditions remain possible. The team will consider the person’s history, prostate-specific antigen (PSA) trend, symptoms, blood and urine tests, and the pattern seen on imaging. Further tests may be appropriate if the cause is not clear.

After radical prostatectomy

After prostate removal, the bladder is joined to the urethra. Scarring at this join (a vesicourethral anastomotic stenosis, sometimes called a bladder-neck contracture) can make it difficult to empty the bladder. Significant retention may raise pressure in the bladder and contribute to dilation of both upper urinary tracts. A ureteric injury or later narrowing is a less common possibility. Recurrent cancer or enlarged lymph nodes can also obstruct a ureter, but this is not the only explanation.

Assessment may include checking bladder emptying, kidney function and imaging, with a camera examination or contrast study if needed. Treatment is directed at the level and cause of the blockage: for example, bladder drainage, treatment of a narrowing, or drainage of an obstructed ureter.

After salvage radiation therapy

Radiation can cause inflammation and, less commonly, delayed scarring in urinary tissues. Narrowing of the urethra or bladder outlet can interfere with emptying. A ureteric stricture after pelvic radiation is uncommon, but may develop months or years later. Salvage radiation after prostatectomy is generally directed to the prostate bed; hydronephrosis that appears afterwards still needs a proper assessment rather than being assumed to be a radiation effect or a cancer recurrence.

If imaging shows a narrowed ureter, the team may use CT or MRI, a contrast study, or a functional kidney scan to clarify its site, length and effect on kidney drainage. Treatment can be more complex in previously irradiated tissue, so decisions are individualised and may involve a reconstructive urologist, radiation oncologist, medical oncologist or interventional radiologist.

Symptoms and when to seek urgent care

Hydronephrosis can cause no noticeable symptoms, particularly when it develops gradually or affects one kidney. When symptoms occur, they may include pain in the side, back or abdomen; nausea or vomiting; blood in the urine; difficulty passing urine; or repeated urinary infections.

Please seek urgent medical assessment for fever or shaking chills with suspected urinary blockage, severe or worsening pain, repeated vomiting, very little or no urine, confusion, or feeling suddenly very unwell. Infection behind a blockage can become serious and may need urgent antibiotics and drainage. Sudden inability to pass urine also needs prompt care.

How is it investigated?

The first aim is to understand whether there is a blockage that needs prompt relief and what is causing it. Assessment commonly includes:

  1. A conversation and examination, including previous cancer treatments, operations, stones, infections, urinary symptoms and medicines.
  2. Blood tests, especially creatinine and estimated kidney function, and urine tests for infection or blood.
  3. Ultrasound, which can show dilation of the kidneys and bladder and whether the bladder empties.
  4. CT or MRI, selected according to the suspected cause and the person’s kidney function, to look for stones, strictures, masses or enlarged lymph nodes.
  5. Additional tests where useful: a MAG3 renal scan can assess each kidney’s contribution and drainage; cystoscopy or contrast X-rays can clarify the bladder outlet or ureter.

Not everyone needs every test. The clinician will choose investigations that answer the question while taking account of kidney function, previous treatment and the person’s circumstances.

Management options

Treatment is tailored to the cause and the degree of risk. The goals may be to protect kidney function, treat infection or pain, restore urine flow, enable other cancer treatment, or support comfort and quality of life.

Observation and treatment of the cause

Mild, stable hydronephrosis may sometimes be monitored with repeat blood tests and imaging, particularly if there is no infection, troublesome pain or evidence of kidney function decline. A stone may pass or be treated with medication, ureteroscopy or another stone procedure. Infection is treated with antibiotics. Retention may be relieved with a bladder catheter while the cause is assessed. A benign narrowing may be treated by endoscopic incision or dilation, reconstruction, or another procedure depending on its location and the person’s health.

Draining the kidney

If drainage is needed, there are two common approaches:

  • Ureteric stent (often called a JJ stent): a thin internal tube placed between the kidney and bladder, usually using a camera. It can avoid an external collection bag, but may cause urinary frequency, urgency, discomfort, blood in the urine or infection, and it usually needs planned replacement or removal. A tight narrowing or external cancer pressure can make stent placement difficult or less reliable.
  • Percutaneous nephrostomy: a small tube placed through the skin of the back into the kidney, usually by an interventional radiologist, to drain urine into an external bag. It can be useful when a stent cannot be placed, has not drained adequately, or rapid reliable drainage is needed. The tube needs care and periodic changes and can affect daily activities.

The choice depends on the site and cause of obstruction, infection, anatomy, kidney function, expected duration, other treatment plans and personal preference. Sometimes a nephrostomy is used first, with an internal stent considered later. Drainage can relieve pressure and help kidney function, but it does not remove the underlying cause; further treatment or monitoring is often needed.

When might palliative care be part of the plan?

“Palliative” can sound frightening, but palliative care is focused on comfort, symptom relief, support and quality of life. It can be provided alongside active cancer treatment. It does not mean that someone is being abandoned or that all treatment has stopped.

When hydronephrosis is caused by advanced cancer, a stent or nephrostomy may help with pain, infection, kidney function, or the ability to receive cancer treatment. It can also bring burdens such as procedures, hospital visits, tube or stent symptoms, repeat exchanges and complications. In some situations, drainage may not improve symptoms or kidney function enough to outweigh those burdens. Evidence in this area is limited, and outcomes vary widely; population averages cannot predict an individual person’s future.

There is no single point at which palliation is “required.” The decision is made with the patient, their chosen supports and the treating team. It can help to discuss:

  • What problem are we hoping drainage will improve?
  • How likely is it to help, and how soon might we know?
  • What would living with a stent or nephrostomy involve?
  • Could the result allow another treatment that matters to me?
  • What might happen if we monitor or manage symptoms without drainage?
  • What matters most to me now: time at home, symptom relief, kidney function, further cancer treatment, or avoiding procedures?

Choosing not to have a procedure is also a valid choice when it best fits a person’s wishes and clinical circumstances. The team can still treat pain, nausea, infection and other symptoms, and provide practical and emotional support. These conversations are best held early and revisited as circumstances change.

In summary

Hydronephrosis means that urine is collecting in one or both kidneys, but it does not identify the cause on its own. Many causes are benign and treatable. Prostate cancer, previous prostate surgery and radiation can be relevant, but a careful assessment is needed before drawing conclusions. Some people need urgent drainage; others can be monitored or treated in a less invasive way. When cancer is advanced, decisions about drainage and palliative care should be compassionate, individualised and guided by what is most important to the person.

References and further reading

  1. National Kidney Foundation. Hydronephrosis. Updated 2023.
  2. Mayo Clinic. Hydronephrosis: Diagnosis and treatment. Updated 2024.
  3. European Association of Urology. EAU Guidelines on Urolithiasis. See section on sepsis and anuria in an obstructed kidney.
  4. National Institute for Health and Care Excellence. Prostate cancer: diagnosis and management (NG131). Includes recommendations on upper urinary tract decompression for obstructive uropathy secondary to hormone-relapsed prostate cancer.
  5. Chorbińska J, Krajewski W, Zdrojowy R. Urological complications after radiation therapy—nothing ventured, nothing gained: a narrative review. Transl Androl Urol. 2021;10(8):3553–3566. doi:10.21037/tau-20-1217.
  6. Carilli M, et al. Management of ureteral stricture disease after radiation therapy for pelvic malignancies. Cancers (Basel). 2024;16(21):3561. doi:10.3390/cancers16213561.
  7. Shah M, et al. Malignant upper urinary tract obstruction in cancer patients: a systematic review. BJUI Compass. 2024;5(11):915–925. doi:10.1002/bco2.340.
  8. Gauhar V, et al. Nephrostomy tube versus double J ureteral stent in patients with malignant ureteric obstruction: a systematic review and meta-analysis of comparative studies. Int Braz J Urol. 2022;48(6):903–914. doi:10.1590/S1677-5538.IBJU.2022.0225.

This page provides general information and is not a substitute for an individual assessment by a qualified health professional. If you have hydronephrosis, your clinician can explain what the scan means in your circumstances and whether further tests or treatment are needed.

PUJ obstruction: when urine cannot drain freely from the kidney

Understanding pelvi-ureteric junction obstruction, its symptoms, investigations and treatment, including robotic-assisted pyeloplasty.

The kidneys produce urine, which collects in a funnel-shaped area called the renal pelvis before travelling down the ureter to the bladder. The pelvi-ureteric junction (PUJ) is where this funnel joins the ureter.

PUJ obstruction means urine does not pass freely through this junction. It is also called ureteropelvic junction obstruction, or UPJ obstruction. The collecting system can enlarge, a finding called hydronephrosis, and significant obstruction may eventually damage the affected kidney. However, a dilated collecting system does not automatically mean surgery is needed. Assessment must establish whether drainage is impaired and whether kidney function is at risk. [1,2]

What causes PUJ obstruction?

Some people are born with a short segment that is narrow or does not propel urine normally. Other anatomical causes include kinking or a ureter that joins the renal pelvis unusually high up. A blood vessel supplying the lower part of the kidney may cross the junction and contribute to compression. Seeing a crossing vessel on a scan does not, by itself, prove that it is causing obstruction.

A congenital problem may first become apparent in adulthood. Acquired narrowing can follow scarring, inflammation or previous surgery. Stones and other causes of upper urinary tract blockage must also be considered during investigation. [2,12]

How does it present?

Symptoms range from none at all to episodes of significant pain. Possible presentations include:

  • Aching or intermittent pain in the flank, the side of the back below the ribs.
  • Episodes of more severe pain, sometimes with nausea or vomiting.
  • Pain after a large fluid intake, when urine production increases.
  • Recurrent urinary infections, including infection of the kidney.
  • Blood in the urine or kidney stones.
  • An incidental finding of hydronephrosis on a scan.

Intermittent painful distension is sometimes called a Dietl’s crisis. These symptoms can also have other causes, so pain or blood in the urine should not simply be attributed to a known PUJ problem. [3,12]

Children may be diagnosed following an antenatal ultrasound. Childhood assessment and treatment decisions differ from those in adults and should involve a paediatric urology team. [3]

Which investigations are useful?

The investigation plan answers three questions: What does the anatomy look like? How well does each kidney function? Is urine drainage genuinely obstructed?

Urine and blood tests

Urine testing looks for blood and evidence of infection; a urine culture is useful when infection is suspected. Blood tests include creatinine and estimated glomerular filtration rate (eGFR). These assess overall kidney function, but can remain normal when the other kidney compensates for an affected kidney. [2,10]

Ultrasound

Ultrasound shows collecting-system dilatation and assesses the thickness of the kidney tissue. It is useful for follow-up because it does not involve radiation. Ultrasound alone cannot reliably establish the functional significance of a PUJ narrowing. [2,3]

CT or MR urography

CT urography can define the junction, identify stones and assess surrounding structures, including crossing vessels. The use of intravenous contrast depends on kidney function and other clinical factors.

MR urography is an alternative in selected patients, particularly when avoiding radiation is desirable. The choice of scan is individualised. [1,2]

MAG3 diuretic renogram

This nuclear medicine scan follows a small injected tracer through the kidneys. A diuretic, usually furosemide, helps assess drainage.

It measures:

  • Differential or split renal function: the proportion contributed by each kidney.
  • Drainage: how effectively tracer leaves the collecting system.

Interpretation considers the images, drainage curves, kidney function, hydration and bladder emptying. A slow drainage number alone is insufficient to diagnose clinically significant obstruction: a large collecting system or poorly functioning kidney can make interpretation difficult. [4]

Further tests in selected cases

A retrograde pyelogram introduces contrast into the ureter during a telescopic bladder examination. It can clarify anatomy when other imaging is incomplete. It is not routinely needed in every patient. [2]

Does every PUJ obstruction need treatment?

No. Observation can be appropriate when symptoms are absent or minor, kidney function is stable, and assessment does not suggest harmful obstruction. Monitoring may include symptoms, ultrasound and repeat functional imaging when indicated. The interval depends on the findings. [5]

Intervention is more likely to be recommended for persistent or troublesome symptoms, recurrent kidney infections, associated stones, or deteriorating function. Decisions use the overall clinical picture rather than the ultrasound appearance alone. [2]

What are the treatment options?

Option When it may be considered Main limitation
Observation Stable function with few symptoms Requires planned follow-up
Ureteric stent or nephrostomy Urgent drainage or temporary management Usually does not permanently correct the narrowing
Endopyelotomy or balloon dilatation Selected narrowings or recurrent obstruction Generally less durable than reconstructive repair
Pyeloplasty A significant obstruction requiring reconstruction Requires an operation and recovery

Temporary or emergency drainage

A ureteric stent passes internally from the kidney to the bladder. A nephrostomy drains the kidney through a tube placed through the skin of the back. These can relieve obstruction while infection is treated or definitive surgery is planned. [5,9]

An infected obstructed kidney is an emergency. Antibiotics may be needed together with urgent drainage. Definitive reconstruction is usually considered after the acute problem has been controlled. [9,10]

Endoscopic treatment

Endopyelotomy opens the narrowed segment from inside the urinary tract; balloon dilatation stretches it. Suitability depends on the anatomy, kidney function and previous treatment.

A large observational study found more repeat procedures after endopyelotomy than after pyeloplasty. Because patients were not randomly assigned to treatment, these results inform discussion but cannot predict an individual outcome. [1,6]

Robotic-assisted pyeloplasty: how is the repair performed?

Pyeloplasty reconstructs the junction to improve drainage. It can be performed through an open incision, conventional laparoscopic keyhole surgery, or robotic-assisted keyhole surgery.

The commonly used Anderson–Hynes dismembered pyeloplasty removes the narrowed segment. The surgeon opens the ureter more widely and stitches it back to the renal pelvis, creating a broader connection. Where a crossing vessel contributes to obstruction, the reconstruction can be positioned in front of it while preserving the vessel. [3]

During robotic-assisted surgery, the surgeon controls the instruments from a console. Magnified three-dimensional vision and articulated instruments assist dissection and suturing. The robot does not operate independently. [7]

A temporary internal stent is commonly placed to support healing. A bladder catheter and, sometimes, a drain may also be used initially. [5,7]

How successful is pyeloplasty, and is robotic surgery better?

Published literature commonly reports success above 90% for primary pyeloplasty, including open, laparoscopic and robotic approaches. Success may mean symptom relief, improved drainage or freedom from further surgery; definitions and follow-up differ between studies. These figures are not a guarantee. [1]

Robotic surgery is an established option, but it should not be presented as necessary or universally superior. Comparative research supports good outcomes with both conventional laparoscopic and robotic repair. Much of the evidence is observational, with differences in patient selection, surgical experience and follow-up. The choice should consider anatomy, surgeon expertise, availability and cost. [8]

The goals are to improve drainage, relieve attributable symptoms and preserve function. Previously lost kidney function may not fully recover, even after a technically successful operation. [11]

What are the risks and recovery expectations?

Risks include bleeding, infection, urine leakage, injury to nearby structures, recurrent narrowing, persistent pain and the need for another procedure. Anaesthetic complications and blood clots are also possible. Occasionally, conversion to open surgery is required. [5,7]

Stents can cause urinary frequency, urgency, blood in the urine and discomfort. Their removal must be arranged. Many patients leave hospital after approximately one to three days following uncomplicated keyhole repair, but recovery varies. Stents are often removed after four to six weeks. [5,7]

Follow-up may include ultrasound and a repeat drainage scan. Residual dilatation does not automatically mean the repair has failed; symptoms, drainage and function are assessed together. [4]

What if the kidney already functions poorly?

A low split-function result does not automatically mean the kidney must be removed. Selected patients may benefit from reconstruction or temporary drainage followed by reassessment. A systematic review found that pyeloplasty may relieve symptoms and stabilise function in poorly functioning kidneys, but the evidence was limited and recovery was unpredictable. [11]

Nephrectomy may be considered if the kidney has negligible useful function and causes ongoing pain or infection. This requires an individual discussion, including the health of the other kidney.

When should I seek urgent help?

Seek urgent medical assessment for fever or shaking chills with flank pain, severe uncontrolled pain, persistent vomiting, markedly reduced urine output, or feeling seriously unwell. The threshold for urgent assessment is particularly low if you have a single functioning kidney. [9,10]

This page provides general education and does not replace an individual assessment. The most suitable investigation and treatment depend on symptoms, anatomy, kidney function and overall health.

References

  1. Khan F, Ahmed K, Lee N, et al. Management of ureteropelvic junction obstruction in adults. Nature Reviews Urology. 2014;11:629–638. doi:10.1038/nrurol.2014.240.
  2. Borin JF. Ureteropelvic Junction Obstruction in Adults. Reviews in Urology. 2017;19(4):261–264. Full text.
  3. Oxford University Hospitals NHS Foundation Trust. PUJ Obstruction and Pyeloplasty: information for parents and carers. 2025. Patient leaflet. Used for congenital presentation and reconstruction principles; adult management differs.
  4. SNMMI/EANM. Procedure Standard/Practice Guideline for Diuretic Renal Scintigraphy in Adults With Suspected Upper Urinary Tract Obstruction 1.0. 2018. Guideline.
  5. British Association of Urological Surgeons. Keyhole reconstruction of the kidney pelvis: laparoscopic pyeloplasty. 2023. Patient leaflet.
  6. Jacobs BL, Lai JC, Seelam R, et al. The comparative effectiveness of treatments for ureteropelvic junction obstruction. Urology. 2018;111:72–77. doi:10.1016/j.urology.2017.09.002.
  7. Kingston and Richmond NHS Foundation Trust. Kidney obstruction removal with robot. Patient information.
  8. Uhlig A, Uhlig J, Trojan L, et al. Surgical approaches for treatment of ureteropelvic junction obstruction—a systematic review and network meta-analysis. BMC Urology. 2019;19:112. doi:10.1186/s12894-019-0544-7.
  9. Guy’s and St Thomas’ NHS Foundation Trust. Nephrostomy catheter to drain urine from the kidney. Patient information.
  10. NHS. Hydronephrosis. Patient information.
  11. Pyeloplasty in Adults With Ureteropelvic Junction Obstruction in Poorly Functioning Kidneys: A Systematic Review. 2021. PubMed.
  12. Cleveland Clinic. Ureteropelvic Junction Obstruction. Reviewed 2024. Patient information.

Prepared October 2026.

Nephroptosis: is a “floating kidney” really a thing?

Can a kidney move enough to cause pain? Yes. Nephroptosis is a recognised anatomical condition, and in selected people it can cause symptoms. However, finding a mobile kidney does not automatically explain abdominal or flank pain. Establishing that connection is the central challenge, and the reason this condition has attracted controversy for more than a century.[1,2]

What is nephroptosis?

The kidneys normally sit towards the back of the abdomen, supported by surrounding fat and connective tissues. Some movement with breathing and changes in posture is normal.

Nephroptosis, also called a floating or mobile kidney, is conventionally defined as downward movement of more than 5 cm, or approximately two vertebral body heights, when a person moves from lying down to standing. A kidney can also rotate or move towards the midline.[3,4]

This differs from a congenital pelvic kidney, which developed in a lower position and stays there.

Published reports describe it more often in slim women and more often on the right, although men and people with other body types can be affected. Reduced support from surrounding fat is a proposed contributor. The true prevalence of symptomatic nephroptosis is uncertain; historical figures from people undergoing particular imaging tests should not be treated as estimates for the general population.[4]

How does it present?

Many mobile kidneys cause no symptoms. When symptoms occur, a suggestive pattern is:

  • An ache, dragging sensation or intermittent pain in the flank, the side between the lower ribs and hip, or abdomen.
  • Pain that becomes worse with standing, prolonged activity or particular positions.
  • Improvement when lying down.
  • Occasionally, a feeling of something moving within the abdomen.

Some patients experience more severe episodes with nausea or vomiting. Positional pain is a useful clue, but it does not establish the diagnosis.[2,5]

Possible mechanisms include intermittent kinking of the ureter, which drains urine to the bladder; stretching or twisting of the kidney’s blood vessels; or traction on nerves around the kidney. These mechanisms may differ between patients. Severe episodic pain from intermittent upper urinary tract obstruction is sometimes called a Dietl’s crisis, but that term is not specific to nephroptosis.[4,5]

Blood in the urine or urinary infections require investigation in their own right and should not simply be attributed to a mobile kidney.

How is the diagnosis made?

There are two separate questions: Does the kidney move excessively? And is that movement responsible for symptoms or impaired function?

1. Establish the symptom pattern and assess other causes

A consultation should explore where the pain occurs, its relationship to posture and activity, what relieves it, and associated urinary or gastrointestinal symptoms. Examination, urine testing and blood tests for kidney function help guide the investigation.

Other explanations include kidney stones, infection, obstruction at the junction between the kidney and ureter, musculoskeletal pain, and gastrointestinal or gynaecological conditions. Depending on the presentation, these may be more likely. A mobile kidney can coexist with an unrelated cause of pain.[2,3]

2. Compare imaging in different positions

A normal scan performed lying down may not exclude a problem that occurs when upright. If the clinical pattern raises suspicion, the imaging request should make the positional question explicit.[3,5]

Investigation What it can contribute Main limitation
Ultrasound lying down and upright Demonstrates movement and checks for changes in collecting-system dilatation Operator dependent; requires a deliberate positional examination
Doppler ultrasound in different positions May identify posture-related changes in renal blood flow An adjunct rather than a definitive test of the cause of pain
Positional nuclear medicine renal scan Assesses drainage and each kidney’s contribution to function; may reveal changes when upright Needs an appropriate protocol and careful interpretation
Intravenous urography with supine and erect images Historically used to measure kidney descent Used less often today; involves radiation and contrast
Selected positional CT urography Can clarify anatomy, rotation or medial movement Routine supine CT may miss positional mobility; repeat imaging adds radiation

The choice should be agreed with radiology or nuclear medicine. Not every centre routinely performs these protocols, and not every patient needs every test.[3,5,6]

3. Link the findings to the symptoms

Diagnostic confidence is stronger when the side and timing of the pain match the demonstrated movement, particularly if there is associated impaired drainage or blood flow. Nevertheless, some symptomatic patients have no demonstrable obstruction. The absence of obstruction does not conclusively exclude symptomatic nephroptosis, but it makes careful exclusion of other causes especially important.[3,4,6]

Normal overall kidney function does not, by itself, exclude an intermittent positional problem. Equally, descent beyond a measurement threshold is not sufficient justification for surgery.[2,5]

What are the treatment options?

Observation and symptom management

An incidentally discovered mobile kidney without symptoms or functional consequences generally does not require surgery.[5]

For mild symptoms, an individual plan may include modifying provoking activities, appropriate pain relief and reviewing other possible contributors. Abdominal supports, exercises and nutritional measures have been used historically, but convincing evidence that they reliably correct symptomatic nephroptosis is limited. They should not be presented as proven cures. Weight gain is not a universal recommendation.[1,2]

Nephropexy: fixing the kidney in position

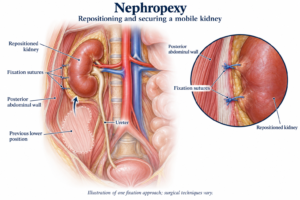
Nephropexy repositions the kidney and secures it to surrounding tissues to limit excessive movement. It aims to preserve the kidney and relieve symptoms or positional impairment.

It may be considered when symptoms substantially affect daily life, nephroptosis has been demonstrated with appropriate imaging, other explanations have been reasonably excluded, and the evidence suggests a meaningful relationship between movement and symptoms. Documented positional obstruction or impaired perfusion strengthens the rationale.[2,3,5]

Modern surgery is usually laparoscopic, through the abdomen or behind it. Robotic assistance has also been described, but there is no convincing comparative evidence that it produces better outcomes than conventional laparoscopy for this condition. Fixation techniques vary, and some published methods use mesh while others use sutures.[3]

Open surgery is less commonly used. Percutaneous techniques, intended to stabilise the kidney through a tract and subsequent scarring, have also been reported. A recent report involved only four patients: such evidence is too limited to establish equivalence with laparoscopic surgery or support routine use.[7]

How effective is surgery, and what are the risks?

Small surgical series describe substantial improvement in selected patients. For example, a long-term study reported 13 patients assessed at a median of 5.9 years: 11 were completely satisfied and two moderately satisfied.[8]

That is encouraging, but it is not a reliable prediction for every patient. Small numbers, selection of patients, loss to follow-up and the absence of a non-operative comparison group limit what can be concluded. Fixing the kidney successfully does not guarantee that pain will disappear.[2,8]

Potential risks include bleeding, infection, injury to nearby organs, vessels or the urinary tract, anaesthetic complications, persistent or new pain, and recurrent kidney movement. If mesh is proposed, its specific benefits and risks should be discussed. Individual risks and expected recovery depend on the technique and the patient’s circumstances.

Why is nephroptosis controversial?

The controversy concerns which patients have symptoms caused by kidney mobility, and which benefit from treatment.

Historically, nephroptosis was blamed for a wide range of nonspecific symptoms, and nephropexy was performed much more frequently than it is today. Recognition that many mobile kidneys were harmless, together with inconsistent surgical results, led to scepticism and a marked decline in treatment.[1]

Modern positional imaging and minimally invasive surgery have renewed interest. However, the evidence remains dominated by small observational series and case reports rather than robust randomised comparisons. There is also no universally accepted combination of symptoms and test findings that predicts success for an individual.[2,6,8]

The appropriate response is to take the symptoms seriously while investigating the cause carefully. A normal routine scan does not mean pain is imagined. A mobile kidney does not mean an operation will solve it.

When should you seek urgent care?

Severe or escalating flank pain, fever or rigors, persistent vomiting, visible blood in the urine, or a marked reduction in urine output warrant prompt medical assessment. These symptoms can signal infection, obstruction or another problem requiring urgent treatment, regardless of whether nephroptosis is present.

This article provides general education. Diagnosis and treatment require an individual clinical assessment.

Patient information by Dr Jo Schoeman | Evidence reviewed October 2026

References

  1. Moss SW. Floating kidneys: a century of nephroptosis and nephropexy. Journal of Urology. 1997;158(3 Pt 1):699–702. doi:10.1016/S0022-5347(01)64296-4.
  2. Barber NJ, Thompson PM. Nephroptosis and nephropexy—hung up on the past? European Urology. 2004;46(4):428–433. doi:10.1016/j.eururo.2004.03.023.
  3. Mogorovich A, Selli C, De Maria M, et al. Clinical reappraisal and state of the art of nephropexy. Urologia. 2018;85(4). doi:10.1177/0391560317749191.
  4. Senaratne R, Anderson S, Kelly C, et al. Rolling in the deep: an illustrative report of symptomatic nephroptosis. Radiology Case Reports. 2024;19(9):4044–4048. doi:10.1016/j.radcr.2024.06.047. Case report.
  5. Murari SB, Gadepalli T, Rao VP, Ram R. Renal scintigraphy in diagnosis and management of nephroptosis. Indian Journal of Nuclear Medicine. 2012;27(1):52–54. doi:10.4103/0972-3919.108874. Case report.
  6. Strohmeyer DM, Peschel R, Effert P, et al. Changes of renal blood flow in nephroptosis: assessment by color Doppler imaging, isotope renography and correlation with clinical outcome after laparoscopic nephropexy. European Urology. 2004;45:790–793. PubMed.
  7. Liu H, Gao W, Zhang Z, et al. Modified percutaneous nephropexy for nephroptosis: technical description and short-term results. Current Urology. 2025;19(3):168–172. doi:10.1097/CU9.0000000000000238. Small technical series; four patients.
  8. Plas E, Daha K, Riedl CR, Hübner WA, Pflüger H. Long-term followup after laparoscopic nephropexy for symptomatic nephroptosis. Journal of Urology. 2001;166(2):449–452. PubMed.

Ureteroceles: symptoms, investigations and treatment

A ureterocoele (also spelt ureterocele) is a balloon-like swelling at the lower end of a ureter: the tube carrying urine from the kidney to the bladder. The swelling usually projects into the bladder. Its opening may be narrow, slowing urine drainage and sometimes causing infection, stones or pressure on the kidney.

Some ureterocoeles cause no problems and are found incidentally. Others need treatment to improve drainage and protect kidney function. [1,2]

Congenital or acquired?

Most true ureteroceles are congenital, meaning they develop before birth. They may be detected on pregnancy ultrasound, during childhood or much later in adult life. A diagnosis in adulthood does not necessarily mean the ureterocele developed recently.

A ureterocoele can occur with a single ureter or a duplex collecting system, in which a kidney has two drainage systems. In a duplex kidney, the ureterocoele commonly involves the ureter draining the upper part of the kidney.

An intravesical or orthotopic ureterocoele lies within the bladder. An ectopic ureterocoele extends into the bladder neck or urethra and may interfere with bladder emptying. Adults more often have an intravesical ureterocoele associated with a single drainage system. [1,3]

The term “acquired ureterocoele” needs care. An acquired swelling of the lower ureter that resembles a ureterocoele is often called a pseudoureterocoele. A stone or a lesion involving the bladder near the ureteric opening can cause this appearance. An irregular or unusual swelling should therefore be investigated rather than assumed to be a harmless congenital abnormality. [4]

Presentation and symptoms

A ureterocoele may be discovered during investigations for an unrelated problem. When symptoms occur, they can include:

  • Recurrent urinary tract infections.
  • Pain in the side, back or lower abdomen.
  • Burning, urgency or frequent urination, particularly with infection.
  • Blood in the urine.
  • Stones trapped within the ureterocoele.
  • Difficulty emptying the bladder or, occasionally, urinary retention.

Children may present with unexplained fever, feeding difficulties or poor growth associated with infection. Rarely, a large ureterocoele can prolapse through the urethra.

Symptoms depend on whether the swelling obstructs drainage, contains a stone or affects the bladder outlet. Prolonged obstruction and repeated kidney infections can damage kidney function. [2,5]

What investigations are needed?

Investigations establish the anatomy, assess drainage and kidney function, and look for infection or reflux. Not everyone needs every test.

Investigation What it helps assess
Urine testing and culture Infection and the appropriate antibiotic
Blood tests Kidney function; inflammatory markers when infection is suspected
Kidney and bladder ultrasound The ureterocoele, stones and swelling of the kidney or ureter
CT, sometimes CT urography Stones and detailed urinary tract anatomy, particularly in adults
MR urography Complex anatomy, including duplicated drainage systems
MAG3 or DMSA kidney scan Drainage and relative function, or functioning kidney tissue and scarring
Micturating cystourethrogram (MCUG/VCUG) Urine flowing backwards from the bladder into a ureter
Cystoscopy Direct inspection of the bladder and ureteric openings

CT involves radiation; contrast use depends on kidney function and the clinical question. Reflux testing is particularly relevant in children or when infection, complex anatomy or postoperative concerns warrant it. Cystoscopy can clarify an uncertain diagnosis and allow treatment during the same procedure. [1,3,5]

Does every ureterocoele need surgery?

No. Observation with planned follow-up may be appropriate when there are no troublesome symptoms, significant obstruction or recurrent infections, and kidney function is satisfactory.

Monitoring may include ultrasound and review of symptoms. Antibiotics treat infection but do not correct the swelling. Preventive antibiotics are considered selectively, particularly in children at increased infection risk. [6]

An infected, obstructed kidney requires urgent assessment and drainage, alongside antibiotics. Drainage may involve endoscopic opening of the ureterocoele or a nephrostomy, a tube placed through the skin into the kidney. Antibiotics alone may be insufficient when infected urine cannot drain. [1]

Endoscopic incision or deroofing

Treatment can often be performed through a telescope passed along the urethra into the bladder, usually under general anaesthesia.

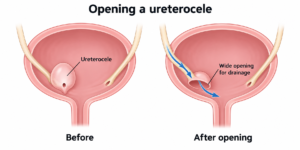
Incision or puncture creates an opening in the wall of the ureterocoele. Deroofing removes part of its wall to create a broader opening. Both aim to let urine drain freely and reduce the balloon-like swelling.

The choice depends on anatomy, obstruction and associated stones. Instruments using electrical energy or a laser may be used. A stone within the sac can sometimes be fragmented and removed at the same operation.

A bladder catheter may be needed temporarily. Endoscopic treatment can be sufficient for a straightforward adult intravesical ureterocoele, while complex duplex or ectopic cases may need further surgery. [5,7,8]

Where does a ureteric stent fit in?

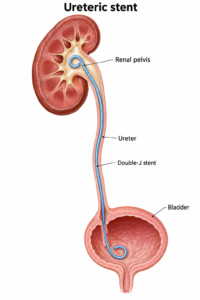
A double-J stent is a soft internal tube extending from the kidney to the bladder. It may be used selectively to support drainage after treatment, during associated stone surgery or while swelling settles. It is not required in every case and does not necessarily provide a permanent solution to the ureterocoele. [8]

Stents can cause frequency, urgency, bladder discomfort, blood in the urine and flank pain, sometimes after urination. Infection, displacement and mineral encrustation are other possible problems.

Every temporary stent needs a clear removal or exchange plan. The duration depends on the procedure and clinical circumstances. Contact the treating team if the removal date is unclear or overdue. [9]

Possible complications, including vesicoureteric reflux

Possible complications of endoscopic treatment include bleeding, infection, discomfort, injury to nearby urinary tract structures, persistent obstruction or narrowing as the opening heals. Repeat treatment or reconstructive surgery may be needed. [3,5,7]

Vesicoureteric reflux (VUR) means urine travels backwards from the bladder towards the kidney. It may already be present before treatment, particularly in a duplex system, or develop after opening the ureterocoele alters the natural anti-reflux mechanism.

Reflux does not automatically mean kidney damage or another operation. Its significance depends on its severity, infections, kidney function and bladder function. Monitoring may be appropriate; persistent significant reflux with recurrent infections can require further treatment, including ureteric reimplantation.

Risk varies with anatomy and technique. Ectopic ureterocoeles and duplex systems have higher rates of postoperative reflux and additional surgery than simpler intravesical cases. [1,7]

In one small adult study, reflux was detected in two of 23 patients followed after endoscopic incision, persisting in one at six months. These results illustrate the possibility of reflux; they do not predict an individual patient’s risk. Adult evidence largely comes from small studies. [7]

Further surgery and follow-up

Reconstructive options include reimplanting the ureter into the bladder or joining it to another healthy ureter in a duplex system. Occasionally, a severely damaged, poorly functioning kidney segment causing problems may require removal. Specialist assessment determines whether reconstruction, observation or removal is appropriate. [1]

Follow-up checks that drainage has improved and looks for recurrent infection, obstruction or reflux. Ultrasound is commonly used; further imaging is selected according to the findings. Symptom improvement alone does not confirm that drainage is normal. [5,7]

Seek urgent medical care for fever or shaking chills with flank pain, inability to pass urine, severe worsening pain, persistent vomiting or feeling seriously unwell. These symptoms may indicate infection or obstruction, including after treatment or with a stent in place. [1,9]

This article provides general education. Treatment should be tailored to the patient’s anatomy, symptoms and kidney function in consultation with their urologist.

References

  1. European Association of Urology. EAU Guidelines on Paediatric Urology: Ureterocele and ectopic ureter. Current online guideline, accessed 5 October 2026. https://uroweb.org/guidelines/paediatric-urology/chapter/ureterocele-and-ectopic-ureter
  2. European Association of Urology. Patient information: Ureterocele. https://patients.uroweb.org/condition/duplex-congenital-malformations-of-the-urinary-tract/ureterocele
  3. The Outcome of Transurethral Electro-Endoscopic Resection of Orthotopic Single System Ureterocoeles in Adults Nigerians. https://pmc.ncbi.nlm.nih.gov/articles/PMC11073836/
  4. Thornbury JR, Silver TM, Vinson RK. Ureteroceles vs. pseudoureteroceles in adults. Urographic diagnosis. Radiology. 1977;122(1):81–84. doi:10.1148/122.1.81. https://pubmed.ncbi.nlm.nih.gov/830358/
  5. An adult ureterocele complicated by a large stone: A case report. International Journal of Surgery Case Reports. 2018. https://pmc.ncbi.nlm.nih.gov/articles/PMC5927814/
  6. European Association of Urology. Watchful waiting for ureterocele. https://patients.uroweb.org/condition/duplex-congenital-malformations-of-the-urinary-tract/ureterocele/wait-and-see-ureterocele
  7. Vijay MK, et al. The safety and efficacy of endoscopic incision of orthotopic ureterocele in adult. Saudi Journal of Kidney Diseases and Transplantation. 2011;22(6):1169–1174. https://pubmed.ncbi.nlm.nih.gov/22089776/
  8. A Large Stone Within a Ureteroceles: A Diagnostic Pitfall and the Utility of Holmium Laser Deroofing as a Viable Surgical Option. https://pubmed.ncbi.nlm.nih.gov/29468199/
  9. British Association of Urological Surgeons. Information about your ureteric stent. https://www.baus.org.uk/_userfiles/pages/files/Patients/Leaflets/Stent%20advice.pdf

A kidney tumour larger than 3 cm: what does it mean?

By Dr Jo Schoeman | Patient information | September 2026

Finding a kidney mass can be frightening. The first question is whether it is cancer; the next is whether it is confined to the kidney. A mass measuring 3.1 cm is not automatically advanced cancer. If a renal cell carcinoma (RCC) is no more than 4 cm and remains within the kidney, it is classified as T1a. A tumour over 4 cm but no more than 7 cm, still confined to the kidney, is T1b. Lymph-node and distant spread are assessed separately. Some kidney masses are benign, and imaging alone cannot always tell us which. [1–3]

How might it present?

Many tumours are discovered by chance during an ultrasound or CT scan for another problem. Others cause blood in the urine, persistent pain in the side or back, or occasionally a palpable lump. Unexplained weight loss, fatigue, anaemia or fever warrant assessment, although they have many possible causes. The combination of blood in the urine, pain and a palpable mass is uncommon. Visible blood in the urine should always be investigated; a kidney mass does not rule out another source of bleeding. [2]

What investigations are needed?

  • Dedicated imaging: A multiphase contrast CT of the kidneys and abdomen shows whether the lesion enhances, its exact position, its relationship to major blood vessels and the collecting system, and whether there are enlarged nodes or signs of spread. Chest imaging completes staging; its extent is tailored to the tumour and clinical circumstances. MRI may clarify an uncertain lesion or suspected tumour extension into a vein, or be useful when CT contrast is unsuitable. A complex kidney cyst needs its own imaging assessment. [2]
  • Blood and urine tests: Kidney function (creatinine and eGFR), a full blood count and other tests guided by the clinical picture help assess fitness for treatment and preserve kidney function. Urine testing may identify infection or another cause of bleeding. [2]
  • Biopsy: A needle biopsy can be useful if its result will change management, particularly before ablation or drug treatment without prior tissue diagnosis. A typical surgically removable solid mass does not always need a biopsy beforehand. A biopsy can occasionally be inconclusive. [2]
  • Further staging: Bone or brain scans are generally reserved for relevant symptoms or suspected advanced disease. Routine PET scans and bone scans are not recommended for initial RCC staging. [2]

The team should review the images, kidney function, other medical conditions and the patient’s priorities together. An indeterminate mass should not be labelled definitively as RCC before appropriate assessment.

A note about my practice: I no longer perform nephrectomies. I can assess your kidney mass, discuss the findings and treatment options with you, and, if an operation is appropriate, refer you to a colleague who performs kidney surgery. We can also arrange input from a multidisciplinary team where needed.

Treatment when the tumour is confined to the kidney

Partial nephrectomy removes the tumour while preserving the rest of the kidney. This is generally preferred for T1 cancers when technically feasible, particularly if kidney function is reduced or there is only one functioning kidney. It can be performed by robotic, laparoscopic or open surgery according to tumour complexity and surgical expertise. Risks include bleeding, urine leak, infection, reduced kidney function and, occasionally, the need to remove the whole kidney. [1]

Radical nephrectomy removes the kidney and may be appropriate when a safe partial nephrectomy is not feasible, particularly with a larger or more complex tumour. Robotic or laparoscopic surgery offers an approach to the operation; it does not change the underlying choice between partial and radical removal. [1]

Active surveillance may suit selected people with a small, slow-growing mass, competing health risks or a strong preference to defer treatment. It involves planned scans and a clear trigger to reconsider treatment. A tumour just above 3 cm needs a particularly careful discussion because the room for further growth before 4 cm is limited. Thermal ablation, such as cryoablation or radiofrequency or microwave ablation, may suit selected small tumours, especially when surgery is unsuitable; a biopsy is recommended before ablation. Local recurrence and the possible need for repeat treatment should be discussed. [1, 2]

Stereotactic ablative radiotherapy (SABR) is also being used in specialist centres for selected patients with localised RCC who cannot undergo surgery. It is a distinct option from routine radiation after an operation, and its long-term comparative evidence continues to mature. [1]

What if lymph nodes look enlarged?

An enlarged node on a scan is suspicious, not proof of cancer; inflammation can also enlarge nodes. The team considers the appearance and site of the nodes, whether there is disease elsewhere and whether tissue confirmation will change treatment. If nephrectomy is planned, visibly enlarged regional nodes may be removed for diagnosis and staging. Removing normal-looking nodes routinely has not been shown to improve survival for organ-confined RCC. The survival benefit of removing involved nodes is uncertain. [1]

Confirmed regional node involvement is a substantial change in risk even if the kidney tumour is small. It calls for multidisciplinary discussion about whether all visible disease can be removed, whether postoperative drug treatment is appropriate, and how closely to monitor. Nodes beyond the regional area, or spread to organs such as the lung or bone, may represent metastatic disease and require a different plan. Surgery on the kidney is not automatically the best first step when cancer is widespread. [1, 3]

When does immunotherapy help?

For selected patients with clear-cell RCC at higher risk of recurrence after complete surgery, a course of pembrolizumab may lower recurrence risk and has shown an overall survival benefit in the KEYNOTE-564 study. The eligible groups include some patients with confirmed regional node involvement and no distant metastases. A 3–4 cm node-negative tumour confined to the kidney would not usually qualify based on size alone. The final pathology, stage and overall health matter. [1, 4]

If cancer has spread and cannot all be removed, initial treatment for clear-cell RCC often combines immune checkpoint drugs with each other (nivolumab plus ipilimumab) or combines immunotherapy with an oral targeted drug (for example, pembrolizumab plus axitinib, pembrolizumab plus lenvatinib, or nivolumab plus cabozantinib). The best regimen depends on risk group, other illnesses, kidney function, previous treatment and the specific cancer subtype. Papillary and other non-clear-cell cancers may need different approaches. Availability and subsidy in Australia should be checked for the individual indication. [1]

Immunotherapy can cause serious inflammation of the bowel, lungs, liver, kidneys or hormone-producing glands; targeted drugs can cause high blood pressure, diarrhoea, fatigue and other adverse effects. Some immune effects can persist after treatment ends. Benefits and risks need an individual discussion with a medical oncologist. [1, 4]

Is chemotherapy useful?

Conventional cytotoxic chemotherapy is generally ineffective for the common types of RCC and is not standard treatment for ordinary clear-cell RCC. Rare subtypes, including collecting duct and renal medullary carcinoma, are exceptions in which chemotherapy may have a role. A cancer arising from the lining of the renal pelvis (upper-tract urothelial carcinoma) is a different disease with different chemotherapy options; establishing the diagnosis matters. [1]

Does radiation offer a benefit?

Radiotherapy is not routinely given after nephrectomy to prevent recurrence of localised RCC. Its clearest established role is treating specific problems from spread, such as painful bone lesions, brain metastases or symptoms from another site. Precisely targeted radiation may also control selected limited metastases or treat a primary tumour in someone unsuitable for surgery. Whether it adds benefit to systemic therapy or surgery in an individual case depends on the site, number and behaviour of lesions and is best decided with radiation oncology input. It should not be presented as a standard substitute for an operable partial nephrectomy. [1, 5]

Questions worth asking at your consultation

  1. Is this definitely a solid enhancing kidney tumour, and what is its exact size and location?
  2. Is the disease confined to the kidney? Are any nodes merely enlarged, or proven to contain cancer?
  3. Can we safely preserve part of the kidney? What is my current kidney function?
  4. Would a biopsy change the plan?
  5. If the cancer is clear-cell and higher risk, would adjuvant pembrolizumab be suitable?
  6. Would drug treatment or targeted radiation offer a benefit in my particular situation?

Seek prompt medical attention for heavy bleeding with clots, inability to pass urine, severe persistent pain, or sudden neurological symptoms. This article is general information and cannot replace review of your scans and pathology at a multidisciplinary meeting.

References

  1. European Association of Urology. EAU Guidelines on Renal Cell Carcinoma: Disease Management. 2026.
  2. European Association of Urology. EAU Guidelines on Renal Cell Carcinoma: Diagnostic Evaluation. 2026.
  3. European Association of Urology. EAU Guidelines on Renal Cell Carcinoma: Staging and Classification Systems. 2026.
  4. National Cancer Institute. Adjuvant Keytruda improves kidney cancer survival, reporting updated KEYNOTE-564 outcomes. 2024.
  5. National Cancer Institute. Renal Cell Cancer Treatment (PDQ), Health Professional Version. Accessed September 2026.

Coffee Break

Coffee, oat milk and the start of my day at the Wesley

By Dr Jo Schoeman

Before a busy day of consultations or operating at the Wesley, I enjoy a small ritual: stopping for a coffee with oat milk at Steamtrain Espresso Bar and Kitchen, beside Auchenflower train station and just outside the hospital. It gives me a moment to gather my thoughts before the day begins. I also simply enjoy a good coffee.

 “A quiet coffee before the working day.” 

What is good about coffee?

For many of us, caffeine helps us feel more alert and focused in the morning. Coffee also contains a range of naturally occurring plant compounds. Large reviews have found that people who drink moderate amounts of coffee tend to have lower rates of several health problems than people who do not drink it. These are mostly associations: they do not prove that coffee itself prevents disease, and they are no reason to start drinking it if you do not enjoy it.[1]

The amount that suits one person may be too much for another. Coffee can disturb sleep or cause jitters and palpitations, especially in people who are sensitive to caffeine. I prefer mine early in the day, when I can enjoy the lift without letting it interfere with the night ahead.

Why oat milk?

I like its taste and the creamy texture it brings to coffee. It is a practical dairy-free option for people who avoid cow’s milk. If oat milk is a regular replacement for dairy, however, it pays to check the carton: products vary, and oat milk usually provides less protein than cow’s milk. Choosing an unsweetened product fortified with calcium can help, while vitamin B12 and iodine are also worth considering in the context of your overall diet.[2,3] A splash in a coffee is a pleasure, rather than a nutritional strategy in itself.

A urologist’s small caveat

I cannot write about coffee without mentioning the bladder. Caffeine can make urinary urgency, frequency or night-time trips to the toilet worse for some people. If that sounds familiar, try a smaller coffee, have it earlier, or see whether decaf makes a difference. Keep drinking an appropriate amount of water; cutting fluids too far can make bladder symptoms worse. Persistent symptoms deserve an assessment rather than being blamed on your morning coffee alone.[4]

For me, that oat milk coffee at Steamtrain marks the start of the working day. It is a pleasant pause, a familiar stop by the station, and a chance to arrive at the Wesley ready to see my patients. Like most good habits, it works best with a little balance.

References and further reading

  1. Poole R, et al. Coffee consumption and health: umbrella review of meta-analyses of multiple health outcomes. BMJ. 2017;359. https://www.bmj.com/content/359/bmj.j5024
  2. Dietitians Australia. Plant-based milks. https://dietitiansaustralia.org.au/health-advice/plant-based-milks
  3. Food Standards Australia New Zealand. Plant-based milk alternatives. https://www.foodstandards.gov.au/consumer/nutrition/milkaltern
  4. Continence Health Australia. Caring for your bladder at night (nocturia). https://www.continence.org.au/about-incontinence/urinary-incontinence/nocturia/caring-for-your-bladder-at-night-nocturia/

This article offers general information and reflects my personal routine. Individual nutrition and bladder needs vary.

How a Stroke Can Affect Bladder Function

A cerebrovascular accident (CVA), more commonly called a stroke, can affect much more than movement and speech. It can also disrupt the communication between the brain and bladder, leading to urgency, urinary leakage, difficulty emptying the bladder or a combination of these problems.

Bladder difficulties are common after stroke, particularly during the early stages of recovery. They can cause embarrassment, interfere with rehabilitation, disturb sleep and increase the risks of falls, skin problems and urinary tract infection. Fortunately, many patients improve as the brain recovers, and persistent symptoms can usually be managed with an individualised bladder rehabilitation and treatment plan.

How does the brain normally control the bladder?

The bladder stores urine at a low pressure until it is convenient to empty. This depends on coordinated communication between:

  • The frontal lobes, which help recognise bladder filling and suppress urination until an appropriate time.
  • Deeper brain centres involved in bladder sensation and behavioural control.
  • The pontine micturition centre in the brainstem, which coordinates contraction of the bladder with relaxation of the urinary sphincter.
  • The spinal cord and peripheral nerves that carry messages between the brain, bladder and sphincter.

A stroke may interrupt one or more of these pathways. The resulting bladder problem depends on the location and extent of the stroke, the patient’s previous bladder function and the presence of other conditions such as prostate enlargement, diabetes, constipation or reduced mobility.

What bladder problems can occur after a stroke?

Urgency and urge urinary incontinence

The most common problem is a sudden, compelling need to pass urine that may be difficult to postpone. Some patients leak before reaching the toilet.

This often results from detrusor overactivity, in which the bladder muscle contracts involuntarily during filling because the brain is no longer suppressing it normally.

Associated symptoms can include:

  • Passing urine frequently.
  • Waking several times at night to urinate.
  • Sudden urgency.
  • Leakage associated with urgency.
  • Bedwetting.
  • Reduced warning before urination.

Difficulty emptying the bladder

Some patients develop a weak or poorly coordinated bladder contraction and cannot empty effectively. This may cause:

  • Difficulty starting urination.
  • A slow or interrupted urinary stream.
  • Straining to pass urine.
  • A sensation of incomplete emptying.
  • Frequent passage of small amounts.
  • Overflow leakage from an overfilled bladder.
  • Recurrent urinary infections.

Urinary retention may be more likely during the acute phase of stroke because of reduced consciousness, immobility, constipation, medication effects, pain, infection or a pre-existing obstruction such as an enlarged prostate.

Functional incontinence

Not every episode of leakage is caused by abnormal bladder contractions. A patient may recognise the need to urinate but be unable to reach or use the toilet because of:

  • Weakness or paralysis.
  • Poor balance or slow mobility.
  • Visual impairment.
  • Difficulty removing clothing.
  • Communication problems.
  • Confusion, memory loss or reduced awareness.
  • An inaccessible toilet or lack of timely assistance.

This is called functional incontinence. Treating the bladder alone will not solve it; the physical and environmental barriers must also be addressed.

Loss of bladder awareness

A stroke can reduce awareness of bladder filling. The patient may not recognise the need to urinate until leakage occurs—or may remain unaware that the bladder is full.

Stress urinary incontinence

Leakage with coughing, sneezing, standing or exertion is not usually caused directly by stroke, but pre-existing pelvic-floor weakness may become more noticeable when mobility and general muscle function decline.

Nocturia and nighttime incontinence

Nighttime urination may be caused by an overactive bladder, sleep disturbance, leg swelling, obstructive sleep apnoea, medication timing or increased nighttime urine production. It is important because repeated attempts to reach the bathroom can significantly increase the risk of falls.

Does the site of the stroke predict the bladder problem?

There are broad associations between the area of brain injury and the type of bladder dysfunction, but the relationship is not exact enough to base treatment on the brain scan alone.

Frontal and subcortical strokes are frequently associated with urgency and detrusor overactivity. Brainstem strokes can interfere with coordination between the bladder and urinary sphincter, while larger strokes may impair bladder sensation, mobility and awareness.

The bladder pattern can also change during recovery. This is why treatment should be based on the patient’s current symptoms and objective bladder assessment rather than the location of the stroke alone.

How is bladder dysfunction assessed?

Assessment should consider the bladder, the patient’s neurological recovery and the practical circumstances surrounding each episode of leakage.

Medical and medication history

Important questions include:

  • Was urgency, nocturia or poor urinary flow present before the stroke?
  • When did the symptoms begin?
  • Is the patient aware of bladder filling?
  • Can the patient reach and use the toilet independently?
  • Is there constipation, pain, visible blood in the urine or fever?
  • What fluids, caffeine and alcohol are being consumed?
  • Could medication be contributing?

Diuretics, sedatives, opioids and some medications with anticholinergic effects can aggravate urinary symptoms, confusion or retention.

Bladder diary

A bladder diary records fluid intake, the time and volume of each urination, urgency and leakage episodes. It can help distinguish reduced bladder capacity from excessive urine production or predominantly functional incontinence.

Physical examination

The assessment may include examination of the abdomen, genital area, prostate where appropriate, pelvic floor, mobility, cognition, sensation and neurological function.

Urine testing

Urinalysis and urine culture when clinically indicated, can identify infection or blood in the urine. Bacteria in the urine without urinary symptoms do not automatically require antibiotics.

Bladder scan and post-void residual

A painless ultrasound bladder scan measures the urine remaining after urination. This is particularly useful when there is a weak stream, retention, recurrent infection, overflow leakage or before treatments that could make emptying more difficult.

Additional investigations

Depending on the circumstances, evaluation may include:

  • Kidney function blood tests.
  • Urinary flow testing.
  • Ultrasound of the kidneys and bladder.
  • Cystoscopy when there is haematuria, suspected obstruction or another appropriate indication.
  • Urodynamic studies.

Are urodynamic studies always necessary?

No. Many patients with straightforward urgency or functional incontinence can begin conservative treatment after clinical assessment, urine testing and measurement of the post-void residual.

Urodynamic studies may be helpful when:

  • The symptoms and clinical findings do not agree.
  • Both urgency and poor emptying are present.
  • There is persistent or unexplained urinary retention.
  • Initial treatment has failed.
  • An invasive treatment such as bladder Botox is being considered.
  • There is concern about obstruction, weak bladder contraction or poor bladder compliance.
  • Previous prostate, bladder or continence surgery complicates the diagnosis.

Urodynamics can distinguish an overactive bladder from impaired bladder contractility, obstruction or sphincter discoordination. This helps avoid giving treatment that reduces bladder contractions to someone who already empties poorly.

Treatment options

Treatment should be based on the bladder abnormality, the patient’s functional ability and their personal goals. Family members, continence nurses, physiotherapists, occupational therapists, rehabilitation physicians and urologists may all contribute.

Treat reversible factors

The first step is to identify problems that may be aggravating bladder control, including:

  • Urinary infection.
  • Constipation or faecal impaction.
  • Excessive caffeine or alcohol.
  • Excessive or poorly timed fluid intake.
  • Uncontrolled diabetes.
  • Leg swelling and nighttime fluid redistribution.
  • Medication side effects.
  • Prostate obstruction.
  • Reduced access to the toilet.

Adequate hydration remains important. Simply restricting fluid can produce concentrated urine, constipation and bladder irritation.

Prompted or timed toileting

Scheduled toileting can be very effective, particularly when memory, mobility or awareness is impaired.

Options include:

  • Timed voiding: visiting the toilet at regular planned intervals.
  • Prompted voiding: a carer reminds and assists the patient to use the toilet.
  • Habit retraining: the schedule is matched to the patient’s usual bladder pattern.
  • Bladder training: gradually increasing the interval between toilet visits when the patient can recognise and suppress urgency.

Easy-to-remove clothing, a bedside commode, urinal, improved lighting and a clear path to the toilet can make a considerable difference.

Pelvic-floor rehabilitation

Pelvic-floor muscle training may improve urinary control in appropriately selected patients who can identify and contract these muscles. A continence or pelvic-floor physiotherapist can adapt the program for weakness, impaired coordination or cognitive limitations following stroke.

Medication for urgency and overactive bladder

Medication may be considered when conservative measures are insufficient.

Antimuscarinic medication

Medicines such as solifenacin, darifenacin, oxybutynin or trospium can reduce involuntary bladder contractions. Possible adverse effects include:

  • Dry mouth.
  • Constipation.
  • Blurred vision.
  • Difficulty emptying the bladder.
  • Confusion or cognitive deterioration.

These medicines should be selected cautiously after stroke, particularly in older patients, those with cognitive impairment, constipation, glaucoma or an elevated post-void residual. The total anticholinergic burden from all medications should be reviewed.

Beta-3 agonists

Mirabegron relaxes the bladder during filling and may have fewer dry-mouth and cognitive adverse effects than antimuscarinic treatment. Blood pressure should be checked because mirabegron may worsen hypertension. Residual urine should also be monitored when there is concern about poor emptying.

Vibegron is another beta-3 agonist, although availability and funding can vary.

Management of incomplete emptying or retention

Treatment depends on the cause and severity.

Options may include:

  • Reviewing medicines that impair bladder contraction.
  • Treating constipation and infection.
  • Managing prostate or urethral obstruction when present.
  • Double voiding.
  • Intermittent catheterisation.

Clean intermittent catheterisation is generally preferred when the bladder cannot empty safely and the patient or carer can perform it. An indwelling urethral catheter may sometimes be necessary during the acute phase, but prolonged unnecessary use should be avoided because of infection, urethral trauma and bladder-stone risks.

A suprapubic catheter may be considered when long-term catheter drainage is unavoidable and urethral catheterisation is unsuitable.

Botulinum toxin injections into the bladder

Botulinum toxin A, commonly called bladder Botox, can reduce severe detrusor overactivity when medication has been ineffective or poorly tolerated.

It may significantly improve urgency and leakage, but it can also weaken bladder emptying. The patient must understand that intermittent catheterisation may be required, sometimes for several months. Careful selection, measurement of residual urine and appropriate follow-up are essential.

Neuromodulation

Posterior tibial nerve stimulation may help some patients with urgency and overactive bladder symptoms. It is minimally invasive but usually requires repeated treatment sessions.

Sacral neuromodulation can be effective in selected people with refractory urinary urgency, urge incontinence or non-obstructive retention. Evidence specifically in post-stroke patients is more limited than in the general overactive-bladder population. The patient’s neurological stability, cognition, mobility, ability to operate the device and need for future MRI examinations should be considered.

Continence products and skin care

Pads, absorbent underwear, mattress protection and external collecting devices can preserve dignity while recovery and treatment continue. They should support, not replace, proper assessment and rehabilitation.

Regular skin care is important, particularly when mobility is limited. Condom drainage systems may help selected men, but correct fitting and skin monitoring are essential.

Can bladder control improve after a stroke?

Yes. Many patients experience substantial improvement during the first weeks and months as consciousness, mobility, communication and neurological control recover.

Persistent urinary incontinence, however, can be a marker of a more severe stroke and may be associated with greater disability. It should not be dismissed as an inevitable consequence of ageing or brain injury. Early assessment and an active continence program can improve independence, participation in rehabilitation and quality of life.

When should medical help be sought urgently?

Prompt medical assessment is required for:

  • Complete inability to pass urine.
  • A painful or visibly swollen lower abdomen.
  • Fever, chills, confusion or suspected urinary infection.
  • Visible blood in the urine.
  • New flank pain.
  • Recurrent infections.
  • Increasing residual urine.
  • New leg weakness, numbness or loss of bowel control.
  • Sudden new neurological symptoms, which may represent another stroke.

In Australia, sudden facial weakness, arm weakness or speech disturbance should be treated as an emergency—call 000 immediately.

The key message

Bladder problems following a stroke are common, but they are not all the same. Leakage may result from an overactive bladder, impaired awareness, poor mobility, urinary retention, obstruction or several factors acting together.

Successful management begins by determining why the problem is occurring. A combination of bladder rehabilitation, environmental assistance, pelvic-floor therapy, carefully selected medication, catheterisation or specialist intervention can then be tailored to the individual patient.

References

  1. Agapiou E, et al. Lower urinary tract dysfunction following stroke. Bladder. 2024. PubMed Central
  2. Agapiou E, et al. Bladder dysfunction following stroke: an updated review on diagnosis and management. Bladder. 2024. PubMed Central
  3. European Association of Urology. EAU Guidelines on Neuro-Urology. 2026. EAU Neuro-Urology Guideline
  4. Stroke Foundation Australia. Incontinence after stroke. Stroke Foundation patient fact sheet
  5. Stroke Foundation Australia. Urinary continence and stroke—resources for health professionals. InformMe
  6. Canadian Stroke Best Practices. Bladder and Bowel Function Following Stroke. Heart & Stroke Foundation of Canada
  7. National Institute for Health and Care Excellence. Stroke rehabilitation in adults (NG236). Updated 2023. NICE recommendations
  8. National Institute for Health and Care Excellence. Urinary incontinence in neurological disease: assessment and management (CG148). NICE guideline
  9. American Urological Association and Society of Urodynamics, Female Pelvic Medicine & Urogenital Reconstruction. Adult Neurogenic Lower Urinary Tract Dysfunction Guideline. AUA/SUFU guideline
  10. Intercollegiate Stroke Working Party. National Clinical Guideline for Stroke: Rehabilitation and recovery—activity and participation. National Clinical Guideline for Stroke

This article provides general educational information and does not replace individual medical assessment. Treatment should be tailored to the type of bladder dysfunction, other medical conditions, current medications and the patient’s rehabilitation goals.