
Tag Archive for: urologist brisbane

Movember and the digital rectal examination: does it still matter?

The digital rectal examination (DRE) has been part of prostate assessment for generations. It is also one of the tests men are most likely to dread, joke about, or avoid. As Movember prompts conversations about prostate health, it is worth asking what a DRE can actually tell us today and when it is useful.

The short answer: a DRE still has a place in clinical assessment, but it is not recommended as a routine add-on to PSA testing for every asymptomatic man. PSA blood testing is the main early-detection test. A DRE can add physical information in selected situations, and it remains one part of monitoring some men with known prostate cancer.

What is a DRE?

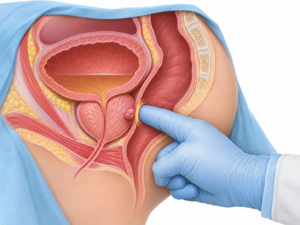
A DRE is a brief examination in which a clinician gently inserts a gloved, lubricated finger into the rectum to feel the back surface of the prostate. The clinician assesses features such as the prostate’s size, shape, firmness, symmetry and any distinct lump or irregular area. It may also give information about tenderness or other rectal findings.

The prostate sits in front of the rectum, so the examination can only feel part of the gland. It cannot reliably assess the whole prostate, and some cancers, particularly those in areas that cannot be reached by touch, may not be felt. A normal DRE therefore does not rule out prostate cancer.
What extra information can it provide?

PSA is a blood marker produced by prostate tissue. It helps estimate risk, but PSA alone does not show where a possible cancer is or how the prostate feels. A DRE gives the clinician a physical finding to interpret alongside the PSA result, symptoms, family history and, when indicated, MRI and biopsy.

A firm nodule, marked asymmetry, or an unusually hard or fixed-feeling area can increase concern and prompt further assessment, even if the PSA is not markedly raised. An abnormal DRE may also help estimate the clinical extent of a cancer and its likelihood of being more significant. But it is not a cancer diagnosis: benign enlargement, inflammation and examiner variation can affect what is felt. A suspicious finding usually needs further assessment, often including MRI and possibly biopsy.

DRE is not a substitute for PSA, MRI or biopsy. Nor does a normal examination provide a guarantee that cancer is absent.

Can it find cancers that produce little PSA?

Occasionally, prostate cancer is found after a suspicious DRE even when PSA is low. Some uncommon or poorly differentiated cancers can produce less PSA than expected. In the 2026 European Association of Urology guideline, a suspicious DRE with PSA at or below 4 ng/mL was associated with a positive predictive value ranging widely from 5% to 30% in the cited evidence. This shows why a distinctly abnormal examination should not automatically be dismissed because of a reassuring PSA.

That does not mean DRE is a dependable way to screen for low-PSA cancers. Many cancers cannot be felt, and DRE’s performance as a stand-alone screening test is limited. If symptoms, imaging or other clinical features raise concern, the clinician should consider the full picture rather than rely on either a normal PSA or a normal DRE alone.

Should every man having a PSA test also have a DRE?

No. The NHMRC-approved 2026 Guidelines for the Early Detection of Prostate Cancer in Australia suggest that DRE not be offered in primary care as a routine addition to PSA testing and risk assessment for asymptomatic men. The RACGP Red Book also advises against routine DRE as an addition to PSA testing in asymptomatic men seeking early detection.

This reflects evidence that routine DRE adds little to population early-detection pathways compared with PSA-based assessment, while it can create discomfort and deter some men from discussing testing. PSA testing itself is a choice to make after discussing potential benefits and harms with a GP; it is not an automatic test for everyone.

A DRE may still be appropriate when a person has symptoms, a concerning PSA result, an abnormality on imaging, or another clinical reason for a physical examination. A clinician should explain why it may help in that specific situation and discuss alternatives where appropriate.

What about men already on active surveillance?

Active surveillance is a monitoring approach for selected men with lower-risk prostate cancer, intended to identify evidence of meaningful change while avoiding or delaying treatment side effects when it is safe to do so.

The 2026 Australian guideline proposes periodic DRE alongside PSA measurements, MRI where appropriate and repeat biopsy when clinically indicated. A change in the examination may be one reason to bring forward MRI or biopsy. It is not, by itself, usually enough to decide that treatment should start. The European Association of Urology also includes DRE in surveillance protocols, while recognising that its frequency may be reduced in selected men with stable MRI and other reassuring findings. Monitoring plans vary with the cancer’s features, prior tests and the person’s circumstances.

Why is the DRE so famous, and why are some men apprehensive?

For many years, before PSA testing and prostate MRI were available, clinicians had fewer ways to assess the prostate. The DRE was a quick bedside examination that could identify a large or locally advanced abnormality. It became closely associated with “getting your prostate checked,” and popular culture has kept it in the spotlight.

When I discuss it with patients, I sometimes call DRE the “dreaded rectal examination” a little wordplay that can break the ice. It acknowledges the test’s reputation, but it is not a request to grin and bear it: I explain what I’m doing, ask permission, and stop if you ask.

The examination can feel intimate or embarrassing. Some men worry it will hurt, feel exposed, or be judged. Others have heard jokes that link the test to masculinity or sexuality. These concerns are understandable, but a DRE is a clinical examination; it says nothing about a person’s identity or sexuality. Many people find it awkward or uncomfortable rather than painful, although experiences differ.

You can ask the clinician to explain each step before starting, request a chaperone, discuss positioning, and ask them to stop at any time. Consent matters. You do not need to agree to an examination simply because you have come to talk about PSA testing.

What should I do this Movember?

If you are thinking about prostate testing, speak with your GP about your age, family history, health and preferences. Ask whether PSA testing is suitable for you and whether an examination would add useful information in your circumstances. If you have urinary symptoms, blood in your urine or semen, persistent unexplained pain, or another concern, arrange an assessment rather than waiting for a routine screening test.

Movember is a chance to make the conversation easier. The aim is not to insist that every man must have a DRE. It is to help each person understand the available tests, feel able to ask questions, and make an informed decision with their clinician.

This article provides general information and is not a substitute for personal medical advice.

References and further information

  1. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia. NHMRC-approved recommendations, 18 May 2026. See Recommendations 4.1 and 8.2.1.
  2. The Royal Australian College of General Practitioners. Guidelines for preventive activities in general practice, 10th edition — prostate cancer. Recommendations updated 28 June 2024.
  3. European Association of Urology. EAU Guidelines on Prostate Cancer: Diagnostic Evaluation, 2026 edition.
  4. European Association of Urology. EAU Guidelines on Prostate Cancer: Treatment and active-surveillance follow-up, 2026 edition.
  5. Sajjad W, et al. Comparing the Performance of Digital Rectal Examination and Prostate-specific Antigen as a Screening Test for Prostate Cancer: A Systematic Review and Meta-analysis. European Urology Oncology. 2024. PubMed.
Know your testes: testicular cancer, self-awareness and Movember

Movember is a good time to talk openly about men’s health. Testicular cancer is uncommon overall, but it matters because it often affects teenagers and younger adults, and a new lump can be easy to dismiss or feel awkward to discuss. Knowing what is usual for your body can help you notice a change and seek advice.

How common is testicular cancer in Australia?

Cancer Australia estimates that 1,040 people will be diagnosed with testicular cancer in Australia in 2025. The estimated lifetime risk for males is about 1 in 188 by age 85. The rate is highest in men aged 30–34, although it can occur at other ages. Testicular cancer is one of the more common cancers in younger men. [1,2]

The outlook is generally very good. For Australians diagnosed from 2017 to 2021, five-year relative survival was 98%. This is a population estimate: an individual’s outlook depends on the cancer type, stage, tumour markers, health and response to treatment. Many testicular cancers, including some that have spread, can be cured with modern treatment. [1,2]

What does “regular self-examination” mean?

There is no national screening program or recommended screening interval for testicular cancer. Research has not shown that scheduled self-examination of people without symptoms reduces deaths, and a Cochrane review found no randomised trials that tested whether screening by self-examination or a clinician prevents testicular-cancer deaths. Cancer Council Australia therefore does not recommend population screening. [3,4]

That is different from being familiar with your own body. Movember’s “Know Thy Nuts” campaign encourages men to learn what feels normal and to get changes checked. A practical approach is to check in with yourself from time to time, such as in the shower, without treating it as a test that can rule cancer in or out. If you have a higher-risk history, discuss an individual plan with your GP or urologist. [3,5]

A simple way to get familiar with what is normal

  1. Warm water can relax the scrotal skin, making it easier to feel the testicles.
  2. Examine one testicle at a time. Gently roll it between your thumb and fingers; do not squeeze hard.
  3. Notice its usual size, shape and feel. It is common for one testicle to hang lower or be slightly larger than the other.
  4. The epididymis, a soft, slightly ridged tube along the back of each testicle, is normal anatomy. It can be mistaken for a lump when you are not familiar with it.
  5. Pay attention to a new firm lump on the testicle, a change in size or shape, new swelling, a feeling of heaviness, or a persistent ache.

There is no need to follow a rigid monthly schedule. The useful point is to know what is usual for you and to arrange a medical review if something changes. Self-checking cannot diagnose cancer, and a normal-feeling testicle does not replace assessment of symptoms.

When should you see a doctor?

Arrange a prompt appointment with your GP if you find a new lump or notice persistent swelling, a change in size or shape, heaviness, or an ache in the testicle, scrotum or lower abdomen. Most scrotal changes are not cancer, but they deserve assessment rather than guesswork. A sudden, severe testicular pain needs urgent emergency assessment because conditions such as testicular torsion can threaten the testicle and require rapid treatment. [2,6]

Movember notes that a GP can ask about symptoms, examine the testicles and arrange an ultrasound or blood tests when needed. It is reasonable to ask when and how you will receive results, and to follow up if you have not heard back. [5]

What types of testicular cancer are there?

Most testicular cancers start in germ cells, the cells that develop into sperm. They are grouped into two main categories: [2,7]

  • Seminoma: Often grows and spreads more slowly than non-seminoma. It is most often diagnosed in adults roughly 25–45 years old, but can occur outside this range. A rare spermatocytic type tends to occur in older men.
  • Non-seminoma: More common in younger men, often from the late teens to early 30s. The main cell types are embryonal carcinoma, yolk-sac tumour, choriocarcinoma and teratoma. A tumour may contain more than one type; mixed tumours are generally managed as non-seminoma.
  • Stromal tumours: These arise from hormone-producing or supporting cells, such as Leydig or Sertoli cells. Many are benign, but specialist assessment is needed to determine what a mass is.
  • Germ-cell neoplasia in situ (GCNIS): Abnormal germ cells that have not invaded surrounding tissue. It is a precursor condition, rather than an invasive cancer, and is usually found on tissue examination.

The type matters because seminoma and non-seminoma can behave differently and may need different follow-up or treatment.

How is a testicular mass investigated?

A doctor will ask about the change and examine the scrotum and surrounding areas. Scrotal ultrasound is the key imaging test to distinguish a solid testicular mass from other causes of swelling. Blood tests may measure alpha-fetoprotein (AFP), beta-human chorionic gonadotrophin (β-hCG) and lactate dehydrogenase (LDH). These markers help with diagnosis, staging and monitoring, but normal results do not exclude testicular cancer. If cancer is suspected, further imaging—often CT scans—is used to assess whether it has spread. [6,8]

A needle biopsy through the scrotum is generally avoided when a germ-cell cancer is suspected. Diagnosis is usually confirmed by removing the affected testicle through an incision in the groin (radical inguinal orchidectomy) and examining it under a microscope. This operation is also the first treatment for most testicular cancers. [6]

Treatment options

Treatment depends on the tumour type, stage, blood-marker results, risk of recurrence, general health and the person’s priorities. Care is planned by a multidisciplinary team, usually including a urologist, medical oncologist, radiation oncologist and cancer-care nurses. Options can include: [6,9]

  • Orchidectomy: Removal of the affected testicle. For some cancers confined to the testicle, this may be the only treatment needed.
  • Active surveillance: Regular appointments, blood tests and imaging after surgery to detect any recurrence early. This is a structured treatment option, not being left without follow-up.
  • Chemotherapy: Often cisplatin-based combinations, such as BEP, for selected cancers with a higher recurrence risk or disease that has spread.
  • Radiotherapy: Used in selected seminoma cases; its role is more limited than in the past because surveillance and chemotherapy are alternatives, and long-term effects are considered.
  • Retroperitoneal lymph-node surgery: Removal of selected lymph nodes in the abdomen in particular non-seminoma situations, often when cancer remains after chemotherapy or when surgery is preferred in carefully selected cases.

The choice after orchidectomy is not the same for everyone. For early seminoma, surveillance is commonly offered; some people may consider a single dose of carboplatin. For early non-seminoma, surveillance, one cycle of chemotherapy, or (in selected cases) lymph-node surgery may be discussed. The aim is to cure the cancer while avoiding treatment that is not necessary. [6]

Fertility, hormones and life after treatment

If there is time before chemotherapy or radiotherapy, ask about sperm banking, even if you are unsure about future plans. Cancer and its treatment can affect fertility, and it is easier to discuss preservation before treatment begins. Many men retain adequate testosterone and fertility with one healthy testicle, but this is not guaranteed; hormone levels, semen quality and sexual wellbeing can be discussed with the treatment team. A testicular prosthesis can be considered before or after surgery. Follow-up also matters because recurrence and some late effects can occur after treatment. [6,9]

A Movember reminder

Movember’s message is straightforward: get to know what is normal for you, speak up if something changes, and make an appointment rather than carrying the worry alone. Testicular cancer is highly treatable, and getting a new lump assessed is a sensible step—not a reason to assume the worst. [1,5]

This article is for general education and does not replace an individual assessment by a doctor.

References

  1. Cancer Australia. Testicular cancer in Australia: statistics. Incidence estimates, age patterns, mortality and relative survival. Accessed 4 November 2026.
  2. Cancer Council Australia. Testicular cancer: causes, symptoms and treatments. Australian overview of incidence, symptoms, types, diagnosis, treatment and screening position. Accessed 4 November 2026.
  3. Ilic D, Misso ML. Screening for testicular cancer. Cochrane Database Syst Rev. 2011;(2). doi:10.1002/14651858.CD007853.pub2.
  4. Cancer Council Australia. Early detection policy: testicular cancer. Position statement on population screening and testicular self-awareness. Accessed 4 November 2026.
  5. Movember Australia. Seeing a doctor about testicles and testicular cancer; and Know Thy Nuts. Campaign information on noticing changes and seeking medical review. Accessed 4 November 2026.
  6. European Association of Urology. EAU Guidelines on Testicular Cancer (2026), including chapters on diagnostic evaluation and disease management. Accessed 4 November 2026.
  7. Cancer Australia. Types of testicular cancer. Accessed 4 November 2026.
  8. Cancer Australia. How is testicular cancer diagnosed?. Accessed 4 November 2026.
  9. Cancer Australia. Treatment options. Accessed 4 November 2026.
  10. Baade PD, Carrière P, Fritschi L. Trends in testicular germ cell cancer incidence in Australia. Cancer Causes Control. 2008;19(10):1043–1049. doi:10.1007/s10552-008-9168-z.

Bladder neck contracture after TURP or laser prostate surgery

Why it happens, why it can recur, and how it may be treated

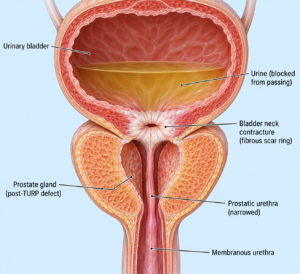
Transurethral resection of the prostate (TURP) and laser procedures such as photoselective vaporisation (PVP) or transurethral vaporisation (TUVP) are used to improve urine flow when an enlarged prostate obstructs the bladder outlet. In a small number of men, healing after surgery causes scar tissue to tighten at the bladder neck: the opening between the bladder and the prostate/urethra. This is called a bladder neck contracture (BNC) or bladder neck stenosis.

A BNC can cause a return of urinary symptoms after an initially successful operation. It is treatable, although some contractures return after treatment and a small group of men need several procedures or specialist reconstructive surgery.

This information is general and is not a substitute for assessment by your GP or urologist. The most suitable option depends on the exact site and length of narrowing, bladder function, previous procedures, continence, and general health.

How common is it?

The reported rate varies with the operation, the definition used, follow-up time, and the patients studied. A recent systematic review of randomised trials with at least two years of follow-up estimated BNC in about 3% after TURP and 9% after photo-selective laser vaporisation (PVP). The confidence intervals were wide, especially for PVP, so these figures should not be treated as a precise prediction for an individual patient. The European Association of Urology (EAU) guideline cites a broader range of approximately 0.3–9.7% for bladder neck stenosis after transurethral prostate surgery.[1,2]

“TUVP” is used for more than one vaporisation technique. Studies of older electrovaporisation, bipolar vaporisation and modern laser PVP are not interchangeable. For example, one small early study of transurethral vaporisation reported BNC in 3 of 30 patients; that result is too small and old to represent the risk from current laser surgery.[3] Your surgeon can explain which procedure was used and what the evidence for that specific technique shows.

Why can it develop?

The bladder neck can heal with excess scar tissue after surgical trauma, heat, or inflammation. The exact cause is not always clear. Factors associated with BNC in published studies include a smaller prostate or less tissue removed, infection around the time of surgery, smoking, diabetes or cardiovascular disease, longer operating time, and extensive treatment near the bladder neck. These are associations: they do not mean that a particular factor caused an individual person’s contracture.[2,4]

BNC often becomes apparent during the first months after surgery, but it can present later. Symptoms may include:

  • a weaker, slower or interrupted stream;
  • straining, hesitancy, or taking longer to pass urine;
  • a feeling that the bladder has not emptied;
  • frequent or urgent urination, or getting up at night;
  • recurrent urinary infections; or
  • inability to pass urine, which needs urgent medical attention.

These symptoms can also be caused by prostate regrowth, urethral narrowing, infection, an underactive bladder, or other bladder conditions. Testing is needed to identify the cause.

How is it assessed?

Assessment commonly includes a history, examination, urine testing, measurement of urine flow (uroflowmetry) and the amount left in the bladder after voiding (post-void residual). Cystoscopy, a small camera passed through the urethra, usually confirms whether the bladder neck is narrowed and whether a scope can pass. Depending on the situation, imaging such as a retrograde urethrogram or a bladder/urethral contrast study may help map the narrowing. Kidney and bladder imaging or kidney blood tests may be appropriate if there is significant retention, infection, or concern about the upper urinary tract.

Treatment options

Treatment is tailored to the narrowing and the person’s symptoms and priorities. A short, non-obliterated contracture is usually approached differently from a long, dense scar or a bladder neck that has closed completely.

Dilatation

A narrow area can sometimes be gently stretched with instruments or a balloon. This is relatively straightforward and can improve flow, but the scar may tighten again. In some cases a planned programme of intermittent self-catheterisation is discussed to help keep the opening stable. It is not suitable or acceptable for everyone.

Endoscopic incision or resection

A surgeon can use a small endoscope to cut (incise) the scar, or remove some of the scar tissue, using an electrical knife or laser. This is a common first treatment for a non-obliterated BNC. A catheter is often left temporarily while the area heals.

A first treatment may be enough, but recurrence is a recognised problem. EAU evidence summaries report patency after the first endoscopic treatment of about 58% following transurethral resection and 72% following incision in the cited studies. Those results come from varied, generally small observational series and should not be taken as a guaranteed personal outcome.[5] Repeated incision or dilation may be reasonable for some men with a passable narrowing; it can relieve symptoms or stabilise the opening, but each recurrence needs reassessment. A completely obliterated bladder neck is unlikely to be cured by routine endoscopic cutting and blind attempts can be unsafe.[5]

Scar-modulating injections

Steroid or mitomycin C injections have been used with endoscopic incision in selected recurrent cases. Evidence is mixed and largely based on retrospective series. Mitomycin C is not a routine, risk-free add-on: a multicentre study reported serious complications in 7% of treated patients, including tissue injury and fistula, with some requiring major further treatment.[6] If considered, the potential benefit and uncommon but significant risks should be discussed explicitly with a reconstructive urologist.

Bladder neck reconstruction

When a contracture repeatedly returns, is long or dense, or is completely closed, a reconstructive operation may be considered. The goal is to create a wider, durable outlet while protecting the bladder, ureters and continence mechanism as much as possible. The choice depends on the site and extent of scar, previous operations or radiotherapy, bladder function, continence, and surgeon expertise.

Options include a Y–V or T-plasty, in which healthy bladder tissue is rearranged to widen the outlet, with scar tissue released or removed as needed. The EAU guideline reports patency rates of 83–100% in published series, with follow-up of 14–45 months; new incontinence was reported in up to 14%. These results are from selected patients and small observational studies, not randomised comparisons.[5]

In selected complex cases, reconstruction can be performed with a robot-assisted approach. The magnified view and instruments that articulate inside the pelvis may help the surgeon work precisely around the bladder neck. Robotic reconstruction is specialised surgery, not a guarantee against recurrence or incontinence. In a systematic review of ten small case series (119 men with different causes and techniques), pooled patency was 80%; new incontinence was reported in 17% of the subset with suitable continence data. Follow-up was relatively short and the evidence was heterogeneous, so longer-term results remain important.[7]

Buccal mucosa graft reconstruction: an emerging option

Buccal mucosa is the moist lining inside the cheek. It can be taken as a graft and used to augment a narrowed or damaged urinary passage. For a severe bladder neck defect, a graft may be placed as an onlay/inlay to create a wider channel rather than simply cutting the scar again. The graft is harvested from the mouth, so temporary cheek soreness, altered mouth sensation, or tightness are possible in addition to the risks of the urinary reconstruction.

A/Prof Devang Desai and colleagues in Toowoomba have reported a robot-assisted reconstruction for complete bladder neck obliteration after TURP using two cheek grafts, one placed anteriorly and one posteriorly, to create a “double-faced” repair. In their reported case, the patient was voiding without incontinence at seven months, with a maximum flow of 23 mL/s. This is an innovative case report and conference abstract, not yet evidence that the technique is superior to established reconstruction or that results will be the same for other patients. The authors themselves note that longer follow-up is needed.[8,9]

This approach may be discussed by a reconstructive urologist for selected men with a complex or completely obliterated bladder neck, particularly after less invasive treatments have failed. It is not needed for most BNCs, and access to the technique depends on specialist experience and individual circumstances.

Catheter drainage and other options

If the bladder cannot empty, a urethral catheter or a suprapubic catheter (placed through the lower abdominal wall) may be needed, temporarily or longer term. A suprapubic catheter can be a practical choice while planning further treatment or when reconstruction is unsuitable or not wanted. In very complex cases, especially when the bladder itself is severely damaged, other forms of urinary diversion may be considered, but this is uncommon for BNC after routine TURP or vaporisation.

Continence and the possibility of further treatment

Opening a tight bladder neck can reveal leakage that was previously masked by the obstruction, or can worsen existing urinary incontinence. This may happen after endoscopic treatment as well as reconstruction. Some men remain dry; others may need continence treatment later. Before proceeding, ask your urologist how the contracture, any previous prostate surgery or radiotherapy, and your existing continence affect the plan.

A recurrence does not mean that you have done anything wrong. Scar healing is variable. If narrowing returns, the next step should be based on updated assessment rather than automatically repeating the same procedure. A reconstructive urologist can help weigh another endoscopic treatment against reconstruction, catheter drainage, or other options.

When to seek urgent help

Seek urgent medical care if you are unable to pass urine, develop fever or shaking chills with urinary symptoms, or have severe lower abdominal pain. Acute retention can require prompt bladder drainage.

References

  1. Mac Curtain BM, et al. Bladder neck contracture post-treatment for benign prostatic hyperplasia: a systematic review and meta-analysis of randomized clinical studies. International Urology and Nephrology. 2025. https://doi.org/10.1007/s11255-025-04648-2
  2. European Association of Urology. EAU Guidelines on Urethral Strictures: Definition, epidemiology, aetiology and prevention. https://uroweb.org/guidelines/urethral-strictures/chapter/definition-epidemiology-aetiology-and-prevention
  3. Chang PL, et al. Clinical outcome at 3 months after transurethral vaporization of prostate for benign prostatic hyperplasia. PubMed. https://pubmed.ncbi.nlm.nih.gov/9255294/
  4. Gül M, et al. Bladder neck contracture following transurethral surgery of prostate: a retrospective single-center study. PubMed. https://pubmed.ncbi.nlm.nih.gov/38189837/
  5. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease management in males—posterior urethral stenosis and bladder neck stenosis. https://uroweb.org/guidelines/urethral-strictures/chapter/disease-management-in-males
  6. Redshaw JD, et al. Intralesional injection of mitomycin C at transurethral incision of bladder neck contracture may offer limited benefit: TURNS Study Group. Journal of Urology. https://pubmed.ncbi.nlm.nih.gov/25200807/
  7. Zhang TR, et al. Summarizing the evidence for robotic-assisted bladder neck reconstruction: systematic review of patency and incontinence outcomes. Asian Journal of Urology. 2024;11(3):341–347. https://doi.org/10.1016/j.ajur.2023.08.007
  8. Desai D, Munien K, Namdarian B. Robotic bladder neck reconstruction using a double-faced buccal mucosal graft: a novel approach to complete bladder neck obliteration. Urology Video Journal. 2023. https://doi.org/10.1016/j.urolvj.2023.100247
  9. Desai D, Munien K, Namdarian B. Robotic bladder neck reconstruction using a double-faced buccal mucosal graft—a novel approach to complete bladder neck obliteration. BJU International. 2025;135(Suppl 2): abstract. https://doi.org/10.1111/bju.16629

This article is for general education and does not replace an individual consultation. Treatment choices, likely outcomes and risks should be discussed with the treating urologist.

Prostate cancer, Movember and the moustache: a conversation worth having

Each November, a moustache can do more than change a face. It can open a conversation that might encourage someone to learn their risk, ask about testing or support a person affected by prostate cancer.

Movember is a good time to talk about prostate cancer, but the message matters all year. The aim is not to alarm every man or suggest that everyone needs the same test. It is to make sure people know the facts and can make an informed decision with their doctor.

Prostate cancer in Australia

Prostate cancer is common. The Australian Institute of Health and Welfare (AIHW) estimated that around 29,000 men would be diagnosed in 2025, making it the most commonly diagnosed cancer in Australian men and accounting for about 30% of cancers diagnosed in men that year. These are projected figures, not a final count. Around 1 in 5 men are expected to be diagnosed with prostate cancer during their lifetime.

The outlook is often very good: the AIHW reports a 96% five-year relative survival rate for prostate cancer diagnosed in 2017–2021. That is a population statistic, not a prediction for any one person. Prostate cancers vary: some grow slowly and may never cause harm, while others can be aggressive and need timely treatment. Early assessment can help identify cancers that are more likely to matter, while careful risk assessment helps avoid unnecessary tests and treatment.

What does Movember mean?

Movember began with a simple idea: grow a moustache, raise funds and get people talking about men’s health. It has grown into a global movement supporting men’s health, including prostate cancer, testicular cancer, mental health and physical activity.

The moustache is a friendly, visible conversation starter. Someone may ask, “Why the Mo?” and that gives you a chance to mention prostate cancer, ask a friend whether he knows his family history, or check in with someone who is going through diagnosis or treatment. A moustache cannot detect cancer, and growing one does not replace medical advice. Its value is in helping make a sometimes awkward subject easier to raise.

How is prostate cancer found?

Prostate cancer often causes no symptoms in its early stages. Urinary symptoms such as a weaker stream, needing to urinate more often or difficulty starting are common with ageing and an enlarged prostate, and do not by themselves mean cancer. Blood in the urine or semen, persistent pain, or a new urinary problem should be discussed with a doctor.

The first step in early detection is usually a conversation about personal risk and the possible benefits and downsides of testing. A prostate-specific antigen (PSA) blood test measures a protein made by the prostate. PSA can rise for reasons other than cancer, including prostate enlargement, infection or inflammation. A raised result is not a diagnosis, and a low result does not rule out every cancer.

Australia’s updated national early-detection guidelines, approved by the National Health and Medical Research Council in May 2026, recommend discussing individual risks, preferences, benefits and possible harms before starting PSA testing. For men who choose testing, the guidelines recommend offering it every two years from age 50 to 69 for those not at higher risk, and from age 45 for those at higher risk. Higher risk includes a relevant family history, a confirmed BRCA2 gene mutation or Black sub-Saharan ancestry. Men aged 70 and over should discuss whether to continue testing in light of their health and preferences. These are discussion points, not a substitute for individual medical advice.

If a PSA result is higher than expected, a doctor may repeat the test and consider other information, such as age, symptoms, family history and examination findings. A urologist may recommend a prostate MRI to help decide whether a biopsy is appropriate and, if so, where to take samples. A biopsy is currently the test that confirms a diagnosis and provides information about the cancer’s grade. Not everyone with an elevated PSA needs a biopsy, and no test is perfect. If cancer is found, the next steps depend on its grade and stage, the person’s health and their preferences; some lower-risk cancers can be monitored with active surveillance.

Make November a reason to check in

This November, consider wearing blue when you walk, jog, run or volunteer at your local parkrun. Invite a friend or family member to join you. It is a simple way to show support, start a conversation and make space for men’s health alongside the usual weekend catch-up. This is a community invitation, not a claim that parkrun is running an official Movember campaign.

If you are unsure whether PSA testing is right for you, speak with your GP. Mention your age, family history and any symptoms, and ask what a result could mean and what the next steps might be. If someone close to you has prostate cancer, listening and offering to go with them to an appointment can be a practical form of support.

Grow a Mo, wear blue, or simply start the conversation. The moustache is the prompt; informed choices and looking out for one another are the point.

This article provides general information and is not a substitute for advice from your doctor. Testing decisions should be made with a health professional who can consider your personal circumstances.

References and further information

  1. Australian Institute of Health and Welfare. Cancer data in Australia: Overview of cancer in Australia, 2025.
  2. Australian Institute of Health and Welfare. Cancer outcomes improving overall.
  3. Prostate Cancer Foundation of Australia. PSA testing and the 2026 Australian early-detection guidelines.
  4. Prostate Cancer Foundation of Australia. Diagnosis of prostate cancer.
  5. Movember. About Movember.
  6. parkrun Australia. Find a parkrun event.

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

A moustache can start a conversation. A conversation can sometimes save a life.

Every November, moustaches begin appearing on faces around Australia and across the world. Some are magnificent. Some are questionable. Some probably deserve their own urological assessment.

But behind the facial hair lies an important message.

Movember is about getting men talking about their health.

What began in Melbourne in 2003 with 30 men growing moustaches has developed into an international men’s health movement focusing particularly on prostate cancer, testicular cancer, mental health and suicide prevention. Movember reports that it has funded more than 1,320 men’s health projects around the world.

And few recent stories demonstrate the importance of men paying attention to their health better than that of King Charles III.


First, an important clarification: King Charles does NOT have prostate cancer

This point has frequently been confused in media and social-media discussions.

In January 2024, Buckingham Palace announced that King Charles was receiving treatment for an enlarged prostate.

This was benign prostatic enlargement, commonly called benign prostatic hyperplasia or BPH. It is extremely common as men get older and is not prostate cancer.

The King underwent a planned hospital procedure for his enlarged prostate.

During this episode of care, however, doctors identified a separate abnormality. Further investigations subsequently diagnosed a form of cancer.

Buckingham Palace specifically confirmed that the King’s cancer was not prostate cancer. The precise type of cancer has remained private.

That distinction matters.

But so does what happened next.


A prostate problem led to something else being discovered

The King’s story provides an interesting lesson for men’s health.

He sought medical attention for a prostate problem.

He underwent investigation and treatment.

During that process, doctors discovered another potentially important medical condition.

In February 2024 Buckingham Palace announced that the King had begun a programme of regular cancer treatments and temporarily reduced his public-facing duties.

By April 2024, following treatment and recuperation, he was able to return to public-facing duties.

The exact cancer treatment has never been publicly disclosed, and it would therefore be inappropriate to speculate whether he has received surgery, radiotherapy, chemotherapy, immunotherapy or another form of treatment.

More recently, the King has continued to speak publicly about his cancer experience. In December 2025 he announced that, following early diagnosis, treatment and adherence to medical advice, his treatment schedule could be reduced in the following year.

In June 2026 he and Queen Camilla hosted a reception marking the 125th anniversary of Cancer Research UK, of which the King has been Patron since 2024.

His message has increasingly centered on a simple theme:

Early diagnosis matters.


The other royal problem: an enlarged prostate

For a urologist, the first part of the King’s story is equally important.

An enlarged prostate is extraordinarily common.

As the prostate enlarges, it can compress the urethra and interfere with the passage of urine.

Men may notice:

  • a slower urinary stream
  • difficulty starting urination
  • stopping and starting
  • straining
  • feeling that the bladder has not emptied completely
  • getting up several times during the night
  • urgency or frequency
  • occasionally an inability to pass urine at all.

These symptoms do not automatically mean prostate cancer.

Most commonly they are associated with benign prostate enlargement.

But that does not mean they should simply be accepted as part of getting older.


“It’s probably just my prostate”

Possibly.

But that is precisely why it is worth having it checked.

Assessment of urinary symptoms may include a discussion about symptoms and medications, examination, urine testing, kidney function, PSA testing where appropriate, urinary flow measurement, ultrasound assessment of bladder emptying and occasionally further investigations.

The objective is not simply to find prostate cancer.

It is to work out why the urinary system is behaving differently.


What about prostate cancer?

This is where Movember becomes particularly relevant.

Prostate cancer remains the most commonly diagnosed cancer in Australian men. Australian Institute of Health and Welfare data indicate that prostate cancer accounted for approximately 28% of cancers diagnosed in Australian males in 2024.

AIHW’s updated projections estimate approximately 26,397 prostate cancer diagnoses in Australia during 2026, although it is important to recognise that this is a projection rather than a final observed case count.

Movember estimates that approximately one in five Australian men will be diagnosed with prostate cancer during their lifetime.

And there is another important difference between prostate cancer and benign enlargement:

Early prostate cancer frequently causes no urinary symptoms at all.

Waiting until something hurts or the urine flow deteriorates is therefore not an effective prostate cancer detection strategy.


The PSA conversation

A PSA blood test can help identify men who may require further investigation for prostate cancer.

But PSA is not simply a “cancer test”.

PSA can be elevated for several reasons, including:

  • benign prostate enlargement
  • prostatitis or inflammation
  • urinary infection
  • recent instrumentation
  • urinary retention
  • and prostate cancer.

An abnormal PSA therefore does not automatically mean cancer.

Similarly, decisions about PSA testing should consider a man’s age, family history, previous PSA results, general health and individual risk factors.

The important step is having the conversation with your GP or urologist rather than avoiding the subject altogether.


And if prostate cancer is found?

Modern prostate cancer treatment is no longer a simple choice between “operate” and “do nothing”.

Depending upon the PSA, MRI findings, biopsy grade, tumour volume, stage, age and general health of the patient, options may include:

Active surveillance for suitable low-risk disease.

Robotic-assisted radical prostatectomy for appropriate localised cancers.

Radiation therapy, sometimes combined with hormonal treatment.

Focal therapies in carefully selected patients and specialised settings.

Androgen deprivation and newer androgen-receptor targeted treatments for more advanced disease.

Chemotherapy and radioligand therapies for selected advanced cancers.

The right treatment is increasingly personalised to both the biology of the cancer and the priorities of the man sitting in front of us.


Treatment is not only about surviving cancer

This is another area in which organisations such as Movember have made an important contribution.

Men understandably want their cancer controlled.

But they also care about what happens afterwards.

Will I leak urine?

Will I still have erections?

What happens to ejaculation and orgasm?

Can I continue working?

How will treatment affect my relationship?

Will I still feel like myself?

Movember has invested not only in prostate cancer research but also in projects examining quality of life, urinary function, sexual function and outcomes following treatment. The Prostate Cancer Outcomes Registry Australia and New Zealand, for example, collects patient-reported outcomes including urinary, bowel and sexual function after prostate cancer diagnosis and treatment.

These aren’t embarrassing side issues.

They are part of treating the whole man.


So what does King Charles have to do with Movember?

Quite a lot, despite the fact that he does not have prostate cancer.

His story began with something millions of older men experience:

an enlarged prostate.

Instead of ignoring it, he sought treatment.

That interaction with the healthcare system resulted in another cancer being discovered.

And by publicly announcing his prostate treatment and subsequent cancer diagnosis, the King did something particularly useful for men’s health:

he made it easier to talk about it.

That is essentially what Movember has been trying to achieve for more than two decades.

A moustache is simply the billboard.

The conversation is the important bit.


My Movember message to men

If your urinary stream isn’t what it used to be, get it checked.

If you’re getting up repeatedly during the night, ask why.

If you’re struggling with erections, don’t be embarrassed to mention it.

If you notice a testicular lump, don’t wait.

If prostate cancer runs in your family, discuss your individual risk.

And if you’ve been putting off that conversation about PSA testing, perhaps Movember is a good time to have it.

Men are remarkably good at servicing cars, replacing batteries, checking tyre pressures and investigating strange noises coming from engines.

We are sometimes considerably less enthusiastic when the strange noise is coming from ourselves.

This Movember, grow the moustache if you wish.

But more importantly:

Have the conversation.
Know your prostate.
Know your risk.
And don’t ignore a change in your body simply because it’s embarrassing to talk about.

Your prostate may be small.

Its ability to cause trouble is disproportionately ambitious.


References and further reading

  1. The Royal Family. A Statement from Buckingham Palace. 5 February 2024. Buckingham Palace confirmed that a separate cancer was discovered during treatment for benign prostate enlargement.
  2. The Royal Family. The King returns to public-facing duties. April 2024.
  3. The Royal Family. A message from The King in support of Stand Up To Cancer. December 2025.
  4. The Royal Family. The King and Queen host a reception for Cancer Research UK. June 2026.
  5. Australian Institute of Health and Welfare. The health of men in Australia. Prostate cancer statistics and Australian cancer burden.
  6. Australian Institute of Health and Welfare. Cancer data in Australia: Prostate cancer projection method changes and updated long-term projections. Updated July 2026.
  7. Movember. Prostate Cancer: Prostate Cancer Action, Innovation & Collaboration. Australian prostate cancer statistics and research programs.
  8. Movember. Our Story. History of the Movember movement from Melbourne in 2003.
  9. Movember. Prostate Cancer Outcomes Registry Australia and New Zealand. Patient outcomes and quality-of-life research.

Medical disclaimer

This article provides general information and should not replace individual medical assessment. Urinary symptoms, an abnormal PSA or concerns about prostate cancer should be discussed with your GP or urologist.

Can You Train Your Bladder Into Bad Habits?

Bladder training and pelvic floor rehabilitation

Bladder training and pelvic floor muscle training are often recommended for urinary urgency and leakage. They address different parts of bladder control, though, and the right approach depends on the symptoms and on whether the pelvic floor muscles are weak, overactive, or both.

A pelvic floor that works well needs to be able to contract when support is needed and relax when it is time to pass urine or stool. More squeezing is not always better.

What is bladder training?

Bladder training is a structured way of gradually changing toileting habits and responding to urgency. It aims to reduce “just in case” trips, increase the time between voids when appropriate, and help a person regain confidence that an urge can settle without immediately rushing to the toilet.

It is a supported behavioural treatment. It does not mean ignoring pain, forcing yourself to hold on for a long time, or following a rigid schedule regardless of what your body is telling you.

A bladder diary for a few days can help record fluid intake, urination times and volumes, urgency, leakage and night-time waking. Together with a clinician, a person can use this information to choose a realistic starting interval. The interval can then be extended gradually, often by small steps, while using calm breathing and urge-control strategies. Adequate fluid intake, avoiding excessive caffeine, and addressing constipation may also help. Fluid restriction should not be used without advice, as too little fluid can cause dehydration and concentrated urine.

When may bladder training help?

Bladder training is commonly offered as an initial treatment for people with:

  • Overactive bladder (OAB) symptoms: urgency, with or without urgency leakage, usually accompanied by increased daytime frequency and/or waking at night to urinate, when infection or another obvious cause has not been found.
  • Urinary frequency or urgency: including frequent “just in case” voiding or difficulty delaying a trip to the toilet.
  • Mixed urinary incontinence: a combination of leakage with urgency and leakage with activities such as coughing or exercise. Bladder training can be combined with pelvic floor muscle training.
  • Urgency without leakage: urgency can still be bothersome and may respond to behavioural strategies.

The International Continence Society defines OAB as a symptom syndrome. It is not the same thing as a urodynamic finding called detrusor overactivity. Some people with OAB symptoms show involuntary bladder contractions during urodynamics; others do not. Urodynamics is not needed for every person with typical OAB symptoms. Overactive Bladder

What does “sensory overactive bladder” mean?

“Sensory urgency” or “sensory OAB” is sometimes used when a person feels an early or unusually strong need to pass urine, often at relatively small bladder volumes, but testing does not show involuntary detrusor contractions. The term is used inconsistently and is not a separate diagnosis in the current ICS symptom definition.

When infection, pain-related bladder conditions, obstruction, significant residual urine and other relevant causes have been considered, a person with urgency or increased bladder sensation may still be offered bladder training according to their symptoms and goals. A normal urodynamic study does not mean that the symptoms are imagined, and a finding of detrusor overactivity does not by itself determine which treatment is best.

Practical urge-control strategies

When an urge arrives before the planned time:

  1. Pause and stop moving if it is safe to do so. Sit or stand comfortably.
  2. Breathe slowly and allow the abdomen and pelvic floor to soften.
  3. Avoid rushing, which can increase the sense of urgency.
  4. If you can contract and fully release the pelvic floor comfortably, a few brief, gentle contractions may help suppress the urge. Then let the muscles go completely.
  5. When the urgency has eased, walk calmly to the toilet if you still need to go.

The approach should be adjusted if contractions cause pain, increase urgency, or make it harder to empty. Repeatedly delaying urination despite pain, a very full bladder, or difficulty passing urine is not the aim.

Pelvic floor muscle training for stress urinary incontinence

Stress urinary incontinence (SUI) is leakage with coughing, sneezing, laughing, lifting or exercise. It commonly occurs when the urethral closure mechanism and its support do not respond adequately to a rise in abdominal pressure.

For SUI, pelvic floor muscle training (PFMT) aims to improve the muscles’ strength, endurance, timing and coordination. Guidelines recommend a supervised programme for at least three months as an initial treatment for women with SUI or mixed incontinence. Training is also commonly used in men recovering from prostate surgery, with advice tailored to their operation and recovery. NICE

A correct contraction should feel like a gentle closing and lifting around the openings of the pelvic floor. It should not feel like pushing down, holding your breath, or tightening the buttocks and thighs instead. Each contraction needs a complete release afterwards. A pelvic health physiotherapist or clinician can check that the muscles are being used correctly and can tailor the programme to the person.

For leakage with a cough or lift, a physiotherapist may teach a brief pelvic floor contraction just before and during the effort. This is sometimes called “the knack.” It is a coordination strategy, not a substitute for a progressive strengthening programme.

PFMT can also support urgency control when a person can contract and relax the muscles correctly. It may be combined with bladder training for OAB or mixed symptoms. However, a high number of forceful contractions is not suitable for everyone.

When pelvic floor relaxation may be the priority

Some people have pelvic floor muscles that are persistently tense, tender, difficult to coordinate, or unable to relax fully during urination or bowel movements. This may be described as a high-tone, overactive or non-relaxing pelvic floor. Symptoms can include pelvic pain or pressure, difficulty starting the stream, straining, a stop-start stream, a feeling of incomplete emptying, constipation, pain with sexual activity, or urinary urgency and frequency. These symptoms have other possible causes as well, so assessment matters.

When examination suggests that the pelvic floor is overactive or does not relax appropriately, treatment may focus first on down-training and coordination, often with a pelvic health physiotherapist. This can include relaxed diaphragmatic breathing, awareness of pelvic floor release, comfortable toileting posture, avoiding straining, and addressing constipation or pain. Biofeedback may be used in selected cases. The aim is not to push or bear down forcefully, but to learn a comfortable release.

In this situation, repeatedly doing “Kegels” without assessment may aggravate pain, urgency or difficulty emptying for some people. The evidence for relaxation-based treatment is less extensive than the evidence supporting supervised strengthening for SUI, but guidelines support relaxation-focused pelvic floor therapy for selected functional emptying problems. Uroweb

Relaxation is not the opposite treatment for ordinary stress incontinence. If the main problem is leakage with exertion and the pelvic floor is weak or poorly coordinated, strengthening and timing are usually the relevant goals. If a person has both stress leakage and a tight, painful or poorly relaxing pelvic floor, a clinician or physiotherapist can sequence the treatment: first restore comfortable release and coordination where needed, then progress to strengthening without reinforcing excessive tension.

When to seek assessment

A clinician may review the symptom pattern, medications, fluid and caffeine intake, bowel habits, urine test, bladder diary, pelvic floor function and how well the bladder empties. Further tests are considered when the diagnosis is uncertain or when results could change management.

Seek medical advice rather than relying on bladder training alone if you have visible blood in the urine, painful urination or fever, new difficulty passing urine, a persistent weak stream, recurrent infections, significant pelvic pain, new neurological symptoms, or a sudden change in bladder control. These symptoms can have causes that need specific assessment.

Key points

  • Bladder training is a first-line behavioural option for urgency, frequency, OAB symptoms and many cases of mixed incontinence.
  • “Sensory OAB” is an imprecise term; urgency can be real and treatable even when urodynamics does not show detrusor overactivity.
  • Supervised pelvic floor muscle training is a first-line treatment for SUI, but correct contraction and full relaxation matter.
  • A tight or non-relaxing pelvic floor may need relaxation and coordination work before strengthening.
  • The best programme is based on an assessment, not on the assumption that every pelvic floor needs more squeezing.

This article provides general information and is not a substitute for an individual assessment or treatment advice.

References

  1. National Institute for Health and Care Excellence (NICE). Urinary incontinence and pelvic organ prolapse in women: management (NG123).
  2. NICE. Pelvic floor dysfunction: prevention and non-surgical management (NG210).
  3. European Association of Urology (EAU). Guidelines on Non-neurogenic Female LUTS: Disease Management.
  4. International Continence Society (ICS). Overactive bladder: terminology and public factsheet.
  5. American Urological Association/Society of Urodynamics, Female Pelvic Medicine & Urogenital Reconstruction. The AUA/SUFU Guideline on the Diagnosis and Treatment of Idiopathic Overactive Bladder (2024).
  6. McAuley JA, Mahoney AT, Austin MM. Clinical Practice Guidelines: Rehabilitation Interventions for Urgency Urinary Incontinence, Urinary Urgency, and/or Urinary Frequency in Adult Women. Journal of Women’s & Pelvic Health Physical Therapy. 2023;47(4):214–216. doi:10.1097/JWH.0000000000000287.

Hydronephrosis: what it means and how it is treated

Finding out that a kidney is swollen on a scan can be worrying. The word hydronephrosis sounds like a diagnosis, but it describes an appearance: urine is collecting and stretching the drainage system of one or both kidneys. It is a sign that needs to be understood in context. It does not, by itself, tell us why it has happened, whether a cancer is present, or whether an operation is needed.

Many causes are treatable, and some cases can be monitored safely. The right approach depends on the cause, the degree and duration of blockage, kidney function, symptoms, overall health and, when cancer is involved, what matters most to the person receiving care.

What are unilateral and bilateral hydronephrosis?

Each kidney drains urine through a tube called a ureter into the bladder. Unilateral hydronephrosis affects one kidney; bilateral hydronephrosis affects both. A blockage may be within the kidney or ureter, or lower down where it affects the bladder outlet. A full bladder or difficulty emptying can sometimes cause dilation on both sides.

One healthy kidney can often maintain overall kidney function when the other side is obstructed. This can mean that a person with a one-sided blockage has few symptoms and normal blood tests. With obstruction affecting both kidneys, or a person who has only one functioning kidney, kidney function can become impaired more quickly. The scan appearance alone does not show how well each kidney is working.

What can cause hydronephrosis?

Causes may be benign (non-cancerous) or malignant (related to cancer). They include:

  • Kidney or ureteric stones, which may block urine flow and cause pain, blood in the urine or infection.
  • Narrowing or scarring of the ureter (a stricture), sometimes following previous surgery, instrumentation, infection or radiation treatment.
  • Bladder outlet obstruction or poor bladder emptying, including from an enlarged prostate before prostate surgery, urethral narrowing, a tight bladder-neck/anastomotic scar after surgery, or a bladder that does not contract effectively.
  • Anatomical or functional conditions, such as a narrowing where the kidney joins the ureter (a pelvi-ureteric junction obstruction), reflux of urine towards the kidney, or in some circumstance, pregnancy.
  • Blood clots or inflammation, which can temporarily obstruct drainage.
  • Cancer, either growing in the urinary tract or pressing on a ureter from nearby tissues or lymph nodes. Possible cancers include prostate, bladder, bowel, gynaecological and other pelvic or abdominal cancers. A cancer-related cause is only one possibility; imaging and clinical assessment are needed to establish the cause.

Prostate cancer and hydronephrosis

Prostate cancer can affect urine drainage in different ways. A locally advanced tumour may involve the bladder outlet or the area where the ureters enter the bladder. Cancer in pelvic or abdominal lymph nodes can press on one or both ureters. These problems are more likely with locally advanced or recurrent disease than with an early cancer confined to the prostate, but each person’s situation is different.

Hydronephrosis in someone who has had prostate cancer does not automatically mean the cancer has returned. Stones, infection, scarring, bladder-emptying problems and unrelated conditions remain possible. The team will consider the person’s history, prostate-specific antigen (PSA) trend, symptoms, blood and urine tests, and the pattern seen on imaging. Further tests may be appropriate if the cause is not clear.

After radical prostatectomy

After prostate removal, the bladder is joined to the urethra. Scarring at this join (a vesicourethral anastomotic stenosis, sometimes called a bladder-neck contracture) can make it difficult to empty the bladder. Significant retention may raise pressure in the bladder and contribute to dilation of both upper urinary tracts. A ureteric injury or later narrowing is a less common possibility. Recurrent cancer or enlarged lymph nodes can also obstruct a ureter, but this is not the only explanation.

Assessment may include checking bladder emptying, kidney function and imaging, with a camera examination or contrast study if needed. Treatment is directed at the level and cause of the blockage: for example, bladder drainage, treatment of a narrowing, or drainage of an obstructed ureter.

After salvage radiation therapy

Radiation can cause inflammation and, less commonly, delayed scarring in urinary tissues. Narrowing of the urethra or bladder outlet can interfere with emptying. A ureteric stricture after pelvic radiation is uncommon, but may develop months or years later. Salvage radiation after prostatectomy is generally directed to the prostate bed; hydronephrosis that appears afterwards still needs a proper assessment rather than being assumed to be a radiation effect or a cancer recurrence.

If imaging shows a narrowed ureter, the team may use CT or MRI, a contrast study, or a functional kidney scan to clarify its site, length and effect on kidney drainage. Treatment can be more complex in previously irradiated tissue, so decisions are individualised and may involve a reconstructive urologist, radiation oncologist, medical oncologist or interventional radiologist.

Symptoms and when to seek urgent care

Hydronephrosis can cause no noticeable symptoms, particularly when it develops gradually or affects one kidney. When symptoms occur, they may include pain in the side, back or abdomen; nausea or vomiting; blood in the urine; difficulty passing urine; or repeated urinary infections.

Please seek urgent medical assessment for fever or shaking chills with suspected urinary blockage, severe or worsening pain, repeated vomiting, very little or no urine, confusion, or feeling suddenly very unwell. Infection behind a blockage can become serious and may need urgent antibiotics and drainage. Sudden inability to pass urine also needs prompt care.

How is it investigated?

The first aim is to understand whether there is a blockage that needs prompt relief and what is causing it. Assessment commonly includes:

  1. A conversation and examination, including previous cancer treatments, operations, stones, infections, urinary symptoms and medicines.
  2. Blood tests, especially creatinine and estimated kidney function, and urine tests for infection or blood.
  3. Ultrasound, which can show dilation of the kidneys and bladder and whether the bladder empties.
  4. CT or MRI, selected according to the suspected cause and the person’s kidney function, to look for stones, strictures, masses or enlarged lymph nodes.
  5. Additional tests where useful: a MAG3 renal scan can assess each kidney’s contribution and drainage; cystoscopy or contrast X-rays can clarify the bladder outlet or ureter.

Not everyone needs every test. The clinician will choose investigations that answer the question while taking account of kidney function, previous treatment and the person’s circumstances.

Management options

Treatment is tailored to the cause and the degree of risk. The goals may be to protect kidney function, treat infection or pain, restore urine flow, enable other cancer treatment, or support comfort and quality of life.

Observation and treatment of the cause

Mild, stable hydronephrosis may sometimes be monitored with repeat blood tests and imaging, particularly if there is no infection, troublesome pain or evidence of kidney function decline. A stone may pass or be treated with medication, ureteroscopy or another stone procedure. Infection is treated with antibiotics. Retention may be relieved with a bladder catheter while the cause is assessed. A benign narrowing may be treated by endoscopic incision or dilation, reconstruction, or another procedure depending on its location and the person’s health.

Draining the kidney

If drainage is needed, there are two common approaches:

  • Ureteric stent (often called a JJ stent): a thin internal tube placed between the kidney and bladder, usually using a camera. It can avoid an external collection bag, but may cause urinary frequency, urgency, discomfort, blood in the urine or infection, and it usually needs planned replacement or removal. A tight narrowing or external cancer pressure can make stent placement difficult or less reliable.
  • Percutaneous nephrostomy: a small tube placed through the skin of the back into the kidney, usually by an interventional radiologist, to drain urine into an external bag. It can be useful when a stent cannot be placed, has not drained adequately, or rapid reliable drainage is needed. The tube needs care and periodic changes and can affect daily activities.

The choice depends on the site and cause of obstruction, infection, anatomy, kidney function, expected duration, other treatment plans and personal preference. Sometimes a nephrostomy is used first, with an internal stent considered later. Drainage can relieve pressure and help kidney function, but it does not remove the underlying cause; further treatment or monitoring is often needed.

When might palliative care be part of the plan?

“Palliative” can sound frightening, but palliative care is focused on comfort, symptom relief, support and quality of life. It can be provided alongside active cancer treatment. It does not mean that someone is being abandoned or that all treatment has stopped.

When hydronephrosis is caused by advanced cancer, a stent or nephrostomy may help with pain, infection, kidney function, or the ability to receive cancer treatment. It can also bring burdens such as procedures, hospital visits, tube or stent symptoms, repeat exchanges and complications. In some situations, drainage may not improve symptoms or kidney function enough to outweigh those burdens. Evidence in this area is limited, and outcomes vary widely; population averages cannot predict an individual person’s future.

There is no single point at which palliation is “required.” The decision is made with the patient, their chosen supports and the treating team. It can help to discuss:

  • What problem are we hoping drainage will improve?
  • How likely is it to help, and how soon might we know?
  • What would living with a stent or nephrostomy involve?
  • Could the result allow another treatment that matters to me?
  • What might happen if we monitor or manage symptoms without drainage?
  • What matters most to me now: time at home, symptom relief, kidney function, further cancer treatment, or avoiding procedures?

Choosing not to have a procedure is also a valid choice when it best fits a person’s wishes and clinical circumstances. The team can still treat pain, nausea, infection and other symptoms, and provide practical and emotional support. These conversations are best held early and revisited as circumstances change.

In summary

Hydronephrosis means that urine is collecting in one or both kidneys, but it does not identify the cause on its own. Many causes are benign and treatable. Prostate cancer, previous prostate surgery and radiation can be relevant, but a careful assessment is needed before drawing conclusions. Some people need urgent drainage; others can be monitored or treated in a less invasive way. When cancer is advanced, decisions about drainage and palliative care should be compassionate, individualised and guided by what is most important to the person.

References and further reading

  1. National Kidney Foundation. Hydronephrosis. Updated 2023.
  2. Mayo Clinic. Hydronephrosis: Diagnosis and treatment. Updated 2024.
  3. European Association of Urology. EAU Guidelines on Urolithiasis. See section on sepsis and anuria in an obstructed kidney.
  4. National Institute for Health and Care Excellence. Prostate cancer: diagnosis and management (NG131). Includes recommendations on upper urinary tract decompression for obstructive uropathy secondary to hormone-relapsed prostate cancer.
  5. Chorbińska J, Krajewski W, Zdrojowy R. Urological complications after radiation therapy—nothing ventured, nothing gained: a narrative review. Transl Androl Urol. 2021;10(8):3553–3566. doi:10.21037/tau-20-1217.
  6. Carilli M, et al. Management of ureteral stricture disease after radiation therapy for pelvic malignancies. Cancers (Basel). 2024;16(21):3561. doi:10.3390/cancers16213561.
  7. Shah M, et al. Malignant upper urinary tract obstruction in cancer patients: a systematic review. BJUI Compass. 2024;5(11):915–925. doi:10.1002/bco2.340.
  8. Gauhar V, et al. Nephrostomy tube versus double J ureteral stent in patients with malignant ureteric obstruction: a systematic review and meta-analysis of comparative studies. Int Braz J Urol. 2022;48(6):903–914. doi:10.1590/S1677-5538.IBJU.2022.0225.

This page provides general information and is not a substitute for an individual assessment by a qualified health professional. If you have hydronephrosis, your clinician can explain what the scan means in your circumstances and whether further tests or treatment are needed.

A kidney tumour larger than 3 cm: what does it mean?

By Dr Jo Schoeman | Patient information | September 2026

Finding a kidney mass can be frightening. The first question is whether it is cancer; the next is whether it is confined to the kidney. A mass measuring 3.1 cm is not automatically advanced cancer. If a renal cell carcinoma (RCC) is no more than 4 cm and remains within the kidney, it is classified as T1a. A tumour over 4 cm but no more than 7 cm, still confined to the kidney, is T1b. Lymph-node and distant spread are assessed separately. Some kidney masses are benign, and imaging alone cannot always tell us which. [1–3]

How might it present?

Many tumours are discovered by chance during an ultrasound or CT scan for another problem. Others cause blood in the urine, persistent pain in the side or back, or occasionally a palpable lump. Unexplained weight loss, fatigue, anaemia or fever warrant assessment, although they have many possible causes. The combination of blood in the urine, pain and a palpable mass is uncommon. Visible blood in the urine should always be investigated; a kidney mass does not rule out another source of bleeding. [2]

What investigations are needed?

  • Dedicated imaging: A multiphase contrast CT of the kidneys and abdomen shows whether the lesion enhances, its exact position, its relationship to major blood vessels and the collecting system, and whether there are enlarged nodes or signs of spread. Chest imaging completes staging; its extent is tailored to the tumour and clinical circumstances. MRI may clarify an uncertain lesion or suspected tumour extension into a vein, or be useful when CT contrast is unsuitable. A complex kidney cyst needs its own imaging assessment. [2]
  • Blood and urine tests: Kidney function (creatinine and eGFR), a full blood count and other tests guided by the clinical picture help assess fitness for treatment and preserve kidney function. Urine testing may identify infection or another cause of bleeding. [2]
  • Biopsy: A needle biopsy can be useful if its result will change management, particularly before ablation or drug treatment without prior tissue diagnosis. A typical surgically removable solid mass does not always need a biopsy beforehand. A biopsy can occasionally be inconclusive. [2]
  • Further staging: Bone or brain scans are generally reserved for relevant symptoms or suspected advanced disease. Routine PET scans and bone scans are not recommended for initial RCC staging. [2]

The team should review the images, kidney function, other medical conditions and the patient’s priorities together. An indeterminate mass should not be labelled definitively as RCC before appropriate assessment.

A note about my practice: I no longer perform nephrectomies. I can assess your kidney mass, discuss the findings and treatment options with you, and, if an operation is appropriate, refer you to a colleague who performs kidney surgery. We can also arrange input from a multidisciplinary team where needed.

Treatment when the tumour is confined to the kidney

Partial nephrectomy removes the tumour while preserving the rest of the kidney. This is generally preferred for T1 cancers when technically feasible, particularly if kidney function is reduced or there is only one functioning kidney. It can be performed by robotic, laparoscopic or open surgery according to tumour complexity and surgical expertise. Risks include bleeding, urine leak, infection, reduced kidney function and, occasionally, the need to remove the whole kidney. [1]

Radical nephrectomy removes the kidney and may be appropriate when a safe partial nephrectomy is not feasible, particularly with a larger or more complex tumour. Robotic or laparoscopic surgery offers an approach to the operation; it does not change the underlying choice between partial and radical removal. [1]

Active surveillance may suit selected people with a small, slow-growing mass, competing health risks or a strong preference to defer treatment. It involves planned scans and a clear trigger to reconsider treatment. A tumour just above 3 cm needs a particularly careful discussion because the room for further growth before 4 cm is limited. Thermal ablation, such as cryoablation or radiofrequency or microwave ablation, may suit selected small tumours, especially when surgery is unsuitable; a biopsy is recommended before ablation. Local recurrence and the possible need for repeat treatment should be discussed. [1, 2]

Stereotactic ablative radiotherapy (SABR) is also being used in specialist centres for selected patients with localised RCC who cannot undergo surgery. It is a distinct option from routine radiation after an operation, and its long-term comparative evidence continues to mature. [1]

What if lymph nodes look enlarged?

An enlarged node on a scan is suspicious, not proof of cancer; inflammation can also enlarge nodes. The team considers the appearance and site of the nodes, whether there is disease elsewhere and whether tissue confirmation will change treatment. If nephrectomy is planned, visibly enlarged regional nodes may be removed for diagnosis and staging. Removing normal-looking nodes routinely has not been shown to improve survival for organ-confined RCC. The survival benefit of removing involved nodes is uncertain. [1]

Confirmed regional node involvement is a substantial change in risk even if the kidney tumour is small. It calls for multidisciplinary discussion about whether all visible disease can be removed, whether postoperative drug treatment is appropriate, and how closely to monitor. Nodes beyond the regional area, or spread to organs such as the lung or bone, may represent metastatic disease and require a different plan. Surgery on the kidney is not automatically the best first step when cancer is widespread. [1, 3]

When does immunotherapy help?

For selected patients with clear-cell RCC at higher risk of recurrence after complete surgery, a course of pembrolizumab may lower recurrence risk and has shown an overall survival benefit in the KEYNOTE-564 study. The eligible groups include some patients with confirmed regional node involvement and no distant metastases. A 3–4 cm node-negative tumour confined to the kidney would not usually qualify based on size alone. The final pathology, stage and overall health matter. [1, 4]

If cancer has spread and cannot all be removed, initial treatment for clear-cell RCC often combines immune checkpoint drugs with each other (nivolumab plus ipilimumab) or combines immunotherapy with an oral targeted drug (for example, pembrolizumab plus axitinib, pembrolizumab plus lenvatinib, or nivolumab plus cabozantinib). The best regimen depends on risk group, other illnesses, kidney function, previous treatment and the specific cancer subtype. Papillary and other non-clear-cell cancers may need different approaches. Availability and subsidy in Australia should be checked for the individual indication. [1]

Immunotherapy can cause serious inflammation of the bowel, lungs, liver, kidneys or hormone-producing glands; targeted drugs can cause high blood pressure, diarrhoea, fatigue and other adverse effects. Some immune effects can persist after treatment ends. Benefits and risks need an individual discussion with a medical oncologist. [1, 4]

Is chemotherapy useful?

Conventional cytotoxic chemotherapy is generally ineffective for the common types of RCC and is not standard treatment for ordinary clear-cell RCC. Rare subtypes, including collecting duct and renal medullary carcinoma, are exceptions in which chemotherapy may have a role. A cancer arising from the lining of the renal pelvis (upper-tract urothelial carcinoma) is a different disease with different chemotherapy options; establishing the diagnosis matters. [1]

Does radiation offer a benefit?

Radiotherapy is not routinely given after nephrectomy to prevent recurrence of localised RCC. Its clearest established role is treating specific problems from spread, such as painful bone lesions, brain metastases or symptoms from another site. Precisely targeted radiation may also control selected limited metastases or treat a primary tumour in someone unsuitable for surgery. Whether it adds benefit to systemic therapy or surgery in an individual case depends on the site, number and behaviour of lesions and is best decided with radiation oncology input. It should not be presented as a standard substitute for an operable partial nephrectomy. [1, 5]

Questions worth asking at your consultation

  1. Is this definitely a solid enhancing kidney tumour, and what is its exact size and location?
  2. Is the disease confined to the kidney? Are any nodes merely enlarged, or proven to contain cancer?
  3. Can we safely preserve part of the kidney? What is my current kidney function?
  4. Would a biopsy change the plan?
  5. If the cancer is clear-cell and higher risk, would adjuvant pembrolizumab be suitable?
  6. Would drug treatment or targeted radiation offer a benefit in my particular situation?

Seek prompt medical attention for heavy bleeding with clots, inability to pass urine, severe persistent pain, or sudden neurological symptoms. This article is general information and cannot replace review of your scans and pathology at a multidisciplinary meeting.

References

  1. European Association of Urology. EAU Guidelines on Renal Cell Carcinoma: Disease Management. 2026.
  2. European Association of Urology. EAU Guidelines on Renal Cell Carcinoma: Diagnostic Evaluation. 2026.
  3. European Association of Urology. EAU Guidelines on Renal Cell Carcinoma: Staging and Classification Systems. 2026.
  4. National Cancer Institute. Adjuvant Keytruda improves kidney cancer survival, reporting updated KEYNOTE-564 outcomes. 2024.
  5. National Cancer Institute. Renal Cell Cancer Treatment (PDQ), Health Professional Version. Accessed September 2026.

Prostate cancer with kidney failure: is surgery, focal therapy or radiation the right choice?

A patient guide by Dr Jo Schoeman

A diagnosis of prostate cancer is unsettling. Having chronic kidney disease or needing dialysis can make treatment decisions feel even harder. The reassuring point is that kidney failure does not automatically rule out treatment. The best choice depends on the cancer, the degree of kidney impairment, other medical conditions and, crucially, whether a kidney transplant is planned.

What does Gleason 3+4 mean?

Gleason 3+4=7 is Grade Group 2 prostate cancer. Most of the sampled tumour has pattern 3, with a smaller component of pattern 4. It is generally less concerning than Gleason 4+3=7, but “3+4” alone cannot tell us whether immediate treatment is needed.

I would review the PSA and PSA density, examination, MRI findings, number and length of positive biopsy cores, percentage of pattern 4, any cribriform or intraductal cancer, and whether disease is confined to the prostate. Kidney function, dialysis schedule, life expectancy and transplant eligibility are considered alongside these findings. Some men have favourable intermediate-risk cancer; others have features that make definitive treatment more appropriate. Staging scans are selected according to overall risk rather than biopsy grade alone. [1,2]

Could active surveillance be reasonable?

Yes, for selected men with small-volume, favourable Grade Group 2 cancer. Surveillance means scheduled PSA tests, clinical review, MRI where useful and repeat biopsy when indicated. It keeps treatment available if the cancer changes. It is a particularly meaningful option when another serious illness makes the harms of immediate treatment more likely to outweigh its benefit. It does, however, require a patient who can attend follow-up and accepts a small increased risk of progression compared with immediate treatment. [1,2]

If kidney disease or other illnesses substantially limit life expectancy, watchful waiting may be more appropriate: care focuses on symptoms rather than routine testing intended to trigger curative treatment. This is a separate decision from active surveillance. [1]

Can radical prostatectomy or robotic surgery be performed?

Often, yes. Chronic kidney disease and dialysis are not automatic contraindications to radical prostatectomy. Robotic assisted surgery may offer less blood loss and a shorter hospital stay than open surgery in selected patients, but it still involves general anaesthesia, abdominal insufflation and a head-down operating position. Advanced kidney disease increases the importance of planning for bleeding, infection, fluid and electrolyte balance, medication dosing and postoperative kidney injury. Population studies find higher complication rates in patients with chronic kidney disease, particularly advanced disease; individual risk varies considerably. [3,4]

Before an operation I would coordinate with the nephrologist, anaesthetist and, where relevant, dialysis team. We would assess cardiovascular health, haemoglobin, potassium, anticoagulants, residual kidney function and the timing of dialysis. Surgery also carries the usual risks of urinary leakage or incontinence, erectile dysfunction, infertility, blood clots and possible need for further cancer treatment. Whether a robotic approach is feasible depends on the patient and the surgical team; it is not automatically a safer choice for every person with kidney failure. [1,3,4]

Is focal therapy a better option?

Not simply because the kidneys are failing. Focal therapy treats the visible cancer-bearing portion of the prostate, using a technique such as focused ultrasound, cryotherapy or another ablative method. It may appeal to men hoping to reduce urinary or sexual side effects, but the cancer can be present elsewhere in the gland, and longer-term cancer control is less certain than for established whole-gland treatments. Further MRI, biopsies and sometimes repeat treatment are necessary.

The AUA/ASTRO guideline notes a lack of high-quality comparisons with surgery, radiation and surveillance. European guidance restricts focal treatment to settings with careful prospective follow-up, such as a trial or registry. Kidney disease alone does not establish that focal treatment is preferable. In a suitable patient it can be discussed with a specialist who explains uncertainty, access, costs and a clear follow-up plan. [1,2]

Is radiotherapy an option?

Yes. External beam radiotherapy avoids major surgery and usually does not expose the kidneys directly when treating a prostate confined to the pelvis. Options include moderately shortened courses and, for selected men, more condensed schedules or brachytherapy. The radiation oncologist will tailor treatment to the cancer and urinary function. Depending on whether the disease is favourable or unfavourable intermediate risk, a course of androgen deprivation therapy (ADT) may also be advised; ADT has its own effects on energy, muscle, bone and metabolic health. [1,2]

Radiotherapy may cause temporary urinary frequency, burning or bowel upset; longer-term urinary, bowel or erectile effects are also possible. Existing urinary obstruction and kidney transplant anatomy can change planning. In a transplant recipient, the graft and ureter may sit in the pelvis, so radiation dose constraints require particular attention. Dialysis, by itself, does not make prostate radiation impossible. [1,2]

What if a kidney transplant is planned?

This is a central part of the discussion. A transplant team may need to know whether the cancer is under surveillance or has been treated, its estimated risk of progression and the proposed follow-up. The presence of prostate cancer does not automatically mean that transplantation must wait for a fixed number of years; transplant eligibility is individual and should be discussed directly with the transplant team. A transplanted kidney in the pelvis also affects the planning of later pelvic surgery or radiotherapy. [5]

How do we decide?

Option When it may fit Main trade-off
Active surveillance Low-volume, favourable Grade Group 2 disease Regular testing and a possibility of later treatment
Robotic radical prostatectomy Fit patient seeking definitive local treatment Anaesthetic and surgical risks, with continence and erectile side effects
Radiotherapy Patient seeking definitive treatment without prostate removal Urinary, bowel and sexual effects; ADT may be needed
Focal therapy Carefully selected patient after discussion of uncertainty Less established long-term cancer control and ongoing biopsies
Watchful waiting Limited life expectancy or major competing health risks Treats symptoms if they arise rather than aiming for cure

There is no universal winner between robotic surgery and radiation for Gleason 3+4 cancer with kidney failure. A multidisciplinary discussion involving urology, radiation oncology, nephrology and the transplant team, if applicable, helps align cancer control with kidney health and the patient’s priorities.

This article offers general information and cannot determine treatment for an individual patient. Decisions require review of the pathology, imaging, kidney function and overall health.

References

  1. European Association of Urology. EAU Guidelines on Prostate Cancer: Treatment. Accessed September 2026.
  2. American Urological Association and American Society for Radiation Oncology. Clinically Localized Prostate Cancer Guideline. 2022.
  3. Post-surgical outcomes of patients with chronic kidney disease and end stage renal disease undergoing radical prostatectomy: 10-year results from the US National Inpatient Sample. 2019.
  4. The Effect of Chronic Kidney Disease on Adverse In-Hospital Outcomes at Radical Prostatectomy. 2025.
  5. Kidney Disease: Improving Global Outcomes. KDIGO Clinical Practice Guideline on the Evaluation and Management of Candidates for Kidney Transplantation. 2020.

Urethral bulking for stress urinary incontinence: a first procedure or an option after a sling?

Leaking urine when you cough, laugh, exercise or lift something is called stress urinary incontinence (SUI). It differs from urgency incontinence, when a sudden need to pass urine leads to leakage. Some women have both. Identifying which symptom is most troublesome matters because an injection aimed at SUI will not reliably treat urgency.

Urethral bulking involves placing small deposits of material into the wall of the urethra, usually through a fine instrument passed into the urethra. The deposits help the urethra close when pressure rises. You may hear this described as periurethral bulking, although many contemporary injections are delivered through the urethra into its surrounding wall. This is generally a day procedure under local anaesthesia or sedation/general anaesthesia, depending on the circumstances. It does not place a sling or mesh tape.

Could bulking be my first procedure?

Yes. After a trial of pelvic floor muscle training and discussion of other conservative measures, bulking can be chosen as a first procedure for appropriately assessed SUI. It may appeal to someone seeking a shorter procedure and recovery, or wishing to avoid a sling. It is also an option when a larger operation or anaesthetic carries additional risk. It is not usually the first treatment before conservative care. USANZ’s 2026 position statement lists bulking alongside autologous fascial slings, colposuspension and synthetic midurethral slings among the standard options that should be discussed. UGSA’s patient information stresses its lower success and frequent need for repeat treatment. [1–3]

Bulking, synthetic midurethral sling surgery, a sling made from the patient’s own fascia, and colposuspension have different benefits and risks. A donated-tissue (allograft) sling is distinct from a sling made from your own tissue (autograft) and from a synthetic mesh sling; the strength and duration of evidence for each are different. No single procedure is best for every woman. [1,4]

How effective and durable is it?

The realistic aim is often less leakage, rather than guaranteed dryness. Success figures change substantially depending on whether researchers count complete dryness, improvement, satisfaction, or avoidance of further treatment. UGSA’s patient leaflet quotes about 40–50% cure or improvement and reports that approximately 30% need a further injection within two years. These are broad counselling figures, not a prediction for an individual. [2]

Some women remain improved for years, but repeat injections or another operation may be needed. In a randomised comparison of polyacrylamide hydrogel injection and synthetic tension-free vaginal tape for primary SUI, the tape achieved better objective continence at one year (negative cough test 95.0% versus 66.4%). The five-year follow-up did not establish that injection was non-inferior to tape. The EAU similarly advises that bulking is generally less effective than slings or colposuspension for cure, and that repeat injection is likely. These findings do not mean everyone should have a tape: the value of a less invasive procedure and the acceptability of a possible repeat treatment are personal considerations. [4–6]

What if I still leak after a sling?

Bulking can be considered for persistent leakage soon after a sling or recurrent leakage after an initial period of improvement. It can sometimes reduce leakage without placing another sling. A 2022 systematic review of 11 studies after synthetic midurethral sling failure reported a pooled 75% cure-or-improvement rate, but also pooled failure and further-operation rates of 32% and 25%. The studies differed considerably in their patients, products, follow-up and definitions of success; the 75% figure should not be presented as a personal chance of cure. An American Urogynecologic Society clinical practice statement also recognises bulking as an option after a sling. [7,8]

After an allograft sling, the same clinical possibility exists, but the published post-sling bulking evidence is mainly about synthetic midurethral slings. We should not simply transfer those success figures to donated-tissue slings. The precise graft, previous surgery and examination findings should guide an individual discussion.

An injection should not be used to mask a sling complication. Before offering more treatment, I would review the original operation, check urine and bladder emptying, examine for prolapse, scarring and vaginal exposure, and assess whether leakage occurs with coughing or with urgency. Cystoscopy, a bladder diary, pad testing or urodynamics may be appropriate, especially after previous surgery, mixed symptoms, pain, blood in the urine or difficulty emptying. A tape or graft causing obstruction, exposure, erosion, infection or pain may require its own assessment and treatment. [1,3,7]

Is it safe? What are the side effects?

Most reported problems are short lived, but no injection is risk free. Possible effects include:

  • burning when passing urine and a little blood in the urine;
  • urinary tract infection;
  • temporary difficulty emptying the bladder, occasionally requiring short-term catheterisation;
  • new or persisting urgency symptoms; and
  • incomplete benefit, recurrence or the need for another injection or operation.

Less commonly, there may be persistent pain, a collection or infection at the injection site, or a reaction or complication related to the particular material. Risks also depend on anaesthesia, previous surgery and the chosen product. Emptying should be checked before discharge. Seek prompt assessment if you cannot pass urine, develop fever, worsening pain or heavy bleeding. [2,4,8]

Choosing a treatment

The first step is to confirm the type and severity of leakage and clarify your goals: complete dryness, meaningful improvement, shorter recovery, avoiding mesh, or avoiding the likelihood of repeat treatment. Pelvic floor therapy remains an initial option. When a procedure is appropriate, we can compare bulking with sling and colposuspension procedures using your examination findings, health history and preferences. If you have already had a sling, the reason for the continuing leakage deserves a fresh assessment before choosing another procedure.

This page is general education, not a recommendation for a particular product or a promise of a result. Treatment, including its material, risks, costs and alternatives, should be discussed during an individual consultation.

References

  1. Urological Society of Australia and New Zealand (USANZ). Surgical Treatment of Stress Urinary Incontinence: Position Statement Pol 054, version 2.0. Approved 9 May 2026.
  2. Urogynaecological Society of Australasia (UGSA). Urethral Bulking: Patient Information.
  3. UGSA. Stress Urinary Incontinence: Patient Resources.
  4. European Association of Urology. Guidelines on Non-neurogenic Female Lower Urinary Tract Symptoms: Disease Management, section 4.2.4.c.2.c.
  5. Itkonen Freitas A-M, et al. Tension-free vaginal tape surgery versus polyacrylamide hydrogel injection for primary stress urinary incontinence: a randomised clinical trial. Journal of Urology. 2020.
  6. Itkonen Freitas A-M, et al. Tension-free vaginal tape versus polyacrylamide hydrogel injection for stress urinary incontinence: five-year follow-up. NEJM Evidence. 2025.
  7. Braga A, et al. Urethral bulking agents for the treatment of recurrent stress urinary incontinence: a systematic review and meta-analysis. Maturitas. 2022. doi:10.1016/j.maturitas.2022.05.007.
  8. American Urogynecologic Society. Urethral Bulking: Clinical Practice Statement. Urogynecology. 2024. doi:10.1097/SPV.0000000000001548.