
Cxbladder Urine Testing for Urothelial Cancer: Diagnosis, Surveillance, Accuracy and Pitfalls
Bladder cancer surveillance can feel repetitive: another cystoscopy, another urine sample and another anxious wait. This has driven interest in urine-based molecular tests that may help identify patients at very low risk of recurrent urothelial carcinoma.
One such platform is Cxbladder. It is sometimes informally called “Cx View,” but the established commercial name is Cxbladder. The version designed for patients who already have a history of urothelial cancer is Cxbladder Monitor.
Cxbladder can provide useful additional information, particularly when the clinical question is whether cancer is unlikely to be present. However, it is not a stand-alone diagnosis, does not show where a tumour is located and should not automatically replace cystoscopy, imaging or biopsy.
What is the Cxbladder test?
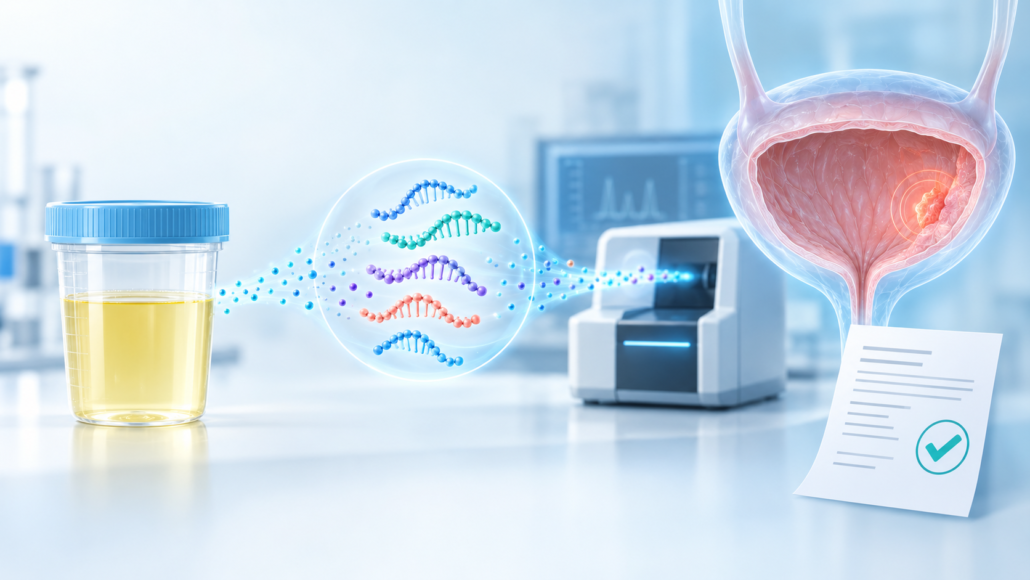
Cxbladder is a non-invasive laboratory test performed on voided urine. It measures the expression of five messenger RNA biomarkers associated with urothelial carcinoma:
- IGFBP5
- HOXA13
- MDK
- CDK1
- CXCR2
The result is calculated using a proprietary algorithm. Depending on the particular Cxbladder assay, clinical variables may also be incorporated into risk assessment.
The test looks for a molecular signal shed into urine by urothelial cancer cells. It does not provide a picture of the bladder, determine tumour size or location, reliably assign stage or grade, or replace histopathological examination.
The different Cxbladder tests are not interchangeable
The name “Cxbladder” covers several tests developed for different clinical settings.
Cxbladder Triage
This is designed primarily to help identify patients with haematuria who have a low probability of urothelial cancer. It prioritises sensitivity and negative predictive value, accepting lower specificity.
Cxbladder Detect
This is intended to help identify urothelial cancer in patients undergoing diagnostic evaluation, such as those presenting with haematuria. It is not specifically designed for post-treatment surveillance.
Cxbladder Monitor
This is designed for patients with a previous diagnosis of urothelial carcinoma who are undergoing surveillance for recurrence. It is the most relevant assay for follow-up after treatment of non-muscle-invasive bladder cancer (NMIBC).
Newer or region-specific Cxbladder combinations may use different algorithms and thresholds. Performance figures from one assay should not be transferred uncritically to another.
How is the sample collected?
The patient provides a voided urine sample into the supplied collection system. No catheter is normally required. The sample is stabilised and sent to a specialised laboratory for analysis.
Collection instructions must be followed carefully. Insufficient urine, incorrect handling, contamination, excessive delay or failure to use the correct collection container may produce an invalid or unreliable result. A repeat sample may occasionally be required.
What role can Cxbladder have in initial diagnosis?
For a patient with visible or microscopic haematuria, Cxbladder may help refine the estimated probability of urothelial cancer. A low-risk result can be reassuring, especially in a carefully selected lower-risk patient.
However, haematuria can be caused by bladder cancer, upper-tract urothelial cancer, renal cancer, urinary stones, infection, benign prostate bleeding and other conditions. A urine biomarker cannot evaluate all these causes. Depending on age, symptoms and risk factors, the patient may still require cystoscopy and upper-tract imaging.
Current guideline-based haematuria assessment is risk stratified. Urine markers may support shared decision-making in selected patients, but should not delay investigation of visible haematuria or replace a complete assessment in a patient at significant risk.
How may Cxbladder Monitor be used in surveillance?
After treatment of NMIBC, conventional surveillance may include:
- cystoscopy;
- urine cytology in selected intermediate- and high-risk patients;
- upper-tract imaging when indicated; and
- biopsy or TURBT when a suspicious lesion is found.
Cxbladder Monitor may be added to this pathway to help identify patients with a low probability of recurrent disease. In selected lower-risk situations, a negative result may support extending the interval to cystoscopy or avoiding an additional cystoscopy, provided this forms part of a urologist-directed protocol.
A positive result does not prove that a recurrence is present. It usually means that further assessment, commonly cystoscopy, and sometimes cytology, enhanced cystoscopy, imaging or biopsy is warranted.
The test should be used particularly cautiously in patients with previous high-grade disease, carcinoma in situ (CIS), recent positive cytology, new haematuria, concerning symptoms or a history suggesting a high risk of progression. Missing high-grade recurrence carries much greater consequences than postponing a procedure in a genuinely low-risk patient.
How accurate is Cxbladder Monitor?
Published validation data have generally shown that Cxbladder Monitor is better at ruling out recurrence than confirming it.
Across key validation studies, reported performance has been approximately:
- sensitivity: 91–93%;
- negative predictive value (NPV): 96–97%;
- specificity: approximately 34–39%; and
- positive predictive value (PPV): approximately 21% in some validation cohorts.
One comparative study reported sensitivity of 91% and NPV of 96% for Cxbladder Monitor, outperforming cytology, NMP22 and UroVysion FISH for sensitivity in that study population. Another validation reported sensitivity of 93% and NPV of 97%.
These results need careful interpretation.
What does a negative predictive value of 97% mean?
In a study population similar to the one in which that figure was measured, about 97 of every 100 patients with a negative result did not have a detected recurrence, while approximately three could still have disease.
It does not mean the test is “97% accurate” in every patient. NPV changes with the underlying prevalence of recurrence. It will usually look higher in a low-risk population and lower when recurrence is common.
Why is the positive predictive value relatively low?
When specificity is low, many patients with a positive result will not have cancer confirmed on the subsequent assessment. A positive test is therefore a prompt to investigate, not a cancer diagnosis.
Does it detect high-grade disease better?
Urine-based biomarkers often perform better for biologically active high-grade tumours than for very small low-grade recurrences. Nevertheless, no negative urine test can guarantee that high-grade tumour or CIS is absent. Study populations also differ in the proportions of low-grade, high-grade and recently treated patients, making direct comparisons difficult.
Important pitfalls
1. A negative result can be falsely reassuring
False negatives occur. Small, low-volume or intermittently shedding tumours may release too little RNA into the urine. A diluted or poorly collected sample may also reduce the signal. A negative result must not override visible haematuria, positive cytology, a suspicious cystoscopy or a high-risk clinical history.
2. A positive result is not proof of cancer
Because Monitor is deliberately designed to be sensitive, specificity is modest. A positive result may lead to cystoscopy or biopsy that finds no tumour. The test cannot identify the lesion’s location, stage or grade.
3. Infection, inflammation and recent instrumentation complicate interpretation
Urinary infection, stones, bleeding, recent cystoscopy, catheterisation, TURBT, intravesical BCG or chemotherapy can alter urinary cellular material and the clinical context. Cxbladder includes an inflammatory-associated marker intended to reduce this “background noise,” but real-world confounding is not eliminated. Testing should be timed and interpreted by the treating urologist.
4. The test does not examine the upper urinary tract
Urothelial cancer may arise in the ureter or renal pelvis. A urine result cannot localise a tumour or replace CT urography, ureteroscopy or other upper-tract evaluation when clinically indicated.
5. It does not replace pathology
Only tissue examination can determine tumour grade, assess invasion and guide definitive treatment. Cxbladder is a risk-stratification tool rather than a histological diagnosis.
6. Performance may not generalise perfectly
Some studies were supported by or involved investigators connected with the test manufacturer. Many validation cohorts were enriched for particular risk groups and may not reflect every Australian practice. Independent prospective studies, longer follow-up and trials showing that biomarker-guided surveillance preserves oncological outcomes are especially important.
7. “Fewer cystoscopies” is not the same as “no cystoscopies”
Real-world studies suggest that Cxbladder Monitor can reduce cystoscopy frequency in selected low-risk patients. This should not be extrapolated to high-risk NMIBC or used to abandon risk-based surveillance. Cystoscopy remains the direct method of inspecting the bladder and permits immediate biopsy or resection planning.
8. Cost and access vary
Availability, laboratory turnaround time, out-of-pocket cost and reimbursement vary by location and insurer. Australian patients should confirm current access and costs with their urologist and testing provider before collection.
How does it compare with urine cytology?
Urine cytology is highly specific for high-grade urothelial carcinoma but has limited sensitivity, particularly for low-grade tumours. Cxbladder Monitor generally has higher reported sensitivity and NPV, but substantially lower specificity.
The tests therefore answer slightly different questions:
- cytology: a clearly positive result strongly raises concern for high-grade disease;
- Cxbladder Monitor: a negative result may help identify a low probability of recurrence; and
- cystoscopy: directly visualises the bladder and remains central to surveillance.
Combining information may be more useful than treating any one result in isolation.
What do international guidelines say?
Major guidelines acknowledge that urinary molecular markers are improving, but remain cautious about their routine use as complete substitutes for cystoscopy.
- The AUA/SUO NMIBC guideline states that urinary biomarkers should not replace cystoscopic evaluation during surveillance. Markers may be used in selected settings, including assessment of an equivocal cytology result or response to intravesical BCG.
- The EAU NMIBC guideline recognises that molecular urine tests may have a future role in reducing cystoscopy frequency, particularly in lower-risk surveillance, but notes that evidence and prospective implementation data remain insufficient for a universal marker-driven schedule.
- Guideline recommendations evolve as new trials emerge; decisions should be based on the patient’s individual recurrence and progression risk rather than the availability of a test alone.
A practical, balanced approach
Cxbladder Monitor is most helpful when the question is: “Is recurrence sufficiently unlikely that we can safely reduce or postpone an invasive investigation in this particular patient?”
It is less useful as a stand-alone answer to: “Does this patient definitely have cancer, where is it, and how aggressive is it?”
For a carefully selected patient with previous low-risk NMIBC, no new symptoms and a negative Monitor result, a biomarker-informed surveillance plan may reduce unnecessary cystoscopies. For a patient with previous CIS or high-grade tumour, positive cytology, visible haematuria or a suspicious finding, conventional investigation should not be deferred because of a negative urine test.
The result is best interpreted alongside tumour history, grade and stage, time since treatment, cystoscopy findings, cytology, imaging and the patient’s preferences.
References
- Kavalieris L, O’Sullivan P, Frampton C, et al. Performance characteristics of a multigene urine biomarker test for monitoring for recurrent urothelial carcinoma in a multicenter study. J Urol. 2017;197(6):1419–1426. PubMed search
- Lotan Y, O’Sullivan P, Raman JD, et al. Clinical comparison of noninvasive urine tests for ruling out recurrent urothelial carcinoma. Urol Oncol. 2017;35(8):531.e15–531.e22. PubMed search
- O’Sullivan P, Sharples K, Dalphin M, et al. A multigene urine test for the detection and stratification of bladder cancer in patients presenting with hematuria. J Urol. 2012;188(3):741–747. PubMed search
- Li KD, McLennan MT, Barocas DA, et al. Cxbladder Monitor testing to reduce cystoscopy frequency in patients with bladder cancer. J Urol. 2023. PubMed
- Konety B, Shore N, Kader AK, et al. Evaluation of Cxbladder and adjudication of atypical cytology and equivocal cystoscopy. Eur Urol. 2019;76(2):238–243. PubMed search
- Darling D, Luxmanan C, O’Sullivan P, et al. Clinical utility of Cxbladder for the diagnosis of urothelial carcinoma. Adv Ther. 2017;34:1087–1096. PubMed search
- Breen V, Kasabov N, Kamat AM, et al. A holistic comparative analysis of diagnostic tests for urothelial carcinoma: a study of Cxbladder Detect, UroVysion FISH, NMP22 and cytology. BMC Med Res Methodol. 2015;15:27. Full text
- Harvey JC, et al. Analytical validation of Cxbladder Detect, Triage, and Monitor assays for detection and management of urothelial carcinoma. Diagnostics. 2024;14(18):2061. Full text
- Holzbeierlein JM, Bixler BR, Buckley DI, et al. Diagnosis and treatment of non-muscle invasive bladder cancer: AUA/SUO guideline. American Urological Association; amended 2024. AUA guideline
- European Association of Urology. EAU Guidelines on Non-Muscle-Invasive Bladder Cancer. Current online edition. EAU guideline
- Barocas DA, Lotan Y, Matulewicz RS, et al. Updates to microhematuria: AUA/SUFU guideline. J Urol. 2025. PubMed
This article provides general information and does not replace personalised medical advice. Surveillance should be tailored to the original tumour’s stage and grade, prior treatment, current symptoms and the individual’s risk of recurrence and progression.







Leave a Reply
Want to join the discussion?Feel free to contribute!