Kidney Stones: Causes, Symptoms and Modern Treatment Options

Kidney stones are a common urinary condition that can cause significant pain and, in some cases, require treatment by a urologist. While some kidney stones are small enough to pass naturally, larger stones may become lodged in the urinary tract and require medical or surgical treatment.

Understanding the symptoms of kidney stones and knowing when to seek medical attention can help prevent complications and ensure appropriate treatment.

What Are Kidney Stones?

Kidney stones are hard deposits that form from minerals and salts within the urine. They develop inside the kidneys but may move into the ureter — the narrow tube that carries urine from the kidney to the bladder.

Kidney stones vary considerably in size. Some are only a few millimetres across and may pass without treatment, while larger stones can obstruct the urinary tract.

There are several types of kidney stones, including calcium stones, uric acid stones, struvite stones and cystine stones. Calcium-based stones are the most common.

What Causes Kidney Stones?

Kidney stones can develop when the urine becomes concentrated, allowing minerals and other substances to crystallise.

Factors that may increase the risk of developing kidney stones include:

  • Not drinking enough water
  • Hot weather and dehydration
  • A previous history of kidney stones
  • Family history of kidney stones
  • Certain dietary factors
  • High levels of calcium, uric acid or other substances in the urine
  • Recurrent urinary tract infections
  • Certain medications
  • Some metabolic and medical conditions

People who have previously experienced kidney stones are also at increased risk of developing another stone in the future.

What Are the Symptoms of Kidney Stones?

A kidney stone may cause no symptoms while it remains inside the kidney. Symptoms often begin when the stone moves into the ureter.

One of the most recognisable symptoms is renal colic — severe pain caused by obstruction of urine flow.

Symptoms can include:

  • Sudden and severe pain in the side or back
  • Pain that travels towards the lower abdomen or groin
  • Pain that comes and goes in waves
  • Blood in the urine
  • Nausea or vomiting
  • Frequent or urgent urination
  • Pain or burning when urinating

The location and severity of the pain can change as the stone moves through the urinary tract.

When Is a Kidney Stone an Emergency?

Kidney stone pain can be extremely uncomfortable, but certain symptoms require urgent medical assessment.

Seek urgent medical attention if kidney stone symptoms are accompanied by fever, chills, difficulty passing urine or feeling significantly unwell.

A stone that obstructs the urinary tract while an infection is present can become a medical emergency and may require urgent drainage of the kidney.

How Are Kidney Stones Diagnosed?

Your doctor or urologist may use several investigations to determine whether a kidney stone is present and assess its size and location.

These may include:

  • Urine testing
  • Blood tests
  • Ultrasound
  • CT imaging
  • Analysis of a previously passed stone

CT scans are commonly used because they can provide detailed information about the size and location of urinary stones.

Once the stone has been identified, treatment depends on factors including its size, position, symptoms and whether it is causing obstruction or infection.

Can Kidney Stones Pass Naturally?

Many small kidney stones can pass through the urinary tract without surgery.

Treatment may involve pain relief, increased fluid intake when appropriate, and monitoring while waiting for the stone to pass. In selected patients, medication may also be prescribed to assist stone passage.

Larger stones or stones that remain lodged within the urinary tract are less likely to pass naturally and may require treatment.

Modern Treatments for Kidney Stones

There are several procedures available for treating kidney stones. The most appropriate treatment depends on the size, location and characteristics of the stone.

Ureteroscopy and Laser Lithotripsy

Ureteroscopy involves passing a small telescope through the urinary tract to locate the stone.

A laser can then be used to break the stone into smaller fragments. These fragments may be removed or allowed to pass naturally.

Because the procedure is performed through the urinary tract, no external surgical incision is usually required.

Shock Wave Lithotripsy

Shock wave lithotripsy uses externally generated shock waves to break selected kidney or ureteric stones into smaller pieces.

The fragments can then pass through the urinary tract.

This treatment is suitable for some stones, although factors such as stone size, location and composition influence whether it is appropriate.

Percutaneous Nephrolithotomy

Very large or complex kidney stones may require percutaneous nephrolithotomy (PCNL).

During this procedure, the kidney is accessed through a small incision in the back, allowing the surgeon to remove or break up larger stones.

PCNL is generally reserved for stones that are too large or complex for less invasive treatments.

Can Kidney Stones Be Prevented?

For people who have experienced kidney stones, prevention is an important part of ongoing care.

One of the most important measures for many patients is maintaining adequate hydration so that the urine remains diluted.

Depending on the type of stone and the individual’s risk factors, prevention may also involve dietary changes, urine testing, blood tests or medication.

Patients who develop recurrent kidney stones may benefit from a metabolic assessment to identify factors contributing to repeated stone formation.

When Should You See a Urologist?

You may benefit from seeing a urologist if you have:

  • Recurrent kidney stones
  • Persistent pain associated with a urinary stone
  • A stone that is not passing naturally
  • Blood in the urine
  • Recurrent urinary infections associated with stones
  • A large kidney stone identified on imaging
  • Evidence of urinary obstruction

A urologist can assess the location and size of the stone and recommend whether observation or treatment is appropriate.

Kidney Stone Treatment

Kidney stones can range from a minor problem that resolves naturally to a condition requiring urgent treatment.

Modern urological techniques allow many stones to be treated using minimally invasive procedures such as ureteroscopy, laser lithotripsy and shock wave therapy.

If you have symptoms of kidney stones or have been diagnosed with a urinary stone, a urological assessment can help determine the most appropriate treatment and whether further investigation is required to reduce the risk of future stones.

This information is general in nature and does not replace individual medical advice. If you have severe pain, fever, chills or difficulty passing urine, seek urgent medical attention.

Come and have a chat to your local Brisbane Based Urologist, Dr Jo, to discuss options in management

Pelvic Floor Rehabilitation Before and After Prostate Surgery

Preparing the Pelvic Floor for Recovery

Urinary leakage is one of the most common concerns men have when preparing for prostate surgery, particularly radical prostatectomy for prostate cancer. Fortunately, urinary control usually improves progressively after surgery, and pelvic floor rehabilitation can play an important role in helping men regain continence.

Pelvic floor rehabilitation is more than simply “doing Kegels”. It involves learning which muscles to use, how to contract them correctly, when to relax them, and how to incorporate them into everyday activities.

Importantly, more exercise is not necessarily better. The aim is a pelvic floor that is strong, coordinated and responsive, rather than one that is constantly clenched.


What Is the Male Pelvic Floor?

The pelvic floor is a group of muscles forming a supportive sling beneath the pelvis. These muscles contribute to:

  • urinary continence;
  • bowel control;
  • support of the pelvic organs;
  • sexual function; and
  • control of pressure generated during coughing, lifting and physical activity.

After radical prostatectomy, the anatomy of the urinary continence mechanism changes. The prostate and prostatic urethra are removed and the bladder is reconnected to the remaining urethra. Urinary control consequently becomes more dependent upon the remaining urinary sphincter and its supporting pelvic floor musculature.

This is why pelvic floor rehabilitation is particularly relevant after prostate cancer surgery.


Why Start Pelvic Floor Rehabilitation Before Surgery?

Ideally, pelvic floor rehabilitation begins before the operation.

The principal advantage of pre-operative training is not necessarily building dramatically stronger muscles. Rather, it gives the patient an opportunity to identify and correctly activate the pelvic floor before surgery, when there is no catheter, discomfort or postoperative urinary leakage.

Evidence regarding whether pre-operative pelvic floor muscle training independently improves long-term continence rates is mixed. Current European guidelines conclude that pre-operative training has not consistently demonstrated an additional long-term benefit. However, pelvic floor muscle training after radical prostatectomy may shorten the time taken to recover continence.

For many patients, a consultation with a physiotherapist experienced in men’s pelvic health before surgery is therefore useful.


Finding the Correct Pelvic Floor Muscles

A pelvic floor contraction should feel as though you are trying to:

stop yourself passing wind while simultaneously shortening or drawing the penis slightly inward and lifting the scrotum.

The movement should be subtle.

During the contraction:

  • continue breathing normally;
  • avoid holding your breath;
  • keep the abdomen relatively relaxed;
  • avoid strongly squeezing the buttocks;
  • avoid excessive tightening of the thighs; and
  • completely relax the pelvic floor between contractions.

Some men find the correct muscles immediately. Others inadvertently brace their abdominal, buttock or thigh muscles.

This is one reason why an assessment by a pelvic floor physiotherapist can be valuable.

Should I stop my urine flow to find the muscles?

Stopping the urinary stream once can sometimes help identify the muscles involved, but repeatedly practising pelvic floor exercises by interrupting urination is generally not recommended.

Regularly stopping and starting the stream can interfere with normal bladder emptying.


A Practical Pelvic Floor Exercise Programme

There is no single exercise prescription that is perfect for every man. Pelvic floor strength, endurance, coordination and postoperative continence vary considerably.

A physiotherapist may therefore modify the programme according to your examination and progress.

A typical programme contains several components.

1. Slow contractions: strength and endurance

Gently contract and lift the pelvic floor.

Hold the contraction for approximately:

5–10 seconds

Then relax completely for approximately:

5–10 seconds

Repeat approximately:

8–10 times

The quality of the contraction is more important than achieving a particular number.

If you can only maintain a good contraction for three seconds initially, three good seconds are preferable to ten seconds of straining.


2. Quick contractions

The urinary sphincter also needs to react rapidly.

Contract the pelvic floor firmly for approximately one second, then completely release it.

Repeat:

5–10 times

These faster contractions help train the pelvic floor to respond to sudden increases in abdominal pressure.


3. The “Knack”

One of the most useful techniques is learning to contract the pelvic floor immediately before an activity that normally produces leakage.

For example, gently activate the pelvic floor just before:

  • coughing;
  • sneezing;
  • standing from a chair;
  • bending;
  • lifting;
  • getting out of a car; or
  • performing physical exercise.

This anticipatory contraction is sometimes called the Knack.

It turns pelvic floor training from an isolated exercise into a functional skill.


How Often Should I Exercise?

This is where the principle of quality rather than quantity becomes important.

For many men, a structured programme performed two to three times per day is sufficient during active rehabilitation.

A session might consist of:

8–10 controlled slow contractions followed by 5–10 quick contractions.

However, this should not be regarded as a universal prescription. Your physiotherapist or surgeon may recommend a different programme according to your muscle strength, continence and ability to relax the pelvic floor.

The pelvic floor is skeletal muscle. Like other muscles, it needs work, recovery and progression.

Doing hundreds of contractions every day is rarely necessary.


Can You Do Too Many Pelvic Floor Exercises?

Yes.

One of the common misconceptions after prostate surgery is:

“If ten exercises are good, one hundred must be better.”

Unfortunately, pelvic floor muscles can become fatigued just like any other muscle.

Excessive training or constantly holding the pelvic floor contracted can potentially cause:

  • pelvic or perineal discomfort;
  • difficulty relaxing the pelvic floor;
  • urinary urgency;
  • difficulty starting urination;
  • interrupted urinary flow;
  • a sensation of incomplete bladder emptying;
  • pelvic muscle fatigue; and
  • occasionally worsening leakage later in the day as the muscles tire.

A healthy pelvic floor needs to be able to contract strongly and relax completely.

Continence does not require walking around all day with the pelvic floor permanently switched on.


How Do I Know When I Am Doing Enough?

Your programme is probably adequate when you can:

  • identify the pelvic floor reliably;
  • contract it without excessive abdominal or buttock activity;
  • maintain several controlled contractions without losing strength;
  • completely relax between contractions;
  • activate the muscles quickly before coughing or lifting; and
  • progressively incorporate pelvic floor control into normal activities.

Progress after prostatectomy is often better measured by continence rather than the number of exercises performed.

Useful measures include:

  • number of pads used each day;
  • degree of pad wetness;
  • a 24-hour pad-weight test;
  • leakage during walking or exercise;
  • ability to remain dry overnight;
  • ability to reach the toilet without leakage; and
  • changes over several weeks rather than from one day to the next.

When Should Exercises Restart After Surgery?

Follow the instructions given by your surgeon.

Pelvic floor contractions are usually stopped while the urinary catheter is in place.

Training can generally recommence after catheter removal once your surgical team considers it appropriate. European guidance notes that pelvic floor muscle training is commonly started approximately 7–10 days after catheter removal, although individual postoperative protocols vary.

Early exercises should be gentle.

This is not the time to test how hard you can squeeze.

As healing progresses, the programme can gradually move from basic contractions to functional training while standing, walking, coughing, lifting and exercising.


What Should I Expect After the Catheter Comes Out?

The first few days can be confronting.

Some men have relatively little leakage immediately. Others experience considerable leakage, particularly when:

  • standing;
  • walking;
  • coughing;
  • exercising;
  • getting out of a chair; or
  • becoming tired later in the day.

This does not necessarily predict the final outcome.

Continence often improves substantially during the first weeks and months following radical prostatectomy.

Recovery is a marathon measured in millilitres rather than kilometres.


How Successful Is Pelvic Floor Physiotherapy?

This question is more complicated than it initially appears.

Urinary continence frequently improves naturally following prostatectomy, making it difficult for studies to separate the effect of pelvic floor physiotherapy from normal postoperative recovery.

The research is consequently mixed.

The European Association of Urology notes that systematic reviews and trials suggest pelvic floor muscle training can shorten the time to continence recovery, although the evidence regarding supervised training, biofeedback and additional therapies remains inconsistent.

For example, one randomised study cited by the EAU compared supervised physiotherapist-directed pelvic floor training with verbal and written instructions. At 12 months, complete pad-free continence was reported in 65.2% of the supervised group versus 31.6% of the comparison group. This result should not be interpreted as the expected success rate for every patient, because continence definitions, surgical techniques and rehabilitation programmes differ considerably between studies.

A 2023 Cochrane review was considerably more cautious. After reviewing 25 trials, the authors concluded that uncertainty remains regarding the magnitude of benefit from conservative treatments because studies vary considerably in their techniques, combinations of treatments and methodological quality.

The practical message is therefore:

Pelvic floor rehabilitation is an important first-line treatment and may accelerate recovery, but it cannot guarantee continence.


What If Pelvic Floor Exercises Are Not Working?

Persistent leakage does not automatically mean you need to exercise harder.

If continence is failing to improve, the first question should be:

Why am I leaking?

Post-prostatectomy urinary incontinence may result from:

  • weakness of the urinary sphincter;
  • bladder overactivity;
  • urinary urgency;
  • incomplete bladder emptying;
  • bladder-neck or urethral narrowing;
  • a combination of stress and urgency incontinence; or
  • less commonly, other urinary tract problems.

The AUA guideline emphasises distinguishing stress incontinence, where leakage occurs with coughing, walking, lifting or exertion, from urgency incontinence, where leakage accompanies a sudden compelling desire to urinate.

No amount of extra squeezing will correct every one of these problems.


When Should Further Investigation Be Considered?

Further assessment may be appropriate when urinary leakage is:

  • severe;
  • worsening rather than improving;
  • associated with difficulty urinating;
  • associated with significant urgency or frequency;
  • persistent despite appropriate rehabilitation; or
  • sufficiently troublesome that surgical treatment is being considered.

Assessment may include:

Bladder diary

Records fluid intake, urinary frequency, urinary volumes and leakage episodes.

Pad-weight testing

Provides an objective measurement of the amount of urine being lost.

Urinary flow measurement and bladder ultrasound

Can identify poor urinary flow or incomplete bladder emptying.

Cystoscopy

May be recommended when urethral or bladder-neck pathology is suspected.

Urodynamic studies

Can sometimes help distinguish sphincter weakness from bladder dysfunction when the cause of persistent leakage is uncertain or before further treatment.


What Alternatives Are Available if Physiotherapy Is Not Enough?

Pelvic floor rehabilitation is only one part of managing post-prostatectomy incontinence.

Lifestyle and bladder strategies

These may include:

  • appropriate fluid intake;
  • reducing excessive caffeine;
  • avoiding constipation;
  • weight management where appropriate;
  • bladder training;
  • management of urinary urgency; and
  • modifying activities that provoke significant leakage during early recovery.

Continence pads

Modern male continence pads provide discreet protection while continence is recovering.

Using pads does not mean rehabilitation has failed. They are simply a tool for allowing normal activity during recovery.

Penile compression devices

A penile clamp can temporarily reduce leakage in selected men, although these devices must be fitted and used correctly and released regularly to avoid excessive pressure or tissue injury.

Medication

Medication does not generally correct true post-prostatectomy sphincter weakness.

However, medication may be useful when overactive bladder or urinary urgency contributes significantly to leakage.

Biofeedback

Biofeedback can help some patients understand whether they are contracting the correct muscles and how effectively they are doing so.

Electrical stimulation

Electrical stimulation has also been investigated. Some studies suggest an early benefit when combined with pelvic floor training, although evidence remains inconsistent.


When Is Surgery Considered?

A small proportion of men continue to experience significant stress urinary incontinence despite adequate healing and rehabilitation.

If the leakage remains bothersome, further treatment should be discussed rather than simply continuing increasingly intensive pelvic floor exercises indefinitely.

The two principal surgical options are:

Male Sling

A male sling supports and repositions the urethral continence mechanism.

It is generally most suitable for selected men with mild to moderate stress urinary incontinence and adequate residual sphincter function.

Results tend to be less favourable when incontinence is severe. The AUA guideline specifically notes that male sling outcomes are poorer in men with severe sphincteric incontinence.

Artificial Urinary Sphincter

The artificial urinary sphincter (AUS) remains an important treatment for moderate to severe post-prostatectomy stress urinary incontinence.

A fluid-filled cuff is placed around the urethra and controlled by a small pump positioned within the scrotum. The patient operates the pump when he wishes to urinate.

Both male sling surgery and artificial urinary sphincter implantation can significantly reduce pad use and improve quality of life in appropriately selected men.


When Should I Stop Pelvic Floor Rehabilitation?

There is rarely a precise finishing date.

Once continence has returned and pelvic floor control is good, intensive rehabilitation can usually be reduced.

Many men transition from a rehabilitation programme to a simple maintenance programme, incorporating occasional pelvic floor exercises and functional contractions during activities that generate abdominal pressure.

If you are completely dry, have good pelvic floor control and can cough, lift and exercise without leakage, performing increasingly large numbers of exercises is unlikely to provide additional benefit.

The goal is not to become a professional Kegel athlete.

The goal is normal function.


The Bottom Line

Pelvic floor rehabilitation is an important component of recovery following radical prostatectomy.

Learning the technique before surgery can make it easier to identify and activate the correct muscles after the catheter is removed. Following surgery, a structured programme focusing on strength, endurance, rapid contractions, relaxation and functional activation may help accelerate the return of urinary control. Current evidence supports pelvic floor muscle training as part of postoperative management, while acknowledging that the precise additional benefit of intensive supervised physiotherapy remains uncertain.

Just as importantly, more is not always better. Persistent leakage should not automatically be treated with ever-increasing numbers of pelvic floor contractions.

If urinary incontinence remains troublesome despite appropriate rehabilitation, further assessment can determine whether the problem is persistent sphincter weakness, bladder dysfunction or another cause. Treatments ranging from bladder therapy and medication to a male sling or artificial urinary sphincter can then be considered.

A useful rule

Train the pelvic floor, don’t exhaust it.

Correct technique, consistency and functional control matter far more than the number of contractions performed.


This information is intended for general patient education and does not replace individual medical advice. The timing and intensity of pelvic floor rehabilitation should be discussed with your surgeon and/or a physiotherapist experienced in male pelvic health.

Come discuss this with your local Brisbane based Urologist, Dr Jo / Uro-Jo to assist in stopping the leak.

Active Surveillance for Prostate Cancer

Being diagnosed with prostate cancer does not always mean that treatment needs to start immediately.

Many prostate cancers grow very slowly and may never cause symptoms or threaten a man’s life. For carefully selected men, active surveillance allows the cancer to be closely monitored while avoiding, or at least delaying, treatments such as surgery or radiation therapy.

Importantly, active surveillance does not mean ignoring the cancer. It is a structured programme of PSA testing, clinical review, prostate MRI and, when appropriate, repeat prostate biopsy. If there are signs that the cancer is becoming more significant, treatment can be recommended while the disease is still potentially curable.

Current international guidelines consider active surveillance the preferred or standard management approach for most suitable men with low-risk localised prostate cancer, and it may also be considered in carefully selected men with favourable intermediate-risk disease.


What Is Active Surveillance?

Active surveillance is a management strategy for prostate cancer in which curative treatment is deliberately postponed while the cancer is carefully monitored.

The aim is simple:

Avoid unnecessary treatment and its potential side effects, without compromising the opportunity for cure if the cancer changes.

This is particularly relevant because prostate cancer behaves very differently from one man to another. Some cancers are aggressive and require treatment, while others may remain small and slow-growing for many years.

Australian patient guidance describes active surveillance as close monitoring of low-risk prostate cancer that is not causing symptoms, with treatment initiated if investigations indicate that the cancer is becoming more aggressive.


Who Qualifies for Active Surveillance?

Active surveillance is most commonly recommended for men with low-risk prostate cancer.

Typical features include:

  • Cancer confined to the prostate
  • Grade Group 1 / Gleason score 3+3=6
  • PSA generally less than 10 ng/mL
  • Clinical stage T1 to T2a
  • Relatively small volume of cancer on prostate biopsy
  • Favourable findings on multiparametric MRI
  • A PSA density that supports low-volume disease
  • No clinical or imaging evidence suggesting more aggressive cancer

The AUA/ASTRO risk classification defines low-risk disease as PSA below 10 ng/mL, Grade Group 1 and clinical stage T1–T2a. For these patients, active surveillance is recommended as the preferred management strategy.

However, no single number determines suitability. Age, general health, family history, MRI findings, PSA density, biopsy findings, life expectancy and personal preferences all contribute to the decision.


Can Men With Gleason 3+4 / Grade Group 2 Cancer Have Active Surveillance?

Sometimes.

Active surveillance is increasingly considered for carefully selected men with favourable intermediate-risk prostate cancer, particularly when there is only a small amount of Gleason pattern 4 disease.

The 2026 European Association of Urology guidelines support active surveillance for selected men with favourable Grade Group 2 cancer. Features favouring surveillance include a small amount of pattern 4 disease, PSA below 10 ng/mL, limited tumour volume on biopsy and favourable imaging.

Similarly, AUA/ASTRO guidance suggests that favourable intermediate-risk patients with low PSA density, low tumour volume and a low percentage of Gleason pattern 4 disease may be considered for active surveillance.

These men require careful counselling because their risk of progression is higher than for men with Grade Group 1 disease.

Active surveillance is generally not appropriate for Grade Group 3 or higher-risk prostate cancer in men otherwise suitable for curative treatment.


What Happens Before Starting Active Surveillance?

The first step is making sure that the cancer really is suitable for surveillance.

Assessment may include:

PSA and PSA Density

PSA is considered together with prostate volume to calculate the PSA density.

A relatively low PSA density, commonly around less than 0.15 ng/mL/cc, provides additional reassurance in men being considered for surveillance, although it should not be interpreted as an absolute cut-off in isolation.

Multiparametric MRI of the Prostate

A high-quality multiparametric MRI (mpMRI) provides important information about:

  • The location of the tumour
  • Tumour size
  • Suspicious areas within the prostate
  • Possible extension outside the prostate
  • Areas that should be targeted during biopsy

MRI has become an important part of modern active surveillance, but MRI alone does not completely replace prostate biopsy.

Review or Confirmation of the Biopsy

The initial biopsy determines the Grade Group, Gleason score and volume of cancer.

Depending on how the original diagnosis was made, a confirmatory biopsy may be recommended. MRI-targeted biopsies can specifically sample suspicious lesions, while systematic or regional biopsies assess other areas of the prostate.


How Is Active Surveillance Performed?

Active surveillance is an ongoing programme rather than a single test.

The exact protocol varies according to the patient’s age, cancer characteristics, previous investigations and the treating urologist or institution.

A typical programme may include:

PSA Testing

PSA is usually measured approximately every 3–6 months initially, although intervals may become longer in men with very stable disease.

Current EAU guidance recommends PSA testing at least every six months, while Australian Cancer Council information describes PSA testing every 3–6 months.

The trend in PSA is usually more informative than one isolated reading.

An unexpected rise does not automatically mean that the cancer has progressed. PSA can fluctuate because of benign prostate enlargement, inflammation, infection and other factors.

For this reason, an unexpected PSA rise will often be repeated before further decisions are made.

Clinical Review

Regular appointments allow your urologist to review:

  • PSA changes
  • Urinary symptoms
  • General health
  • Examination findings
  • MRI results
  • Whether further investigation is required

A digital rectal examination may form part of surveillance, although its frequency can be individualised.

Repeat Prostate MRI

Repeat mpMRI may be performed periodically or earlier if PSA or other findings become concerning.

MRI allows comparison with previous scans to determine whether a lesion is:

  • Stable
  • Increasing in size
  • Becoming more suspicious
  • Showing features suggesting progression

Importantly, a change on MRI will often lead to a repeat biopsy rather than automatically triggering treatment. The EAU recommends confirming suspected histological progression before changing treatment strategy where appropriate.

Repeat Prostate Biopsy

Repeat biopsy remains an important component of active surveillance.

The frequency varies according to individual risk, previous MRI and biopsy findings and the surveillance protocol being followed.

The biopsy may involve:

  • Targeted biopsy of an MRI abnormality
  • Systematic sampling
  • A combination of targeted and regional/systematic biopsies

Modern surveillance programmes increasingly tailor biopsy frequency according to the individual’s risk rather than applying exactly the same schedule to every patient.


What Are We Looking for During Surveillance?

The purpose of surveillance is to identify reclassification or progression before the cancer becomes difficult to cure.

Your urologist will be looking for several possible warning signs.

These include:

Increasing cancer grade

For example, a cancer initially classified as Grade Group 1 may subsequently demonstrate a significant amount of Gleason pattern 4 disease.

Increasing cancer volume

More biopsy samples may contain cancer, or individual samples may contain a greater amount of cancer.

Changes on MRI

An existing lesion may enlarge or become more suspicious, or a new lesion may appear.

Persistent PSA changes

A progressively increasing PSA, particularly when accompanied by increasing PSA density or concerning MRI findings, may trigger further investigation.

Clinical progression

Changes on examination or other investigations may suggest that the cancer is no longer behaving as expected.


When Should Active Surveillance Stop?

Active surveillance should generally continue for as long as the cancer remains suitable for surveillance and curative treatment remains relevant.

The decision to move to treatment should ideally be based on the overall picture rather than PSA alone.

Treatment may be recommended when there is:

  • Significant upgrading of the cancer on repeat biopsy
  • Increasing amounts of higher-grade cancer
  • Significant increase in tumour volume
  • Concerning progression on MRI confirmed by appropriate investigation
  • Evidence suggesting progression beyond the original low-risk category
  • A change in the patient’s preference after informed discussion

AUA/ASTRO guidance recommends that significantly higher-volume or higher-grade disease on surveillance biopsy should prompt discussion about definitive therapy.


What Happens If the Cancer Progresses?

The important concept behind active surveillance is that treatment has been postponed, not abandoned.

If investigations demonstrate clinically significant progression, curative treatment can be considered.

Depending on the man’s age, general health, cancer characteristics and preferences, options may include:

Radical Prostatectomy

Surgical removal of the prostate, increasingly performed using robotic-assisted radical prostatectomy.

Focal therapy

Nanoknife electroporation

ProFocal laser ablation

Radiation Therapy

Options may include:

  • External beam radiation therapy
  • Stereotactic radiation therapy in appropriate patients
  • Brachytherapy in selected cases
  • Radiation combined with hormonal therapy where clinically indicated

Other Selected Treatments

In carefully selected circumstances, other approaches may be discussed. The evidence for focal ablative therapies remains less mature than that for established treatments such as surgery and radiation therapy, and suitability needs individual assessment.


What Are the Benefits of Active Surveillance?

For appropriately selected men, the major advantage is avoiding treatment that may never have been necessary.

Avoiding or Delaying Treatment Side Effects

Radical treatment can potentially cause:

  • Urinary incontinence
  • Erectile dysfunction
  • Ejaculatory changes
  • Urinary symptoms
  • Bowel symptoms following some forms of radiation therapy

Active surveillance allows men to maintain their existing urinary, sexual and bowel function for longer.

Maintaining Quality of Life

Many men can continue normal work, exercise, travel and sexual activity without the recovery period or functional consequences associated with immediate treatment.

Avoiding Overtreatment

Some low-risk prostate cancers may never become clinically significant during a man’s lifetime.

Treating every prostate cancer immediately would therefore expose some men to treatment complications without providing a meaningful survival advantage.

Treatment Remains Available

Active surveillance preserves the opportunity for curative treatment if the cancer subsequently demonstrates significant progression.

Long-term outcomes from well-conducted active surveillance programmes are reassuring. The EAU reports 10-year prostate cancer-specific survival rates of approximately 98–100% in active surveillance cohorts, although outcomes depend on appropriate patient selection and follow-up.


What Are the Risks of Active Surveillance?

Active surveillance is not completely risk-free.

The Cancer May Progress

Some cancers initially thought to be low risk will subsequently demonstrate more aggressive features.

In fact, a significant proportion of men are eventually reclassified during long-term surveillance and may proceed to treatment.

The Initial Biopsy May Underestimate the Cancer

A prostate biopsy samples only part of the prostate.

Occasionally, higher-grade cancer may already be present but was not captured during the original biopsy. Modern MRI and targeted biopsy techniques help reduce this risk but cannot eliminate it completely.

Small Risk of Losing the Optimal Window for Treatment

This is one of the main reasons that regular follow-up is essential.

In appropriately selected men who comply with structured surveillance, the risk is low, but surveillance must be active rather than passive.

Repeat Investigations

Active surveillance may involve:

  • Repeated blood tests
  • MRI scans
  • Urology appointments
  • Repeat prostate biopsies

Biopsies can cause discomfort, bleeding and infection, although contemporary transperineal biopsy techniques can substantially reduce the risk of serious infection.

Psychological Impact

Some men find living with untreated cancer surprisingly easy. Others find it difficult.

Anxiety may occur around:

  • PSA tests
  • MRI scans
  • Repeat biopsies
  • Waiting for results
  • Concern that the cancer may be progressing

For some men, the psychological burden becomes an important factor when deciding whether to remain on surveillance.


Active Surveillance Is Not the Same as Watchful Waiting

These terms are sometimes confused, but they describe different approaches.

Active surveillance is generally used for men with potentially curable prostate cancer. The cancer is actively monitored, with the intention of offering curative treatment if clinically significant progression occurs.

Watchful waiting is more commonly used in older men or men with significant other medical conditions where prostate cancer is unlikely to affect life expectancy. Monitoring is less intensive, and treatment is generally introduced to control symptoms rather than with the intention of cure.


Does Active Surveillance Mean Doing Nothing?

No.

This is perhaps the most important misconception about active surveillance.

A better description might be:

“Treatment if and when it becomes necessary.”

The cancer is being monitored carefully so that unnecessary treatment can be avoided while retaining the opportunity to intervene if its behaviour changes.

For the right patient, this can provide an excellent balance between cancer control and preservation of quality of life.


The Bottom Line

Active surveillance has become an established standard of care for appropriately selected men with low-risk prostate cancer and can also be considered for some men with carefully selected favourable intermediate-risk disease.

The decision should take into account:

  • PSA and PSA density
  • Grade Group and Gleason score
  • Amount of cancer found on biopsy
  • MRI findings
  • Clinical stage
  • Age and life expectancy
  • General health
  • Family and genetic risk factors
  • Personal preferences

Most importantly, active surveillance requires a partnership between the patient and his urologist.

The goal is not simply to avoid treatment.

The goal is to avoid treatment that is unnecessary, while identifying the point at which treatment becomes worthwhile.


This information is intended for general education and does not replace individual medical advice. Recommendations for prostate cancer management should be based on a detailed assessment of the individual patient, pathology, PSA results, imaging, general health and personal preferences.

Come chat with your friendly Brisbane Based Urologist, Dr Jo Schoeman, to discuss this option with you

Robotic-Assisted Radical Prostatectomy for Prostate Cancer

Understanding Robotic Prostate Cancer Surgery

A diagnosis of prostate cancer brings with it several important decisions. For men with cancer that is confined to the prostate, or selected cancers that have extended just beyond it, radical prostatectomy remains an established curative treatment option.

Robotic-assisted radical prostatectomy (RARP) is a minimally invasive approach in which the prostate and seminal vesicles are removed using a robotic surgical system. Depending on the characteristics of the cancer, lymph nodes in the pelvis may also be removed.

The robotic system does not perform the operation independently. Every movement is controlled by the surgeon. The technology provides magnified three-dimensional vision and highly manoeuvrable instruments, allowing precise dissection within the confined space of the male pelvis.

Compared with traditional open surgery, robotic-assisted surgery generally offers smaller incisions, less blood loss, a shorter hospital stay and faster early recovery. Importantly, however, the experience and skill of the surgeon remain more important than the particular surgical platform used.


Who May Benefit from Radical Prostatectomy?

Radical prostatectomy is most commonly considered for men with localised prostate cancer who have a sufficiently long-life expectancy to benefit from definitive treatment.

It may also form part of treatment for selected men with locally advanced or higher-risk prostate cancer, sometimes combined with additional treatments such as radiotherapy or androgen deprivation therapy.

The decision is individual and takes into account:

  • PSA level and PSA history
  • Prostate biopsy results and Grade Group/Gleason score
  • Clinical stage of the cancer
  • MRI findings
  • PSMA PET/CT or other staging investigations when indicated
  • Age and general health
  • Other medical conditions
  • Baseline urinary function
  • Baseline erectile and sexual function
  • Expected life expectancy
  • Patient preferences regarding cancer control and treatment side effects

For some men with low-risk prostate cancer, active surveillance may be preferable to immediate surgery. Radiotherapy is also an important alternative to surgery for many patients.

The objective is therefore not simply to determine whether an operation can be performed, but whether surgery represents the most appropriate treatment for that individual patient.


When May Surgery Not Be Appropriate?

There are relatively few absolute contraindications to robotic prostatectomy, but surgery may not be the preferred treatment when the potential risks outweigh the expected benefits.

Examples include:

  • Significant medical illness making general anaesthesia or major surgery unsafe
  • Limited life expectancy from other health conditions
  • Some cases of metastatic prostate cancer where systemic therapy is the principal treatment
  • Situations where another treatment offers a better balance between cancer control and quality of life
  • Large BMI, requiring a weight loss program prior to surgery

Previous abdominal or pelvic surgery, obesity, a very large prostate or previous prostate procedures may make robotic surgery technically more challenging, but they are not necessarily absolute contraindications.

Previous pelvic radiotherapy can make surgery substantially more complex and may increase the risk of complications. Such cases require careful individual assessment.


What Happens During Robotic Radical Prostatectomy?

Several small incisions are made in the abdomen through which robotic instruments and a camera are introduced.

The prostate and seminal vesicles are carefully separated from surrounding structures and removed. The bladder is then reconnected to the urethra, creating a new join called the vesicourethral anastomosis.

A urinary catheter is left across this join while it heals.

For men with intermediate- or high-risk prostate cancer, a pelvic lymph node dissection may also be recommended depending on the estimated likelihood of lymph node involvement.

One of the most important decisions made before and during surgery concerns the nerves responsible for erections.


Nerve-Sparing Versus Non-Nerve-Sparing Surgery

Running immediately alongside the prostate are delicate neurovascular structures that contribute to erectile function.

Whenever oncologically safe, the surgeon may attempt to preserve these nerves.

Bilateral nerve sparing

Both neurovascular bundles are preserved where the cancer characteristics and anatomy allow.

This offers the greatest opportunity for recovery of natural erections, particularly in younger men who had good erectile function before surgery.

Unilateral nerve sparing

Sometimes cancer is close to the nerves on one side of the prostate but appears safely separated on the other.

In this situation, the surgeon may preserve the neurovascular bundle on one side while performing a wider excision on the cancer-bearing side.

Non-nerve-sparing surgery

When cancer appears to extend close to or beyond the prostate adjacent to the neurovascular bundles, preserving these structures may compromise the completeness of cancer removal.

One or both bundles may therefore need to be removed.

Cancer control takes priority over preservation of erectile function.

Nerve-sparing is most appropriate when there is a reasonable expectation that the cancer can be completely removed while leaving the neurovascular tissue intact. Cancer Council Australia similarly notes that nerve-sparing surgery is most suitable when cancer is not close to these nerves and that erectile difficulties can still occur despite successful nerve preservation.

Modern MRI and biopsy information can help the surgeon plan whether nerve sparing is appropriate on each side of the prostate.


Preparing for Robotic Prostatectomy

Successful recovery begins before the operation.

Preparation may include a pre-operative medical and anaesthetic assessment, blood tests and review of medications. Blood-thinning medications may need to be stopped or modified under medical supervision.

Patients should maintain regular physical activity where possible and optimise conditions such as diabetes, hypertension and cardiovascular disease. Smoking cessation is strongly encouraged.

Patients should also understand what to expect regarding the urinary catheter, hospital stay, postoperative activity restrictions and recovery at home.

Pelvic Floor Physiotherapy Before Surgery

Pelvic floor rehabilitation should ideally begin before surgery rather than after the catheter is removed.

A consultation with a physiotherapist experienced in men’s pelvic health can help identify the correct muscles and teach an individualised exercise program.

The Prostate Cancer Foundation of Australia recommends at least one pre-operative assessment with a specialist men’s health pelvic floor physiotherapist to optimise urinary continence recovery.

The goal is not simply to perform hundreds of pelvic floor contractions. Correct technique, coordination, endurance and appropriate relaxation of the muscles are important.


What Happens After Surgery?

Hospitalisation following uncomplicated robotic prostatectomy is generally relatively short.

Patients are encouraged to mobilise soon after surgery to reduce the risk of blood clots and assist recovery.

A urinary catheter remains in place while the connection between the bladder and urethra heals. Catheter removal is commonly performed approximately one to two weeks after surgery, depending on the surgeon and individual circumstances.

Patients can gradually increase their activity after discharge but should avoid heavy lifting and strenuous exercise during the early healing period. Many patients return towards their usual activities over approximately six weeks.

The removed prostate is examined by a specialist pathologist. The final pathology provides important information including:

  • Cancer Grade Group
  • Pathological tumour stage
  • Whether cancer extends outside the prostate
  • Seminal vesicle involvement
  • Surgical margin status
  • Lymph node involvement, when lymph nodes have been removed

A PSA blood test is subsequently performed. Following successful radical prostatectomy, PSA should fall to a very low or undetectable level.

Ongoing PSA monitoring is essential.


Pelvic Floor Rehabilitation and Urinary Continence

Temporary urinary leakage is common after radical prostatectomy.

Leakage is usually most noticeable when coughing, sneezing, standing from a chair, exercising or lifting. Continence generally improves progressively over the following weeks and months and may continue improving for up to a year.

Once the catheter has been removed and the surgeon has given approval, pelvic floor exercises are recommenced.

A structured program may involve:

  • Correct pelvic floor muscle activation
  • Strength and endurance training
  • Functional contractions before coughing, lifting or standing
  • Bladder training where appropriate
  • Gradual return to exercise
  • Monitoring of pad usage and urinary leakage

Patients with troublesome persistent incontinence should undergo further assessment rather than simply being advised to continue exercises indefinitely.

For persistent stress urinary incontinence, surgical treatments including a male sling or artificial urinary sphincter may eventually be considered. Cancer Council notes that surgical treatment may be appropriate when significant incontinence fails to improve over approximately 6–12 months.


Erectile Function and Penile Rehabilitation

Erectile dysfunction is one of the most important potential consequences of radical prostatectomy.

Even when both neurovascular bundles are preserved perfectly, erections usually do not return immediately.

The nerves may temporarily lose function following surgery because of manipulation, inflammation and changes in their blood supply. Recovery can take months and sometimes several years. Cancer Council Australia notes that erectile function can continue improving for up to three years after prostate cancer treatment.

Recovery depends on several factors including:

  • Age
  • Erectile function before surgery
  • Cardiovascular health
  • Diabetes and other medical conditions
  • Smoking
  • Whether one or both nerves could be preserved
  • Extent of the cancer
  • Surgical factors

What Is Penile Rehabilitation?

Penile rehabilitation aims to maintain penile tissue health while the nerves recover and to assist patients in returning to satisfactory sexual function.

Treatment is individualized and may include:

PDE5 inhibitor tablets

Medications such as sildenafil or tadalafil increase blood flow to the penis and may be introduced following surgery when clinically appropriate.

They are more likely to produce erections when functional nerve pathways remain.

Vacuum erection device

A vacuum erection device draws blood into the penis mechanically. Regular use may help maintain penile tissue health and can also provide erections for sexual activity.

Penile injection therapy

Intracavernosal injections can produce erections independently of normal nerve signalling and can be particularly useful when tablets are ineffective during the early recovery period.

Penile prosthesis

For men with persistent erectile dysfunction who have not achieved satisfactory results with less invasive therapies, implantation of a penile prosthesis can provide a reliable long-term solution.

Cancer Council Australia recommends discussing penile rehabilitation before and after treatment and describes tablets, vacuum devices, injections and penile implants among the available treatment options.

Sexual rehabilitation should ideally be discussed before surgery, so that the patient and partner understand what changes to expect and what treatment options are available afterwards.


Changes to Orgasm, Ejaculation and Fertility

Radical prostatectomy permanently changes ejaculation.

Because the prostate and seminal vesicles are removed and the vas deferens are divided, semen is no longer produced during orgasm.

Men can usually still experience orgasm, but it is a dry orgasm.

Some men describe altered orgasmic sensation, and a small proportion experience discomfort or urinary leakage during orgasm.

Natural fertility is lost following radical prostatectomy. Men who may wish to father children in the future should therefore discuss sperm banking before treatment.


Possible Complications of Robotic Radical Prostatectomy

Most patients recover without major complications, but radical prostatectomy remains major pelvic surgery.

Potential complications include:

Bleeding

Blood loss is generally lower with robotic surgery than traditional open surgery, although significant bleeding or transfusion is still possible.

Infection

Urinary, wound or other infections can occur and may require antibiotics.

Blood clots

Deep vein thrombosis and pulmonary embolism are uncommon but potentially serious complications. Early mobilisation and, where indicated, compression devices or anticoagulant medication help reduce this risk.

Urinary leakage

Stress urinary incontinence is common initially and usually improves progressively.

Persistent significant leakage should be assessed by a urologist and may eventually require a male sling or artificial urinary sphincter.

Erectile dysfunction

This is managed through a structured sexual and penile rehabilitation program using medication, vacuum therapy, injection therapy or, where appropriate, penile prosthesis surgery.

Urine leak from the bladder-urethral join

Occasionally the new connection between the bladder and urethra takes longer to heal. The urinary catheter may simply need to remain in place for longer.

Bladder neck contracture or urethral narrowing

Scar tissue can occasionally narrow the urinary passage and cause a weak urinary stream or difficulty emptying the bladder. Further investigation and endoscopic treatment may be required.

Lymphocele

Following pelvic lymph node dissection, lymphatic fluid can occasionally collect within the pelvis. Small collections may resolve without treatment, while larger or symptomatic collections may require drainage.

Injury to adjacent structures

Damage to structures such as the rectum, ureters, blood vessels or bowel is uncommon but recognised and may require immediate repair or further treatment.


What If Cancer Is Found at the Surgical Margin?

The pathology report determines whether cancer cells extend to the edge of the removed specimen. This is called a positive surgical margin.

A positive margin does not automatically mean that prostate cancer will return.

Management depends on the final pathology, PSA results and other risk factors. Some patients can be safely monitored, while others may benefit from additional treatment.

If PSA remains detectable after surgery or subsequently begins to rise, investigations and salvage radiotherapy, sometimes combined with hormone therapy, may be considered.

Regular PSA surveillance therefore remains an essential part of prostate cancer care after surgery.


Balancing Cancer Control and Quality of Life

Robotic radical prostatectomy is not simply an operation to remove the prostate. Successful treatment involves three overlapping goals:

Cancer control
Complete removal of the cancer remains the primary objective.

Urinary recovery
Early pelvic floor assessment and structured rehabilitation can assist recovery of continence.

Sexual recovery
Appropriate nerve preservation, where oncologically safe, combined with early penile rehabilitation can maximise the opportunity for recovery of sexual function.

These priorities sometimes compete with one another. In particular, aggressive nerve preservation should never compromise cancer clearance.

For this reason, treatment should be tailored to the individual patient, the individual cancer and even the individual side of the prostate.


Questions to Ask Your Urologist

Before deciding on robotic radical prostatectomy, useful questions include:

  • Is surgery the best treatment for my particular prostate cancer?
  • What alternatives should I consider?
  • Is my cancer suitable for nerve-sparing surgery?
  • Can both nerves be preserved, or only one?
  • Will I require pelvic lymph node dissection?
  • What is my individual risk of urinary incontinence?
  • What is my likelihood of recovering erections?
  • When should I start pelvic floor physiotherapy?
  • What penile rehabilitation program do you recommend?
  • How long will the catheter remain in place?
  • When can I return to driving, exercise and work?
  • How will my PSA be monitored after surgery?
  • What happens if my PSA does not become undetectable or rises later?

The Importance of Individualized Treatment

No two prostate cancers, and no two patients, are exactly alike.

Robotic-assisted radical prostatectomy can provide excellent cancer control for appropriately selected men while offering the advantages of minimally invasive surgery. The best outcomes, however, depend on careful patient selection, appropriate surgical planning, experienced surgery and structured rehabilitation following treatment.

A comprehensive approach should therefore begin before the operation and continue well beyond discharge from hospital, incorporating cancer surveillance, urinary continence rehabilitation, sexual rehabilitation and attention to overall physical and psychological wellbeing.

This information is intended for general education and does not replace individual medical advice. Treatment recommendations should be discussed with your urologist, radiation oncologist and multidisciplinary prostate cancer team.

Come and have a chat to your local Brisbane Based Urologist, Dr Jo Schoeman, to discuss options for your prostate cancer.

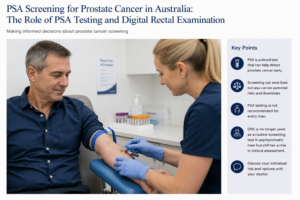
PSA Screening for Prostate Cancer in Australia: Should You Have a PSA Test?

Prostate cancer is one of the most commonly diagnosed cancers in Australian men. One of the difficulties with prostate cancer is that early prostate cancer usually causes no symptoms. By the time symptoms develop, some cancers may already have progressed beyond the prostate.

A simple blood test called the prostate-specific antigen (PSA) test can help identify men who may be at increased risk of prostate cancer. However, PSA testing is not a perfect cancer test and deciding whether to have regular PSA testing involves balancing the potential benefits of early diagnosis against the risks of unnecessary investigation and treatment.

In Australia, there is currently no national population-based prostate cancer screening program. Instead, PSA testing is based on an informed discussion between a man and his doctor, taking into account age, family history, overall health, life expectancy and personal preferences.


What is PSA?

PSA, or prostate-specific antigen, is a protein produced by prostate cells. A small amount normally enters the bloodstream and can be measured with a simple blood test.

An elevated PSA does not automatically mean that you have prostate cancer.

PSA can rise because of:

  • prostate cancer
  • benign enlargement of the prostate (BPH)
  • inflammation or infection of the prostate
  • urinary infection
  • recent ejaculation or sexual activity
  • recent instrumentation of the urinary tract
  • manipulation of the prostate.

Conversely, some men with prostate cancer can have a PSA within the expected range. PSA is therefore best considered a marker of prostate activity and prostate cancer risk rather than a test that diagnoses cancer.


Who Should Consider PSA Testing in Australia?

Current Australian guidance supports informed, individualized PSA testing rather than universal population screening.

For men at average risk who have been informed about the potential benefits and harms and decide to undergo regular testing, current RACGP guidance recommends offering PSA testing every two years between the ages of 50 and 69 years.

Men with a significant family history may be advised to start earlier. Depending on the strength of the family history, testing may begin from approximately 40–45 years of age and continue every two years to age 69.

A stronger family history includes having a father, brother or multiple close relatives diagnosed with prostate cancer, particularly when prostate cancer occurred at a younger age.

Other factors, including ancestry, genetic predisposition and an individual’s general health and life expectancy, may also influence the decision about when to begin testing.

Importantly, these recommendations apply to men without symptoms. Men with symptoms or clinical findings that raise concern about prostate cancer require individual assessment rather than simply entering a screening program.


What Does an Elevated PSA Mean?

An elevated PSA is not a diagnosis of prostate cancer.

For men aged 50–69 undergoing early detection testing, a PSA above 3.0 ng/mL generally prompts further assessment under current Australian guidance. An abnormal result will often be repeated because PSA levels can fluctuate and temporary elevations are common.

Depending on the PSA level, age, prostate size, family history and other risk factors, further assessment may include:

Repeat PSA → assessment of PSA trend and other risk factors → specialist review → prostate MRI → possible prostate biopsy

Modern prostate cancer assessment has changed substantially. An abnormal PSA no longer necessarily means proceeding directly to a prostate biopsy. Multiparametric MRI (mpMRI) can help identify suspicious areas within the prostate and assist the urologist in deciding whether biopsy is necessary.


The Potential Benefits of PSA Screening

The principal advantage of PSA testing is straightforward:

It may detect a significant prostate cancer while it is still curable.

Aggressive prostate cancer can spread to lymph nodes, bones and other organs. Once metastatic prostate cancer develops, treatment is generally aimed at controlling rather than curing the disease.

Regular PSA testing provides an opportunity to identify some clinically important cancers years before they would otherwise become apparent.

Large screening trials have produced differing results, which is one reason PSA screening remains controversial. European screening data have demonstrated a reduction in prostate cancer mortality associated with PSA-based screening, while other trials have shown less convincing mortality benefits.

For an individual man, therefore, the potential benefit is significant: early detection may identify an aggressive cancer at a stage when curative treatment remains possible.


What Are the Downsides of PSA Screening?

The difficulty is that prostate cancer is not one disease.

Some prostate cancers are aggressive and potentially life-threatening. Others grow extremely slowly and may never cause symptoms during a man’s lifetime.

PSA testing can detect both.

False-positive PSA results

An elevated PSA may lead to anxiety, repeat blood tests, MRI scans and sometimes biopsy even when no cancer is ultimately found.

Overdiagnosis

PSA testing can identify a prostate cancer that would never have caused illness or shortened the man’s life.

This is known as overdiagnosis.

Overtreatment

If an insignificant cancer is diagnosed and subsequently treated, the man can potentially experience treatment complications without gaining a meaningful survival benefit.

Potential consequences of prostate cancer treatment include:

  • erectile dysfunction
  • urinary incontinence
  • urinary symptoms
  • ejaculatory changes
  • bowel symptoms following some forms of radiotherapy.

This is one of the major reasons Australia does not currently have a universal PSA population-screening program.

Importantly, however, diagnosing prostate cancer does not automatically mean treating it.

Many men with low-risk prostate cancer are now managed with active surveillance, involving PSA monitoring, MRI and selective repeat biopsy. Treatment is reserved for evidence that the cancer is becoming more significant.


What Are the Implications of Not Having PSA Screening?

Choosing not to undergo PSA testing is also a legitimate decision, particularly after considering the benefits and disadvantages.

The advantage is avoiding the potential cascade of:

PSA testing → abnormal result → anxiety → MRI → biopsy → diagnosis of an insignificant cancer → possible unnecessary treatment.

However, there is another side to this decision.

Because early prostate cancer frequently produces no symptoms, a man who does not undergo PSA testing may remain unaware that he has prostate cancer.

For most men who never develop clinically significant disease, this causes no harm.

For a smaller group who develop aggressive prostate cancer, however, the first indication of the disease may occur after the cancer has grown substantially or spread beyond the prostate.

At that stage, the opportunity for curative treatment may have been reduced or lost.

The decision is therefore not simply:

“Do I want to know whether I have prostate cancer?”

A more useful question is:

“Given my age, health, family history and personal priorities, do the potential benefits of finding a significant prostate cancer early outweigh the potential harms of investigating and possibly diagnosing a cancer that may never affect me?”

This is why shared decision-making with your GP or urologist is important.


What About a Digital Rectal Examination?

The digital rectal examination, or DRE, involves a doctor gently inserting a gloved, lubricated finger into the rectum to examine the back surface of the prostate.

The doctor assesses the prostate for abnormalities such as:

  • unusual hardness
  • nodules
  • asymmetry
  • irregularity
  • loss of the normal contour of the gland.

Historically, DRE was routinely combined with PSA testing for prostate cancer screening.

This has changed.

DRE is no longer recommended as a routine screening test in asymptomatic men

Current Australian guidance states that DRE should not routinely be added to PSA testing for early detection in asymptomatic men in primary care.

There are several reasons.

A finger can examine only part of the prostate. Small cancers may not be palpable, and cancers in areas of the prostate that cannot be reached during examination can be missed. A normal DRE therefore does not exclude prostate cancer.

Conversely, benign prostate enlargement and other abnormalities can sometimes produce an abnormal examination.


Does DRE Still Have a Role?

Yes.

Not recommending DRE as a routine screening test does not mean that the examination has become obsolete.

A urologist may perform a DRE when assessing a man with:

  • an elevated or rising PSA
  • urinary symptoms
  • suspected prostate disease
  • an abnormal MRI
  • concern about locally advanced prostate cancer
  • other pelvic or rectal symptoms.

Occasionally, a prostate cancer may produce a distinctly hard or irregular prostate even when the PSA is not dramatically elevated. An abnormal DRE can therefore remain clinically important and may prompt further investigation. Cancer Council Australia notes that urologists will commonly perform DRE as part of prostate assessment even though GPs no longer routinely use it for screening asymptomatic men.

The key distinction is:

DRE has a role in clinical examination and investigation, but it is not recommended as a routine population-screening test in an otherwise well man undergoing PSA testing.


PSA Screening Is About Risk, Not Just a Number

One of the most important changes in modern prostate cancer detection is moving away from treating PSA as simply “normal” or “abnormal.”

A PSA result should be interpreted in context.

Your doctor or urologist may consider:

your age + PSA level + change in PSA over time + family history + prostate size + symptoms + examination findings + MRI findings + overall health

Together, these provide a much more meaningful assessment of prostate cancer risk than a single PSA result.


Should I Have a PSA Test?

There is no single answer that is appropriate for every man.

For a healthy man in the appropriate age group, particularly someone with a family history of prostate cancer, the potential benefit of identifying an aggressive cancer while it remains curable may be important.

For an older man with substantial medical problems or limited life expectancy, the likelihood that PSA screening will provide meaningful benefit becomes considerably smaller. Current Australian guidance advises against PSA testing in men whose life expectancy is likely to be less than approximately seven years because a mortality benefit from early detection is unlikely to occur within that period.

The decision should therefore be individual rather than automatic.


The Bottom Line

PSA testing can save lives by detecting clinically significant prostate cancer at an earlier and potentially curable stage, but it can also detect cancers that would never have caused harm.

Australia therefore does not currently operate a universal PSA screening program. Instead, men are encouraged to make an informed decision about PSA testing after discussing their individual risk and the potential benefits and harms with their doctor.

For men who choose screening, current Australian guidance generally supports PSA testing every two years from age 50–69 for men at average risk, with earlier testing considered for men with a significant family history.

A digital rectal examination is no longer recommended as a routine addition to PSA screening in asymptomatic men, but it remains an important component of specialist prostate assessment in selected circumstances.

Concerned about your prostate cancer risk?

If you are considering PSA testing, have a family history of prostate cancer, have noticed a change in your PSA, or have urinary symptoms, discuss your individual risk with your GP or urologist.

Early detection should not simply be about finding more prostate cancers. The goal is to identify the cancers that matter, at a time when something useful can still be done about them.

This information is intended for general education and does not replace individual medical advice. Recommendations may differ according to your age, family history, medical conditions and previous PSA results.

Further information

Australian patient information and guidance are available from Cancer Council Australia: Prostate cancer screening and early detection and the RACGP Guidelines for preventive activities in general practice.

Contact your friendly Brisbane based Urologist, Dr Jo Schoeman, to discuss this with you. Don’t ignore something you can have control over.

Fascia Lata Allograft as a Mid-Urethral Sling for Female Stress Urinary Incontinence

A “new/revamped” kid on the block – Fascia Lata Allograft: A biological alternative to synthetic mesh

Stress urinary incontinence (SUI) is one of the most common forms of urinary incontinence in women. It occurs when urine leaks with activities that increase abdominal pressure, such as coughing, sneezing, laughing, exercising, lifting or running.

For women whose symptoms remain troublesome despite pelvic floor muscle training and appropriate conservative treatment, surgical treatment can provide substantial and durable improvement.

For many years, the mid-urethral sling has been one of the most effective minimally invasive surgical treatments for SUI. Synthetic mesh mid-urethral slings remain available in Australia and have extensive evidence supporting their effectiveness. However, concerns surrounding synthetic mesh have led many women to ask whether there is a biological alternative.

One such option is a fascia lata allograft, including the fascia lata allograft supplied by Samson Medical Technologies in Australia.

The important distinction is that the Samson product is not a synthetic mesh. It is human donor fascia lata, processed for use as a biological graft. Samson describes its current fascia lata allograft as 100% human-derived, without storage media, non-irradiated and processed using Super Critical CO₂ technology.

However, there is an important caveat: the published clinical evidence for fascia lata allografts in SUI largely relates to earlier cadaveric fascia products and pubovaginal sling techniques, rather than Samson’s current specific product. Therefore, the historical allograft results should not be presented as if they were Samson-specific clinical trial results.


What is an allograft sling?

An allograft is tissue obtained from a human donor rather than from the patient herself.

Traditional biological pubovaginal slings have commonly used the patient’s own rectus fascia or fascia lata. This provides a strong, durable biological support but requires an additional incision to harvest the patient’s tissue.

An allograft avoids this donor-site surgery.

The fascia lata is positioned beneath the urethra and secured to provide a supportive platform. During coughing, sneezing or physical exertion, the urethra is compressed against this support, helping prevent urine leakage.

The concept is therefore quite different from a synthetic polypropylene mid-urethral sling. Instead of leaving a permanent synthetic mesh implant, the surgeon is using processed human connective tissue.

Samson currently supplies fascia lata allografts in several dimensions, including 20 × 100 mm and 20 × 120–140 mm configurations.


How effective are fascia lata allografts?

This is where the evidence requires some careful interpretation.

There is a substantial historical literature examining cadaveric fascia lata as a sling material, but the results have been inconsistent.

Early studies

Some early studies reported excellent short-term results.

One study of 26 women treated with solvent-dehydrated cadaveric fascia lata reported that 77% were completely dry and 92% used one pad or fewer per day at a mean follow-up of 15 months.

Another series of 31 women reported complete resolution of SUI in 93% at approximately one year.

A larger series of 104 women using freeze-dried, non-irradiated cadaveric fascia lata demonstrated substantial reductions in pad use, although the study’s follow-up was relatively short.

These studies created considerable enthusiasm for allograft tissue because it offered the advantages of a biological sling without the morbidity of harvesting the patient’s own fascia.

But there was also a warning signal

Other studies produced considerably less encouraging results.

A study of 18 women using solvent-dehydrated, gamma-irradiated fascia lata found that 27.8% experienced significant failure, with recurrent incontinence occurring within 3–6 months. The authors concluded that this particular allograft material was unreliable.

A subsequent comparative study of 71 women found a concerning difference in objective urodynamic recurrence: urodynamic stress incontinence was present in 41.7% of women who received Tutoplast allograft compared with none of those receiving autologous fascia lata at follow-up. Patient-reported outcomes, however, were more favourable.

Other series have reported much better results. In a 134-patient comparison, 63 women received allograft fascia and 71 received autologous fascia. There was no statistically significant difference in overall cure of stress and urge incontinence at approximately two years, while the allograft group experienced less postoperative pain and disability.

What does this mean?

The historical evidence suggests that allograft fascia can work well, but the durability and consistency of older allograft products were variable.

This variability is important when discussing the Samson allograft. There is currently insufficient published comparative evidence to state that the Samson product has a specific cure rate such as 80%, 90% or 95%.

The more scientifically defensible statement is:

Samson fascia lata provides a contemporary biological allograft option for sling surgery, but Samson-specific long-term comparative clinical outcome data are still developing.

That distinction is important when counselling patients.


How does Samson allograft differ from older allografts?

The earlier allograft literature predominantly involved freeze-dried, solvent-dehydrated and/or gamma-irradiated cadaveric fascia lata.

The Samson product currently described by the manufacturer is different in its processing. Samson reports that its fascia lata is:

  • 100% human-derived
  • non-irradiated
  • supplied without storage media
  • processed using Super Critical CO₂ technology
  • available in several sizes.

The rationale behind modern tissue processing is to preserve the structural characteristics of the collagenous tissue while making the graft suitable for implantation.

Nevertheless, a different processing technology does not automatically establish superior clinical continence outcomes. Laboratory characteristics, tensile strength and histological appearance are not substitutes for long-term clinical trials.

This is one of the areas where future Australian outcome data will be particularly valuable.


How does an allograft compare with synthetic mid-urethral mesh?

Synthetic mid-urethral slings have the largest evidence base of any minimally invasive SUI operation.

A Cochrane review including 81 trials and more than 12,000 women found that more than 80% of women were cured or significantly improved following mid-urethral sling surgery, with good results maintained for up to five years.

Retropubic and transobturator approaches have broadly comparable effectiveness, although their complication profiles differ.

For example, retropubic slings have a higher risk of bladder perforation, whereas transobturator procedures have more groin pain. Vaginal mesh exposure is uncommon but recognised with both approaches.

The Australian situation

It is important to distinguish mid-urethral slings from transvaginal mesh used for pelvic organ prolapse.

The Australian TGA has removed certain transvaginal mesh products from the market, particularly mesh used for prolapse and single-incision mini-slings. However, mid-urethral sling devices for SUI remain approved in Australia.

Indeed, a 2026 Australian Government review concluded that mid-urethral sling devices should remain on the Prescribed List, with their existing listing unchanged.

Therefore, synthetic MUS should not simply be described as “banned mesh” in Australia. It remains an accepted treatment for appropriately selected women.

Potential advantages of an allograft

A biological fascia lata sling potentially offers:

Advantages

  • No synthetic polypropylene mesh
  • No fascial harvest from the patient’s abdomen or thigh
  • Avoidance of donor-site pain
  • Biological rather than permanent synthetic material
  • Potentially useful where avoidance of synthetic mesh is an important patient preference

Potential disadvantages

  • Less robust long-term evidence than synthetic MUS
  • Historical allograft studies have shown variable durability
  • It is still a surgical sling and can cause obstruction, urinary retention, infection, bleeding or pain
  • It requires more extensive dissection than a conventional MUS
  • It should not currently be marketed as proven superior to synthetic MUS

What about the Burch colposuspension?

The Burch colposuspension is the classic non-mesh surgical treatment for SUI.

Rather than placing a sling beneath the urethra, sutures are placed beside the bladder neck and proximal urethra and attached to supporting pelvic tissues.

It can be performed by open or laparoscopic surgery.

Long-term studies demonstrate that Burch colposuspension can be highly effective. One classic study found an 81.6% cure rate at 5–10 years.

More contemporary comparative data are reassuring. In a large study with more than 1,300 women and long-term follow-up, the proportion reporting no ongoing SUI was 83.0% after Burch colposuspension compared with 85.0% following retropubic MUS, with no significant difference.

However, Burch surgery is more invasive than a mid-urethral sling and is generally no longer the first surgical option for uncomplicated primary SUI.

It can nevertheless be an attractive option in selected women, particularly when avoiding synthetic mesh is important.


What about peri-urethral bulking agents?

Urethral bulking agents occupy a completely different part of the treatment spectrum.

A material is injected into the urethral wall around the bladder neck or proximal urethra to increase coaptation and improve continence.

In Australia, polyacrylamide hydrogel such as Bulkamid is an established example.

The major attraction is that it is substantially less invasive than sling surgery.

It can often be performed under local anaesthesia or sedation and has a relatively favourable safety profile.

The trade-off is effectiveness and durability.

A 2024 study of Bulkamid reported that at 12 months 69% of women described themselves as cured or improved, with 40% reporting cure, while 23% underwent subsequent treatment, including repeat Bulkamid injection or MUS.

Longer-term data are more modest. In a cohort of 357 women followed for a median of approximately 2.5 years, subjective cure was 30.9%, while 52.1% reported improvement. Minor adverse events occurred in 21%, with no serious adverse events attributed to the procedure.

Current guideline evidence therefore generally considers bulking agents less effective than MUS, Burch colposuspension or autologous fascial sling surgery, and repeat injections may be necessary.


Putting the options together

Treatment Approximate effectiveness Main advantages Main disadvantages
Samson fascia lata allograft sling Samson-specific long-term cure rate not yet established; historical allograft studies range widely Biological tissue; no synthetic mesh; no tissue harvest Limited contemporary comparative evidence; historical allograft durability concerns; surgical sling risks
Synthetic mid-urethral sling Generally >80% cure/improvement in medium-term evidence Minimally invasive, rapid recovery, extensive evidence Mesh-specific complications including exposure, pain and voiding dysfunction
Burch colposuspension Approximately 70–85% long-term continence in many series No vaginal mesh; durable native-tissue operation More invasive; longer recovery; risk of prolapse and voiding problems
Autologous fascial sling Generally high effectiveness, comparable with other established sling procedures No synthetic mesh; patient’s own tissue Requires tissue harvest; more postoperative morbidity
Bulking agent Lower cure rate, but meaningful improvement for many women Minimally invasive; useful for frail/high-risk patients or those avoiding sling surgery Less durable; repeat injections commonly required

The Australian Government’s own review of MUS specifically considered colposuspension, native-tissue pubovaginal slings and urethral bulking agents as important comparators.


Who might consider an allograft sling?

A fascia lata allograft may be particularly attractive for a woman who:

  • has objectively demonstrated SUI;
  • has failed appropriate conservative treatment;
  • wishes to avoid a permanent synthetic mesh implant;
  • does not want an abdominal or thigh incision to harvest her own fascia;
  • understands that the long-term evidence base for contemporary allograft products is smaller than that for synthetic MUS;
  • accepts that biological tissue does not eliminate the risks associated with sling surgery.

It may also have a role in selected women with recurrent SUI, particularly where previous synthetic mesh surgery makes another synthetic procedure unattractive. However, recurrent SUI is a more complex clinical situation and requires individual assessment.


The important question: is Samson allograft better than synthetic mesh?

At present, there is not enough evidence to say that it is.

The strongest evidence remains with synthetic mid-urethral slings. Their effectiveness has been demonstrated in thousands of women and across multiple randomised trials and systematic reviews.

The potential attraction of Samson fascia lata is different.

It offers a biological alternative for women who would prefer to avoid synthetic mesh while also avoiding the morbidity of harvesting their own fascia.

That makes it an interesting addition to the surgeon’s toolbox rather than a replacement for the established mid-urethral sling.

The key unanswered question is long-term durability.

Historical cadaveric allograft studies demonstrate that some allografts performed extremely well, while others experienced substantial early failure.

Consequently, contemporary prospective data specifically evaluating Samson’s processing technology, clinical continence outcomes, complications and durability would be valuable.


What should a woman expect from the procedure?

As with any continence operation, the goal is not simply to make a stress test negative. The aim is to improve the woman’s quality of life while preserving normal bladder emptying and sexual function.

Potential complications of sling surgery include:

  • temporary or persistent difficulty emptying the bladder;
  • urinary retention requiring catheterisation;
  • urinary tract infection;
  • bleeding or haematoma;
  • pain;
  • de novo urgency or worsening overactive bladder;
  • recurrent or persistent SUI;
  • vaginal wound problems;
  • infection;
  • rarely, injury to the bladder, urethra or surrounding structures.

Synthetic mesh has additional mesh-specific risks, including vaginal exposure/erosion and chronic pain. The TGA specifically requires information regarding complications such as severe chronic pain, groin pain and bladder perforation in the instructions for use of Australian MUS devices.

An allograft avoids synthetic mesh exposure, but it does not make the operation risk-free.


The bottom line

For a woman with bothersome stress urinary incontinence, there is no single operation that is right for everyone.

Synthetic mid-urethral slings remain the most extensively studied minimally invasive surgical treatment and have excellent success rates.

Burch colposuspension remains a durable non-mesh alternative, although it is more invasive.

Bulking agents offer the least invasive surgical option but generally have lower and less durable success rates.

Fascia lata allograft represents an intriguing middle ground: a biological sling that avoids both synthetic mesh and the need to harvest the patient’s own fascia.

The Samson allograft is particularly interesting because its contemporary processing differs from several of the older cadaveric fascia products that generated the historical literature. Samson describes its current graft as non-irradiated human fascia lata processed using Super Critical CO₂ technology.

However, the enthusiasm should be matched by scientific caution. The historical literature demonstrates that allografts can achieve good continence outcomes, but it also demonstrates that not all allograft materials have behaved identically over time.

For patients considering this option, the most accurate discussion is therefore not “this is a better sling than mesh.” It is:

“This is a biological alternative to synthetic mesh, with encouraging historical experience but less mature long-term clinical evidence for the contemporary product.”

As further Australian experience and prospective follow-up accumulate, Samson fascia lata allograft may become an increasingly useful option in the treatment of female stress urinary incontinence.

Important note

This article is intended for general information and does not replace an individual assessment by a urologist or uro-gynaecologist. The choice between conservative management, bulking agent, synthetic MUS, biological or autologous sling and Burch colposuspension depends on the type and severity of incontinence, previous surgery, urethral function, pelvic anatomy, patient preference and overall health.

Don’t suffer in silence: Come see your friendly Brisbane Urologist for advice.

Stress Urinary Incontinence in Women: Symptoms, Investigations and Treatment Options in Australia

Stress urinary incontinence (SUI) is one of the most common forms of urinary incontinence in women. It occurs when urine leaks because pressure inside the abdomen rises faster than the urethra and pelvic floor can close.

Coughing, sneezing, laughing, lifting, running, jumping and exercise can all trigger leakage. For some women the leakage is only a few drops; for others it can be substantial enough to interfere with exercise, work, intimacy and everyday life.

The good news is that SUI is treatable, and treatment can be tailored to the severity of symptoms, the woman’s lifestyle and preferences, previous surgery, pelvic floor function and other bladder symptoms.

What are the symptoms and signs of stress urinary incontinence?

The classic symptom is involunta

ry urine leakage with physical exertion.

Common triggers include:

  • Coughing or sneezing
  • Laughing
  • Getting up from a chair
  • Lifting children or heavy objects
  • Running or jumping
  • Exercise, particularly high-impact exercise
  • Sexual intercourse
  • Changes in position
  • Sports such as tennis, running or aerobics

Some women notice only occasional leakage, while others need pads every day.

Stress incontinence versus urgency incontinence

It is important to distinguish SUI from urgency urinary incontinence, where urine leakage follows a sudden, difficult-to-defer urge to urinate.

Many women have mixed urinary incontinence, with both stress and urgency leakage.

This distinction matters because the treatment strategy can be quite different. Treating the wrong component first can produce disappointing results.


How is stress urinary incontinence diagnosed?

For many women, the diagnosis can be made from the history and examination without an extensive battery of tests.

A specialist assessment usually includes:

1. Medical history

Your doctor will ask about:

  • The nature and severity of leakage
  • What activities trigger leakage
  • Urinary urgency and frequency
  • Night-time urination
  • Recurrent urinary tract infections
  • Previous pregnancies and childbirth
  • Menopause and hormonal symptoms
  • Previous pelvic or continence surgery
  • Pelvic-organ prolapse
  • Neurological conditions
  • Medications
  • Impact on exercise, work, social activities and sexual function

2. Bladder or voiding diary

A bladder diary records fluid intake, urinary frequency, urine volumes, urgency episodes and leakage over several days.

It can be surprisingly revealing. It helps determine whether the problem is predominantly stress leakage, urgency, excessive fluid intake, frequent small-volume voiding or a combination of these.

3. Physical examination

A pelvic examination can assess:

  • Pelvic organ prolapse
  • Pelvic floor muscle strength
  • Urethral mobility
  • Vaginal and vulval health
  • Atrophic changes associated with menopause
  • Evidence of previous surgery

A cough stress test may be performed with a comfortably full bladder. Leakage of urine through the urethra during coughing supports the diagnosis of stress urinary incontinence.

4. Urine testing

A urine test is often appropriate, particularly when there are symptoms suggesting infection, blood in the urine or other urinary abnormalities.

5. Measurement of residual urine

A bladder ultrasound can measure the amount of urine left after voiding. This is particularly useful if there are symptoms suggesting incomplete bladder emptying or voiding dysfunction.


Do I need urodynamic studies?

This is one of the most common questions asked by women considering treatment.

Not every woman with straightforward stress urinary incontinence requires urodynamics.

Urodynamic testing measures how the bladder, urethra and pelvic floor behave while the bladder fills and empties. It can determine whether leakage is associated with increased abdominal pressure, whether involuntary bladder contractions occur and whether there is evidence of obstruction or impaired bladder emptying.

Contemporary guidelines generally do not recommend routine urodynamics before surgery in women with uncomplicated, clinically demonstrable SUI because it has not been shown to improve surgical outcomes.

Urodynamics becomes particularly useful when:

  • The diagnosis is uncertain
  • There are significant urgency or other storage symptoms
  • Mixed urinary incontinence is present
  • Voiding dysfunction is suspected
  • There is significant pelvic organ prolapse
  • Previous continence surgery has failed
  • The symptoms and examination findings do not match
  • There is suspected intrinsic sphincter deficiency
  • The results may change the choice of treatment

In these situations, urodynamics can turn a clinical puzzle into a much clearer picture.


Treatment of stress urinary incontinence

Treatment is usually progressive, beginning with conservative measures and moving towards minimally invasive or surgical treatment when necessary.

The appropriate treatment depends on the severity of the leakage and, importantly, how much it bothers you.

1. Pelvic floor muscle training

Pelvic floor muscle training (PFMT) is generally the first-line treatment for SUI.

The pelvic floor muscles provide support to the bladder neck and urethra. Strengthening and correctly coordinating these muscles can significantly reduce leakage.

A structured program with a pelvic floor physiotherapist is preferable to simply being told to “do your Kegels”.

A good program may include:

  • Identification of the correct muscles
  • Strength training
  • Endurance training
  • Rapid contractions for coughs and sneezes
  • Coordination of the pelvic floor with movement
  • Techniques for managing leakage during exercise

Guidelines recommend supervised pelvic floor muscle training for at least three months as initial therapy for SUI.

The advantage is obvious: there is no incision, no anaesthetic and essentially no procedural risk.

The disadvantage is that it requires commitment, correct technique and time.


2. Lifestyle measures

Lifestyle modifications can make a meaningful difference, particularly when combined with pelvic floor rehabilitation.

These may include:

  • Weight reduction where appropriate
  • Optimizing fluid intake
  • Reducing excessive caffeine intake
  • Treating constipation
  • Addressing chronic coughing
  • Smoking cessation
  • Modifying high-impact exercise temporarily while rehabilitation is undertaken

These measures rarely “cure” significant anatomical SUI on their own, but they can reduce symptoms and improve the results of other treatments.


3. Continence pessary

A vaginal continence pessary can provide mechanical support to the urethra and bladder neck.

It may be particularly useful for women who:

  • Want to avoid surgery
  • Have leakage predominantly during exercise
  • Are awaiting surgery
  • Have coexisting pelvic organ prolapse
  • Want an additional treatment alongside pelvic floor rehabilitation

A pessary is fitted inside the vagina and can sometimes be removed and inserted by the patient.

Possible problems include vaginal irritation, discharge, discomfort and difficulty with insertion or removal. Regular review is important.


4. Vaginal oestrogen

For postmenopausal women with vaginal or genitourinary symptoms, local vaginal oestrogen may improve vaginal tissue health and urinary symptoms.

It is not a replacement for continence surgery when significant anatomical SUI is present, but it can be a useful component of treatment in appropriately selected women.


5. Urethral bulking injections

Urethral bulking involves injecting a material around the urethra to improve its ability to remain closed.

One example used clinically is polyacrylamide hydrogel.

The procedure is minimally invasive and can be attractive to women who:

  • Prefer to avoid sling surgery
  • Are poor surgical candidates
  • Have recurrent SUI after previous surgery
  • Want a relatively quick procedure

The trade-off is durability.

Bulking agents are generally less effective than sling procedures and repeat injections may be necessary. Their effectiveness can diminish with time.

Potential side effects include:

  • Temporary urinary urgency
  • Urinary tract infection
  • Difficulty emptying the bladder
  • Blood in the urine
  • Discomfort
  • Recurrent leakage
  • Need for repeat treatment

6. Mid-urethral sling

For women with bothersome SUI who have not obtained sufficient improvement from conservative treatment, a mid-urethral sling (MUS) is one of the most established surgical treatments.

The sling sits beneath the middle portion of the urethra and provides support when abdominal pressure rises.

Two principal approaches have been used:

Retropubic mid-urethral sling

The tape passes behind the pubic bone.

Mid-urethral slings have substantially reduced the morbidity and complexity of traditional continence surgery, with high rates of improvement and continence. Contemporary evidence suggests broadly similar effectiveness between retropubic and transobturator approaches, although their complication profiles differ.

Importantly, mid-urethral sling surgery is not the same as the transvaginal mesh products that were used for pelvic organ prolapse. The Australian regulatory position is different. Mid-urethral slings for SUI remain approved products in Australia, with approved devices subject to Class III medical-device requirements.


What are the risks of a mid-urethral sling?

Although most women do well, sling surgery is not risk-free.

Potential complications include:

  • Bleeding or haematoma
  • Infection
  • Bladder or urethral injury during insertion
  • Temporary or persistent difficulty passing urine
  • Urinary retention
  • New or worsening urgency
  • Recurrent stress incontinence
  • Pelvic, groin or suprapubic pain
  • Pain during sexual intercourse
  • Mesh exposure or erosion
  • Rarely, chronic pain or other mesh-related complications
  • Need for further surgery

The TGA specifically identifies complications including bladder or urethral injury, mesh exposure or erosion, voiding dysfunction, urinary retention, urgency and acute or chronic pain among the potential adverse outcomes associated with urogynaecological mesh.

The decision to use a sling should therefore involve an individual discussion about benefits, alternatives and risks rather than treating the operation as a one-size-fits-all solution.


7. Autologous fascial sling

For women who wish to avoid synthetic mesh, another established surgical option is an autologous fascial sling.

A strip of the woman’s own tissue, usually rectus fascia from the lower abdominal wall, is fashioned into a sling and placed beneath the bladder neck/urethra.

This avoids a synthetic implant.

It can be particularly useful in selected women with:

  • Severe stress incontinence
  • Intrinsic sphincter deficiency
  • Previous failed sling surgery
  • Previous mesh complications
  • A strong preference to avoid synthetic mesh

The disadvantages are that it is generally a more extensive operation, requires harvesting tissue and can have a higher risk of postoperative voiding dysfunction. Fascial harvest can also cause abdominal wound pain, infection, seroma or, rarely, hernia.


What about an allograft mid-urethral sling?

This is an important distinction.

An allograft is tissue obtained from another human donor, rather than tissue harvested from the woman herself. Historically, cadaveric fascia lata has been used to construct pubovaginal slings.

The attraction is obvious: it avoids harvesting the woman’s own rectus fascia and therefore avoids the additional abdominal wound associated with an autologous sling.

However, there is an important catch.

The evidence for allograft slings is considerably weaker than for modern mid-urethral synthetic slings or autologous fascial slings. This based on older studies and different mechanisms to prepare the graft.

Older studies of cadaveric fascia lata reported encouraging short-term outcomes, including reduced postoperative pain compared with harvesting autologous fascia. However, other studies reported substantial recurrence of stress incontinence, raising concerns about long-term durability.

Systematic evidence reviews have also concluded that the evidence supporting biological/allograft slings is limited and of low or very low certainty. In comparisons with synthetic slings, there has not been convincing evidence that cadaveric fascia lata provides a superior outcome.

For this reason, an allograft sling should not simply be regarded as a “mesh sling without mesh.”

Its role is much more selective.

Where available, it may be considered in carefully selected women who want to avoid synthetic mesh and would otherwise be candidates for a fascial sling, but the surgeon should explain the limitations of the evidence and uncertainty around long-term durability.

In Australia, the availability and regulatory status of any particular allograft product or technique should be confirmed with the treating surgeon and relevant institution. The TGA’s current approved urogynaecological mesh list specifically identifies approved devices for SUI, while not all historical mesh or biological products remain available.


8. Burch colposuspension

Burch colposuspension is a traditional operation in which sutures are placed to support the tissues around the bladder neck and urethra.

It can be performed through an abdominal approach, including laparoscopically or robotically in appropriately experienced centres.

It remains an important non-mesh surgical option, although it is more invasive than a mid-urethral sling.

Potential complications include:

  • Bleeding
  • Infection
  • Bladder injury
  • Postoperative urinary retention or voiding dysfunction
  • New urgency
  • Recurrent SUI
  • Pelvic or abdominal pain
  • Development or worsening of pelvic organ prolapse

Choosing the right operation

There is no single “best” operation for every woman.

The decision should take into account:

Consideration Why it matters
Severity of SUI Determines how much treatment is justified
Previous surgery May alter the choice of procedure
Intrinsic sphincter deficiency May favour a different surgical approach
Pelvic organ prolapse May require combined treatment
Urgency/mixed incontinence May affect expected outcome
Desire to avoid synthetic mesh Makes fascial procedures more relevant
Previous mesh complications May favour non-mesh options
General health Influences operative risk
Future pregnancies May influence timing and choice of surgery
Patient preference An essential part of shared decision-making

The aim is not simply to make the pad dry. The aim is to find the treatment that gives the woman the best balance between continence, bladder function, quality of life and procedural risk.


What happens after treatment?

Following continence surgery, women are generally reviewed to assess:

  • Continence
  • Urgency and frequency
  • Bladder emptying
  • Residual urine
  • Pelvic pain
  • Sexual function
  • Vaginal healing
  • Mesh exposure where a mesh sling has been used

If symptoms persist or recur, further investigation may be necessary. In women with failed previous SUI surgery, repeat urodynamics and specialist assessment can be particularly valuable.

Australia also has the Australasian Pelvic Floor Procedures Registry, which collects information about stress incontinence and pelvic floor procedures with the goal of improving quality and long-term safety.


The bottom line

Stress urinary incontinence is common, but it is not something women simply have to put up with.

Treatment ranges from pelvic floor physiotherapy and lifestyle modification through to pessaries, urethral bulking injections and surgery.

For women requiring surgery, options in Australia include mid-urethral sling procedures, autologous fascial sling surgery and colposuspension, with the appropriate choice depending on individual circumstances.

An allograft fascial sling is a more specialised option. Although it avoids harvesting the patient’s own fascia, the evidence base is considerably less robust than that for established mid-urethral sling and autologous fascial sling procedures. It should therefore be discussed as a selective option rather than assumed to be a routine alternative to synthetic mesh.

Most importantly, treatment should be individualised. A woman should understand not only the likelihood of becoming dry, but also the possibility of urgency, voiding problems, pain, recurrent incontinence and other procedure-specific complications before making a decision.

If urinary leakage is interfering with exercise, work, relationships or everyday life, an assessment by a GP, urogynaecologist, urologist or pelvic-floor physiotherapist is a good place to start.

This information is intended for education and does not replace an individual medical assessment. Treatment availability, device approvals and clinical recommendations can change, so patients should discuss the current options with their treating clinician.

Don’t suffer in silence. Come see what your Brisbane Urologist Uro-Jo can do for you.

Post-Prostatectomy Urinary Incontinence

Sources

Men’s Guide to Lower Urinary Tract Symptoms: What’s Causing Them and What Can Be Done?

Medical note: This is patient education rather than individual medical advice. The investigation and treatment approach should be tailored to the individual, particularly where there is haematuria, urinary retention, recurrent infection, neurological disease or concern about prostate cancer. The treatment information above reflects contemporary EAU guidance, including the 2026 guideline update.

Sources

Come see your friendly Brisbane Urologist, Uro-Jo, to discuss these options

Re-Thinking the “8 Glasses a Day” Rule in Subtropical Queensland

We have all heard the standard health advice: drink eight glasses of water a day for optimal health. But if you live in Brisbane, this generic advice might actually be working against your sleep quality, your energy levels, and your bladder health.

Living in a subtropical climate changes the rules of hydration, and local specialists are seeing the side effects of a well-intentioned but flawed approach to drinking water.

The Daytime Deficit and the Nighttime Flood

Because Brisbane summers are humid and warm, many active locals experience a subtle, ongoing fluid deficit throughout the work day. To compensate, a common habit has formed: chugging massive amounts of water after getting home from work or finishing an evening gym session.

While this technically hits your daily fluid target, it creates an intense volume spike right before bed. This triggers an inevitable cycle:

  • Fragmented Sleep: Waking up multiple times a night to use the bathroom, disrupting critical REM and deep sleep cycles.

  • Bladder Irritation: Flooding the bladder rapidly causes sudden stretching, which can mimic the symptoms of overactivity.

  • Chronic Fatigue: Missing out on uninterrupted sleep ruins morning focus and long-term cognitive performance.

The Art of Strategic Hydration

If your sleep is constantly interrupted, the solution isn’t just buying a better mattress; it’s looking at your renal and bladder habits. A Urologist in Brisbane can help you break down the timing and chemistry of your fluid intake.

Rather than playing catch-up at night, a tailored approach involves front-loading your hydration early in the day, using electrolyte balances suited to the Queensland climate, and tapering off fluid intake smoothly before the evening. Protecting your sleep is a fundamental pillar of health, and sometimes, the key to a restful night starts with managing your bladder’s biological clock.