
Tag Archive for: wesley hospital urologist brisbane

When the leak won’t quit: urinary incontinence in men

A Movember reminder that help is available

Movember is a good time to talk about men’s health issues that are often kept quiet. Urinary leakage is one of them. It can affect confidence, exercise, work, travel, intimacy and sleep. After prostate surgery, some leakage is common during recovery, but men do not have to simply put up with persistent or troublesome symptoms.

This article focuses on urinary incontinence after prostatectomy. It is general information, not a diagnosis or a substitute for advice from your own doctor.

What does “incontinence” mean?

Urinary incontinence means urine escapes when you do not intend it to. After prostate surgery, the most common pattern is stress urinary incontinence: leakage with coughing, sneezing, lifting, walking, standing up or exercise. The operation can affect the urinary sphincter and the support around the urethra.

Some men instead, or as well, experience urgency incontinence: a sudden, hard-to-delay urge followed by leakage. This may relate to an overactive bladder. Other causes: including infection, difficulty emptying the bladder, a narrowing at the bladder outlet or a medication effect. may also need consideration. The treatment depends on the pattern, so it is worth describing exactly when leakage happens.

What to expect after prostatectomy

Leakage is common soon after the catheter is removed and usually improves over time. Many men continue to regain control over the first 6–12 months, although recovery varies and some men have persistent leakage. A small amount of leakage can still be very disruptive, and heavier leakage deserves timely review rather than a wait-and-see approach without support.

If leakage is not improving, is affecting daily life, or you are worried, speak with your GP, urologist, continence nurse or pelvic health physiotherapist. You can ask for help at any stage of recovery.

Start with an assessment

A clinician will ask about the amount and timing of leakage, urgency, night-time symptoms, bowel habits, previous radiation or other procedures, and how much the problem affects you. A bladder diary and pad count or pad-weight test can help describe the pattern and severity. Examination, urine testing, bladder emptying checks, cystoscopy or urodynamic testing may be useful in selected cases—particularly before surgery or if the symptoms are not straightforward.

Assessment helps distinguish stress leakage from urgency or mixed symptoms, and checks for problems that should be treated before continence surgery.

Pelvic floor physiotherapy: learning the right muscles

Pelvic floor muscle training is commonly offered after radical prostatectomy and may also be started before surgery with your treating team’s advice. A pelvic health physiotherapist or continence nurse can show you how to find and correctly contract the muscles, then build a programme around your recovery. The aim is a controlled lift and squeeze around the back passage and base of the penis, followed by a full relaxation. Try not to hold your breath or tighten your buttocks, thighs or stomach.

A correct contraction should not hurt. Avoid repeatedly stopping your urine stream as an exercise; that can interfere with normal bladder emptying. Follow your surgeon’s instructions about when to begin or resume exercises, particularly while a catheter is in place. Some men benefit from learning a quick pelvic floor contraction before coughing, lifting or standing.

Training can help speed recovery and improve control, but it is not a guaranteed cure, and it may not overcome significant sphincter damage on its own. Keeping active safely, avoiding constipation and getting advice about continence products can make recovery more manageable. Do not deliberately dehydrate yourself; adequate fluid intake helps avoid concentrated urine and constipation. If caffeine or alcohol aggravates urgency, reducing it may help those symptoms.

Other non-surgical support

Absorbent pads or a male urinary sheath can help you stay active while recovery continues. A continence nurse can help with fit, skin care and practical use. A penile clamp may suit selected men for short periods, but it can restrict blood flow or injure skin and should only be used after professional advice. Medicines may help urgency or overactive bladder symptoms, but they do not repair a weakened urinary sphincter.

When is surgery considered?

If bothersome stress leakage is not improving despite conservative care, surgery can be discussed from around six months in selected men; persistent leakage is generally reviewed for surgical treatment by about 12 months. The timing should be individualised with your urologist, taking account of the severity and trajectory of leakage, cancer treatment plan, bladder and urethral health, and your preferences.

Two established operations are a male sling and an artificial urinary sphincter (AUS). Neither is right for every man, and both require a careful assessment and discussion of expected benefits, possible complications and the chance of future treatment.

Male sling

A sling is placed beneath the urethra to support it and improve its closure. It is generally considered for men with mild-to-moderate stress leakage, particularly when they have not had pelvic radiotherapy and do not have severe leakage. It does not have a pump to operate. A sling may not work as well for heavier leakage, and previous radiation or some other urethral procedures can reduce the chance of success. Some men continue to leak or may later need another procedure.

Artificial urinary sphincter

An AUS uses a fluid-filled cuff around the urethra, connected to a small pump placed in the scrotum. The cuff stays closed to prevent leakage. To urinate, the man presses the pump; the cuff opens temporarily and then closes again automatically. The device is a well-established option for moderate-to-severe stress leakage, and may also be considered for other degrees of troublesome leakage after discussion.

An AUS requires an operation and the ability to understand and operate the pump. It can substantially improve control, but it may not make every man completely dry. Infection, erosion or mechanical problems can occur, and the device can lose effectiveness over time. Further procedures to revise or replace it are common over a person’s lifetime. If you have an AUS, tell any doctor, nurse or hospital team before a urinary catheter or instrument is inserted, as special care is needed to avoid damaging the cuff or urethra.

Choosing between them

The choice depends on leakage severity, previous radiotherapy or urethral surgery, bladder function, hand function and cognition, anatomy, personal priorities and the surgeon’s assessment. In general, slings are most often discussed for mild-to-moderate leakage, while an AUS is often favoured for more significant leakage or after radiotherapy. Cystoscopy is usually part of the assessment before an operation; urodynamics may be useful where it could clarify the diagnosis or guide counselling.

The emotional side matters too

Wearing pads, planning every trip around a toilet, or worrying about leakage during exercise or sex can be isolating. These concerns are legitimate health issues, not a personal failure. A partner, GP, urologist, continence nurse or physiotherapist can help you find a practical next step. Movember is a reminder to check in with your mates—and to speak up about your own health as well.

When to seek prompt medical advice

Seek urgent medical advice if you cannot pass urine, develop fever or feel acutely unwell with urinary symptoms, notice visible blood in your urine, or develop new severe pain. If you have an AUS and develop pain, swelling, redness, difficulty urinating or a sudden change in leakage, contact your treating team promptly.

Key message

Urinary leakage after prostatectomy is common, but persistent leakage has treatment options. Pelvic floor physiotherapy is an important part of recovery; pads and other supports can help in the meantime; and selected men may benefit from a sling or artificial urinary sphincter. The first step is an open conversation and an assessment tailored to the type and severity of leakage.

Further information and references

  1. American Urological Association, GURS and SUFU. Incontinence after Prostate Treatment: Guideline (2019; amended 2024). AUA guideline PDF.
  2. European Association of Urology. Guidelines on the Management of Non-neurogenic Male LUTS, 2026: Disease Management. EAU guideline.
  3. Continence Health Australia. Bladder control after prostate surgery. Patient information.
  4. Prostate Cancer Foundation of Australia. Pre- and rehabilitation: urinary incontinence and pelvic floor exercises. PCFA resource.
  5. Cancer Council Australia. Managing side effects of prostate cancer treatment. Cancer Connect.

This information is educational and does not replace an individual consultation. Treatment decisions should be made with your treating health professional.
Movember: PSA testing: what it can tell you, and what it can’t

An informed conversation with your GP can help you decide whether a PSA test is right for you. Your age, family history, general health and preferences all matter.

Movember is a good time to talk about men’s health, including prostate cancer. One of the most useful steps is often a simple conversation with your GP about prostate-specific antigen (PSA) testing. A PSA blood test can help identify men who may need further assessment, but it is not a yes-or-no cancer test. Understanding what it can and cannot show helps you make an informed choice.

What is PSA?

PSA is a protein made by cells in the prostate. A small amount normally enters the bloodstream, where it can be measured with a blood test. PSA is prostate-specific, but not cancer-specific: a higher result can occur with prostate cancer, but also with benign prostate enlargement, inflammation or infection, urinary retention, or after some urinary procedures. PSA levels also tend to rise with age.

A PSA test is different from a digital rectal examination (DRE). The blood test measures PSA. A DRE is an examination in which a clinician feels the prostate through the rectum. A DRE is not routinely required as an addition to PSA testing for an asymptomatic man under RACGP guidance, although examination may be useful when symptoms or other findings make it appropriate.

Why do we use PSA?

Prostate cancer may cause no symptoms in its early stages. PSA testing can identify a result that deserves a closer look before symptoms develop. Used thoughtfully, early detection may help find clinically significant cancer while treatment or monitoring options remain available.

There are limits and possible harms. PSA can be raised when cancer is not present, leading to anxiety, repeat tests, scans and sometimes biopsy. It can also find a slow-growing cancer that would never have caused a problem during a person’s lifetime. Diagnosis and treatment can have side effects, including changes to urinary continence and sexual function. The chance of benefit depends on a person’s risk, health and life expectancy. That is why Australian guidance recommends an informed discussion before testing rather than testing everyone automatically.

Is PSA a good marker for prostate disease or prostate cancer?

PSA is a useful risk marker, not a diagnosis. It can help estimate the chance of prostate cancer and guide whether further assessment is sensible. It is not a reliable general test for every prostate problem, and it cannot by itself distinguish cancer from benign enlargement or inflammation.

A low PSA lowers the chance of prostate cancer but does not make it zero. A raised PSA does not mean that cancer is present. If the result is higher than expected for a person’s age and risk, the GP will usually consider the whole picture and repeat the test before acting on a single result. Infection, inflammation, retention and recent instrumentation can affect the result, so timing and clinical context matter.

If PSA remains elevated, further assessment may include a clinical review, examination when appropriate, and prostate MRI. Current Australian guidance recommends multiparametric MRI before biopsy. A biopsy, when indicated, is what confirms whether cancer is present and provides information about its grade. Not everyone with a raised PSA needs a biopsy.

How often should PSA be tested?

Australia’s guidance has evolved. The RACGP’s Guidelines for preventive activities in general practice (Red Book, 10th edition, 2024) recommends offering informed men at average risk aged 50–69 PSA testing every two years if they choose regular testing. It recommends testing every two years from age 45 for men at moderately increased risk because of family history, and from age 40 for those at high risk due to family history, through age 69.

USANZ’s published PSA position statement is described as an interim document pending updates to the PCFA and RACGP guidelines. It supports an individualised, risk-based discussion for well-informed men over 50 with an adequate life expectancy, earlier testing from over 45 for men with a family history or higher-risk ethnicity, and from over 40 for men with a BRCA2 mutation.

Since those documents, the NHMRC approved the 2026 Guidelines for the Early Detection of Prostate Cancer in Australia. These are the latest national recommendations and give the following general pathway for people who decide to test after discussion with their GP:

Age and risk General testing approach
Average risk, age 50–69 Offer PSA testing every two years.
Higher risk, age 45 and over Offer testing every two years, using lower PSA levels to trigger a repeat test and possible referral.
Age 70 and over Individualise the decision. The guideline generally considers testing when estimated life expectancy is more than seven years.
Age 45–49, not at higher risk Routine testing is not recommended; an initial test may be discussed if the person is interested.

The 2026 guideline defines higher risk to include having a brother with prostate cancer; a father diagnosed before age 65; two or more second-degree relatives who died from prostate cancer; Black sub-Saharan ancestry; or a confirmed BRCA2 mutation. Family-history details and other health factors still need to be discussed with a GP. The guideline uses age- and risk-specific PSA action levels; a result at or above an action level is generally repeated within one to three months, rather than treated as a cancer diagnosis.

These recommendations guide discussion; they are not a substitute for individual advice. Screening recommendations apply to people without symptoms. If you have symptoms, your GP may recommend assessment regardless of your age or the usual testing interval.

How important is family history?

Family history can make a real difference. Prostate cancer in a close relative, especially a brother, or a father diagnosed at a younger age, can increase a person’s risk and may mean discussing PSA testing earlier than age 50. Multiple affected relatives can also point to an inherited risk. A known BRCA2 mutation is another important risk factor.

If you know that prostate cancer has affected your family, tell your GP which relative was affected and how old they were when diagnosed. Also mention any known breast, ovarian, pancreatic or other cancers in the family, as these may help the GP decide whether genetic counselling or testing should be discussed. Do not wait for symptoms before raising a strong family history.

When should I see a urologist?

Your GP is usually the right first contact. A referral to a urologist may be appropriate if a repeat PSA remains at or above the age- and risk-based action level, if the prostate examination is concerning, or if MRI or other findings suggest that specialist assessment is needed. A urologist can discuss the benefits and limits of further tests, including MRI and biopsy, and help decide on next steps.

Make an appointment with your GP if you notice persistent or new urinary problems, blood in your urine or semen, or ongoing unexplained pain. These symptoms can have many causes and do not automatically mean prostate cancer, but they deserve assessment. Do not wait for a routine PSA check if you have a concerning symptom. If you cannot pass urine, seek urgent medical care.

A useful Movember conversation

Ask your GP: “Given my age, health and family history, should I have a PSA test? If we test, how often should I repeat it, and what would we do if it is raised?” Knowing your family history and discussing the possible benefits and harms can make the decision more useful than simply ordering a blood test without a plan.

Movember is a reminder to look out for one another. Start the conversation, share what you know about your family history, and encourage the men in your life to seek advice when something does not feel right.

This article provides general information and is not a substitute for personal medical advice. PSA testing is a shared decision between you and your healthcare professional.

References and further information

  1. Prostate Cancer Foundation of Australia. 2026 Guidelines for the Early Detection of Prostate Cancer in Australia: summary and recommendations. NHMRC approved 18 May 2026.
  2. The Royal Australian College of General Practitioners. Guidelines for preventive activities in general practice, 10th edition — prostate cancer, recommendations updated 28 June 2024.
  3. Urological Society of Australia and New Zealand. PSA Testing position statement. Interim guidance pending updated guidelines.
  4. Huang S, Chen DC, Crowe J, et al. Navigating the shift: New RACGP Red Book guidelines for prostate-specific antigen testing in general practice. Australian Journal of General Practice. 2025;54(12). Article PDF.

Know your testes: testicular cancer, self-awareness and Movember

Movember is a good time to talk openly about men’s health. Testicular cancer is uncommon overall, but it matters because it often affects teenagers and younger adults, and a new lump can be easy to dismiss or feel awkward to discuss. Knowing what is usual for your body can help you notice a change and seek advice.

How common is testicular cancer in Australia?

Cancer Australia estimates that 1,040 people will be diagnosed with testicular cancer in Australia in 2025. The estimated lifetime risk for males is about 1 in 188 by age 85. The rate is highest in men aged 30–34, although it can occur at other ages. Testicular cancer is one of the more common cancers in younger men. [1,2]

The outlook is generally very good. For Australians diagnosed from 2017 to 2021, five-year relative survival was 98%. This is a population estimate: an individual’s outlook depends on the cancer type, stage, tumour markers, health and response to treatment. Many testicular cancers, including some that have spread, can be cured with modern treatment. [1,2]

What does “regular self-examination” mean?

There is no national screening program or recommended screening interval for testicular cancer. Research has not shown that scheduled self-examination of people without symptoms reduces deaths, and a Cochrane review found no randomised trials that tested whether screening by self-examination or a clinician prevents testicular-cancer deaths. Cancer Council Australia therefore does not recommend population screening. [3,4]

That is different from being familiar with your own body. Movember’s “Know Thy Nuts” campaign encourages men to learn what feels normal and to get changes checked. A practical approach is to check in with yourself from time to time, such as in the shower, without treating it as a test that can rule cancer in or out. If you have a higher-risk history, discuss an individual plan with your GP or urologist. [3,5]

A simple way to get familiar with what is normal

  1. Warm water can relax the scrotal skin, making it easier to feel the testicles.
  2. Examine one testicle at a time. Gently roll it between your thumb and fingers; do not squeeze hard.
  3. Notice its usual size, shape and feel. It is common for one testicle to hang lower or be slightly larger than the other.
  4. The epididymis, a soft, slightly ridged tube along the back of each testicle, is normal anatomy. It can be mistaken for a lump when you are not familiar with it.
  5. Pay attention to a new firm lump on the testicle, a change in size or shape, new swelling, a feeling of heaviness, or a persistent ache.

There is no need to follow a rigid monthly schedule. The useful point is to know what is usual for you and to arrange a medical review if something changes. Self-checking cannot diagnose cancer, and a normal-feeling testicle does not replace assessment of symptoms.

When should you see a doctor?

Arrange a prompt appointment with your GP if you find a new lump or notice persistent swelling, a change in size or shape, heaviness, or an ache in the testicle, scrotum or lower abdomen. Most scrotal changes are not cancer, but they deserve assessment rather than guesswork. A sudden, severe testicular pain needs urgent emergency assessment because conditions such as testicular torsion can threaten the testicle and require rapid treatment. [2,6]

Movember notes that a GP can ask about symptoms, examine the testicles and arrange an ultrasound or blood tests when needed. It is reasonable to ask when and how you will receive results, and to follow up if you have not heard back. [5]

What types of testicular cancer are there?

Most testicular cancers start in germ cells, the cells that develop into sperm. They are grouped into two main categories: [2,7]

  • Seminoma: Often grows and spreads more slowly than non-seminoma. It is most often diagnosed in adults roughly 25–45 years old, but can occur outside this range. A rare spermatocytic type tends to occur in older men.
  • Non-seminoma: More common in younger men, often from the late teens to early 30s. The main cell types are embryonal carcinoma, yolk-sac tumour, choriocarcinoma and teratoma. A tumour may contain more than one type; mixed tumours are generally managed as non-seminoma.
  • Stromal tumours: These arise from hormone-producing or supporting cells, such as Leydig or Sertoli cells. Many are benign, but specialist assessment is needed to determine what a mass is.
  • Germ-cell neoplasia in situ (GCNIS): Abnormal germ cells that have not invaded surrounding tissue. It is a precursor condition, rather than an invasive cancer, and is usually found on tissue examination.

The type matters because seminoma and non-seminoma can behave differently and may need different follow-up or treatment.

How is a testicular mass investigated?

A doctor will ask about the change and examine the scrotum and surrounding areas. Scrotal ultrasound is the key imaging test to distinguish a solid testicular mass from other causes of swelling. Blood tests may measure alpha-fetoprotein (AFP), beta-human chorionic gonadotrophin (β-hCG) and lactate dehydrogenase (LDH). These markers help with diagnosis, staging and monitoring, but normal results do not exclude testicular cancer. If cancer is suspected, further imaging—often CT scans—is used to assess whether it has spread. [6,8]

A needle biopsy through the scrotum is generally avoided when a germ-cell cancer is suspected. Diagnosis is usually confirmed by removing the affected testicle through an incision in the groin (radical inguinal orchidectomy) and examining it under a microscope. This operation is also the first treatment for most testicular cancers. [6]

Treatment options

Treatment depends on the tumour type, stage, blood-marker results, risk of recurrence, general health and the person’s priorities. Care is planned by a multidisciplinary team, usually including a urologist, medical oncologist, radiation oncologist and cancer-care nurses. Options can include: [6,9]

  • Orchidectomy: Removal of the affected testicle. For some cancers confined to the testicle, this may be the only treatment needed.
  • Active surveillance: Regular appointments, blood tests and imaging after surgery to detect any recurrence early. This is a structured treatment option, not being left without follow-up.
  • Chemotherapy: Often cisplatin-based combinations, such as BEP, for selected cancers with a higher recurrence risk or disease that has spread.
  • Radiotherapy: Used in selected seminoma cases; its role is more limited than in the past because surveillance and chemotherapy are alternatives, and long-term effects are considered.
  • Retroperitoneal lymph-node surgery: Removal of selected lymph nodes in the abdomen in particular non-seminoma situations, often when cancer remains after chemotherapy or when surgery is preferred in carefully selected cases.

The choice after orchidectomy is not the same for everyone. For early seminoma, surveillance is commonly offered; some people may consider a single dose of carboplatin. For early non-seminoma, surveillance, one cycle of chemotherapy, or (in selected cases) lymph-node surgery may be discussed. The aim is to cure the cancer while avoiding treatment that is not necessary. [6]

Fertility, hormones and life after treatment

If there is time before chemotherapy or radiotherapy, ask about sperm banking, even if you are unsure about future plans. Cancer and its treatment can affect fertility, and it is easier to discuss preservation before treatment begins. Many men retain adequate testosterone and fertility with one healthy testicle, but this is not guaranteed; hormone levels, semen quality and sexual wellbeing can be discussed with the treatment team. A testicular prosthesis can be considered before or after surgery. Follow-up also matters because recurrence and some late effects can occur after treatment. [6,9]

A Movember reminder

Movember’s message is straightforward: get to know what is normal for you, speak up if something changes, and make an appointment rather than carrying the worry alone. Testicular cancer is highly treatable, and getting a new lump assessed is a sensible step—not a reason to assume the worst. [1,5]

This article is for general education and does not replace an individual assessment by a doctor.

References

  1. Cancer Australia. Testicular cancer in Australia: statistics. Incidence estimates, age patterns, mortality and relative survival. Accessed 4 November 2026.
  2. Cancer Council Australia. Testicular cancer: causes, symptoms and treatments. Australian overview of incidence, symptoms, types, diagnosis, treatment and screening position. Accessed 4 November 2026.
  3. Ilic D, Misso ML. Screening for testicular cancer. Cochrane Database Syst Rev. 2011;(2). doi:10.1002/14651858.CD007853.pub2.
  4. Cancer Council Australia. Early detection policy: testicular cancer. Position statement on population screening and testicular self-awareness. Accessed 4 November 2026.
  5. Movember Australia. Seeing a doctor about testicles and testicular cancer; and Know Thy Nuts. Campaign information on noticing changes and seeking medical review. Accessed 4 November 2026.
  6. European Association of Urology. EAU Guidelines on Testicular Cancer (2026), including chapters on diagnostic evaluation and disease management. Accessed 4 November 2026.
  7. Cancer Australia. Types of testicular cancer. Accessed 4 November 2026.
  8. Cancer Australia. How is testicular cancer diagnosed?. Accessed 4 November 2026.
  9. Cancer Australia. Treatment options. Accessed 4 November 2026.
  10. Baade PD, Carrière P, Fritschi L. Trends in testicular germ cell cancer incidence in Australia. Cancer Causes Control. 2008;19(10):1043–1049. doi:10.1007/s10552-008-9168-z.

Bladder neck contracture after TURP or laser prostate surgery

Why it happens, why it can recur, and how it may be treated

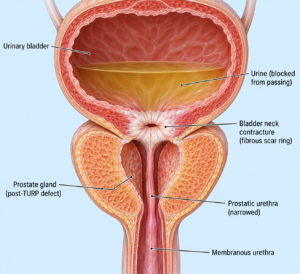
Transurethral resection of the prostate (TURP) and laser procedures such as photoselective vaporisation (PVP) or transurethral vaporisation (TUVP) are used to improve urine flow when an enlarged prostate obstructs the bladder outlet. In a small number of men, healing after surgery causes scar tissue to tighten at the bladder neck: the opening between the bladder and the prostate/urethra. This is called a bladder neck contracture (BNC) or bladder neck stenosis.

A BNC can cause a return of urinary symptoms after an initially successful operation. It is treatable, although some contractures return after treatment and a small group of men need several procedures or specialist reconstructive surgery.

This information is general and is not a substitute for assessment by your GP or urologist. The most suitable option depends on the exact site and length of narrowing, bladder function, previous procedures, continence, and general health.

How common is it?

The reported rate varies with the operation, the definition used, follow-up time, and the patients studied. A recent systematic review of randomised trials with at least two years of follow-up estimated BNC in about 3% after TURP and 9% after photo-selective laser vaporisation (PVP). The confidence intervals were wide, especially for PVP, so these figures should not be treated as a precise prediction for an individual patient. The European Association of Urology (EAU) guideline cites a broader range of approximately 0.3–9.7% for bladder neck stenosis after transurethral prostate surgery.[1,2]

“TUVP” is used for more than one vaporisation technique. Studies of older electrovaporisation, bipolar vaporisation and modern laser PVP are not interchangeable. For example, one small early study of transurethral vaporisation reported BNC in 3 of 30 patients; that result is too small and old to represent the risk from current laser surgery.[3] Your surgeon can explain which procedure was used and what the evidence for that specific technique shows.

Why can it develop?

The bladder neck can heal with excess scar tissue after surgical trauma, heat, or inflammation. The exact cause is not always clear. Factors associated with BNC in published studies include a smaller prostate or less tissue removed, infection around the time of surgery, smoking, diabetes or cardiovascular disease, longer operating time, and extensive treatment near the bladder neck. These are associations: they do not mean that a particular factor caused an individual person’s contracture.[2,4]

BNC often becomes apparent during the first months after surgery, but it can present later. Symptoms may include:

  • a weaker, slower or interrupted stream;
  • straining, hesitancy, or taking longer to pass urine;
  • a feeling that the bladder has not emptied;
  • frequent or urgent urination, or getting up at night;
  • recurrent urinary infections; or
  • inability to pass urine, which needs urgent medical attention.

These symptoms can also be caused by prostate regrowth, urethral narrowing, infection, an underactive bladder, or other bladder conditions. Testing is needed to identify the cause.

How is it assessed?

Assessment commonly includes a history, examination, urine testing, measurement of urine flow (uroflowmetry) and the amount left in the bladder after voiding (post-void residual). Cystoscopy, a small camera passed through the urethra, usually confirms whether the bladder neck is narrowed and whether a scope can pass. Depending on the situation, imaging such as a retrograde urethrogram or a bladder/urethral contrast study may help map the narrowing. Kidney and bladder imaging or kidney blood tests may be appropriate if there is significant retention, infection, or concern about the upper urinary tract.

Treatment options

Treatment is tailored to the narrowing and the person’s symptoms and priorities. A short, non-obliterated contracture is usually approached differently from a long, dense scar or a bladder neck that has closed completely.

Dilatation

A narrow area can sometimes be gently stretched with instruments or a balloon. This is relatively straightforward and can improve flow, but the scar may tighten again. In some cases a planned programme of intermittent self-catheterisation is discussed to help keep the opening stable. It is not suitable or acceptable for everyone.

Endoscopic incision or resection

A surgeon can use a small endoscope to cut (incise) the scar, or remove some of the scar tissue, using an electrical knife or laser. This is a common first treatment for a non-obliterated BNC. A catheter is often left temporarily while the area heals.

A first treatment may be enough, but recurrence is a recognised problem. EAU evidence summaries report patency after the first endoscopic treatment of about 58% following transurethral resection and 72% following incision in the cited studies. Those results come from varied, generally small observational series and should not be taken as a guaranteed personal outcome.[5] Repeated incision or dilation may be reasonable for some men with a passable narrowing; it can relieve symptoms or stabilise the opening, but each recurrence needs reassessment. A completely obliterated bladder neck is unlikely to be cured by routine endoscopic cutting and blind attempts can be unsafe.[5]

Scar-modulating injections

Steroid or mitomycin C injections have been used with endoscopic incision in selected recurrent cases. Evidence is mixed and largely based on retrospective series. Mitomycin C is not a routine, risk-free add-on: a multicentre study reported serious complications in 7% of treated patients, including tissue injury and fistula, with some requiring major further treatment.[6] If considered, the potential benefit and uncommon but significant risks should be discussed explicitly with a reconstructive urologist.

Bladder neck reconstruction

When a contracture repeatedly returns, is long or dense, or is completely closed, a reconstructive operation may be considered. The goal is to create a wider, durable outlet while protecting the bladder, ureters and continence mechanism as much as possible. The choice depends on the site and extent of scar, previous operations or radiotherapy, bladder function, continence, and surgeon expertise.

Options include a Y–V or T-plasty, in which healthy bladder tissue is rearranged to widen the outlet, with scar tissue released or removed as needed. The EAU guideline reports patency rates of 83–100% in published series, with follow-up of 14–45 months; new incontinence was reported in up to 14%. These results are from selected patients and small observational studies, not randomised comparisons.[5]

In selected complex cases, reconstruction can be performed with a robot-assisted approach. The magnified view and instruments that articulate inside the pelvis may help the surgeon work precisely around the bladder neck. Robotic reconstruction is specialised surgery, not a guarantee against recurrence or incontinence. In a systematic review of ten small case series (119 men with different causes and techniques), pooled patency was 80%; new incontinence was reported in 17% of the subset with suitable continence data. Follow-up was relatively short and the evidence was heterogeneous, so longer-term results remain important.[7]

Buccal mucosa graft reconstruction: an emerging option

Buccal mucosa is the moist lining inside the cheek. It can be taken as a graft and used to augment a narrowed or damaged urinary passage. For a severe bladder neck defect, a graft may be placed as an onlay/inlay to create a wider channel rather than simply cutting the scar again. The graft is harvested from the mouth, so temporary cheek soreness, altered mouth sensation, or tightness are possible in addition to the risks of the urinary reconstruction.

A/Prof Devang Desai and colleagues in Toowoomba have reported a robot-assisted reconstruction for complete bladder neck obliteration after TURP using two cheek grafts, one placed anteriorly and one posteriorly, to create a “double-faced” repair. In their reported case, the patient was voiding without incontinence at seven months, with a maximum flow of 23 mL/s. This is an innovative case report and conference abstract, not yet evidence that the technique is superior to established reconstruction or that results will be the same for other patients. The authors themselves note that longer follow-up is needed.[8,9]

This approach may be discussed by a reconstructive urologist for selected men with a complex or completely obliterated bladder neck, particularly after less invasive treatments have failed. It is not needed for most BNCs, and access to the technique depends on specialist experience and individual circumstances.

Catheter drainage and other options

If the bladder cannot empty, a urethral catheter or a suprapubic catheter (placed through the lower abdominal wall) may be needed, temporarily or longer term. A suprapubic catheter can be a practical choice while planning further treatment or when reconstruction is unsuitable or not wanted. In very complex cases, especially when the bladder itself is severely damaged, other forms of urinary diversion may be considered, but this is uncommon for BNC after routine TURP or vaporisation.

Continence and the possibility of further treatment

Opening a tight bladder neck can reveal leakage that was previously masked by the obstruction, or can worsen existing urinary incontinence. This may happen after endoscopic treatment as well as reconstruction. Some men remain dry; others may need continence treatment later. Before proceeding, ask your urologist how the contracture, any previous prostate surgery or radiotherapy, and your existing continence affect the plan.

A recurrence does not mean that you have done anything wrong. Scar healing is variable. If narrowing returns, the next step should be based on updated assessment rather than automatically repeating the same procedure. A reconstructive urologist can help weigh another endoscopic treatment against reconstruction, catheter drainage, or other options.

When to seek urgent help

Seek urgent medical care if you are unable to pass urine, develop fever or shaking chills with urinary symptoms, or have severe lower abdominal pain. Acute retention can require prompt bladder drainage.

References

  1. Mac Curtain BM, et al. Bladder neck contracture post-treatment for benign prostatic hyperplasia: a systematic review and meta-analysis of randomized clinical studies. International Urology and Nephrology. 2025. https://doi.org/10.1007/s11255-025-04648-2
  2. European Association of Urology. EAU Guidelines on Urethral Strictures: Definition, epidemiology, aetiology and prevention. https://uroweb.org/guidelines/urethral-strictures/chapter/definition-epidemiology-aetiology-and-prevention
  3. Chang PL, et al. Clinical outcome at 3 months after transurethral vaporization of prostate for benign prostatic hyperplasia. PubMed. https://pubmed.ncbi.nlm.nih.gov/9255294/
  4. Gül M, et al. Bladder neck contracture following transurethral surgery of prostate: a retrospective single-center study. PubMed. https://pubmed.ncbi.nlm.nih.gov/38189837/
  5. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease management in males—posterior urethral stenosis and bladder neck stenosis. https://uroweb.org/guidelines/urethral-strictures/chapter/disease-management-in-males
  6. Redshaw JD, et al. Intralesional injection of mitomycin C at transurethral incision of bladder neck contracture may offer limited benefit: TURNS Study Group. Journal of Urology. https://pubmed.ncbi.nlm.nih.gov/25200807/
  7. Zhang TR, et al. Summarizing the evidence for robotic-assisted bladder neck reconstruction: systematic review of patency and incontinence outcomes. Asian Journal of Urology. 2024;11(3):341–347. https://doi.org/10.1016/j.ajur.2023.08.007
  8. Desai D, Munien K, Namdarian B. Robotic bladder neck reconstruction using a double-faced buccal mucosal graft: a novel approach to complete bladder neck obliteration. Urology Video Journal. 2023. https://doi.org/10.1016/j.urolvj.2023.100247
  9. Desai D, Munien K, Namdarian B. Robotic bladder neck reconstruction using a double-faced buccal mucosal graft—a novel approach to complete bladder neck obliteration. BJU International. 2025;135(Suppl 2): abstract. https://doi.org/10.1111/bju.16629

This article is for general education and does not replace an individual consultation. Treatment choices, likely outcomes and risks should be discussed with the treating urologist.

Prostate cancer, Movember and the moustache: a conversation worth having

Each November, a moustache can do more than change a face. It can open a conversation that might encourage someone to learn their risk, ask about testing or support a person affected by prostate cancer.

Movember is a good time to talk about prostate cancer, but the message matters all year. The aim is not to alarm every man or suggest that everyone needs the same test. It is to make sure people know the facts and can make an informed decision with their doctor.

Prostate cancer in Australia

Prostate cancer is common. The Australian Institute of Health and Welfare (AIHW) estimated that around 29,000 men would be diagnosed in 2025, making it the most commonly diagnosed cancer in Australian men and accounting for about 30% of cancers diagnosed in men that year. These are projected figures, not a final count. Around 1 in 5 men are expected to be diagnosed with prostate cancer during their lifetime.

The outlook is often very good: the AIHW reports a 96% five-year relative survival rate for prostate cancer diagnosed in 2017–2021. That is a population statistic, not a prediction for any one person. Prostate cancers vary: some grow slowly and may never cause harm, while others can be aggressive and need timely treatment. Early assessment can help identify cancers that are more likely to matter, while careful risk assessment helps avoid unnecessary tests and treatment.

What does Movember mean?

Movember began with a simple idea: grow a moustache, raise funds and get people talking about men’s health. It has grown into a global movement supporting men’s health, including prostate cancer, testicular cancer, mental health and physical activity.

The moustache is a friendly, visible conversation starter. Someone may ask, “Why the Mo?” and that gives you a chance to mention prostate cancer, ask a friend whether he knows his family history, or check in with someone who is going through diagnosis or treatment. A moustache cannot detect cancer, and growing one does not replace medical advice. Its value is in helping make a sometimes awkward subject easier to raise.

How is prostate cancer found?

Prostate cancer often causes no symptoms in its early stages. Urinary symptoms such as a weaker stream, needing to urinate more often or difficulty starting are common with ageing and an enlarged prostate, and do not by themselves mean cancer. Blood in the urine or semen, persistent pain, or a new urinary problem should be discussed with a doctor.

The first step in early detection is usually a conversation about personal risk and the possible benefits and downsides of testing. A prostate-specific antigen (PSA) blood test measures a protein made by the prostate. PSA can rise for reasons other than cancer, including prostate enlargement, infection or inflammation. A raised result is not a diagnosis, and a low result does not rule out every cancer.

Australia’s updated national early-detection guidelines, approved by the National Health and Medical Research Council in May 2026, recommend discussing individual risks, preferences, benefits and possible harms before starting PSA testing. For men who choose testing, the guidelines recommend offering it every two years from age 50 to 69 for those not at higher risk, and from age 45 for those at higher risk. Higher risk includes a relevant family history, a confirmed BRCA2 gene mutation or Black sub-Saharan ancestry. Men aged 70 and over should discuss whether to continue testing in light of their health and preferences. These are discussion points, not a substitute for individual medical advice.

If a PSA result is higher than expected, a doctor may repeat the test and consider other information, such as age, symptoms, family history and examination findings. A urologist may recommend a prostate MRI to help decide whether a biopsy is appropriate and, if so, where to take samples. A biopsy is currently the test that confirms a diagnosis and provides information about the cancer’s grade. Not everyone with an elevated PSA needs a biopsy, and no test is perfect. If cancer is found, the next steps depend on its grade and stage, the person’s health and their preferences; some lower-risk cancers can be monitored with active surveillance.

Make November a reason to check in

This November, consider wearing blue when you walk, jog, run or volunteer at your local parkrun. Invite a friend or family member to join you. It is a simple way to show support, start a conversation and make space for men’s health alongside the usual weekend catch-up. This is a community invitation, not a claim that parkrun is running an official Movember campaign.

If you are unsure whether PSA testing is right for you, speak with your GP. Mention your age, family history and any symptoms, and ask what a result could mean and what the next steps might be. If someone close to you has prostate cancer, listening and offering to go with them to an appointment can be a practical form of support.

Grow a Mo, wear blue, or simply start the conversation. The moustache is the prompt; informed choices and looking out for one another are the point.

This article provides general information and is not a substitute for advice from your doctor. Testing decisions should be made with a health professional who can consider your personal circumstances.

References and further information

  1. Australian Institute of Health and Welfare. Cancer data in Australia: Overview of cancer in Australia, 2025.
  2. Australian Institute of Health and Welfare. Cancer outcomes improving overall.
  3. Prostate Cancer Foundation of Australia. PSA testing and the 2026 Australian early-detection guidelines.
  4. Prostate Cancer Foundation of Australia. Diagnosis of prostate cancer.
  5. Movember. About Movember.
  6. parkrun Australia. Find a parkrun event.

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

Movember, King Charles and the Prostate: Why Men Shouldn’t Ignore Their Health

A moustache can start a conversation. A conversation can sometimes save a life.

Every November, moustaches begin appearing on faces around Australia and across the world. Some are magnificent. Some are questionable. Some probably deserve their own urological assessment.

But behind the facial hair lies an important message.

Movember is about getting men talking about their health.

What began in Melbourne in 2003 with 30 men growing moustaches has developed into an international men’s health movement focusing particularly on prostate cancer, testicular cancer, mental health and suicide prevention. Movember reports that it has funded more than 1,320 men’s health projects around the world.

And few recent stories demonstrate the importance of men paying attention to their health better than that of King Charles III.


First, an important clarification: King Charles does NOT have prostate cancer

This point has frequently been confused in media and social-media discussions.

In January 2024, Buckingham Palace announced that King Charles was receiving treatment for an enlarged prostate.

This was benign prostatic enlargement, commonly called benign prostatic hyperplasia or BPH. It is extremely common as men get older and is not prostate cancer.

The King underwent a planned hospital procedure for his enlarged prostate.

During this episode of care, however, doctors identified a separate abnormality. Further investigations subsequently diagnosed a form of cancer.

Buckingham Palace specifically confirmed that the King’s cancer was not prostate cancer. The precise type of cancer has remained private.

That distinction matters.

But so does what happened next.


A prostate problem led to something else being discovered

The King’s story provides an interesting lesson for men’s health.

He sought medical attention for a prostate problem.

He underwent investigation and treatment.

During that process, doctors discovered another potentially important medical condition.

In February 2024 Buckingham Palace announced that the King had begun a programme of regular cancer treatments and temporarily reduced his public-facing duties.

By April 2024, following treatment and recuperation, he was able to return to public-facing duties.

The exact cancer treatment has never been publicly disclosed, and it would therefore be inappropriate to speculate whether he has received surgery, radiotherapy, chemotherapy, immunotherapy or another form of treatment.

More recently, the King has continued to speak publicly about his cancer experience. In December 2025 he announced that, following early diagnosis, treatment and adherence to medical advice, his treatment schedule could be reduced in the following year.

In June 2026 he and Queen Camilla hosted a reception marking the 125th anniversary of Cancer Research UK, of which the King has been Patron since 2024.

His message has increasingly centered on a simple theme:

Early diagnosis matters.


The other royal problem: an enlarged prostate

For a urologist, the first part of the King’s story is equally important.

An enlarged prostate is extraordinarily common.

As the prostate enlarges, it can compress the urethra and interfere with the passage of urine.

Men may notice:

  • a slower urinary stream
  • difficulty starting urination
  • stopping and starting
  • straining
  • feeling that the bladder has not emptied completely
  • getting up several times during the night
  • urgency or frequency
  • occasionally an inability to pass urine at all.

These symptoms do not automatically mean prostate cancer.

Most commonly they are associated with benign prostate enlargement.

But that does not mean they should simply be accepted as part of getting older.


“It’s probably just my prostate”

Possibly.

But that is precisely why it is worth having it checked.

Assessment of urinary symptoms may include a discussion about symptoms and medications, examination, urine testing, kidney function, PSA testing where appropriate, urinary flow measurement, ultrasound assessment of bladder emptying and occasionally further investigations.

The objective is not simply to find prostate cancer.

It is to work out why the urinary system is behaving differently.


What about prostate cancer?

This is where Movember becomes particularly relevant.

Prostate cancer remains the most commonly diagnosed cancer in Australian men. Australian Institute of Health and Welfare data indicate that prostate cancer accounted for approximately 28% of cancers diagnosed in Australian males in 2024.

AIHW’s updated projections estimate approximately 26,397 prostate cancer diagnoses in Australia during 2026, although it is important to recognise that this is a projection rather than a final observed case count.

Movember estimates that approximately one in five Australian men will be diagnosed with prostate cancer during their lifetime.

And there is another important difference between prostate cancer and benign enlargement:

Early prostate cancer frequently causes no urinary symptoms at all.

Waiting until something hurts or the urine flow deteriorates is therefore not an effective prostate cancer detection strategy.


The PSA conversation

A PSA blood test can help identify men who may require further investigation for prostate cancer.

But PSA is not simply a “cancer test”.

PSA can be elevated for several reasons, including:

  • benign prostate enlargement
  • prostatitis or inflammation
  • urinary infection
  • recent instrumentation
  • urinary retention
  • and prostate cancer.

An abnormal PSA therefore does not automatically mean cancer.

Similarly, decisions about PSA testing should consider a man’s age, family history, previous PSA results, general health and individual risk factors.

The important step is having the conversation with your GP or urologist rather than avoiding the subject altogether.


And if prostate cancer is found?

Modern prostate cancer treatment is no longer a simple choice between “operate” and “do nothing”.

Depending upon the PSA, MRI findings, biopsy grade, tumour volume, stage, age and general health of the patient, options may include:

Active surveillance for suitable low-risk disease.

Robotic-assisted radical prostatectomy for appropriate localised cancers.

Radiation therapy, sometimes combined with hormonal treatment.

Focal therapies in carefully selected patients and specialised settings.

Androgen deprivation and newer androgen-receptor targeted treatments for more advanced disease.

Chemotherapy and radioligand therapies for selected advanced cancers.

The right treatment is increasingly personalised to both the biology of the cancer and the priorities of the man sitting in front of us.


Treatment is not only about surviving cancer

This is another area in which organisations such as Movember have made an important contribution.

Men understandably want their cancer controlled.

But they also care about what happens afterwards.

Will I leak urine?

Will I still have erections?

What happens to ejaculation and orgasm?

Can I continue working?

How will treatment affect my relationship?

Will I still feel like myself?

Movember has invested not only in prostate cancer research but also in projects examining quality of life, urinary function, sexual function and outcomes following treatment. The Prostate Cancer Outcomes Registry Australia and New Zealand, for example, collects patient-reported outcomes including urinary, bowel and sexual function after prostate cancer diagnosis and treatment.

These aren’t embarrassing side issues.

They are part of treating the whole man.


So what does King Charles have to do with Movember?

Quite a lot, despite the fact that he does not have prostate cancer.

His story began with something millions of older men experience:

an enlarged prostate.

Instead of ignoring it, he sought treatment.

That interaction with the healthcare system resulted in another cancer being discovered.

And by publicly announcing his prostate treatment and subsequent cancer diagnosis, the King did something particularly useful for men’s health:

he made it easier to talk about it.

That is essentially what Movember has been trying to achieve for more than two decades.

A moustache is simply the billboard.

The conversation is the important bit.


My Movember message to men

If your urinary stream isn’t what it used to be, get it checked.

If you’re getting up repeatedly during the night, ask why.

If you’re struggling with erections, don’t be embarrassed to mention it.

If you notice a testicular lump, don’t wait.

If prostate cancer runs in your family, discuss your individual risk.

And if you’ve been putting off that conversation about PSA testing, perhaps Movember is a good time to have it.

Men are remarkably good at servicing cars, replacing batteries, checking tyre pressures and investigating strange noises coming from engines.

We are sometimes considerably less enthusiastic when the strange noise is coming from ourselves.

This Movember, grow the moustache if you wish.

But more importantly:

Have the conversation.
Know your prostate.
Know your risk.
And don’t ignore a change in your body simply because it’s embarrassing to talk about.

Your prostate may be small.

Its ability to cause trouble is disproportionately ambitious.


References and further reading

  1. The Royal Family. A Statement from Buckingham Palace. 5 February 2024. Buckingham Palace confirmed that a separate cancer was discovered during treatment for benign prostate enlargement.
  2. The Royal Family. The King returns to public-facing duties. April 2024.
  3. The Royal Family. A message from The King in support of Stand Up To Cancer. December 2025.
  4. The Royal Family. The King and Queen host a reception for Cancer Research UK. June 2026.
  5. Australian Institute of Health and Welfare. The health of men in Australia. Prostate cancer statistics and Australian cancer burden.
  6. Australian Institute of Health and Welfare. Cancer data in Australia: Prostate cancer projection method changes and updated long-term projections. Updated July 2026.
  7. Movember. Prostate Cancer: Prostate Cancer Action, Innovation & Collaboration. Australian prostate cancer statistics and research programs.
  8. Movember. Our Story. History of the Movember movement from Melbourne in 2003.
  9. Movember. Prostate Cancer Outcomes Registry Australia and New Zealand. Patient outcomes and quality-of-life research.

Medical disclaimer

This article provides general information and should not replace individual medical assessment. Urinary symptoms, an abnormal PSA or concerns about prostate cancer should be discussed with your GP or urologist.

Can You Train Your Bladder Into Bad Habits?

Bladder training and pelvic floor rehabilitation

Bladder training and pelvic floor muscle training are often recommended for urinary urgency and leakage. They address different parts of bladder control, though, and the right approach depends on the symptoms and on whether the pelvic floor muscles are weak, overactive, or both.

A pelvic floor that works well needs to be able to contract when support is needed and relax when it is time to pass urine or stool. More squeezing is not always better.

What is bladder training?

Bladder training is a structured way of gradually changing toileting habits and responding to urgency. It aims to reduce “just in case” trips, increase the time between voids when appropriate, and help a person regain confidence that an urge can settle without immediately rushing to the toilet.

It is a supported behavioural treatment. It does not mean ignoring pain, forcing yourself to hold on for a long time, or following a rigid schedule regardless of what your body is telling you.

A bladder diary for a few days can help record fluid intake, urination times and volumes, urgency, leakage and night-time waking. Together with a clinician, a person can use this information to choose a realistic starting interval. The interval can then be extended gradually, often by small steps, while using calm breathing and urge-control strategies. Adequate fluid intake, avoiding excessive caffeine, and addressing constipation may also help. Fluid restriction should not be used without advice, as too little fluid can cause dehydration and concentrated urine.

When may bladder training help?

Bladder training is commonly offered as an initial treatment for people with:

  • Overactive bladder (OAB) symptoms: urgency, with or without urgency leakage, usually accompanied by increased daytime frequency and/or waking at night to urinate, when infection or another obvious cause has not been found.
  • Urinary frequency or urgency: including frequent “just in case” voiding or difficulty delaying a trip to the toilet.
  • Mixed urinary incontinence: a combination of leakage with urgency and leakage with activities such as coughing or exercise. Bladder training can be combined with pelvic floor muscle training.
  • Urgency without leakage: urgency can still be bothersome and may respond to behavioural strategies.

The International Continence Society defines OAB as a symptom syndrome. It is not the same thing as a urodynamic finding called detrusor overactivity. Some people with OAB symptoms show involuntary bladder contractions during urodynamics; others do not. Urodynamics is not needed for every person with typical OAB symptoms. Overactive Bladder

What does “sensory overactive bladder” mean?

“Sensory urgency” or “sensory OAB” is sometimes used when a person feels an early or unusually strong need to pass urine, often at relatively small bladder volumes, but testing does not show involuntary detrusor contractions. The term is used inconsistently and is not a separate diagnosis in the current ICS symptom definition.

When infection, pain-related bladder conditions, obstruction, significant residual urine and other relevant causes have been considered, a person with urgency or increased bladder sensation may still be offered bladder training according to their symptoms and goals. A normal urodynamic study does not mean that the symptoms are imagined, and a finding of detrusor overactivity does not by itself determine which treatment is best.

Practical urge-control strategies

When an urge arrives before the planned time:

  1. Pause and stop moving if it is safe to do so. Sit or stand comfortably.
  2. Breathe slowly and allow the abdomen and pelvic floor to soften.
  3. Avoid rushing, which can increase the sense of urgency.
  4. If you can contract and fully release the pelvic floor comfortably, a few brief, gentle contractions may help suppress the urge. Then let the muscles go completely.
  5. When the urgency has eased, walk calmly to the toilet if you still need to go.

The approach should be adjusted if contractions cause pain, increase urgency, or make it harder to empty. Repeatedly delaying urination despite pain, a very full bladder, or difficulty passing urine is not the aim.

Pelvic floor muscle training for stress urinary incontinence

Stress urinary incontinence (SUI) is leakage with coughing, sneezing, laughing, lifting or exercise. It commonly occurs when the urethral closure mechanism and its support do not respond adequately to a rise in abdominal pressure.

For SUI, pelvic floor muscle training (PFMT) aims to improve the muscles’ strength, endurance, timing and coordination. Guidelines recommend a supervised programme for at least three months as an initial treatment for women with SUI or mixed incontinence. Training is also commonly used in men recovering from prostate surgery, with advice tailored to their operation and recovery. NICE

A correct contraction should feel like a gentle closing and lifting around the openings of the pelvic floor. It should not feel like pushing down, holding your breath, or tightening the buttocks and thighs instead. Each contraction needs a complete release afterwards. A pelvic health physiotherapist or clinician can check that the muscles are being used correctly and can tailor the programme to the person.

For leakage with a cough or lift, a physiotherapist may teach a brief pelvic floor contraction just before and during the effort. This is sometimes called “the knack.” It is a coordination strategy, not a substitute for a progressive strengthening programme.

PFMT can also support urgency control when a person can contract and relax the muscles correctly. It may be combined with bladder training for OAB or mixed symptoms. However, a high number of forceful contractions is not suitable for everyone.

When pelvic floor relaxation may be the priority

Some people have pelvic floor muscles that are persistently tense, tender, difficult to coordinate, or unable to relax fully during urination or bowel movements. This may be described as a high-tone, overactive or non-relaxing pelvic floor. Symptoms can include pelvic pain or pressure, difficulty starting the stream, straining, a stop-start stream, a feeling of incomplete emptying, constipation, pain with sexual activity, or urinary urgency and frequency. These symptoms have other possible causes as well, so assessment matters.

When examination suggests that the pelvic floor is overactive or does not relax appropriately, treatment may focus first on down-training and coordination, often with a pelvic health physiotherapist. This can include relaxed diaphragmatic breathing, awareness of pelvic floor release, comfortable toileting posture, avoiding straining, and addressing constipation or pain. Biofeedback may be used in selected cases. The aim is not to push or bear down forcefully, but to learn a comfortable release.

In this situation, repeatedly doing “Kegels” without assessment may aggravate pain, urgency or difficulty emptying for some people. The evidence for relaxation-based treatment is less extensive than the evidence supporting supervised strengthening for SUI, but guidelines support relaxation-focused pelvic floor therapy for selected functional emptying problems. Uroweb

Relaxation is not the opposite treatment for ordinary stress incontinence. If the main problem is leakage with exertion and the pelvic floor is weak or poorly coordinated, strengthening and timing are usually the relevant goals. If a person has both stress leakage and a tight, painful or poorly relaxing pelvic floor, a clinician or physiotherapist can sequence the treatment: first restore comfortable release and coordination where needed, then progress to strengthening without reinforcing excessive tension.

When to seek assessment

A clinician may review the symptom pattern, medications, fluid and caffeine intake, bowel habits, urine test, bladder diary, pelvic floor function and how well the bladder empties. Further tests are considered when the diagnosis is uncertain or when results could change management.

Seek medical advice rather than relying on bladder training alone if you have visible blood in the urine, painful urination or fever, new difficulty passing urine, a persistent weak stream, recurrent infections, significant pelvic pain, new neurological symptoms, or a sudden change in bladder control. These symptoms can have causes that need specific assessment.

Key points

  • Bladder training is a first-line behavioural option for urgency, frequency, OAB symptoms and many cases of mixed incontinence.
  • “Sensory OAB” is an imprecise term; urgency can be real and treatable even when urodynamics does not show detrusor overactivity.
  • Supervised pelvic floor muscle training is a first-line treatment for SUI, but correct contraction and full relaxation matter.
  • A tight or non-relaxing pelvic floor may need relaxation and coordination work before strengthening.
  • The best programme is based on an assessment, not on the assumption that every pelvic floor needs more squeezing.

This article provides general information and is not a substitute for an individual assessment or treatment advice.

References

  1. National Institute for Health and Care Excellence (NICE). Urinary incontinence and pelvic organ prolapse in women: management (NG123).
  2. NICE. Pelvic floor dysfunction: prevention and non-surgical management (NG210).
  3. European Association of Urology (EAU). Guidelines on Non-neurogenic Female LUTS: Disease Management.
  4. International Continence Society (ICS). Overactive bladder: terminology and public factsheet.
  5. American Urological Association/Society of Urodynamics, Female Pelvic Medicine & Urogenital Reconstruction. The AUA/SUFU Guideline on the Diagnosis and Treatment of Idiopathic Overactive Bladder (2024).
  6. McAuley JA, Mahoney AT, Austin MM. Clinical Practice Guidelines: Rehabilitation Interventions for Urgency Urinary Incontinence, Urinary Urgency, and/or Urinary Frequency in Adult Women. Journal of Women’s & Pelvic Health Physical Therapy. 2023;47(4):214–216. doi:10.1097/JWH.0000000000000287.

Your Bladder and Your Bowels: The Connection Nobody Talks About

The bowel–bladder connection: how good bowel habits can support bladder health

When urinary urgency or leakage is troubling you, bowel habits may be the last thing on your mind. Yet the bowel and bladder share the limited space of the pelvis, the pelvic floor muscles and parts of their nerve supply. Constipation can contribute to urinary symptoms in some people, so bowel health is often worth discussing during a bladder assessment.

This does not mean that constipation explains every bladder problem. Infection, prostate or pelvic floor conditions, medication effects, neurological conditions and other causes may need to be considered too.

How can constipation affect the bladder?

A full rectum can press on the bladder and change the space available for it to fill. In some people this may increase urinary urgency or frequency, contribute to urgency leakage, or make it harder to empty the bladder comfortably. Constipation and bladder symptoms may also occur together because of shared pelvic floor or neurological problems.

The relationship is not the same for everyone, and constipation is only one possible contributor. Bladder symptoms should be assessed on their own merits, especially if they are new, persistent or worsening.

Some medicines used for bladder symptoms, including anticholinergic medicines, can make constipation worse. Pain medicines, iron and some other medicines can also affect bowel habits. If you think a medicine may be contributing, discuss it with your doctor or pharmacist rather than stopping it yourself.

The pelvic floor connection

The pelvic floor is a group of muscles and connective tissues that supports the bladder, bowel and other pelvic organs. It helps maintain urinary and bowel control, and it must also relax and coordinate when you empty your bladder or bowel.

Repeated straining to pass hard stool can place ongoing pressure on the pelvic floor. A pelvic floor that is weak, painful, tense or poorly coordinated may affect both bladder and bowel emptying or control. Treatment therefore depends on what the muscles are doing: strengthening is useful for some forms of leakage, while people who cannot relax or coordinate the pelvic floor may need a different approach, sometimes with a pelvic health physiotherapist.

How are the bladder and bowel nerves connected?

The bladder and rectum have different jobs, but their nerve pathways meet and interact through the spinal cord, pelvic nerve networks and the brain. The pathways below are a simplified guide; the actual nerve networks are interconnected.

Nerve pathway Main spinal levels Role in bladder and bowel function
Pelvic splanchnic nerves (parasympathetic) S2–S4 Help the bladder contract to empty and contribute to rectal activity and bowel emptying. They also carry important sensation from the lower urinary tract and rectum.
Hypogastric nerves (sympathetic) About T11–L2 Support bladder storage by relaxing the bladder wall and helping maintain outlet closure. They also contribute to bowel storage and internal anal sphincter function.
Pudendal nerves (somatic) S2–S4 Provide voluntary control of the external urethral sphincter, external anal sphincter and parts of the pelvic floor. These muscles help maintain continence and must coordinate with relaxation during emptying.

Bladder filling and emptying, bowel filling and defecation are coordinated with pelvic floor activity and brain control. Because some of these pathways and muscles are shared, neurological conditions or injuries affecting the brain, spinal cord or sacral nerves can affect both bladder and bowel function. A full rectum can also alter the local pressure and sensory environment around the bladder.

Constipation is not only about how often you go

Bowel frequency varies. Not having a bowel motion every day does not, by itself, mean you are constipated. It is also important to mention:

  • hard or lumpy stools;
  • needing to strain or push repeatedly;
  • discomfort or pain when passing stool;
  • a feeling that the bowel has not emptied completely; or
  • needing to use your fingers or change position to help stool pass.

A short bowel diary, used alongside a bladder diary, can help identify whether urinary urgency or leakage changes when constipation is worse.

Good bowel habits to support pelvic health

A few practical habits may help maintain regular, comfortable bowel movements:

  1. Respond to the urge. Try not to repeatedly postpone a bowel motion. Many people find it helpful to allow unhurried time after a meal, when the bowel may be more active.
  2. Use a comfortable position. Sit with your feet supported on a small footstool so your knees are a little higher than your hips. Lean forward with your forearms on your thighs and keep your abdomen relaxed.
  3. Avoid prolonged straining. Breathe out gently rather than holding your breath and pushing hard. If stool will not pass, get up and try again later instead of sitting and straining for a long time.
  4. Eat a varied, fibre-containing diet. Whole grains, vegetables, fruit, legumes, nuts and seeds can help. Increase fibre gradually to reduce bloating. Adults’ fibre needs vary; one commonly used guide is around 22–34 grams a day, adjusted for age, health and tolerance.
  5. Drink an appropriate amount. Adequate fluid helps fibre work and can soften stool. Your needs vary, and people who have been advised to restrict fluids because of heart, kidney or other conditions should follow their treating clinician’s advice. Restricting fluids to manage urinary frequency may worsen constipation.
  6. Keep moving regularly. Walking and other suitable physical activity can support bowel function.
  7. Review medicines and ongoing symptoms. Ask your doctor or pharmacist whether medicines may be contributing. Persistent constipation may need tailored treatment; a clinician can advise whether dietary changes, a laxative or pelvic floor assessment is appropriate.

If you have difficulty relaxing the pelvic floor or feel that stool is blocked despite soft stools, simply adding more fibre or doing repeated pelvic floor squeezes may not solve the problem. Ask about an assessment of bowel emptying and pelvic floor coordination.

Looking beyond the bladder

Improving bowel habits may reduce one contributor to bladder symptoms, but it is not a substitute for investigating persistent urinary problems. A clinician may ask about both bladder and bowel symptoms, review medications, test the urine and check how well the bladder empties. Further assessment depends on the symptoms and medical history.

Seek medical advice for ongoing or worsening urgency, leakage, difficulty passing urine or constipation. Blood in the urine or stool, severe abdominal pain, vomiting, inability to pass urine, or a sudden major change in bowel or bladder control needs prompt medical attention.

This article provides general information and is not a substitute for individual medical advice.

References

  1. Queensland Spinal Cord Injuries Service. Bowel and bladder relationship.
  2. Continence Health Australia. Constipation.
  3. Australian Government Department of Health, Disability and Ageing. Bladder and bowel health: recognising a problem.
  4. National Institute of Diabetes and Digestive and Kidney Diseases. Eating, diet and nutrition for constipation and prevention of bladder control problems.
  5. de Groat WC, Griffiths D, Yoshimura N. Neural control of the lower urinary tract. Comprehensive Physiology. 2015;5(1):327–396. doi:10.1002/cphy.c130056.
  6. StatPearls. Anatomy, abdomen and pelvis: pelvic floor.


Painful Ejaculation: The Symptom Men Rarely Talk About

Painful ejaculation: causes, assessment and treatment

Pain during or after ejaculation can be difficult to mention, even to a doctor. Some men hope it will disappear; others avoid sex because they worry the pain will return.

Painful ejaculation, sometimes called dysejaculation or dysorgasmia, is a symptom, not a diagnosis. It can have several causes, including infection, inflammation, pelvic floor problems, medication effects or, less commonly, a blockage in the passages that carry semen. The pattern of symptoms and the findings on assessment help guide the next steps.

What can painful ejaculation feel like?

The experience varies. Pain may be burning, sharp, cramping or a deeper ache. It can be felt in the penis, testicles, scrotum, perineum (the area between the scrotum and anus), lower abdomen or pelvis.

It may begin during orgasm or ejaculation, just afterwards, or continue for minutes or hours. It may occur every time or only occasionally. Some men also notice urinary symptoms, blood in the semen, changes in the amount of semen, erection or orgasm changes, or pain with bowel movements.

The details are useful: where the pain is, when it starts, how long it lasts, whether it is linked to urination or a particular activity, and whether it is changing over time.

What can cause painful ejaculation?

Prostate or pelvic pain conditions

Inflammation or infection of the prostate can cause painful ejaculation, sometimes with pelvic discomfort, urinary frequency, burning when passing urine or difficulty urinating. Acute bacterial prostatitis may cause fever and feeling unwell and needs prompt medical assessment.

Many men with persistent pelvic pain have chronic prostatitis/chronic pelvic pain syndrome (CP/CPPS). This is not necessarily a bacterial infection. Symptoms can involve the perineum, penis, testicles or lower abdomen and may include urinary or sexual symptoms. Pelvic floor muscle tension, nerve sensitivity and other factors can contribute. Repeated antibiotic courses are not appropriate when there is no evidence of a bacterial infection. Painful ejaculation is a recognised feature of chronic pelvic pain, but it can have other causes too. Oxford Academic

Urethral or genital infection

Urethritis, including a sexually transmitted infection (STI), can cause pain or burning during urination and ejaculation. Infection or inflammation involving the epididymis or testicle can also be painful. Discharge, a new sexual partner, testicular tenderness, fever or urinary burning may guide testing.

Pelvic floor muscle tension or poor coordination

The pelvic floor muscles contract and coordinate during ejaculation. If they are tender, overactive or unable to relax, ejaculation may trigger pelvic or perineal pain. This may occur on its own or as part of a broader chronic pelvic pain syndrome. A pelvic health physiotherapist can assess muscle coordination and tenderness when indicated.

Narrowing or obstruction in the semen pathway

A narrowing of the urethra, ejaculatory duct obstruction, or a problem involving the seminal vesicles may cause pain in selected cases. A previous vasectomy or surgery affecting the prostate, bladder, urethra or pelvis may also be relevant. These causes are less common and usually require targeted investigation rather than assuming that obstruction is present.

Medicines, procedures and radiotherapy

Some medicines have been reported to cause painful ejaculation or changes in orgasm. The timing of symptoms in relation to starting or changing a medicine can be helpful. Do not stop a prescribed medicine without discussing it with the prescriber.

Pain may also follow pelvic surgery, instrumentation or radiotherapy. The cause and appropriate assessment depend on the procedure and when the symptoms began.

Other contributors

Nerve-related pain, chronic medical conditions and psychological or relationship stress can influence the experience of pain. This does not mean the pain is “all in your head.” Pain is real, and several physical, nervous-system and emotional factors can interact.

Sometimes no single cause is identified. Even then, a structured assessment can help select reasonable symptom-management options.

How is painful ejaculation investigated?

Testing is guided by the history and examination. Not every man needs a scan, cystoscopy or extensive testing. Current sexual-medicine recommendations advise assessing painful ejaculation along established pelvic-pain pathways, with tests and imaging chosen according to symptoms. Oxford Academic

1. A detailed history

Your doctor may ask about:

  • where the pain occurs, when it starts and how long it lasts;
  • whether it happens with every ejaculation or only in certain situations;
  • urinary symptoms such as burning, urgency, weak stream or difficulty emptying;
  • blood in the urine or semen, discharge, fever or testicular swelling;
  • recent sexual partners or possible STI exposure;
  • previous infections, vasectomy, pelvic surgery, radiotherapy or urinary procedures;
  • medicines and recent dose changes; and
  • how the symptoms affect sexual activity, fertility plans and quality of life.

You do not need technical language. Describing what happens in your own words is a good starting point.

2. Examination

Depending on the symptoms, examination may include the abdomen, penis, testicles, epididymides and groin. A prostate or pelvic floor examination may be considered when it is likely to help identify the cause. The examination should be explained and performed with your consent.

3. Urine and infection testing

A urine test and culture may be used to look for a urinary infection. STI testing, often using a urine sample or swab, may be appropriate based on symptoms and sexual history. Blood tests are sometimes used if there are signs of systemic infection or another specific concern.

Antibiotics should be directed at a suspected or confirmed bacterial infection. Painful ejaculation alone does not prove that an infection is present.

4. Tests for urinary or structural problems

If there are urinary symptoms, a clinician may measure urine flow or check the amount left in the bladder after urination. Further investigations are selected according to the suspected cause:

  • Ultrasound or other imaging may be considered for testicular symptoms, suspected seminal vesicle or ejaculatory duct problems, or persistent unexplained pain.
  • Cystoscopy or urethral imaging may be appropriate if a urethral narrowing, bleeding or another urethral problem is suspected.
  • Prostate-specific antigen (PSA) testing is considered selectively based on age, examination and prostate-cancer risk. It is not a test for painful ejaculation itself and may be misleading during active infection or inflammation.
  • Semen testing is not routinely required for every man with painful ejaculation, but may be considered when fertility or a specific semen-pathway problem is part of the question.

How is painful ejaculation managed?

Treatment depends on the cause and on how much the symptom affects you. There is no single treatment that suits everyone. Guidelines recommend tailoring care to the likely cause; procedures are generally reserved for selected cases with a demonstrated structural problem because evidence for surgery for unexplained pain is limited. Uroweb

  • Confirmed or strongly suspected infection: treatment may include the appropriate antibiotic or other infection-specific care. If an STI is diagnosed, partner testing or treatment and avoiding sex until treatment is complete may be advised.
  • Medication-related symptoms: the prescriber may review the timing, dose or alternatives. Do not change medication on your own.
  • Chronic pelvic pain or pelvic floor tenderness: care may include pelvic floor physiotherapy focused on relaxation and coordination, pain-management strategies, and selected medicines. Strengthening exercises are not automatically appropriate if the muscles are already tight or painful.
  • Urinary symptoms: treatment may be directed at an identified urinary condition. For some men, a clinician may consider an alpha-blocker or other targeted treatment.
  • A defined obstruction or structural problem: a urologist may discuss a procedure if investigations confirm a cause and symptoms justify it. Procedures are not routine for unexplained pain, and potential effects on ejaculation and fertility should be discussed.
  • No clear cause found: trigger modification, review of sexual activity patterns, supportive counselling or a multidisciplinary chronic-pain approach may help. The plan can be adjusted over time.

The evidence for specific treatments of painful ejaculation is limited, so decisions are usually tailored to the likely cause and the individual’s priorities.

When should you seek urgent care?

Seek prompt medical attention if painful ejaculation occurs with fever or shaking chills, feeling very unwell, inability to pass urine, sudden severe testicular pain or swelling, or visible blood in the urine. These symptoms may need urgent assessment. Blood in the semen should also be discussed with a doctor, particularly if it recurs or occurs with other symptoms. NHS

Starting the conversation

You do not need medical terminology. You can simply say: “I have pain when I ejaculate.” If it is recurring, worsening or affecting intimacy, speak with your GP. They can begin the assessment and arrange urology referral if needed.

This article provides general information and is not a substitute for individual medical advice.

References

  1. Shindel AW, Serefoglu EC, et al. Review of recent data on disorders of ejaculation and orgasm in men: recommendations from the Fifth International Consultation on Sexual Medicine. Sexual Medicine Reviews. 2025;13(3):318–337. doi:10.1093/sxmrev/qeaf016.
  2. European Association of Urology. Guidelines on Sexual and Reproductive Health: Disorders of Ejaculation.
  3. American Urological Association. Diagnosis and Management of Male Chronic Pelvic Pain: AUA Guideline (2025).
  4. Donatucci CF, et al. Contemporary management of ejaculatory dysfunction. Translational Andrology and Urology. 2018. Full text.
  5. Acharya S, et al. Painful ejaculation—an ignored symptom. Sexual Medicine Reviews. 2020. Full text.
  6. NHS. Prostatitis and Blood in semen.

Hydronephrosis: what it means and how it is treated

Finding out that a kidney is swollen on a scan can be worrying. The word hydronephrosis sounds like a diagnosis, but it describes an appearance: urine is collecting and stretching the drainage system of one or both kidneys. It is a sign that needs to be understood in context. It does not, by itself, tell us why it has happened, whether a cancer is present, or whether an operation is needed.

Many causes are treatable, and some cases can be monitored safely. The right approach depends on the cause, the degree and duration of blockage, kidney function, symptoms, overall health and, when cancer is involved, what matters most to the person receiving care.

What are unilateral and bilateral hydronephrosis?

Each kidney drains urine through a tube called a ureter into the bladder. Unilateral hydronephrosis affects one kidney; bilateral hydronephrosis affects both. A blockage may be within the kidney or ureter, or lower down where it affects the bladder outlet. A full bladder or difficulty emptying can sometimes cause dilation on both sides.

One healthy kidney can often maintain overall kidney function when the other side is obstructed. This can mean that a person with a one-sided blockage has few symptoms and normal blood tests. With obstruction affecting both kidneys, or a person who has only one functioning kidney, kidney function can become impaired more quickly. The scan appearance alone does not show how well each kidney is working.

What can cause hydronephrosis?

Causes may be benign (non-cancerous) or malignant (related to cancer). They include:

  • Kidney or ureteric stones, which may block urine flow and cause pain, blood in the urine or infection.
  • Narrowing or scarring of the ureter (a stricture), sometimes following previous surgery, instrumentation, infection or radiation treatment.
  • Bladder outlet obstruction or poor bladder emptying, including from an enlarged prostate before prostate surgery, urethral narrowing, a tight bladder-neck/anastomotic scar after surgery, or a bladder that does not contract effectively.
  • Anatomical or functional conditions, such as a narrowing where the kidney joins the ureter (a pelvi-ureteric junction obstruction), reflux of urine towards the kidney, or in some circumstance, pregnancy.
  • Blood clots or inflammation, which can temporarily obstruct drainage.
  • Cancer, either growing in the urinary tract or pressing on a ureter from nearby tissues or lymph nodes. Possible cancers include prostate, bladder, bowel, gynaecological and other pelvic or abdominal cancers. A cancer-related cause is only one possibility; imaging and clinical assessment are needed to establish the cause.

Prostate cancer and hydronephrosis

Prostate cancer can affect urine drainage in different ways. A locally advanced tumour may involve the bladder outlet or the area where the ureters enter the bladder. Cancer in pelvic or abdominal lymph nodes can press on one or both ureters. These problems are more likely with locally advanced or recurrent disease than with an early cancer confined to the prostate, but each person’s situation is different.

Hydronephrosis in someone who has had prostate cancer does not automatically mean the cancer has returned. Stones, infection, scarring, bladder-emptying problems and unrelated conditions remain possible. The team will consider the person’s history, prostate-specific antigen (PSA) trend, symptoms, blood and urine tests, and the pattern seen on imaging. Further tests may be appropriate if the cause is not clear.

After radical prostatectomy

After prostate removal, the bladder is joined to the urethra. Scarring at this join (a vesicourethral anastomotic stenosis, sometimes called a bladder-neck contracture) can make it difficult to empty the bladder. Significant retention may raise pressure in the bladder and contribute to dilation of both upper urinary tracts. A ureteric injury or later narrowing is a less common possibility. Recurrent cancer or enlarged lymph nodes can also obstruct a ureter, but this is not the only explanation.

Assessment may include checking bladder emptying, kidney function and imaging, with a camera examination or contrast study if needed. Treatment is directed at the level and cause of the blockage: for example, bladder drainage, treatment of a narrowing, or drainage of an obstructed ureter.

After salvage radiation therapy

Radiation can cause inflammation and, less commonly, delayed scarring in urinary tissues. Narrowing of the urethra or bladder outlet can interfere with emptying. A ureteric stricture after pelvic radiation is uncommon, but may develop months or years later. Salvage radiation after prostatectomy is generally directed to the prostate bed; hydronephrosis that appears afterwards still needs a proper assessment rather than being assumed to be a radiation effect or a cancer recurrence.

If imaging shows a narrowed ureter, the team may use CT or MRI, a contrast study, or a functional kidney scan to clarify its site, length and effect on kidney drainage. Treatment can be more complex in previously irradiated tissue, so decisions are individualised and may involve a reconstructive urologist, radiation oncologist, medical oncologist or interventional radiologist.

Symptoms and when to seek urgent care

Hydronephrosis can cause no noticeable symptoms, particularly when it develops gradually or affects one kidney. When symptoms occur, they may include pain in the side, back or abdomen; nausea or vomiting; blood in the urine; difficulty passing urine; or repeated urinary infections.

Please seek urgent medical assessment for fever or shaking chills with suspected urinary blockage, severe or worsening pain, repeated vomiting, very little or no urine, confusion, or feeling suddenly very unwell. Infection behind a blockage can become serious and may need urgent antibiotics and drainage. Sudden inability to pass urine also needs prompt care.

How is it investigated?

The first aim is to understand whether there is a blockage that needs prompt relief and what is causing it. Assessment commonly includes:

  1. A conversation and examination, including previous cancer treatments, operations, stones, infections, urinary symptoms and medicines.
  2. Blood tests, especially creatinine and estimated kidney function, and urine tests for infection or blood.
  3. Ultrasound, which can show dilation of the kidneys and bladder and whether the bladder empties.
  4. CT or MRI, selected according to the suspected cause and the person’s kidney function, to look for stones, strictures, masses or enlarged lymph nodes.
  5. Additional tests where useful: a MAG3 renal scan can assess each kidney’s contribution and drainage; cystoscopy or contrast X-rays can clarify the bladder outlet or ureter.

Not everyone needs every test. The clinician will choose investigations that answer the question while taking account of kidney function, previous treatment and the person’s circumstances.

Management options

Treatment is tailored to the cause and the degree of risk. The goals may be to protect kidney function, treat infection or pain, restore urine flow, enable other cancer treatment, or support comfort and quality of life.

Observation and treatment of the cause

Mild, stable hydronephrosis may sometimes be monitored with repeat blood tests and imaging, particularly if there is no infection, troublesome pain or evidence of kidney function decline. A stone may pass or be treated with medication, ureteroscopy or another stone procedure. Infection is treated with antibiotics. Retention may be relieved with a bladder catheter while the cause is assessed. A benign narrowing may be treated by endoscopic incision or dilation, reconstruction, or another procedure depending on its location and the person’s health.

Draining the kidney

If drainage is needed, there are two common approaches:

  • Ureteric stent (often called a JJ stent): a thin internal tube placed between the kidney and bladder, usually using a camera. It can avoid an external collection bag, but may cause urinary frequency, urgency, discomfort, blood in the urine or infection, and it usually needs planned replacement or removal. A tight narrowing or external cancer pressure can make stent placement difficult or less reliable.
  • Percutaneous nephrostomy: a small tube placed through the skin of the back into the kidney, usually by an interventional radiologist, to drain urine into an external bag. It can be useful when a stent cannot be placed, has not drained adequately, or rapid reliable drainage is needed. The tube needs care and periodic changes and can affect daily activities.

The choice depends on the site and cause of obstruction, infection, anatomy, kidney function, expected duration, other treatment plans and personal preference. Sometimes a nephrostomy is used first, with an internal stent considered later. Drainage can relieve pressure and help kidney function, but it does not remove the underlying cause; further treatment or monitoring is often needed.

When might palliative care be part of the plan?

“Palliative” can sound frightening, but palliative care is focused on comfort, symptom relief, support and quality of life. It can be provided alongside active cancer treatment. It does not mean that someone is being abandoned or that all treatment has stopped.

When hydronephrosis is caused by advanced cancer, a stent or nephrostomy may help with pain, infection, kidney function, or the ability to receive cancer treatment. It can also bring burdens such as procedures, hospital visits, tube or stent symptoms, repeat exchanges and complications. In some situations, drainage may not improve symptoms or kidney function enough to outweigh those burdens. Evidence in this area is limited, and outcomes vary widely; population averages cannot predict an individual person’s future.

There is no single point at which palliation is “required.” The decision is made with the patient, their chosen supports and the treating team. It can help to discuss:

  • What problem are we hoping drainage will improve?
  • How likely is it to help, and how soon might we know?
  • What would living with a stent or nephrostomy involve?
  • Could the result allow another treatment that matters to me?
  • What might happen if we monitor or manage symptoms without drainage?
  • What matters most to me now: time at home, symptom relief, kidney function, further cancer treatment, or avoiding procedures?

Choosing not to have a procedure is also a valid choice when it best fits a person’s wishes and clinical circumstances. The team can still treat pain, nausea, infection and other symptoms, and provide practical and emotional support. These conversations are best held early and revisited as circumstances change.

In summary

Hydronephrosis means that urine is collecting in one or both kidneys, but it does not identify the cause on its own. Many causes are benign and treatable. Prostate cancer, previous prostate surgery and radiation can be relevant, but a careful assessment is needed before drawing conclusions. Some people need urgent drainage; others can be monitored or treated in a less invasive way. When cancer is advanced, decisions about drainage and palliative care should be compassionate, individualised and guided by what is most important to the person.

References and further reading

  1. National Kidney Foundation. Hydronephrosis. Updated 2023.
  2. Mayo Clinic. Hydronephrosis: Diagnosis and treatment. Updated 2024.
  3. European Association of Urology. EAU Guidelines on Urolithiasis. See section on sepsis and anuria in an obstructed kidney.
  4. National Institute for Health and Care Excellence. Prostate cancer: diagnosis and management (NG131). Includes recommendations on upper urinary tract decompression for obstructive uropathy secondary to hormone-relapsed prostate cancer.
  5. Chorbińska J, Krajewski W, Zdrojowy R. Urological complications after radiation therapy—nothing ventured, nothing gained: a narrative review. Transl Androl Urol. 2021;10(8):3553–3566. doi:10.21037/tau-20-1217.
  6. Carilli M, et al. Management of ureteral stricture disease after radiation therapy for pelvic malignancies. Cancers (Basel). 2024;16(21):3561. doi:10.3390/cancers16213561.
  7. Shah M, et al. Malignant upper urinary tract obstruction in cancer patients: a systematic review. BJUI Compass. 2024;5(11):915–925. doi:10.1002/bco2.340.
  8. Gauhar V, et al. Nephrostomy tube versus double J ureteral stent in patients with malignant ureteric obstruction: a systematic review and meta-analysis of comparative studies. Int Braz J Urol. 2022;48(6):903–914. doi:10.1590/S1677-5538.IBJU.2022.0225.

This page provides general information and is not a substitute for an individual assessment by a qualified health professional. If you have hydronephrosis, your clinician can explain what the scan means in your circumstances and whether further tests or treatment are needed.