Tag Archive for: best urologist brisbane

Testicular rupture: causes, warning signs, diagnosis and treatment

Testicular rupture is a surgical emergency. It occurs when trauma tears the tough outer covering of the testis (the tunica albuginea), allowing testicular tissue to protrude through the defect. Prompt assessment offers the best opportunity to control bleeding, relieve pain and preserve viable testicular tissue.

Seek urgent medical care: After an injury, go promptly to the nearest emergency department if there is severe or increasing scrotal pain, marked swelling or bruising, nausea or vomiting, a testis that feels abnormal or cannot be clearly felt, an open wound, or blood at the urinary opening or in the urine. Do not delay assessment while waiting to see whether the swelling settles.

What causes a testicular rupture?

Most ruptures follow a forceful, direct blow that compresses the testis against the pubic bone. Causes include:

  • contact sport, particularly without an appropriate protective cup;
  • bicycle or motorcycle accidents and straddle injuries;
  • falls, motor-vehicle trauma, workplace injuries or assault;
  • a kick, ball or other high-impact object striking the scrotum; and
  • penetrating trauma, such as a stab, gunshot, machinery injury or animal bite.

A major blunt injury can also cause a scrotal haematoma, haematocele (blood around the testis), testicular contusion, torsion, fracture without tunical rupture, or injury to the epididymis or spermatic cord. These conditions can look similar, and more than one injury may be present.

How does it present?

Typical features include immediate severe pain followed by rapidly developing swelling, tenderness and bruising. Nausea, vomiting or faintness may occur. The normal outline of the testis may be difficult to feel because of pain and swelling. An open injury, scrotal skin loss or bleeding may be present after penetrating or high-energy trauma.

Symptoms alone cannot reliably distinguish rupture from torsion or other serious injury. Testicular torsion may occur with or without trauma and is also time-critical. A seemingly modest external bruise does not exclude a significant internal injury.

Assessment and investigation

Assessment begins with the circumstances and timing of the injury, examination of both testes and the scrotum, and checking for injury to the penis, urethra, pelvis and abdomen where relevant. Blood at the urethral opening, difficulty passing urine or visible blood in the urine requires assessment for associated urinary-tract injury.

Ultrasound with Doppler

High-resolution scrotal ultrasound with colour Doppler is the preferred first-line imaging test for blunt testicular trauma. Findings that may indicate rupture include:

  • loss of the smooth testicular contour;
  • disruption of the tunica albuginea;
  • heterogeneous testicular tissue;
  • protrusion of tissue through a tunical defect;
  • reduced or absent blood flow; and
  • a surrounding haematocele.

Ultrasound is very useful but is not infallible. Pain, extensive swelling, haematoma and operator or equipment factors can make interpretation difficult. The 2026 European Association of Urology (EAU) guideline strongly recommends ultrasound for testicular trauma and surgical exploration for confirmed rupture and for inconclusive ultrasound when rupture remains a concern. Imaging should not cause an avoidable delay when the clinical findings clearly warrant surgery.

CT is useful for associated abdominal or pelvic trauma but is not the usual test for deciding whether the testis has ruptured. MRI is occasionally considered when ultrasound is equivocal and immediate exploration is not otherwise indicated, but it should not delay necessary surgery.

Treatment

Immediate care

In hospital, initial treatment may include appropriate pain relief, fasting in preparation for possible anaesthesia, scrotal support and management of other injuries. Open or contaminated wounds require wound care; tetanus status and antimicrobial treatment are considered according to the mechanism, contamination and local protocols.

Surgical exploration and repair

Confirmed or strongly suspected rupture is generally treated by urgent scrotal exploration. During surgery, the surgeon will usually:

  1. evacuate blood clot and inspect the testis and surrounding structures;
  2. control bleeding;
  3. remove only tissue that is clearly non-viable;
  4. preserve as much healthy, perfused testicular tissue as possible; and
  5. close the tunica albuginea, sometimes using local tissue coverage when primary closure would place the remaining testis under excessive tension.

Associated injuries to the epididymis or spermatic cord are addressed where possible. A drain may occasionally be used. After surgery, patients commonly require scrotal support, analgesia, wound care and temporary restriction of sport, heavy lifting and sexual activity. The exact plan depends on the injury and operation.

Older clinical series reported testicular salvage rates around 80–90% when rupture was recognised and repaired promptly. These figures describe groups of patients and cannot predict an individual result. The chance of salvage depends on the energy and type of trauma, the amount of tissue destruction, blood supply, contamination, associated injuries and time to treatment.

Is non-operative treatment ever suitable?

Minor trauma with an intact tunica, preserved blood flow and a small, stable haematoma may sometimes be managed with observation, analgesia, ice used safely, scrotal support and arranged review. This is not the usual management for a confirmed rupture. Increasing pain, swelling, fever or other deterioration requires urgent reassessment.

When is orchidectomy necessary?

Orchidectomy means removal of a testis. It is not the preferred treatment when viable tissue can be repaired. It may nevertheless be necessary when the testis is completely shattered, devascularised or infarcted; the spermatic cord is irreparably damaged or avulsed; bleeding cannot otherwise be controlled; contamination and tissue destruction are extreme; or no meaningful viable tissue remains.

The decision is usually made during exploration after blood supply and tissue viability have been assessed. Surgeons aim to conserve viable testicular tissue, but retaining a completely non-viable testis can expose the patient to infection, persistent pain and further surgery. Severe penetrating injuries and delayed treatment are more likely to require orchidectomy than a limited rupture treated early.

If removal is required, a testicular prosthesis can be discussed. It is cosmetic and does not make sperm or testosterone. Placement may be performed at the same operation or later, depending on contamination, swelling, patient preference and clinical circumstances.

Effects on fertility and testosterone

The effect on fertility varies considerably.

  • Unilateral injury: A healthy opposite testis will often produce enough testosterone and sperm for normal sexual development, erections and natural conception. However, normal fertility cannot be guaranteed. Trauma itself, loss of testicular volume, later atrophy and unilateral orchidectomy can reduce sperm reserve.
  • Testicular repair: Preserving viable tissue is generally preferred and may better preserve sperm-producing and hormonal function. Small human follow-up studies suggest that semen abnormalities can occur after trauma even when testosterone remains normal; the evidence is limited by small patient numbers.
  • Bilateral injury or a solitary testis: The risk to fertility and testosterone production is much greater. Loss of both testes causes permanent infertility and requires long-term testosterone replacement. Preservation of even a portion of viable tissue may therefore be especially important.

For severe bilateral injury, injury to a solitary testis, pre-existing subfertility, or concern about future family planning, early discussion with a urologist and fertility specialist is appropriate. Semen analysis, reproductive hormone testing and sperm cryopreservation may be considered when feasible; emergency surgery should not be dangerously delayed to obtain a sample. Follow-up may include examination, ultrasound when indicated, testosterone, LH and FSH testing, and semen analysis after recovery if fertility is a concern.

Possible complications

Even after appropriate treatment, complications can include:

  • infection, wound problems or recurrent haematoma;
  • testicular atrophy or loss of blood supply;
  • persistent scrotal discomfort or chronic pain;
  • impaired sperm production or subfertility;
  • reduced testosterone production, particularly after bilateral injury;
  • the need for later surgery or orchidectomy; and
  • psychological distress or concern about body image and fertility.

Increasing pain or swelling, fever, wound discharge, skin discolouration, difficulty passing urine or feeling generally unwell after discharge warrants urgent medical review.

The practical message

Following significant scrotal trauma, early assessment matters. Ultrasound with Doppler is the main imaging investigation, but a reassuring-looking exterior, or an uncertain scan, does not safely exclude rupture. Timely exploration and repair provide the best opportunity to save viable testicular tissue. Orchidectomy is reserved for a testis that cannot be safely or meaningfully salvaged.


Important information

This article provides general health information and does not replace an examination, diagnosis, individual medical advice or informed consent. Treatment and outcomes vary according to the mechanism, severity, timing, associated injuries, health history and operative findings. If testicular rupture or torsion is suspected, seek urgent assessment at an emergency department.

References

  1. European Association of Urology. EAU Guidelines on Urological Trauma: Urogenital Trauma Guidelines (2026). Uroweb guideline.
  2. Morey AF, Brandes S, Dugi DD III, et al. Urotrauma: AUA Guideline. Journal of Urology. 2014;192:327–335. Full text via PubMed Central. Updated guideline information: American Urological Association.
  3. Morey AF, Broghammer JA, Hollowell CMP, McKibben MJ, Souter L. Urotrauma Guideline 2020: AUA Guideline. Journal of Urology. 2021;205(1):30–35. PubMed.
  4. Buckley JC, McAninch JW. Use of ultrasonography for the diagnosis of testicular injuries in blunt scrotal trauma. Journal of Urology. 2006;175(1):175–178. PubMed.
  5. Cass AS, Luxenberg M. Testicular injuries. Urology. 1991;37(6):528–530. PubMed.
  6. Lin WW, Kim ED, Quesada ET, Lipshultz LI, Coburn M. Unilateral testicular injury from external trauma: evaluation of semen quality and endocrine parameters. Journal of Urology. 1998;159(3):841–843. PubMed.
  7. Kukadia AN, Ercole CJ, Gleich P, Hensleigh H, Pryor JL. Testicular trauma: potential impact on reproductive function. Journal of Urology. 1996;156(5):1643–1646. PubMed.
  8. Yagil Y, Naroditsky I, Milhem J, et al. Role of Doppler ultrasonography in the triage of acute scrotum in the emergency department. Journal of Ultrasound in Medicine. 2010;29(1):11–21. PubMed.
  9. Australian Health Practitioner Regulation Agency. Guidelines for advertising a regulated health service and acceptable evidence in health advertising. Ahpra Advertising Hub.
  10. Therapeutic Goods Administration. Advertising health services that involve therapeutic goods (updated 18 June 2026). TGA guidance.


 

Radical Prostatectomy After Radiation Therapy for Prostate Cancer

When prostate cancer returns after radiotherapy

Radiotherapy, whether external-beam radiation or brachytherapy can provide excellent long-term control of localised prostate cancer. However, a rising prostate-specific antigen (PSA) after treatment may indicate that the cancer has returned.

This does not automatically mean that the cancer is still in the prostate, nor does every PSA rise require immediate treatment. Recurrence may be confined to the prostate, present in lymph nodes or bones, or involve more than one site. Some recurrences also progress slowly enough that surveillance may be appropriate.

When clinically significant cancer is proven to have returned within the irradiated prostate, with no evidence of spread elsewhere, removal of the prostate may still offer a chance of cure. This operation is called a salvage radical prostatectomy.

What is a salvage radical prostatectomy?

A salvage radical prostatectomy removes the entire prostate and seminal vesicles after previous prostate radiotherapy. Depending on the cancer and imaging findings, pelvic lymph nodes may also be removed.

The operation may be performed using robotic-assisted or open surgery. A robotic approach can improve magnification and access, but it does not remove the biological effects of previous radiation. Surgeon and centre experience are therefore more important than the label attached to the surgical technique.

Salvage surgery is technically more difficult than a prostatectomy performed before radiotherapy. Radiation can cause:

  • scarring and fibrosis around the prostate;
  • loss of the normal tissue planes between the prostate, bladder and rectum;
  • reduced tissue blood supply;
  • poorer tissue healing; and
  • pre-existing damage to urinary, erectile or bowel function.

For these reasons, salvage prostatectomy should generally be undertaken in a centre with specific experience in complex prostate cancer surgery and access to multidisciplinary care.

When might salvage surgery be considered?

The aim is to identify a man who has a meaningful risk from his recurrent cancer, but whose disease still appears curable with local treatment. Possible indications include:

  • a rising PSA after radiotherapy, commonly assessed using the Phoenix definition: a PSA rise of at least 2 ng/mL above the lowest PSA reached after treatment;
  • prostate cancer confirmed on biopsy after radiotherapy;
  • imaging suggesting that the recurrence is confined to the prostate or immediate surrounding tissues;
  • no evidence of distant metastatic disease;
  • a life expectancy long enough to benefit from curative treatment, often more than 10 years;
  • good general health and fitness for major surgery;
  • acceptable baseline bladder function; and
  • willingness to accept a higher risk of urinary and sexual side effects than with a primary prostatectomy.

Factors such as the PSA level, PSA doubling time, interval since radiotherapy, biopsy Grade Group, clinical stage and the original cancer characteristics help estimate whether salvage treatment is likely to be worthwhile.

Assessment before considering surgery

A rising PSA is the beginning of the assessment—not the final diagnosis. Investigations commonly include:

Review of the original treatment

The radiation dose and field, use of brachytherapy, previous androgen-deprivation therapy, original biopsy grade and pre-treatment imaging should all be reviewed.

Multiparametric MRI

MRI can help identify the site and extent of a local recurrence, assess the seminal vesicles, bladder neck and rectal interface, and guide biopsy. Interpretation after radiation can be challenging and benefits from specialist radiological expertise.

PSMA PET/CT

PSMA PET/CT is used to look for disease in lymph nodes, bones or other organs. Finding metastatic disease usually changes the treatment plan and may mean that removing the prostate would not provide the expected benefit. Very small-volume disease can still be below the resolution of any scan.

Prostate biopsy

Major guidelines recommend pathological confirmation before potentially morbid local salvage therapy. Biopsy can confirm viable cancer, determine its grade and help distinguish clinically important recurrence from post-radiation change. Both targeted and systematic sampling may be considered.

Urinary-function assessment

Assessment may include symptom scores, urine testing, urinary-flow measurement, residual urine ultrasound and cystoscopy. Urodynamic testing may be helpful when there is significant urgency, leakage, poor flow, retention or uncertainty about bladder function.

Who may not be a good candidate?

Salvage prostatectomy is less likely to be appropriate when:

  • metastatic or extensive nodal disease is present;
  • the cancer is unlikely to be completely removable;
  • life expectancy is limited by age, frailty or other illness;
  • the recurrence is low risk and unlikely to threaten health;
  • severe urinary or bowel damage already exists after radiation; or
  • the anticipated harms of surgery outweigh the probability of cancer control.

These are not absolute rules. Individual circumstances should be reviewed by a multidisciplinary team involving urology, radiation oncology, medical oncology, radiology and pathology.

What are the potential benefits?

For carefully selected men, salvage prostatectomy can:

  • remove the recurrent cancer and provide complete pathological staging;
  • provide durable PSA control without immediately committing the patient to lifelong hormonal therapy; and
  • offer a possibility of cure when disease is truly confined to the prostate.

Published results vary considerably because most evidence comes from retrospective series involving highly selected patients. The European Association of Urology reports five-year biochemical recurrence-free estimates broadly around 41–52% in a large contemporary systematic review, while older selected series have reported ranges of approximately 47–82%. A broader meta-analysis of all local salvage approaches found roughly 50–60% five-year recurrence-free survival, without clear evidence that one approach was oncologically superior. These figures should not be interpreted as a personal prediction.

Cancer control is generally more favourable when the PSA is lower, the recurrent tumour is organ-confined, the cancer grade is lower, the PSA doubling time is longer and there is no nodal or distant disease.

Side effects and complications

Complication rates vary with baseline function, radiation type and dose, disease extent, surgical technique, definitions used in studies and surgeon experience. Results from specialist centres may not apply everywhere.

Urinary incontinence

Loss of urinary control is one of the most important risks. Radiation may already have affected the sphincter, bladder and urethral tissues, and surgery removes the prostate through which the urethra passes.

Leakage may range from mild stress incontinence to severe continuous leakage. Pelvic-floor rehabilitation can help, but some men may later require a male sling or artificial urinary sphincter. Continence outcomes reported in the literature vary widely because studies use different definitions; the risk of significant or persistent leakage is clearly higher than after primary prostatectomy.

Erectile dysfunction

Erectile function is often already impaired by radiotherapy, age, vascular disease or hormonal treatment. Preservation of the erectile nerves may be unsafe or technically impossible because of tumour location and radiation fibrosis. Consequently, erectile dysfunction after salvage prostatectomy is very common and recovery of unassisted erections is uncommon.

Rehabilitation and treatment options include tablets, vacuum devices, penile injections and penile prosthesis surgery. As with any radical prostatectomy, ejaculation and natural fertility are lost because the prostate and seminal vesicles are removed.

Bladder-neck contracture or urethral narrowing

Scar tissue may develop where the bladder is reconnected to the urethra. This can cause a weak stream, straining, incomplete emptying, retention or recurrent infection. Treatment may require endoscopic incision or dilatation, sometimes more than once. Repeated procedures can worsen incontinence.

Urine leak and delayed healing

The new bladder-to-urethra join may heal slowly because irradiated tissues have reduced blood supply. A urinary catheter may need to remain in place longer, and imaging may be required before its removal. Persistent leakage can require drainage or further intervention.

Rectal injury and urinary fistula

The rectum can be densely adherent to the prostate after radiotherapy. Rectal injury is uncommon in expert contemporary practice but occurs more often than during primary prostatectomy and can be serious. It may require repair, temporary bowel diversion or, rarely, more extensive surgery. An abnormal connection between the urinary tract and rectum—a rectourinary fistula—is rare but particularly difficult to treat.

Other surgical risks

Other possible complications include bleeding or transfusion, infection, blood clots, lymphocele after lymph-node dissection, injury to nearby structures, anaesthetic complications, chronic pelvic pain and the need for further procedures.

Cancer may still recur

Even when preoperative imaging suggests local disease, microscopic cancer may already exist outside the prostate. PSA may therefore remain detectable or rise again after surgery. Further treatment—such as hormonal therapy, systemic therapy or selected metastasis-directed treatment—may still be required.

Are there alternatives?

Depending on the cancer, previous treatment, anatomy, urinary function and patient priorities, alternatives may include:

  • active monitoring for a slow or low-risk recurrence;
  • androgen-deprivation therapy, sometimes with additional systemic treatment;
  • salvage brachytherapy or stereotactic re-irradiation;
  • cryotherapy;
  • high-intensity focused ultrasound (HIFU); or
  • focal salvage treatment in carefully selected cases.

No single salvage treatment is best for every patient. Available studies are mostly non-randomised and use differing definitions. A large meta-analysis found broadly similar five-year cancer control among local salvage methods, but severe urinary toxicity was higher after salvage prostatectomy than after modern re-irradiation approaches. Treatment should therefore be selected through shared decision-making rather than on cancer-control figures alone.

The bottom line

Radical prostatectomy after prostate radiotherapy is possible and can be curative, but it is not a routine operation. The best candidate is generally a fit man with biopsy-proven, clinically significant recurrence confined to the prostate, no metastatic disease on appropriate staging, a meaningful life expectancy and a clear understanding of the potential functional consequences.

Accurate staging, confirmation by biopsy, assessment of baseline urinary function and review by an experienced multidisciplinary team are essential. The decision must balance the chance of durable cancer control against the higher risks of urinary incontinence, erectile dysfunction, urinary narrowing, poor healing and rectal complications.

This article provides general information and does not replace individual medical advice. Recommendations should be tailored to the pathology, imaging, previous radiation treatment, general health and preferences of each patient.

References

  1. European Association of Urology. EAU Guidelines on Prostate Cancer: Treatment—management of PSA failure after radiation therapy and salvage radical prostatectomy. Current online edition. https://uroweb.org/guidelines/prostate-cancer/chapter/treatment
  2. Morgan TM, et al. Salvage Therapy for Prostate Cancer: AUA/ASTRO/SUO Guideline. Journal of Urology. 2024. https://www.auanet.org/guidelines-and-quality/guidelines/salvage-therapy-for-prostate-cancer
  3. Valle LF, et al. A systematic review and meta-analysis of local salvage therapies after radiotherapy for prostate cancer (MASTER). European Urology. 2021;80(3):280–292. doi:10.1016/j.eururo.2020.11.010.
  4. Grubmüller B, et al. Salvage radical prostatectomy for radio-recurrent prostate cancer: an updated systematic review of oncological, histopathological and functional outcomes and predictors. European Urology Focus. 2021;7(5):967–978.
  5. Perera M, et al. Morbidity of salvage radical prostatectomy: limited impact of the minimally invasive approach. European Urology Open Science. 2022;39:64–72.
  6. Zumsteg ZS, et al. The natural history and predictors of outcome following biochemical relapse in the dose-escalation era for prostate cancer patients undergoing definitive external beam radiotherapy. European Urology. 2015;67(6):1009–1016.


The Story Behind The “Happy Prostate”

More than a logo

The Happy Prostate is not simply a practice logo. It began as an original artwork that I painted myself, and it now hangs in my study at home.

Its cheerful expression reflects what I hope to achieve when caring for men with prostate and urinary problems: less worry, better understanding, improved bladder function and renewed confidence.

The prostate may be a small gland, but when it misbehaves, it can have an enormous effect on daily life. It can interrupt sleep, dictate travel plans, interfere with intimacy and leave a man constantly searching for the nearest toilet.

The Happy Prostate represents the other side of that story the moment when a man feels that he has regained control of his life. Having had prostate surgery myself, I am on the same page as my patients, I get you. And no, I did not do it myself!

When a growing prostate becomes a grumpy prostate

Benign prostatic hyperplasia, or BPH, is the non-cancerous enlargement of the prostate that commonly develops as men age.

An enlarged prostate may compress the urinary passage and cause:

  • A slow or interrupted urinary stream
  • Difficulty starting urination
  • Straining to pass urine
  • A feeling that the bladder has not emptied
  • Urgency and frequent urination
  • Getting up repeatedly during the night
  • Urinary retention or recurrent infections

Not every enlarged prostate needs surgery. Treatment begins with understanding the symptoms, examining the prostate and assessing bladder emptying, urinary flow, PSA and other relevant factors.

When a procedure is needed, there is no single operation that suits every man. Modern BPH treatment can be tailored according to prostate size and shape, symptom severity, bladder function, general health and the importance of preserving ejaculation.

Steam

Water-vapour therapy delivers small amounts of controlled steam into selected areas of enlarged prostate tissue. The treated tissue gradually shrinks, creating more room for urine to pass.

It may suit selected men looking for a minimally invasive option with a relatively low risk of sexual side effects. Improvement develops gradually rather than overnight.

Clips or a prostatic urethral lift

Tiny implants can be used to hold enlarged prostate tissue away from the urinary channel. Nothing is cut away.

This approach may offer a rapid recovery and a good chance of preserving ejaculation in appropriately selected men. Prostate anatomy is important, and some men may require further treatment later.

Temporary prostate stents or implants

A temporary implant can reshape the prostatic urethra without leaving a permanent device behind. It is usually removed after several days.

This can be useful for carefully selected prostates, although symptom improvement and long-term durability may not equal those achieved with more definitive tissue-removing procedures.

Laser treatment

Laser surgery can vaporise or enucleate obstructing prostate tissue. The technique selected depends on prostate size, anatomy, bleeding risk and the available equipment and expertise.

Laser treatment can provide powerful relief of obstruction, but temporary urgency, burning, bleeding and changes in ejaculation may occur during recovery.

Bipolar energy

Bipolar electrical energy can remove or enucleate enlarged prostate tissue while controlling bleeding. Bipolar TURP remains an established surgical option for many men with bothersome urinary obstruction.

Robotic-assisted enucleation

Very large prostates may be treated by robotic-assisted simple prostatectomy or enucleation. The obstructing inner portion of the prostate is removed while the outer capsule remains.

This is a more substantial procedure than a minimally invasive treatment, but it can provide excellent relief when a very large prostate is causing severe obstruction, retention, infections, bladder stones or kidney problems.

The right procedure is not necessarily the newest or the biggest. It is the procedure that best matches the individual man and his priorities. Current guidelines emphasise shared decision-making because treatments differ in effectiveness, recovery, durability and effects on sexual function. (EAU Male LUTS guideline)

When the diagnosis is prostate cancer

The words “prostate cancer” naturally produce fear, but prostate cancer is not one uniform disease. Some cancers grow so slowly that immediate treatment may cause more harm than benefit. Others require timely and decisive treatment.

The goal is to understand the cancer accurately and choose a strategy that balances cancer control with urinary, sexual and general health.

Active surveillance

For appropriately selected men with low-risk—and some favourable intermediate-risk—prostate cancer, active surveillance can avoid or delay unnecessary treatment.

It does not mean ignoring the cancer. It is a structured programme that may include:

  • Regular PSA testing
  • Clinical review
  • Prostate MRI
  • Repeat biopsy when indicated
  • Conversion to active treatment if there are signs of progression

The aim is to preserve quality of life while retaining the opportunity for curative treatment if the cancer changes. (EAU Prostate Cancer guideline)

Robotic-assisted radical prostatectomy

Robotic-assisted radical prostatectomy removes the prostate and seminal vesicles with the intention of curing localised prostate cancer.

Where it is oncologically safe, nerve-sparing and careful reconstruction may help preserve erectile function and accelerate recovery of urinary control. Cancer clearance remains the first priority, and continence and sexual outcomes vary between men.

Focal therapy

Focal therapy treats the cancerous area while attempting to preserve as much normal prostate tissue as possible. Techniques may include irreversible electroporation, focal laser ablation, high-intensity focused ultrasound or cryotherapy.

It may be considered for carefully selected men with localised, MRI-visible disease who understand the need for close follow-up. Focal therapy is not suitable for every prostate cancer, and long-term comparative evidence continues to develop. Some international guidelines recommend that it be performed within structured prospective studies or registries.

When continence is preserved, improved or restored

Urinary continence is one of the most important themes represented by the Happy Prostate.

Whenever possible, treatment planning aims to preserve continence. This involves careful patient selection, thoughtful surgical technique, protection of the urinary sphincter and appropriate pelvic-floor preparation and rehabilitation.

When leakage occurs, it should never be dismissed as something a man must simply tolerate. Assessment may include a bladder diary, pad testing, urine-flow measurement, ultrasound, cystoscopy or urodynamic studies. This helps distinguish weakness of the urinary sphincter from urgency, overactive bladder, obstruction or poor bladder emptying.

Depending on the cause, continence may be improved or restored through:

  • Pelvic-floor rehabilitation
  • Bladder training and lifestyle measures
  • Medication for urgency or overactive bladder
  • Treatment of residual obstruction
  • A male urethral sling
  • An artificial urinary sphincter
  • Other carefully selected continence procedures

The joyful progression shown in the Happy Prostate GIF represents this recovery: uncertainty giving way to hope, improvement and confidence. As urinary control returns, the character stands taller, moves with greater freedom and finally throws away his diaper.

The humour is intentional, but so is the dignity behind it. Incontinence can affect work, exercise, travel, intimacy and self-esteem. Restoring continence is not merely about keeping underwear dry, it is about helping a man feel comfortable in the world again.

As I like to put it:

When treatment works, the bladder stops writing the day’s itinerary and the diaper can take the day off.

A small painting with a larger purpose

The original Happy Prostate painting hanging in my home study reminds me that urology is not only about scans, PSA results, flow rates and surgical technology. It is about the man sitting on the other side of the desk.

A prostate becomes truly “happy” when its owner:

  • Understands what is happening
  • Feels comfortable discussing embarrassing symptoms
  • Has treatment suited to his individual circumstances
  • Maintains or regains urinary control
  • Can return to sleep, exercise, travel and intimacy with confidence
  • Feels that he has been heard and treated with dignity

A little humour can open the door, but dignity keeps the conversation going.

That is the story of the Happy Prostate: an original painting, a slightly cheeky character and a serious commitment to helping men regain comfort, confidence and joy.

Dr Jo Schoeman
The “Happy-Prostate” Urologist

This article provides general information and does not replace an individual medical assessment. The suitability, benefits and potential complications of each treatment should be discussed with a urologist.

Bridge to Brisbane 2026: Running in Blue for Prostate Cancer

On Sunday, 13 September 2026, Brisbane will once again come alive with runners, walkers, families, friends and more than a few wonderfully questionable costumes for the annual Bridge to Brisbane.

This year’s event includes the RBWH Foundation Blue Run 5 km, raising awareness and support for prostate cancer research and care. Participants are encouraged to turn the course blue—whether that means blue shirts, blue socks or the increasingly popular blue skirts and tutus.

The blue skirts may attract a smile, but the message behind them is serious: men’s health deserves to be seen, discussed and supported.

Why run in blue?

Blue is widely recognised as the colour of prostate cancer awareness. Wearing blue creates a visible show of support for men diagnosed with prostate cancer, those undergoing treatment, survivors and the families who travel the journey beside them.

Prostate cancer remains the most commonly diagnosed cancer among Australian men. It can often develop without causing obvious symptoms, particularly in its early stages. Community events such as the Blue Run help bring prostate health into everyday conversation and encourage men to learn about their individual risk.

The blue skirt also carries a distinctly Australian message: we can address an important issue without losing our sense of humour. If pulling on a tutu prompts one man to discuss prostate cancer with his brother, friend or doctor, it has done something worthwhile.

More than a fun run

Bridge to Brisbane enables participants to raise funds for causes that matter to them. Through the RBWH Foundation Blue Run, the community can help support prostate cancer research, clinical care and greater awareness of early detection.

Funds raised for medical research can contribute to:

  • Better methods of identifying significant prostate cancer
  • Improvements in surgery, radiation therapy and medical treatment
  • Research into advanced and metastatic prostate cancer
  • Better management of treatment-related urinary and sexual side effects
  • Support for patients and their families

The Blue Run is therefore not simply about reaching the finish line. Every registration, donation and conversation can help improve the outlook for men affected by prostate cancer. Information about joining or supporting the event is available through the RBWH Foundation and the official Bridge to Brisbane website.

The health benefits of a fun run

You do not have to be an elite runner to benefit. Preparing for a 5 km or 10 km event can provide a realistic goal and a reason to exercise more consistently.

Regular walking, jogging or running may help to:

  • Improve cardiovascular and lung fitness
  • Assist with weight, blood pressure and blood-sugar control
  • Strengthen muscles and bones
  • Improve balance, mobility and physical confidence
  • Reduce stress and improve sleep
  • Support mood and mental wellbeing
  • Maintain independence as we grow older
  • Create valuable social connection

For men living with or recovering from prostate cancer, appropriately prescribed exercise can also help maintain strength, fitness and quality of life. It may be particularly valuable for men receiving androgen-deprivation therapy, which can contribute to fatigue, muscle loss, weight gain and reduced bone density.

Exercise is not a substitute for prostate cancer assessment or treatment, but it is an important part of looking after the whole person.

You may walk—it still counts

The word “run” should not frighten anyone away. Bridge to Brisbane can be approached as a run, jog, walk or a cheerful combination of all three.

A simple preparation program might begin with:

  1. Three comfortable walks each week.
  2. Gradually increasing the time or distance.
  3. Introducing short jogging intervals if appropriate.
  4. Including two weekly sessions of light strength training.
  5. Allowing rest days and increasing activity gradually.

Supportive footwear, hydration and sun protection are important. Anyone with chest pain, unexplained breathlessness, dizziness, significant joint problems or an unstable medical condition should speak with their GP before commencing vigorous exercise.

Men undergoing prostate cancer treatment should seek individual guidance from their treating team or an accredited exercise physiologist.

A different kind of men’s health check

A fun run is not a prostate cancer screening test—but it can start an important conversation.

Men should discuss their prostate cancer risk and the potential benefits and limitations of PSA testing with their GP, particularly if they have a father, brother or son diagnosed with the disease. Aboriginal and Torres Strait Islander men and men with a strong family history may also benefit from an earlier, individualised discussion.

A blue skirt cannot diagnose prostate cancer. It can, however, make the subject difficult to ignore.

My Bridge to Brisbane journey

For me Bridge to Brisbane is more than a single morning of exercise. I participated in the 10 km event since 2019, joining thousands of Queenslanders crossing the Gateway Bridge in support of fitness, community spirit and charitable causes.

Each run has brought its own combination of early-morning nerves, Brisbane sunshine, tired legs and the satisfaction of reaching the finish line. I aim for a sub-50 min each year…

Although achieving a personal best is rewarding, I believe the greater value of the event lies in simply taking part. And for me, having my family participate with me is GOLD. Training provides a reason to remain active, while race day brings people together around important causes—including prostate cancer awareness, research and patient care.

As a urological surgeon, I have seen how prostate cancer can affect not only a man’s physical health but also his continence, sexual function, emotional wellbeing and family life. Running the 10 km course is therefore both a personal challenge and an opportunity to encourage men to pay attention to their health.

The 2026 Blue Run adds special meaning to that involvement. Wearing blue—and perhaps even a blue skirt or tutu—helps turn a private men’s health issue into a visible community conversation. The time on the clock matters, but helping another man think about his prostate health matters even more.

Crossing the bridge together

Prostate cancer affects more than the prostate. It can influence continence, sexual function, relationships, emotional wellbeing and a man’s sense of identity. It also affects partners, children, friends and caregivers.

Bridge to Brisbane reminds us that health challenges are easier to face when we do not face them alone.

So, lace up your shoes, gather your family or mates and add something blue. Walk if you wish, run if you can—and wear the blue skirt with pride.

The finish-line photograph may not be dignified, but the reason behind it certainly is.

Looking forward to seeing many Blue-Skirts!

This article provides general health information and does not replace individual medical advice. Speak with your GP or urologist about prostate symptoms, PSA testing or your personal prostate cancer risk.

Prostate Abscess: A Rare but Serious Infection

A prostate abscess is a collection of pus within the prostate gland. It usually develops as a complication of acute bacterial prostatitis when infection progresses despite treatment or when treatment has been delayed.

Prostate abscesses are uncommon, but they can become life-threatening if the infection spreads into the bloodstream. Early diagnosis, intravenous antibiotics and, when necessary, drainage of the abscess are essential.

What causes a prostate abscess?

Most prostate abscesses develop when bacteria enter the prostate from the urinary tract. The infection may begin in the bladder or urethra and travel backwards through the prostatic ducts.

Common bacteria include:

  • Escherichia coli
  • Klebsiella species
  • Pseudomonas species
  • Proteus species
  • Enterococcus species
  • Staphylococcus aureus, including resistant strains such as MRSA

Less commonly, bacteria reach the prostate through the bloodstream from an infection elsewhere in the body. Fungal and tuberculosis-related abscesses are rare but may occur in people with significant immune suppression.

Who is at increased risk?

A prostate abscess is more likely to develop in men with:

  • Diabetes, particularly when blood glucose is poorly controlled
  • A weakened immune system
  • Long-term corticosteroid or immunosuppressive treatment
  • HIV or another significant immune disorder
  • Difficulty emptying the bladder
  • Benign prostate enlargement
  • A urethral stricture
  • A long-term urinary catheter
  • Recent urinary tract instrumentation
  • Recent prostate biopsy or prostate surgery
  • Recurrent urinary tract infections
  • Chronic kidney disease or dialysis
  • Intravenous drug use
  • Acute bacterial prostatitis that is not improving with appropriate antibiotics

Diabetes is one of the most frequently identified risk factors. High blood glucose can impair the immune response and make infection more difficult to control.

How does a prostate abscess present?

The symptoms often resemble acute prostatitis or a severe urinary tract infection. A man may experience:

  • Fever, chills or shaking
  • Pain or burning when passing urine
  • Frequent or urgent urination
  • Difficulty starting or maintaining the urinary stream
  • Inability to pass urine
  • Pain in the pelvis, perineum, groin or lower back
  • Painful ejaculation
  • Blood in the urine
  • Cloudy or unpleasant-smelling urine
  • General weakness, nausea or confusion

On examination, the prostate may be enlarged, tender or feel unusually soft or fluctuant. However, the absence of a typical prostate examination does not exclude an abscess.

Forceful prostate massage should be avoided in someone with acute prostatitis or a suspected abscess because it may push bacteria into the bloodstream.

When should a prostate abscess be suspected?

A prostate abscess should be considered when a patient with acute prostatitis:

  • Remains febrile after approximately 48–72 hours of appropriate antibiotics
  • Becomes more unwell despite treatment
  • Develops urinary retention
  • Has persistent pelvic or perineal pain
  • Has recurrent infection with the same organism
  • Has diabetes, immune suppression or another major risk factor

Symptoms alone cannot reliably distinguish an abscess from uncomplicated prostatitis. Imaging is usually needed to confirm the diagnosis.

How is it diagnosed?

Initial investigations may include:

  • Urine microscopy and culture
  • Blood cultures, preferably before antibiotics when this does not delay treatment
  • Full blood count
  • Kidney function and electrolyte tests
  • Inflammatory markers
  • Blood glucose testing
  • Blood lactate and other sepsis investigations when the patient is seriously unwell

Imaging may be performed using:

Transrectal ultrasound

Transrectal ultrasound can demonstrate one or more fluid-filled cavities within the prostate. It can also be used to guide needle drainage.

CT scan

A CT scan of the pelvis is particularly useful when the patient is very unwell or when infection may have spread beyond the prostate. It can also identify urinary obstruction, stones or another source of infection.

MRI

MRI provides detailed images of the prostate and surrounding tissues. It may be helpful when ultrasound or CT findings are unclear, but it is not always the most practical first investigation in an emergency.

Is a prostate abscess an emergency?

A prostate abscess can lead to bloodstream infection, sepsis and septic shock. Patients with fever, shaking chills, confusion, low blood pressure, rapid breathing, severe weakness or inability to pass urine require urgent hospital assessment.

Emergency management may involve:

  • Immediate assessment for sepsis
  • Blood and urine cultures
  • Intravenous fluids
  • Prompt intravenous antibiotics
  • Pain relief
  • Monitoring of blood pressure, urine output and kidney function
  • Treatment of uncontrolled diabetes
  • Urgent urinary drainage if the bladder cannot empty
  • Early consultation with a urologist and, when appropriate, an infectious diseases physician

Antibiotics should not be delayed in a patient who is septic while waiting for scans or culture results.

If urinary retention is present, bladder drainage is required. A urethral catheter may sometimes be used carefully, but a suprapubic catheter inserted through the lower abdomen may be preferred when urethral catheterisation is difficult or likely to cause significant prostate irritation. The best approach depends on the patient’s condition and anatomy.

Treatment with antibiotics

All prostate abscesses require antibiotic treatment.

A patient who is systemically unwell will usually begin treatment with broad-spectrum intravenous antibiotics. The initial antibiotic choice depends on:

  • The likely source of infection
  • Local bacterial resistance patterns
  • Previous urine culture results
  • Recent hospital admission or antibiotic exposure
  • Recent catheterisation or urinary surgery
  • Kidney function
  • Drug allergies
  • The possibility of resistant bacteria or Staphylococcus aureus

Once culture results become available, treatment can be narrowed to an antibiotic that targets the identified organism and penetrates prostate tissue effectively.

After clear clinical improvement, intravenous treatment may be changed to an appropriate oral antibiotic. Treatment is usually longer than for a simple bladder infection and commonly continues for several weeks. The exact duration depends on the organism, abscess size, success of drainage, immune status and response to treatment.

Follow-up urine cultures and repeat imaging may be required to confirm that the infection and abscess have resolved.

Can antibiotics alone cure a prostate abscess?

Occasionally, a small abscess in a clinically stable patient can be treated with antibiotics and close observation. This is more likely to succeed when the collection is small, often less than approximately 1 cm, and drains naturally into the prostatic ducts.

There is no single size threshold that applies to every patient. Larger, multiloculated or persistent abscesses are less likely to resolve with antibiotics alone.

Drainage should be considered when:

  • The patient is septic or clinically deteriorating
  • Fever persists despite appropriate antibiotics
  • The abscess is relatively large
  • There are several abscess cavities
  • The abscess is not shrinking on repeat imaging
  • Urinary obstruction is present
  • The infecting organism is difficult to eradicate
  • The patient has diabetes or significant immune suppression
  • The infection repeatedly returns

Current European guidance recognises that both conservative treatment and drainage may be appropriate in selected patients, with abscess size and clinical response helping to guide the decision. EAU Guidelines on Urological Infections

How is a prostate abscess drained?

Several drainage techniques are available. The method chosen depends on the size and position of the abscess, whether it has multiple compartments, the patient’s condition and local expertise.

Transrectal ultrasound-guided aspiration

A needle is passed through the rectum into the abscess under ultrasound guidance, and the pus is aspirated.

Advantages include:

  • Minimally invasive treatment
  • Usually limited anaesthesia
  • Collection of pus for culture

However, the abscess may refill, particularly if it is large, thick-walled or divided into several compartments. Repeat aspiration may be needed.

Transperineal drainage

A needle or drain is inserted through the skin between the scrotum and anus under ultrasound or imaging guidance.

This approach avoids passing through the rectal wall and may allow a drainage catheter to remain temporarily. It can be useful for appropriately positioned abscesses or when repeated drainage is anticipated.

Transurethral drainage

A telescope is passed through the urethra, and the abscess cavity is opened internally so that it can drain into the urinary channel. This may be performed by incision, deroofing or limited resection of the involved prostate tissue.

Transurethral drainage is often considered when:

  • The abscess is large
  • There are multiple or deep cavities
  • Needle aspiration has failed
  • The abscess has recurred
  • Prostate enlargement is contributing to obstruction
  • Rapid and complete drainage is required

Possible complications include bleeding, urinary infection, temporary worsening of urinary symptoms, retrograde ejaculation, urethral stricture and, less commonly, urinary incontinence or injury to surrounding structures.

Open or laparoscopic surgery

Open, laparoscopic or robotic drainage is rarely required. It may be considered if the abscess extends outside the prostate, cannot be reached by less invasive methods or is associated with another condition requiring surgery.

Antibiotics plus effective drainage remain the central principles of treatment. Management of prostate abscess in the absence of guidelines and MSD Manual: Prostate Abscess

What happens after drainage?

The drained fluid is sent for microbiological testing. This is important because the organism within the abscess may differ from that found in the urine.

Following drainage, the patient usually continues antibiotics. Clinical improvement is monitored by checking:

  • Temperature and general wellbeing
  • Pain and urinary symptoms
  • White blood cell count and inflammatory markers
  • Kidney function
  • Blood glucose in patients with diabetes
  • Urine and blood culture results
  • Follow-up ultrasound, CT or MRI when indicated

Any contributing problem, such as bladder obstruction, a urethral stricture, a catheter or poorly controlled diabetes, should also be addressed to reduce the risk of recurrence.

What is the outlook?

With early recognition, appropriate antibiotics and adequate drainage, most prostate abscesses can be successfully treated.

Delayed treatment may result in:

  • Sepsis or septic shock
  • Spread of infection beyond the prostate
  • Fistula formation into nearby structures
  • Recurrent urinary infection
  • Chronic pelvic discomfort
  • Prolonged difficulty passing urine
  • Rarely, death from overwhelming infection

A prostate abscess should therefore be regarded as a potentially serious complication of prostatitis rather than an ordinary urinary infection.

When should you seek urgent medical attention?

Attend an emergency department urgently if you develop:

  • Fever or shaking chills with urinary symptoms
  • Confusion, faintness or severe weakness
  • Inability to pass urine
  • Severe pelvic or perineal pain
  • Rapid breathing or a racing heartbeat
  • Persistent fever despite antibiotics
  • Worsening symptoms after treatment for prostatitis

Early assessment is particularly important for men with diabetes, immune suppression, a urinary catheter or recent urinary tract surgery.

This information is intended for general education and does not replace individual medical assessment. A suspected prostate abscess requires urgent assessment by a medical practitioner and usually early involvement of a urologist.

So, if this is happening to you, attend your local Emergency Department ASAP, or if you are still OK, ask your GP for an urgent referral to see your local Brisbane Urologist Dr Jo Schoeman ASAP

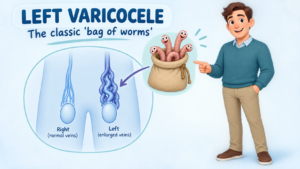
‘Bag-of-Worms” Varicocele: Causes, Symptoms, Fertility and Treatment Options

A varicocele is an enlargement of the veins surrounding the testicle. It is similar to a varicose vein in the leg, although it occurs within the scrotum.

Varicoceles are common and often harmless. However, in some men they may cause discomfort, reduce the size or function of the affected testicle, or contribute to fertility problems. Most varicoceles do not require treatment, and the decision to intervene depends on symptoms, testicular development, semen quality and plans for future fertility.

What causes a varicocele?

Blood leaves each testicle through a network of small veins called the pampiniform plexus. These veins normally carry blood upwards towards larger veins in the abdomen.

A varicocele develops when blood pools within these veins. This is usually related to poorly functioning venous valves, together with the anatomy and pressure within the testicular veins.

Around 80–90% of clinically detected varicoceles occur on the left side. This is because the left testicular vein is longer and enters the left renal vein at a right angle, making venous drainage less efficient. A varicocele may occur on both sides, while an isolated right-sided varicocele is much less common.

Most varicoceles develop gradually during puberty and have no dangerous underlying cause.

A new varicocele in an older man, particularly one that is right-sided, develops suddenly or does not disappear when lying down, may require abdominal imaging to exclude obstruction of the vein by an abdominal or retroperitoneal condition. This is uncommon but important to recognise.

How common are varicoceles?

A varicocele is found in approximately 15% of adolescent and adult men. Many men never know that they have one.

Varicoceles are more frequently identified among men being investigated for infertility. They may be present in approximately:

  • 35–40% of men with primary infertility
  • Up to 70–80% of men with secondary infertility, where a previous pregnancy has occurred, but the couple is now having difficulty conceiving

Importantly, most men with a varicocele remain fertile. Finding a varicocele does not automatically mean that it is causing infertility.

What are the symptoms?

Many varicoceles cause no symptoms and are discovered during a routine examination, fertility assessment or scrotal ultrasound.

When symptoms occur, they may include:

  • A dull ache, dragging sensation or heaviness in the scrotum
  • Discomfort that becomes worse after standing, exercising or later in the day
  • Improvement in discomfort when lying down
  • Visible or enlarged veins above the testicle
  • A soft swelling sometimes described as feeling like a “bag of worms”
  • Reduced size or slower growth of the affected testicle
  • Abnormal semen-analysis results
  • Difficulty conceiving with a partner

A varicocele generally does not cause erectile dysfunction or difficulty urinating. Its relationship with testosterone production remains under investigation, although some men with a clinically significant varicocele may have impaired testicular function.

Sudden severe testicular pain is not typical of a varicocele and requires urgent medical assessment to exclude testicular torsion or another acute scrotal condition. An abdominal ultrasound is also required to exclude a possible lesion in the abdomen obstructing the veins.

How is a varicocele diagnosed?

Diagnosis usually begins with a physical examination. The scrotum is examined while the patient is standing and lying down. You may be asked to take a breath and gently bear down, the Valsalva manoeuvre, to make enlarged veins easier to feel.

Clinical varicoceles are commonly graded as:

  • Grade 1: Felt only during the Valsalva manoeuvre
  • Grade 2: Felt while standing without straining
  • Grade 3: Easily visible through the scrotal skin

A scrotal ultrasound may be recommended if the examination is uncertain, the testicles differ in size, pain is present, or another scrotal problem needs to be excluded. Ultrasound can measure the veins, assess backward blood flow and examine the testicles.

For fertility assessment, investigations may include:

  • One or more semen analyses
  • Testicular volume measurement
  • Hormone tests when indicated
  • Assessment of both partners, because fertility is a shared consideration

An ultrasound-only or “subclinical” varicocele that cannot be felt on examination is not usually treated for infertility.

How can a varicocele affect fertility?

The testicles work best at a temperature slightly below core body temperature. The pampiniform veins help cool the arterial blood entering the testicle.

Pooling of warm blood in a varicocele may interfere with this cooling system. Increased temperature, venous pressure, oxidative stress and altered blood flow may affect sperm production and testicular function.

Possible semen changes include:

  • Reduced sperm concentration
  • Reduced sperm movement or motility
  • Increased abnormal sperm forms
  • Increased sperm DNA damage

The degree of impact varies considerably. A large varicocele can be associated with normal fertility, while a smaller palpable varicocele may be significant in another man. The diagnosis must therefore be interpreted together with semen results, the couple’s fertility history, the female partner’s age and other fertility factors.

Does every varicocele require treatment?

No. Observation is appropriate when a varicocele:

  • Causes no troublesome symptoms
  • Is not affecting testicular growth
  • Is associated with normal semen parameters
  • Is found incidentally on ultrasound but cannot be felt
  • Is unlikely to be the main cause of the couple’s fertility difficulty

Simple measures such as supportive underwear, avoiding activities that consistently aggravate discomfort and occasional appropriate pain relief may help mild symptoms. Regular review may be recommended for adolescents with a difference in testicular size.

When should treatment be considered?

Treatment may be considered when there is:

Infertility with abnormal semen parameters

Repair is most likely to benefit a couple when the man has:

  • A varicocele that can be felt on examination
  • Difficulty conceiving
  • One or more abnormal semen parameters
  • No better explanation for the infertility
  • A reasonable opportunity for natural conception following treatment

Both the AUA/ASRM and European guidance support considering repair in men attempting conception who have a palpable varicocele and abnormal semen parameters. Treatment is not routinely recommended for a varicocele detected only by ultrasound. AUA/ASRM male infertility guideline and EAU male infertility guideline

Persistent scrotal pain

Repair may be reasonable when typical varicocele-related discomfort persists despite conservative measures and other causes of scrotal pain have been excluded.

Reduced testicular growth in an adolescent

Treatment may be discussed if the affected testicle is persistently smaller, growth is impaired, the varicocele is large or semen parameters are abnormal in an appropriately selected older adolescent.

Progressive testicular dysfunction

Selected men with deteriorating semen quality or evidence of impaired testicular function may benefit from repair after individual assessment.

What treatment procedures are available?

Treatment works by blocking or dividing the abnormal veins. Blood then returns through healthy alternative veins while the testicular artery and lymphatic drainage are preserved.

Management option How it is performed Advantages Disadvantages and risks
Observation Clinical review, with semen analysis or testicular measurements when appropriate No procedure or anaesthetic; suitable for most asymptomatic men; avoids unnecessary treatment Does not correct the varicocele; symptoms or testicular changes may require future review
Conservative symptom management Scrotal support, activity modification and appropriate pain relief Simple and non-invasive; may adequately control mild discomfort Does not remove the varicocele or improve abnormal semen parameters; long-term anti-inflammatory medication may not be suitable for everyone
Microsurgical subinguinal varicocelectomy A small incision is made near the groin. An operating microscope helps identify and divide abnormal veins while protecting the testicular artery and lymphatics Usually the lowest recurrence and hydrocele rates; no abdominal incision; effective for unilateral or bilateral disease; commonly preferred for fertility treatment Requires an anaesthetic and microsurgical expertise; temporary bruising, swelling or discomfort; uncommon risks include infection, recurrence, hydrocele or testicular artery injury
Microsurgical inguinal varicocelectomy Similar microsurgical repair through a slightly higher groin incision Good visualisation and low recurrence when performed microsurgically Requires opening the external oblique fascia; recovery may involve slightly more groin discomfort
Laparoscopic varicocelectomy Veins are clipped or divided through small abdominal keyhole incisions Both sides can be treated during the same procedure; useful in selected cases General anaesthetic; entry into the abdomen; generally higher hydrocele risk than lymphatic-sparing microsurgery; rare abdominal or vascular complications
Open high ligation The testicular vein is divided through an abdominal or groin incision without microsurgical magnification Established technique; may be effective where microsurgery is unavailable Higher recurrence and hydrocele rates than modern microsurgical repair; less precise preservation of small arteries and lymphatics
Radiological embolisation or sclerotherapy An interventional radiologist passes a catheter into the testicular vein and blocks it using coils, plugs or a sclerosant No surgical incision in the scrotum or groin; often performed with local anaesthesia or sedation; relatively quick recovery; useful for recurrence after surgery The vein cannot always be accessed; radiation and contrast exposure; recurrence or persistence may occur; coils can rarely migrate; availability depends on local expertise

How effective is treatment?

The results depend on why treatment is being performed, the technique used and whether other fertility or pain-related factors are present.

Improvement in semen quality

Following repair of a clinically significant varicocele, approximately 60–80% of appropriately selected men demonstrate improvement in at least one semen parameter. Improvement is not guaranteed, and some men show little or no measurable change.

Because sperm production takes approximately three months, semen analysis is usually repeated about three months after treatment and may be reassessed again at six months.

Pregnancy and fertility outcomes

Varicocele repair may increase the chance of natural pregnancy in selected infertile couples, but it does not guarantee conception. Studies commonly report spontaneous pregnancy in roughly 25–40% of couples after repair, although rates vary substantially according to female partner factors, duration of infertility, baseline semen quality and study design.

Treatment may also improve semen quality sufficiently to allow a couple to use a less invasive assisted-reproduction option. In other cases, IVF or intracytoplasmic sperm injection may still be required.

The couple’s overall fertility timeline is important. If the female partner has reduced ovarian reserve or advancing reproductive age, waiting several months for semen improvement may not be appropriate. Varicocele repair and assisted reproductive treatment should therefore be considered as part of a shared plan.

Relief of pain

When pain is typical of a varicocele, a dull ache or heaviness made worse by standing or activity, approximately 70–90% of appropriately selected men experience meaningful improvement after repair.

Surgery is less predictable when pain is sharp, constant or atypical, and pain may occasionally persist despite technically successful treatment.

Testicular growth

In adolescents with a persistently smaller affected testicle, repair may allow “catch-up” growth. Decisions should be based on repeated measurements rather than a single ultrasound result.

What are the possible complications?

Varicocele procedures are generally safe, but potential complications include:

  • Bruising, swelling or wound discomfort
  • Infection or bleeding
  • Persistence or recurrence of the varicocele
  • Hydrocele, caused by fluid collecting around the testicle
  • Ongoing or occasionally altered scrotal pain
  • Injury to the testicular artery, which is uncommon but potentially serious
  • Testicular shrinkage, which is rare
  • Anaesthetic complications
  • Technical failure, contrast reaction, radiation exposure or coil-related problems following embolisation

Using microsurgical magnification and preserving the lymphatic vessels usually reduces the risks of recurrence, hydrocele and arterial injury.

Recovery after varicocele repair

Most men return home on the day of treatment. Bruising, mild swelling and groin or scrotal discomfort are expected during the early recovery period.

Patients are commonly advised to:

  • Wear supportive underwear
  • Keep the wound clean and dry
  • Avoid heavy lifting and strenuous exercise for the period advised by the surgeon
  • Resume sexual activity when comfortable and medically cleared
  • Attend follow-up to assess healing and symptom improvement
  • Repeat semen analysis after approximately three months when fertility is the reason for treatment

Specific recovery instructions vary according to the procedure and the individual patient.

When should you seek medical advice?

Arrange a medical assessment if you notice:

  • A new lump or swelling in the scrotum
  • Persistent scrotal discomfort or heaviness
  • A difference in testicular size
  • Difficulty conceiving
  • A new right-sided varicocele
  • A swelling that remains when lying down

Seek urgent medical attention for sudden severe testicular pain, rapid swelling, nausea or a high-riding testicle. These features may indicate testicular torsion, which is an emergency.

The bottom line

A varicocele is common and, for most men, causes no significant harm. Treatment is not based on the ultrasound appearance alone. The most important considerations are symptoms, testicular development, semen quality and the couple’s overall fertility situation.

For men with persistent typical pain, impaired testicular growth or a palpable varicocele associated with infertility and abnormal semen parameters, treatment can be worthwhile. Microsurgical varicocelectomy generally offers the most favourable balance between effectiveness, recurrence and complication risk, while embolisation is an effective minimally invasive alternative in selected patients.

A consultation with a urologist allows the varicocele—and the patient rather than simply the scan—to be assessed before deciding whether observation, surgery or embolisation is the most appropriate approach.

This article provides general information and does not replace an individual medical assessment. Treatment recommendations depend on examination findings, semen results, symptoms, age and the fertility circumstances of both partners.

So, if this is something that you have found on your regular scrotal examinations, and you have concerns, come see your Brisbane urologist, Dr Jo Schoeman for advice.

Conservative Management of a Distal Ureteric Stone: When Can You Wait and When Is Surgery Needed?

A distal ureteric calculus is a stone located in the lower part of the ureter—the tube carrying urine from the kidney to the bladder. These stones are often close to the ureterovesical junction, where the ureter enters the bladder.

As the stone moves towards the bladder, it can cause severe intermittent pain known as renal colic. Pain commonly begins in the side or back and travels into the lower abdomen, groin, testicle or labia. Blood in the urine, nausea, vomiting, urinary urgency and frequency may also occur.

Many small distal ureteric stones pass naturally. However, conservative management is only safe when pain is controlled, infection is absent, kidney function is satisfactory and appropriate follow-up is arranged.

When is a ureteric stone an emergency?

A stone obstructing an infected kidney is a urological emergency. Antibiotics alone may be insufficient because infected urine cannot drain normally.

Seek urgent medical assessment if stone symptoms are accompanied by:

  • Fever or shaking chills
  • Feeling severely unwell, weak, confused or drowsy
  • Persistent vomiting or inability to drink
  • Pain that remains severe despite medication
  • Passing very little or no urine
  • Known poor kidney function
  • A solitary functioning kidney
  • Pregnancy with significant pain or fever

The obstructed kidney may need urgent drainage with a ureteric stent or nephrostomy tube. Definitive stone treatment is usually delayed until the infection has been controlled. The European Association of Urology recommends immediate antibiotics and urgent drainage for sepsis associated with an obstructing stone. EAU Guidelines on Urolithiasis

Australian Healthdirect similarly advises patients with renal colic and fever to attend a doctor or hospital emergency department promptly. Healthdirect Australia—Kidney stones

What determines whether a stone will pass naturally?

The likelihood of spontaneous passage depends mainly on:

  • Stone size
  • Position within the ureter
  • Degree of obstruction
  • Ureteric anatomy
  • Whether the stone is impacted
  • Previous stone history
  • Associated swelling and inflammation
  • The duration for which the stone has remained in the same position

Smaller stones located close to the bladder have the greatest likelihood of passing.

The EAU reports that distal ureteric stones collectively have a spontaneous passage rate of approximately 68–83%. A distal ureteric stone smaller than 5 mm has an estimated passage rate of approximately 89%. The likelihood decreases as stone size increases.

These percentages describe groups of patients and cannot predict exactly what will happen to an individual stone. A 4 mm stone may occasionally become impacted, while a larger stone may sometimes pass without surgery.

The average reported passage time is approximately 17 days, although passage can occur sooner or take several weeks. EAU Guidelines on Urolithiasis

Who may be suitable for conservative management?

Conservative management, also called observation, expectant management or a trial of passage, may be appropriate when:

  • The stone is small enough to have a reasonable chance of passing
  • The stone is in the distal ureter
  • Pain can be controlled with oral medication
  • There is no fever or evidence of urinary infection
  • Kidney function is stable
  • The patient can drink and keep medication down
  • There is no complete obstruction threatening kidney function
  • The patient is passing urine normally
  • There is no high-risk situation involving a solitary kidney or bilateral obstruction
  • The patient understands the warning symptoms
  • Follow-up and repeat imaging can be arranged
  • The patient is comfortable waiting for the stone to pass

Stones of 5 mm or less are particularly suitable for observation when no complications are present.

Selected distal stones between 5 and 10 mm may also be managed conservatively. These stones are less likely to pass than smaller stones, but some patients may avoid surgery with careful observation and medical expulsive therapy.

Stones larger than 10 mm are substantially less likely to pass naturally and are more commonly treated with an intervention.

What assessment is required?

Before recommending conservative management, the diagnosis and severity of obstruction should be established.

Assessment may include:

  • A detailed history and physical examination
  • Urine dipstick testing
  • Urine culture when infection is suspected
  • Kidney-function blood tests
  • Full blood count and inflammatory markers
  • Non-contrast CT scan of the kidneys, ureters and bladder
  • Ultrasound in selected patients
  • A plain abdominal X-ray when the stone is visible on X-ray
  • Pregnancy testing when clinically relevant

A low-dose non-contrast CT scan is often the most accurate test for determining the stone’s size and location. It can also assess hydronephrosis, the swelling of the kidney caused by obstruction and identify alternative causes of pain.

Ultrasound is particularly useful when radiation should be avoided, including during pregnancy, although it may not show every ureteric stone.

What does conservative management involve?

Pain relief

Non-steroidal anti-inflammatory medicines, NSAIDs, are often the most effective initial treatment for renal colic when they are medically safe.

Depending on the patient, treatment may include:

  • Ibuprofen
  • Diclofenac
  • Paracetamol
  • A prescribed opioid for breakthrough pain
  • Medication for nausea or vomiting

NSAIDs may be unsuitable for people with:

  • Reduced kidney function
  • Previous stomach ulcers or gastrointestinal bleeding
  • Certain cardiovascular conditions
  • Anticoagulant treatment
  • NSAID allergy
  • Some stages of pregnancy

Pain medication should be selected according to the patient’s medical history rather than taken indiscriminately.

Hydration

Patients should generally remain normally hydrated and avoid becoming dehydrated.

Drinking excessive volumes of water during an episode of acute obstruction does not necessarily force the stone through and may increase discomfort. The aim is steady, sensible fluid intake unless a doctor has advised otherwise.

Straining the urine

Passing urine through a stone strainer can help recover the calculus. A captured stone can be sent for laboratory analysis, which may guide future prevention.

Pain disappearing does not always prove that the stone has passed. Occasionally a stone stops causing pain while obstruction remains, so follow-up imaging may still be required.

Activity

Normal gentle activity is usually reasonable if the patient feels well. Some patients find walking helpful, although exercise cannot guarantee stone passage.

Driving, remote travel and hazardous work may be unsafe while unpredictable severe pain or medication-related drowsiness remains possible.

Medical expulsive therapy

Medical expulsive therapy—usually abbreviated to MET, uses medication to help a ureteric stone pass.

The most frequently used medicines are alpha-blockers, including:

  • Tamsulosin
  • Silodosin
  • Alfuzosin

Tamsulosin is commonly selected because it is widely available and familiar to urologists.

Alpha-blockers are primarily used to improve urinary symptoms caused by prostate enlargement. Their use for ureteric stone passage is generally off-label, meaning that stone passage is not necessarily the indication listed in the medicine’s formal registration.

Off-label use does not mean that treatment is experimental or prohibited. It means that the potential benefits, limitations and side effects should be discussed before prescribing it.

How do alpha-blockers affect the distal ureter?

The ureter contains smooth muscle and alpha-adrenergic receptors. These receptors are particularly relevant in the distal ureter.

When a stone enters the ureter, the surrounding muscle can contract and spasm. Swelling may develop around the stone, increasing resistance to its movement.

Alpha-blockers may:

  • Relax distal ureteric smooth muscle
  • Reduce ureteric spasm
  • Reduce pressure below and around the stone
  • Increase the ureter’s ability to accommodate the calculus
  • Improve the likelihood of stone passage
  • Shorten passage time in some patients
  • Reduce episodes of renal colic and analgesic requirements in selected cases

An alpha-blocker does not:

  • Dissolve most stones
  • Make the stone physically smaller
  • Treat a urinary infection
  • Remove a completely impacted stone
  • Protect a kidney from prolonged significant obstruction
  • Replace drainage of an infected obstructed kidney

How effective are alpha-blockers?

Research into alpha-blockers has produced mixed results.

When all ureteric stones are grouped together, some large studies have shown little or no overall benefit. This may be because very small stones frequently pass without medication and very large or impacted stones remain unlikely to pass despite treatment.

The clearest benefit appears to be in patients with distal ureteric stones between approximately 5 and 10 mm.

The EAU recommends offering an alpha-blocker as one treatment option for conservatively managed distal ureteric stones in this size range, while explaining that treatment is off-label. EAU Guidelines on Urolithiasis

For a stone smaller than 5 mm, the natural passage rate is already high, so an alpha-blocker may add relatively little benefit. Treatment decisions should therefore be individualised.

Side effects and precautions with alpha-blockers

Possible side effects include:

  • Dizziness
  • Light-headedness on standing
  • Low blood pressure
  • Weakness or fatigue
  • Headache
  • Nasal congestion
  • Palpitations
  • Reduced semen volume
  • Failure of ejaculation or retrograde ejaculation

Extra caution is required in patients who:

  • Already have low blood pressure
  • Have a history of fainting or falls
  • Take several blood-pressure medicines
  • Use medication for erectile dysfunction
  • Have significant cardiovascular disease
  • Are planning cataract or glaucoma surgery

Tamsulosin has been associated with intraoperative floppy iris syndrome during cataract surgery. Patients should tell their ophthalmologist about current or previous use.

Alpha-blocker treatment should be stopped and medical advice obtained if infection, uncontrollable pain or deterioration in kidney function develops.

How long can conservative management continue?

There is no single safe waiting period for every patient. The decision depends on symptoms, obstruction, kidney function, stone movement and the likelihood of passage.

Many stones that pass naturally do so within two to four weeks. A monitored trial of passage may sometimes continue for up to approximately four to six weeks, provided that:

  • Pain remains manageable
  • Infection does not develop
  • Kidney function remains stable
  • Obstruction is not causing progressive harm
  • Follow-up imaging is performed
  • The patient still prefers conservative treatment

Observation should not become open-ended. A painless obstructing stone can still impair kidney function.

Follow-up may involve an X-ray, ultrasound or low-dose CT scan. The most suitable test depends on whether the stone was visible on the original X-ray and whether ongoing obstruction needs to be assessed.

When has conservative management failed?

Conservative management should be reconsidered when:

  • The stone has not passed within an appropriate observation period
  • Repeat imaging shows that the stone has not moved
  • Pain remains severe despite adequate medication
  • Repeated emergency presentations are required
  • Nausea or vomiting prevents oral fluids or medication
  • Fever or urinary infection develops
  • Kidney function deteriorates
  • Hydronephrosis persists or worsens
  • Urine output falls significantly
  • The stone has a low likelihood of spontaneous passage
  • The patient has a solitary kidney or bilateral obstruction
  • The patient cannot safely continue waiting
  • Work, caring responsibilities or travel make unpredictable colic unacceptable
  • The patient prefers definitive removal

The EAU identifies persistent pain, persistent obstruction, impaired kidney function and a low likelihood of spontaneous passage as indications for active stone removal. EAU Guidelines on Urolithiasis

Failure of conservative management is not a personal failure. It usually means that the stone is too large, impacted, anatomically trapped or producing complications that make further waiting unsafe.

Surgical and procedural treatment

The two main definitive treatments for a distal ureteric calculus are:

  • Ureteroscopy with laser lithotripsy or stone extraction
  • Shock wave lithotripsy

The most appropriate option depends on stone size, density and position, as well as the patient’s anatomy, medical health, preferences and treatment availability.

Ureteroscopy and laser lithotripsy

Ureteroscopy is commonly used for distal ureteric stones and generally provides the best chance of becoming stone-free after one procedure.

Under anaesthesia, a small telescope is passed through:

  1. The urethra
  2. The bladder
  3. The opening of the ureter
  4. The ureter to the level of the stone

The stone may be removed intact with a small basket or fragmented using a holmium or thulium laser. The pieces are then extracted or allowed to pass naturally.

No external incision is usually required.

Is a ureteric stent required?

A temporary ureteric stent may be inserted when:

  • The ureter is swollen
  • Access was difficult
  • Infection is a concern
  • Stone fragments remain
  • There was ureteric trauma
  • Reliable drainage is required
  • Kidney function is vulnerable

A stent extends from the kidney to the bladder. It can cause:

  • Urinary frequency and urgency
  • Bladder discomfort
  • Pain in the kidney during urination
  • Blood in the urine
  • Discomfort during activity
  • A sensation of incomplete emptying

Stents must be removed or exchanged at the planned time. A forgotten stent can become encrusted and cause serious complications.

Risks of ureteroscopy

Possible complications include:

  • Urinary infection or sepsis
  • Bleeding
  • Failure to reach or remove the stone
  • Residual fragments
  • Ureteric perforation
  • Ureteric narrowing or stricture
  • Need for a further procedure
  • Anaesthetic complications

Major ureteric injury is uncommon but can require additional surgery.

Compared with shock wave treatment, ureteroscopy generally offers a higher chance of clearing the stone in one procedure, although it is more invasive and has a higher complication rate. EAU Guidelines on Urolithiasis

Shock wave lithotripsy

Shock wave lithotripsy, SWL or ESWL, uses externally generated shock waves focused onto the stone. These waves fragment the calculus into smaller pieces that can pass down the ureter.

Advantages may include:

  • No telescope passing up the ureter
  • No surgical incision
  • Lower procedural morbidity
  • Day-treatment suitability in many patients

Limitations include:

  • Lower single-treatment stone-free rates than ureteroscopy
  • Possible need for repeat treatment
  • Pain while fragments pass
  • Residual fragments
  • Difficulty targeting some distal stones
  • Reduced success with dense or impacted stones
  • Reduced effectiveness with greater skin-to-stone distance
  • Possible need for subsequent ureteroscopy

SWL may not be suitable during pregnancy, with untreated infection, uncorrected bleeding disorders, an aneurysm near the treatment field or an anatomical obstruction below the stone.

The American Urological Association recognises both ureteroscopy and shock wave lithotripsy as options when active treatment is required for a distal ureteric stone. AUA Surgical Management of Kidney and Ureteral Stones Guideline

Emergency drainage with a ureteric stent

A ureteric stent may be inserted urgently to bypass an obstructing stone and allow urine to drain from the kidney.

This is particularly important when there is:

  • Infection or sepsis
  • Deteriorating kidney function
  • A solitary obstructed kidney
  • Bilateral obstruction
  • Uncontrollable pain
  • Severe obstruction where immediate stone removal is unsuitable

Emergency stenting relieves the obstruction but does not always remove the stone. Definitive ureteroscopy or SWL may be scheduled later.

Percutaneous nephrostomy

A nephrostomy tube is inserted through the skin of the back directly into the kidney under imaging guidance.

It may be used when:

  • Rapid drainage of an infected kidney is required
  • A ureteric stent cannot be inserted
  • The patient is too unwell for a longer procedure
  • Ureteric anatomy prevents retrograde access

Both ureteric stenting and nephrostomy provide effective emergency drainage. The choice depends on clinical circumstances, local expertise and the patient’s condition.

Open, laparoscopic or robotic stone removal

Open or keyhole ureterolithotomy is now rarely required for an isolated distal ureteric stone.

It may occasionally be considered for:

  • A very large impacted stone
  • Unusual urinary anatomy
  • Failure of less invasive treatments
  • A stone requiring treatment during another planned reconstruction

Most distal stones can be treated successfully with ureteroscopy or SWL.

Which treatment is best?

There is no single procedure that is best for every patient.

Ureteroscopy may be preferred when:

  • Rapid and reliable stone clearance is important
  • The stone is impacted
  • The stone is dense or unlikely to fragment with SWL
  • Previous SWL has failed
  • The patient has significant obesity
  • The stone is difficult to target externally
  • The patient wishes to minimise the likelihood of repeat treatment

SWL may be preferred when:

  • The stone can be targeted clearly
  • The stone has favourable size and density
  • The patient wishes to avoid ureteroscopy
  • Anaesthetic considerations favour a less invasive approach
  • The patient accepts the possibility of repeat treatment

The decision should include a discussion of success rates, anaesthesia, stent requirements, recovery, complications and the possible need for another procedure.

Preventing another stone

Once the acute episode has resolved, prevention becomes important.

General measures may include:

  • Drinking enough fluid to produce at least 2–2.5 litres of urine daily, unless medically restricted
  • Reducing excessive salt intake
  • Maintaining normal dietary calcium rather than eliminating calcium
  • Moderating excessive animal-protein intake
  • Maintaining a healthy body weight
  • Avoiding recurrent dehydration
  • Capturing the stone for analysis
  • Completing blood and urine testing when indicated

Patients with recurrent stones, a solitary kidney, childhood stone disease, unusual stone types or a strong family history may require a formal metabolic evaluation, including 24-hour urine testing.

Prevention should be tailored to the stone composition and the patient’s metabolic risk factors.

The bottom line

Many small distal ureteric stones can be managed safely without surgery. Stones smaller than 5 mm near the bladder have the greatest likelihood of passing naturally.

Conservative treatment usually involves appropriate pain relief, sensible hydration, urine straining, follow-up imaging and—in selected patients—an alpha-blocker such as tamsulosin.

Alpha-blockers relax the smooth muscle of the distal ureter. Their greatest likely benefit is for distal stones between approximately 5 and 10 mm. They do not dissolve the stone and should not delay treatment when infection, uncontrolled pain, persistent obstruction or declining kidney function develops.

Ureteroscopy with laser treatment provides the most reliable single-procedure clearance for many distal stones. Shock wave lithotripsy is less invasive but may require repeat treatment. An infected obstructed kidney requires urgent drainage rather than continued observation.

This article provides general information and does not replace individual medical assessment. Anyone with renal colic and fever, inability to pass urine, persistent vomiting or uncontrollable pain should seek urgent medical care.

Need help deciding whether your ureteric stone can safely pass?

If you have been diagnosed with a distal ureteric calculus, appropriate management depends on more than its size alone. Stone position, pain, infection, kidney function and the degree of obstruction must all be considered.

Your local Brisbane urologist, Dr Jo Schoeman, can assess whether observation, medical expulsive therapy, ureteroscopy or shock wave treatment is the most appropriate option for you.

References and further reading

Balanitis Xerotica Obliterans and Lichen Sclerosus of the Foreskin

Balanitis xerotica obliterans—usually abbreviated to BXO, is the traditional urological name for male genital lichen sclerosus.

Lichen sclerosus is a chronic inflammatory skin condition that most commonly affects the foreskin and head of the penis. It can cause whitening, inflammation, splitting and progressive scarring of the foreskin. In some men it also narrows the urinary opening or extends into the urethra.

BXO is not simply an infection or ordinary balanitis. Early recognition and treatment can relieve symptoms and reduce permanent scarring. Long-term observation is also important because genital lichen sclerosus is associated with a small but genuine risk of penile squamous cell carcinoma.

Is BXO different from lichen sclerosus?

The names are often used interchangeably:

  • Lichen sclerosus is the preferred modern medical term.
  • Balanitis xerotica obliterans describes lichen sclerosus affecting the glans penis and foreskin, particularly when scarring has developed.

The condition may involve:

  • The inner and outer foreskin
  • The glans penis
  • The frenulum
  • The urinary opening—the meatus
  • The fossa navicularis and penile urethra

The disease is usually confined to the genital region in men, although lichen sclerosus can occasionally affect skin elsewhere.

What causes lichen sclerosus?

The exact cause remains uncertain. It is probably produced by a combination of inflammation, immune-system dysfunction, genetic susceptibility, skin injury and local environmental factors.

Possible associations include:

  • Autoimmune or inflammatory activity
  • Chronic exposure of susceptible skin to trapped urine
  • Repeated friction or minor trauma
  • A tight foreskin
  • Previous inflammation beneath the foreskin
  • Obesity and a “buried” penis
  • Diabetes or metabolic disease
  • Cigarette smoking
  • Genetic susceptibility

The moist, occluded environment beneath the foreskin may contribute to continuing inflammation in susceptible men.

Lichen sclerosus is:

  • Not caused by poor personal character or behaviour
  • Not usually a sexually transmitted infection
  • Not contagious
  • Not something that can be passed to a partner through ordinary sexual contact

Yeast or bacterial infection may occur at the same time, particularly in men with diabetes, but infection is not the underlying cause of lichen sclerosus.

Who can develop it?

Male genital lichen sclerosus can occur at any age.

It is recognised in:

  • Boys with acquired or severe scarring phimosis
  • Adolescents
  • Younger and middle-aged men
  • Older men
  • Men with a previously retractable foreskin that has gradually tightened

It is much less common in men who were circumcised early in life, although circumcision does not make the risk absolutely zero.

How does lichen sclerosus present?

The appearance varies considerably. Early disease can be subtle and may initially be mistaken for thrush, dermatitis, recurrent balanitis or ordinary phimosis.

Possible signs include:

  • White, pale or porcelain-coloured foreskin
  • A white, firm ring around the foreskin opening
  • Thickened or hardened skin
  • Shiny, crinkled or “cigarette-paper” skin
  • Red or inflamed areas
  • Small cracks or splits
  • Easy bleeding or bruising
  • Painful erosions
  • Adhesions between the foreskin and glans
  • Progressive tightening of the foreskin
  • Shortening or scarring of the frenulum
  • Whitening around the urinary opening
  • Narrowing of the meatus
  • Loss of the normal shape or definition of the glans and foreskin

Some men have significant visible disease with surprisingly little discomfort.

Symptoms patients may notice

Symptoms can include:

  • Difficulty retracting the foreskin
  • Inability to replace or retract the foreskin fully
  • Pain during erections
  • Splitting or bleeding during intercourse
  • Itching, burning or soreness
  • Recurrent “balanitis”
  • Pain or reduced enjoyment during sexual activity
  • Spraying or deflection of the urinary stream
  • A weak or narrowed stream
  • Straining to urinate
  • Dribbling after urination
  • Ballooning of the foreskin
  • Recurrent urinary infections
  • Difficulty emptying the bladder

A narrow urinary opening may be the first sign that the disease has extended beyond the foreskin.

Lichen sclerosus and phimosis

Phimosis means that the foreskin cannot be retracted comfortably behind the glans.

A non-retractile foreskin is normal in young boys and does not automatically indicate disease. However, a previously retractable foreskin that becomes tight, particularly when accompanied by a white scarred ring is suspicious for lichen sclerosus.

Forceful stretching of a scarred foreskin is not recommended. Repeated tearing may cause additional inflammation and scarring.

Paraphimosis, where a retracted tight foreskin becomes trapped behind the glans, requires urgent medical attention.

How is lichen sclerosus diagnosed?

The diagnosis is often made from the history and characteristic appearance.

Assessment should include examination of:

  • The complete foreskin
  • Glans penis
  • Frenulum
  • Urinary opening
  • Palpable tissue beneath abnormal skin
  • Urinary stream and bladder emptying when relevant
  • Groin lymph nodes if cancer is suspected

Other conditions that can resemble lichen sclerosus include:

  • Fungal or bacterial balanitis
  • Irritant or allergic dermatitis
  • Psoriasis
  • Lichen planus
  • Zoon balanitis
  • Vitiligo
  • Genital warts
  • Penile intraepithelial neoplasia: PeIN
  • Squamous cell carcinoma

Diabetes testing may be appropriate in men with recurrent inflammation or other risk factors.

Is a biopsy always necessary?

Not every typical case requires a biopsy before treatment. However, biopsy is important when:

  • The diagnosis is uncertain
  • Treatment has not produced the expected response
  • An erosion or ulcer does not heal
  • There is a persistent red or thickened area
  • A lump or hardened area can be felt
  • The skin bleeds easily without an obvious cause
  • Pigmentation changes unexpectedly
  • Penile intraepithelial neoplasia or cancer is suspected

When circumcision is performed for suspected lichen sclerosus, the foreskin should usually be sent for pathological examination.

A biopsy should be taken from any suspicious persistent lesion rather than relying only on the appearance.

Medical management

The goals of medical treatment are to:

  • Suppress inflammation
  • Relieve discomfort and itching
  • Prevent further scarring
  • Preserve foreskin and urinary function where possible
  • Identify patients who require surgery or biopsy

General skin care

Helpful measures include:

  • Washing gently with water or a non-soap cleanser
  • Avoiding perfumed soaps, antiseptics and harsh products
  • Drying the glans and foreskin gently after urination
  • Applying a bland barrier ointment or emollient
  • Avoiding forceful foreskin retraction
  • Using adequate lubrication during sexual activity
  • Stopping smoking
  • Managing diabetes carefully
  • Addressing obesity or a buried penis where relevant

Good hygiene means gentle care. Repeated scrubbing or strong antiseptics can worsen inflamed genital skin.

Potent topical corticosteroids

A prescribed potent or ultrapotent topical corticosteroid is the usual first-line medical treatment.

Clobetasol propionate 0.05% ointment is commonly used in specialist practice. A typical initial course may involve a small amount applied to the affected skin once daily for one to three months, but the exact regimen should be determined by the treating doctor.

Patients should be shown:

  • Exactly where to apply the medication
  • How much to use
  • How long to continue
  • Whether treatment should be reduced gradually
  • When follow-up is required

When used correctly for a defined course, topical corticosteroids can reduce inflammation, soreness and early tightening. They cannot always reverse established dense scar tissue.

Possible steroid-related effects include irritation, secondary infection, skin thinning or visible small blood vessels, although these are uncommon with appropriate genital use and medical supervision.

Other topical treatments

Topical calcineurin inhibitors such as tacrolimus or pimecrolimus may occasionally be considered by a dermatologist or experienced specialist when corticosteroids are unsuitable.

They are not generally preferred over potent topical corticosteroids as initial treatment. They can cause burning or irritation, and persistent suspicious lesions must be biopsied rather than repeatedly treated empirically.

Antifungal or antibiotic medication is only useful when a secondary infection is actually present. It does not treat the underlying lichen sclerosus.

When should circumcision be considered?

Circumcision is an important and often definitive treatment for foreskin lichen sclerosus.

It should be considered when there is:

  • Established scarring phimosis
  • Painful or recurrent splitting
  • Difficulty with hygiene
  • Recurrent balanitis
  • Paraphimosis
  • Failure to respond adequately to a prescribed steroid course
  • Rapid recurrence after apparently successful medical treatment
  • Significant functional or sexual difficulty
  • Concern about premalignant or malignant change
  • A need to obtain tissue for diagnosis

Complete circumcision removes the diseased foreskin and eliminates the moist, urine-exposed environment beneath it. Many men experience long-term resolution when the disease is limited to the foreskin.

Partial circumcision or simply making a slit in the scarred foreskin is generally less reliable because affected skin remains and may scar again.

Will circumcision cure lichen sclerosus?

Circumcision is often highly effective when the condition is limited to the foreskin. However, it is not an absolute guarantee of cure.

Disease may persist or recur on the:

  • Glans
  • Coronal sulcus
  • Frenulum
  • Urinary opening
  • Urethra

Ongoing symptoms or abnormal skin after circumcision should therefore be reviewed rather than assumed to be normal postoperative scarring.

Circumcision appears to reduce the risk associated with chronic inflammation and phimosis, but it does not completely eliminate the future risk of penile cancer.

Surgery for meatal narrowing

Lichen sclerosus can scar the urinary opening, producing meatal stenosis.

Symptoms may include:

  • A thin urinary stream
  • Spraying or deflection
  • Prolonged urination
  • Straining
  • Discomfort
  • Incomplete emptying

Treatment may require a meatotomy or meatoplasty, in which the opening is enlarged and reconstructed.

Simple dilatation may provide temporary improvement but often does not control active scar disease. Medical treatment of the surrounding lichen sclerosus and continued surveillance may still be required.

What if the disease involves the urethra?

In some men, scarring extends from the meatus into the penile urethra and occasionally further towards the bulbar urethra.

Assessment may include:

  • Urinary flow-rate testing
  • Post-void residual ultrasound
  • Flexible cystoscopy
  • Retrograde urethrogram
  • Voiding cystourethrogram
  • Urethral ultrasound in selected cases

Short strictures may sometimes be managed endoscopically, but repeated dilatation or urethrotomy has a significant recurrence risk when active lichen sclerosus remains.

Longer or recurrent strictures may require urethroplasty. Oral lining tissue, usually buccal mucosa from the inside of the cheek, is commonly used for reconstruction.

The European Association of Urology recommends that genital skin should not be used as a graft for lichen-sclerosus-related urethral strictures, because the disease can affect the graft and recurrence rates are poor.

Complex cases are best managed by a urologist experienced in reconstructive urethral surgery.

Other surgical options

Depending on the extent of disease, specialist procedures may include:

  • Frenuloplasty in carefully selected cases without extensive LS
  • Complete circumcision
  • Meatotomy or meatoplasty
  • Excision or biopsy of suspicious lesions
  • Glans resurfacing when premalignant disease is present
  • Oral-mucosa graft urethroplasty
  • Staged urethral reconstruction
  • Perineal urethrostomy for severe or recurrent extensive stricture disease

The operation should be tailored to the location and activity of the condition. Preserving diseased genital skin simply to avoid circumcision may produce repeated scarring and further procedures.

Lichen sclerosus and penile cancer

Male genital lichen sclerosus is associated with squamous cell carcinoma of the penis and with penile intraepithelial neoplasia, which is a precancerous change.

Published studies have reported widely differing cancer rates among men with genital lichen sclerosus, from close to zero in some groups to approximately 12.5% in highly selected specialist series. Frequently quoted estimates place the risk at roughly 2–6%, but the precise lifetime risk for an individual man remains uncertain.

This does not mean that most men with lichen sclerosus will develop penile cancer. Penile cancer remains rare, and appropriate treatment of inflammation and phimosis is expected to reduce risk.

It is also reported that lichen sclerosus is found in a substantial proportion of penile cancer specimens. This association cannot be reversed to mean that the same proportion of men with lichen sclerosus will develop cancer.

Risk is likely to be greater when there is:

  • Long-standing uncontrolled inflammation
  • Severe phimosis
  • Persistent ulceration or thickening
  • Poor visibility of the glans
  • Cigarette smoking
  • Immune suppression
  • Coexisting penile intraepithelial neoplasia
  • Failure to attend follow-up

Warning signs that require prompt review

A man with current or previous lichen sclerosus should seek medical assessment for:

  • A persistent ulcer or sore
  • A new lump or firm area
  • Skin thickening
  • An irregular red or velvety patch
  • A warty or cauliflower-like growth
  • Unexplained bleeding
  • Offensive discharge
  • Increasing pain
  • A lesion that does not respond to prescribed steroid treatment
  • A new lump in the groin

These findings do not necessarily mean cancer, but they should not be treated repeatedly as thrush or simple inflammation without further investigation.

Follow-up and self-examination

Lichen sclerosus can recur, and cancer-related changes may develop many years after initial treatment.

Patients should become familiar with the normal appearance of their penis and perform regular self-examination. When possible, the entire glans, foreskin and urinary opening should be inspected.

Medical follow-up should be tailored to disease severity. More frequent review is appropriate during active treatment, after surgery or when urethral involvement is present. Once stable, periodic or annual review may be appropriate, together with lifelong self-monitoring.

Circumcised men should still report new or persistent abnormalities.

The outlook

When recognised early, male genital lichen sclerosus can often be controlled successfully with appropriate topical corticosteroid treatment, good skin care and follow-up.

Established scarring is less likely to resolve with medication alone. Circumcision is usually highly effective for disease confined to the foreskin, while meatal and urethral disease may require more specialised reconstruction.

The important message is not to ignore a foreskin that is becoming progressively white, scarred or tight. Early assessment may prevent painful erections, urinary obstruction and more complex surgery.

The bottom line

Balanitis xerotica obliterans is the older name for male genital lichen sclerosus involving the foreskin and glans.

It commonly presents with white or scarred skin, acquired phimosis, splitting, painful erections or urinary-stream changes. Potent prescribed topical corticosteroids are the first medical treatment for suitable early disease, while circumcision is often required for established phimosis, recurrent disease or failure of medical treatment.

Meatal or urethral involvement requires urological assessment and may need reconstructive surgery.

The risk of penile squamous cell carcinoma is small but real. Persistent thickening, ulceration, bleeding, a lump or a lesion that does not respond to treatment requires prompt examination and often biopsy.

This article provides general information and does not replace personalised medical assessment. Do not use potent topical corticosteroids on genital skin without appropriate medical advice.

So guys, if you cannot retract the foreskin and has the typical appearance discussed in this article, take the time to review with your GP to have this checked out. There is effective management for this which will also then reduce your risk for penile cancer. Do not vary your head in the send and ignore this, have it seen to and let your GP refer you to your local Brisbane urologist, Dr Jo Schoeman.

References and further reading

Enlarged Prostate (BPH): Understanding Prescription Combination Therapy

Benign prostatic hyperplasia (BPH), also called benign prostate enlargement, becomes more common as men get older. An enlarged prostate may narrow the urethra or affect the way the bladder works.

Possible symptoms include:

  • a slow or intermittent urinary stream
  • difficulty starting urination
  • straining to urinate
  • a feeling that the bladder has not emptied fully
  • urinary frequency or urgency
  • waking at night to urinate
  • dribbling after urination
  • urinary retention

These symptoms are not always caused by an enlarged prostate. Infection, overactive bladder, urethral narrowing, bladder stones, neurological conditions and prostate or bladder cancer can sometimes produce similar symptoms. An appropriate clinical assessment is therefore important before treatment is selected.

What treatments are available?

Management depends on symptom severity, prostate size, bladder emptying, general health and personal preferences. Options may include:

  • monitoring and lifestyle measures
  • prescription medicines
  • minimally invasive procedures
  • prostate surgery

No single option is best for every patient. A treatment that improves symptoms in one man may be unsuitable for another.

How prescription combination therapy works

For selected men, a doctor may prescribe two types of medicine together:

  1. An alpha blocker, such as tamsulosin, relaxes smooth muscle in the prostate and bladder neck. This may improve urine flow and symptoms relatively quickly, although response varies.
  2. A 5-alpha-reductase inhibitor, such as dutasteride or finasteride, alters the hormonal pathway involved in prostate growth. Over time, it may reduce prostate volume and lower the risk of urinary retention or BPH-related surgery in appropriately selected men.

These medicines are available only on prescription. They may be prescribed separately or, in some circumstances, in a fixed-dose combination. This article does not recommend a particular medicine or brand.

The prostate-reducing component acts gradually. Any benefit is generally assessed over months rather than days. Combination therapy is commonly considered as a longer-term treatment, but regular review remains important.

Who might be considered for combination therapy?

A doctor may consider combination treatment for a man who has moderate-to-severe urinary symptoms associated with a demonstrably enlarged prostate and an increased risk of BPH progression.

The decision may take account of:

  • how troublesome the symptoms are
  • prostate size and shape
  • PSA results, interpreted in clinical context
  • urinary flow rate
  • the amount of urine left in the bladder after voiding
  • previous urinary retention
  • the expected benefits, limitations and adverse effects of treatment
  • other illnesses and medicines
  • the patient’s preferences, including the importance of preserving sexual and ejaculatory function

Prostate size alone should not determine treatment. Some men with large prostates have few symptoms, while a smaller prostate can still cause obstruction because of its shape, a tight bladder neck or another condition.

Assessment before treatment

Depending on the individual, assessment may include:

  • a urinary, medical and medication history
  • a validated symptom questionnaire
  • physical examination, which may include a digital rectal examination
  • urine testing
  • PSA testing after discussion of its benefits and limitations
  • kidney-function blood tests
  • urinary flow measurement
  • ultrasound assessment of prostate size and post-void residual urine
  • a bladder diary
  • cystoscopy or urodynamic testing in selected cases

The purpose is to confirm the likely cause of the symptoms and identify complications or conditions that require a different approach.

Possible benefits and limitations

An alpha blocker may improve urine flow and some symptoms within days or weeks. It does not substantially shrink the prostate.

A 5-alpha-reductase inhibitor works more slowly. In men with prostate enlargement, it may reduce prostate volume and lower the long-term risk of acute urinary retention or BPH-related surgery. Not every patient will experience a worthwhile improvement.

Combination treatment may improve symptoms more than either medicine alone in appropriately selected patients, but it also exposes the patient to the adverse effects of both medicine classes. It controls BPH rather than permanently curing it. Symptoms may recur or progress, and a procedure may still be required.

Clinical-trial averages cannot predict an individual patient’s result. Benefits and harms should be reviewed with the prescribing doctor.

Possible adverse effects

Adverse effects differ between people. The Consumer Medicine Information supplied with the prescribed medicine should be read, and new or troublesome symptoms should be discussed with the prescriber or pharmacist.

Sexual and ejaculatory effects

Possible effects include:

  • reduced semen volume or absent ejaculation
  • semen passing backwards into the bladder
  • reduced sexual desire
  • difficulty achieving or maintaining an erection
  • changes in fertility or semen characteristics

Some sexual adverse effects have been reported to persist after a 5-alpha-reductase inhibitor is stopped, although their frequency, cause and predictors remain uncertain. Persistent symptoms deserve appropriate assessment.

Dizziness and low blood pressure

Alpha blockers may cause dizziness, light-headedness, weakness or, less commonly, fainting—particularly when standing up. The risk may be greater when treatment begins or when combined with other medicines that lower blood pressure. Patients who become dizzy should take care to avoid falls and seek medical advice.

Breast and other changes

5-alpha-reductase inhibitors may cause breast tenderness or enlargement. A breast lump, nipple discharge or persistent one-sided change requires medical assessment rather than being assumed to be a medicine effect.

Other reported adverse effects can include headache, tiredness, palpitations, nasal congestion, gastrointestinal discomfort, skin reactions, testicular symptoms and mood changes. The exact safety information depends on the medicine prescribed.

Seek urgent help

Urgent medical attention is appropriate for symptoms such as:

  • swelling of the face, tongue or throat, or difficulty breathing
  • collapse or fainting
  • a painful, prolonged erection
  • a severe blistering or peeling skin reaction
  • suicidal thoughts or severe psychological distress
  • inability to pass urine, especially with increasing lower abdominal pain

In Australia, call Triple Zero (000) in an emergency. Lifeline is available on 13 11 14 for crisis support. These services do not replace assessment by the treating clinician.

PSA monitoring

5-alpha-reductase inhibitors commonly lower PSA. This does not eliminate the possibility of prostate cancer.

A new PSA baseline may need to be established after treatment begins. Later results must be interpreted with knowledge that the patient is taking this type of medicine. A confirmed increase from the lowest PSA reached may require further assessment, even if the result falls within a laboratory’s usual reference range.

Patients should tell any clinician ordering or interpreting a PSA test about all current and recent prostate medicines.

Cataract or glaucoma surgery

Tamsulosin and some other alpha blockers are associated with intraoperative floppy iris syndrome, which may complicate cataract or glaucoma surgery.

Patients should tell their ophthalmologist about current or previous alpha-blocker use. They should not stop a prescribed medicine solely for an eye operation unless advised by the relevant treating clinicians, because stopping it may not remove the surgical risk.

Mood and persistent symptoms

Sexual, cognitive and mood symptoms have been reported during or after treatment with 5-alpha-reductase inhibitors. The evidence about persistent syndromes, their frequency and causation continues to evolve.

This uncertainty should be discussed without either assuming that persistent symptoms will occur or dismissing symptoms that a patient experiences. New depression, marked anxiety or sexual dysfunction should be reviewed. Suicidal thoughts require urgent assistance.

Monitoring treatment

Follow-up may include review of:

  • symptom response and quality of life
  • dizziness and postural blood pressure
  • sexual and ejaculatory function
  • mood changes
  • urinary flow and post-void residual urine
  • PSA results
  • kidney function when clinically indicated

Lack of early improvement does not necessarily mean the slower-acting component has failed. However, severe or worsening symptoms should not be managed by continuing medicine indefinitely without reassessment.

When might a procedure or surgery be considered?

A procedure may be discussed when there is:

  • recurrent or persistent urinary retention
  • catheter dependence
  • recurrent infection associated with poor bladder emptying
  • bladder stones
  • recurrent visible bleeding attributed to BPH
  • kidney or upper urinary tract effects from obstruction
  • a high or increasing post-void residual volume
  • persistent troublesome symptoms despite appropriate conservative treatment
  • unacceptable medicine adverse effects
  • a preference for a procedural option after informed discussion

Procedural choices include established operations and selected minimally invasive treatments. Suitability depends on prostate anatomy, bladder function, general health, bleeding risk, expected durability and the importance of preserving ejaculation. Each option has potential benefits, limitations and complications.

Questions to discuss with your doctor

  • What is the most likely cause of my urinary symptoms?
  • Is my prostate enlarged, and am I at risk of progression?
  • What are the reasonable alternatives, including observation, medicines and procedures?
  • How likely is each option to help in my circumstances?
  • What sexual, ejaculatory, blood-pressure and mood effects should I consider?
  • How will treatment affect the interpretation of my PSA?
  • When should treatment be reviewed or changed?
  • Which symptoms require urgent assessment?

The bottom line

Prescription combination therapy can be one option for selected men with bothersome urinary symptoms, prostate enlargement and a risk of BPH progression. It is not suitable for every urinary problem and does not guarantee that surgery will be avoided.

The choice should follow an individual assessment and a balanced discussion of expected benefit, possible harm, alternatives and the option of no immediate treatment. Do not start, stop or change a prescription medicine without advice from the prescribing clinician.

This article provides general educational information. It is not medical advice and does not promote or recommend a particular prescription medicine or brand. Treatment decisions should be made with an appropriately qualified health professional after individual assessment.

References and further reading


Superficial Bladder Cancer: Diagnosis, Treatment and the Risk of Progression

“Superficial bladder cancer” is an older term for cancer confined to the bladder lining or the tissue immediately beneath it. The preferred modern term is non–muscle-invasive bladder cancer, usually abbreviated to NMIBC.

Although these cancers have not invaded the bladder muscle, they do not all behave in the same way. Some are small, low-grade tumours with a relatively low risk of causing serious harm. Others, particularly high-grade T1 cancer and carcinoma in situ, can recur frequently and may progress into the bladder muscle.

Accurate staging and risk classification are therefore essential when deciding between surveillance, intravesical treatment and removal of the bladder.

What is non-muscle-invasive bladder cancer?

The bladder wall consists of several layers. Most bladder cancers begin in the urothelium, the specialised lining on the inside of the bladder.

NMIBC includes three main stages:

  • Ta: a papillary tumour growing from the bladder lining without invading the supporting tissue
  • T1: cancer that has invaded the connective tissue beneath the lining but has not reached the bladder muscle
  • Carcinoma in situ/CIS or Tis: a flat, usually high-grade cancer confined to the bladder lining

CIS can be difficult to see because it may look like a red or inflamed area rather than a typical bladder tumour. Despite being confined to the surface, CIS is biologically aggressive and requires active treatment.

Once cancer enters the bladder muscle, it becomes muscle-invasive bladder cancer—stage T2 or higher. This usually requires a different and more intensive treatment approach.

How common is superficial bladder cancer?

Approximately 70–75% of bladder cancers are non–muscle-invasive when first diagnosed. The remaining patients generally have muscle-invasive or metastatic disease at presentation.

Bladder cancer is considerably more common in men than women and occurs most frequently in people over 60. Women sometimes experience delays in diagnosis when blood in the urine is initially attributed to urinary infection.

Most bladder cancers are urothelial carcinomas. Less common types include squamous cell carcinoma, adenocarcinoma and small-cell or neuroendocrine carcinoma.

What symptoms can bladder cancer cause?

The most common presentation is visible blood in the urine, haematuria.

The urine may appear:

  • Pink
  • Red
  • Rust-coloured
  • Tea-coloured
  • Normal between episodes

The bleeding is often painless and may disappear for days or weeks. Its disappearance does not mean the underlying problem has resolved.

Other possible symptoms include:

  • Microscopic blood detected on a urine test
  • Urinary frequency
  • A sudden need to urinate
  • Burning or discomfort when passing urine
  • Recurrent symptoms resembling a urinary tract infection
  • Difficulty emptying the bladder
  • Pelvic discomfort

CIS may cause urinary urgency, frequency and burning without producing a large visible tumour.

Blood in the urine should always be investigated, particularly in an older adult or someone with a history of smoking. Infection, stones and benign prostate enlargement are common alternative explanations, but bladder and upper urinary tract cancers must be excluded.

What causes bladder cancer?

Bladder cancer develops when genetic damage causes cells in the bladder lining to grow abnormally. In many patients there is no single identifiable cause.

Cigarette smoking

Smoking is the most important preventable risk factor. Carcinogens from tobacco enter the bloodstream, are filtered by the kidneys and remain in contact with the bladder lining in the urine.

The risk increases with the amount and duration of smoking. Stopping smoking remains valuable even after diagnosis because continued smoking may increase the risk of recurrence and progression.

Occupational chemical exposure

Long-term exposure to certain aromatic amines and industrial chemicals can increase risk. Historically, higher-risk industries have included:

  • Dye and pigment manufacturing
  • Rubber and leather production
  • Painting
  • Printing
  • Metal processing
  • Petroleum and chemical industries

Modern workplace protections have reduced—but not eliminated—these exposures.

Other risk factors

Additional risk factors include:

  • Increasing age
  • Male sex
  • Previous pelvic radiotherapy
  • Previous cyclophosphamide chemotherapy
  • Chronic bladder irritation or inflammation
  • Long-term urinary catheterisation
  • Certain inherited cancer syndromes, particularly Lynch syndrome
  • A personal history of cancer elsewhere in the urinary tract

Bladder cancer is not generally considered hereditary, although familial and genetic risks exist in a minority of patients.

How is bladder cancer investigated?

Medical history and urine testing

Assessment begins with a history of the bleeding, urinary symptoms, smoking and occupational exposure. Urine testing may identify blood, infection or abnormal cells.

A negative urine test after an episode of visible haematuria does not remove the need for investigation.

Urine cytology

Urine cytology examines shed urinary cells under a microscope.

It is most useful for detecting:

  • High-grade urothelial cancer
  • Carcinoma in situ
  • Cancer elsewhere in the urinary tract

Cytology is less sensitive for low-grade tumours, so a negative result does not exclude bladder cancer.

Urinary molecular-marker tests may occasionally provide additional information, but they do not usually replace cystoscopy.

Imaging of the urinary tract

A CT urogram is commonly used to assess:

  • Kidneys
  • Renal pelvises
  • Ureters
  • Bladder
  • Enlarged lymph nodes or other abnormalities

An ultrasound may be appropriate for selected patients, particularly when CT contrast or radiation should be avoided. However, ultrasound cannot reliably exclude small bladder tumours or CIS.

Flexible cystoscopy

A flexible cystoscope is passed through the urethra under local anaesthetic to inspect the bladder directly.

If a suspicious lesion is found, the next step is generally a formal resection under anaesthesia.

Transurethral resection of bladder tumour: TURBT

TURBT is the central procedure for diagnosing and treating NMIBC.

A rigid telescope is passed through the urethra, and the visible tumour is removed using an electrical loop, bipolar instrument or other resection technique. Tissue is sent to a pathologist to determine:

  • Cancer type
  • Tumour grade
  • Depth of invasion
  • Whether bladder muscle is present in the specimen
  • Whether muscle invasion has occurred
  • Whether variant histology or lymphovascular invasion is present

A complete TURBT should remove all visible tumour where safely possible and include adequate sampling of the underlying bladder muscle.

Enhanced cystoscopy using blue-light fluorescence or narrow-band imaging may help identify small tumours or CIS in selected patients.

When is a second TURBT required?

A repeat resection, usually within approximately two to six weeks, may be recommended when:

  • The first resection was incomplete
  • No bladder muscle was present in the specimen, apart from selected clearly low-risk Ta tumours
  • The tumour is high-grade T1
  • There is uncertainty about staging
  • Residual tumour is suspected

Repeat TURBT may find residual cancer and occasionally identifies previously unrecognised muscle invasion. It can therefore materially change treatment.

Understanding low-, intermediate-, high- and very-high-risk disease

Treatment is based on more than the word “superficial.” Important risk factors include:

  • Ta, T1 or CIS stage
  • Low-grade or high-grade pathology
  • Number of tumours
  • Tumour size
  • First occurrence or recurrence
  • Frequency of previous recurrences
  • Presence of CIS
  • Depth and extent of T1 invasion
  • Variant histology
  • Lymphovascular invasion
  • Involvement of the prostatic urethra
  • Response to previous BCG treatment

Low-risk NMIBC

This usually involves a first, solitary, small, low-grade Ta tumour without CIS.

These cancers commonly recur but have a very low risk of progressing to muscle-invasive disease.

Intermediate-risk NMIBC

This is a broad group between low and high risk. It may include recurrent, multiple or larger low-grade tumours and selected other tumours without high-risk features.

The pattern and frequency of recurrence help determine treatment intensity.

High-risk NMIBC

High-risk disease includes most:

  • High-grade T1 tumours
  • Carcinoma in situ
  • High-grade Ta tumours with adverse features
  • Tumours with other aggressive pathological findings

These cancers have a meaningful risk of entering the bladder muscle and require more intensive treatment and surveillance.

Very-high-risk NMIBC

Very-high-risk disease may include combinations such as extensive high-grade T1 cancer with CIS, lymphovascular invasion, certain aggressive variant histologies or involvement of the prostatic urethra.

For these patients, early radical cystectomy may provide the best chance of cure.

Initial treatment after TURBT

Surveillance for selected low-risk disease

For a completely removed low-risk tumour, treatment may consist of:

  • TURBT
  • A single immediate dose of intravesical chemotherapy when safe
  • Follow-up cystoscopy

Small, recurrent low-grade tumours may sometimes be treated with office fulguration or carefully selected surveillance, depending on the patient and tumour history.

Intravesical treatment

“Intravesical” means that a medication is placed directly into the bladder through a catheter. The medicine is retained for a prescribed time and then drained or passed in the urine.

Because the treatment remains mainly inside the bladder, it generally causes fewer whole-body effects than intravenous chemotherapy.

The role of intravesical mitomycin C

Mitomycin C is a chemotherapy medicine that damages the DNA of rapidly dividing cancer cells.

A single immediate postoperative dose

A single dose may be placed into the bladder shortly after TURBT—preferably within 24 hours—when the procedure has been uncomplicated.

Its purpose is to destroy floating tumour cells and reduce the chance that they implant elsewhere in the bladder. It also treats microscopic tumour cells remaining at the resection site.

This treatment is particularly useful for low-risk tumours and selected intermediate-risk tumours.

Mitomycin should not be administered immediately when there is:

  • Suspected bladder perforation
  • A very deep or extensive resection
  • Significant ongoing bleeding
  • A need for continuous bladder irrigation
  • Concern that the drug could leak outside the bladder

A course of mitomycin

Patients with intermediate-risk disease may receive weekly mitomycin treatments followed by a variable maintenance schedule. The exact schedule depends on tumour characteristics, previous recurrence pattern and local protocol.

Side effects of mitomycin

Possible side effects include:

  • Burning when urinating
  • Urinary frequency and urgency
  • Bladder discomfort
  • Blood in the urine
  • Chemical cystitis
  • Skin irritation or a rash involving the hands or genital region
  • Reduced bladder capacity after repeated severe inflammation
  • Infection
  • Rare injury if the medication leaks outside the bladder

Patients should follow the treatment unit’s instructions regarding fluid intake, urine handling and washing after treatment.

The role of intravesical BCG

BCG, Bacillus Calmette–Guérin, is a live, weakened form of Mycobacterium bovis. It was originally developed as a tuberculosis vaccine but also stimulates a powerful immune response against bladder cancer cells.

BCG is generally the preferred bladder-preserving treatment for:

  • Carcinoma in situ
  • High-risk high-grade Ta cancer
  • High-grade T1 cancer after adequate resection
  • Selected recurrent or aggressive intermediate-risk tumours

How is BCG given?

The usual initial course consists of one bladder instillation each week for six weeks. This is called induction BCG.

Patients who respond may then receive maintenance BCG. For high-risk disease, treatment may continue intermittently for one to three years, depending on tolerance, availability and individual risk.

Maintenance therapy is important because induction BCG alone provides less durable protection against recurrence and progression.

Side effects of BCG

Common short-term effects include:

  • Burning when urinating
  • Frequency and urgency
  • Mild blood in the urine
  • Bladder discomfort
  • Fatigue
  • Low-grade fever
  • Flu-like symptoms

These effects usually settle within one or two days.

Less common but potentially serious complications include:

  • Severe bacterial urinary infection
  • Prostatitis
  • Epididymo-orchitis
  • Granulomatous inflammation
  • Joint inflammation
  • Hepatitis or pneumonitis
  • Systemic BCG infection or sepsis

A high or persistent fever, shaking chills, breathing difficulty, confusion or severe illness after BCG requires urgent medical assessment.

When should BCG be postponed or avoided?

BCG should not be given:

  • Within the early healing period after TURBT, generally the first two weeks
  • After traumatic catheterisation
  • When visible haematuria is present
  • During a symptomatic urinary tract infection
  • When bladder perforation is suspected
  • In some patients with significant immune suppression
  • When previous BCG caused a severe systemic reaction

BCG is handled differently from routine chemotherapy because it contains live bacteria. Patients must follow the treatment centre’s hygiene and urine-disposal instructions.

Mitomycin or BCG: which is better?

Neither treatment is best for every patient.

  • Low-risk disease: a single immediate chemotherapy instillation is usually sufficient after complete TURBT.
  • Intermediate-risk disease: a course of chemotherapy or one year of BCG may be considered according to recurrence and progression risk.
  • High-risk disease: induction and maintenance BCG is generally preferred when bladder preservation is appropriate.
  • Very-high-risk disease: early radical cystectomy should be discussed, although BCG may remain an option in carefully selected patients who understand the risk.

BCG is more effective than chemotherapy for preventing recurrence and progression in appropriately selected high-risk disease, particularly when maintenance BCG is completed. It also tends to cause more local and systemic side effects.

What is the chance of developing muscle-invasive cancer?

There is no single percentage that applies to every NMIBC patient.

Across all NMIBC categories, approximately 10–20% of patients may eventually develop muscle-invasive disease, but this average hides enormous differences between low- and high-risk tumours.

Using contemporary EAU risk categories, estimated five-year progression risks can range approximately from:

  • Around 1% or less for low-risk disease
  • Several per cent for intermediate-risk disease
  • Around 10% or higher for high-risk disease
  • Approximately 40% or more for very-high-risk disease

At ten years, the estimated risk in very-high-risk patients may exceed 50% without effective additional treatment. These figures are estimates from risk models and do not precisely predict an individual patient’s outcome. BCG, repeat resection, early cystectomy and other treatments can substantially change the risk.

Progression risk is particularly concerning with:

  • Persistent or recurrent high-grade T1 cancer
  • T1 cancer associated with CIS
  • Extensive or multifocal CIS
  • Deep invasion into the lamina propria
  • Lymphovascular invasion
  • Aggressive variant histology
  • Prostatic urethral involvement
  • Failure to respond to adequate BCG
  • Early high-grade recurrence following BCG

Recurrence and progression are different. A small low-grade Ta tumour may recur several times without becoming muscle invasive, while a high-grade T1 tumour may progress after relatively few visible recurrences.

What is BCG-unresponsive bladder cancer?

BCG-unresponsive disease is a specific high-risk situation in which high-grade cancer persists or returns despite an adequate course of BCG within a defined period.

Continuing the same BCG treatment in genuinely BCG-unresponsive disease is unlikely to provide meaningful benefit and could delay curative surgery.

For a patient fit enough for major surgery, radical cystectomy is generally the preferred oncological treatment for BCG-unresponsive high-risk NMIBC.

Alternative bladder-preserving treatments or clinical trials may be considered when a patient:

  • Is medically unfit for cystectomy
  • Declines cystectomy after informed discussion
  • Has a strong preference for bladder preservation and accepts the additional risk

However, the possibility of losing the optimal window for curative surgery must be discussed clearly.

When should removal of the bladder be considered?

Radical cystectomy means removing the bladder, nearby lymph nodes and certain adjacent organs, followed by creating a new way for urine to leave the body.

It may be considered for NMIBC when there is:

  • Very-high-risk NMIBC at initial diagnosis
  • Persistent high-grade T1 cancer after repeat TURBT
  • High-grade T1 cancer with CIS
  • Lymphovascular invasion
  • Aggressive variant histology, such as micropapillary, plasmacytoid or selected sarcomatoid differentiation
  • Extensive CIS that does not respond adequately to BCG
  • High-grade recurrence following adequate BCG
  • BCG-unresponsive disease
  • Tumour involvement of the prostatic urethra or ducts
  • Disease that cannot be completely controlled endoscopically
  • Frequent, extensive high-grade recurrences
  • Progression to muscle-invasive bladder cancer

Cystectomy may sound excessive for a cancer described as “superficial,” but high-grade T1 disease can already possess the biological ability to spread. Delaying surgery until muscle invasion or metastasis develops can reduce the chance of cure.

What does radical cystectomy involve?

In men, surgery commonly removes the:

  • Bladder
  • Prostate
  • Seminal vesicles
  • Pelvic lymph nodes

In women, surgery is tailored individually and may involve removal of the bladder, pelvic lymph nodes and selected reproductive organs. Organ-preserving approaches may be possible in carefully selected patients.

Urinary reconstruction options include:

  • Ileal conduit: urine drains through a short segment of bowel to a stoma and external bag
  • Orthotopic neobladder: bowel is used to create an internal reservoir connected to the urethra
  • Continent catheterisable reservoir: an internal pouch is emptied using a catheter through a small abdominal opening

The most appropriate option depends on cancer location, kidney function, bowel health, manual dexterity, general fitness and patient preference.

Radical cystectomy is major surgery. Potential effects on urinary, sexual and bowel function must be balanced against the danger of progression.

Why lifelong surveillance is important

NMIBC has a strong tendency to recur, even after apparently complete treatment. Follow-up commonly includes:

  • Regular cystoscopy
  • Urine cytology in higher-risk patients
  • Periodic upper urinary tract imaging
  • Biopsy or repeat TURBT when abnormalities are found
  • Monitoring for late treatment complications

Low-risk patients generally require less intensive surveillance. High-risk patients need frequent cystoscopy and cytology, particularly during the first two years, followed by long-term or lifelong monitoring.

The exact schedule should be tailored to the patient’s EAU risk group, pathology, treatment response and general health.

Can recurrence be prevented?

Not every recurrence can be prevented, but patients can improve their general and bladder health by:

  • Stopping smoking
  • Avoiding occupational carcinogen exposure
  • Completing recommended intravesical treatment
  • Attending every surveillance cystoscopy
  • Reporting recurrent blood in the urine promptly
  • Treating urinary infections appropriately
  • Maintaining good hydration unless medically restricted

Smoking cessation remains the most important modifiable step.

The bottom line

Most bladder cancers are diagnosed before they enter the bladder muscle, but the term “superficial” should not be mistaken for harmless.

Low-grade Ta tumours frequently recur but rarely progress. High-grade T1 cancer and CIS behave much more aggressively and require complete TURBT, appropriate intravesical therapy and close surveillance.

Mitomycin C is particularly useful for reducing recurrence after TURBT and treating selected low- or intermediate-risk disease. BCG is the main bladder-preserving treatment for high-risk NMIBC and CIS.

Radical cystectomy should be discussed early—not only after muscle invasion—in patients with very-high-risk features, persistent high-grade T1 cancer or BCG-unresponsive disease. For these patients, timely surgery may offer the best chance of cure.

This article provides general information and does not replace individual medical advice. Treatment should be based on formal pathology review, complete staging, medical fitness and multidisciplinary discussion.

References and further reading

So, if you are experiencing blood in your urine and have been identified by your GP as having a possible bladder cancer, come see your Urologist in Brisbane, Dr Jo Schoeman to discuss options with you.